
LHSAA Medical History Evaluation at a glance
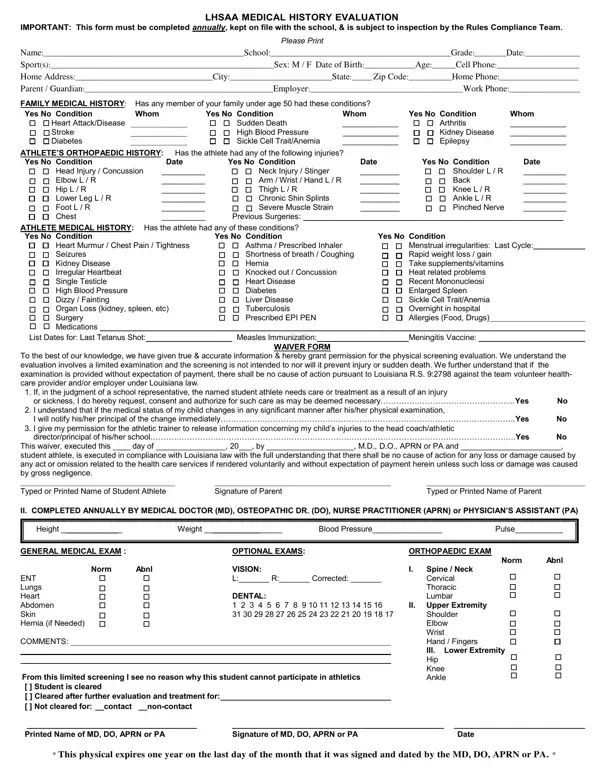
What it is: The LHSAA Medical History Evaluation has a family medical history, an athlete orthopaedic history, an athlete medical history, a parents' waiver form and a Health Care Provider section on page 2.
Where and when to file: This form must be completed annually, kept on file with the school, and is subject to inspection by the Rules Compliance Team.
A filled-in LHSAA Medical History Evaluation example: a parent fills out the athlete's history

How to fill out LHSAA Medical History Evaluation, box by box
Name, School, Grade, Date of Birth and Parent / Guardian

Please Print. Enter Name, School, Grade, Date, Sport(s), Sex, Date of Birth, Age, Cell Phone, Home Address, City, State, Zip Code, Home Phone, Parent / Guardian, Employer and Work Phone.
Family Medical History

Has any member of your family under age 50 had these conditions? Mark Yes or No for each condition and write Whom: Heart Attack/Disease, Sudden Death, Arthritis, Stroke, High Blood Pressure, Kidney Disease, Diabetes, Sickle Cell Trait/Anemia, Epilepsy.
Athlete Orthopaedic History

Has the athlete had any of these injuries? Mark Yes or No for each condition and enter the Date: Head Injury / Concussion, Neck Injury / Stinger, Shoulder L / R, Elbow L / R, Arm / Wrist / Hand L / R, Back, Hip L / R, Thigh L / R, Knee L / R, Lower Leg L / R, Chronic Shin Splints, Ankle L / R, Foot L / R, Severe Muscle Strain, Pinched Nerve, Chest. Then enter Previous Surgeries.
Athlete Medical History

Has the athlete had any of these conditions? Mark Yes or No for each condition: Heart Murmur / Chest Pain / Tightness, Asthma / Prescribed Inhaler, Menstrual irregularities: Last Cycle, Seizures, Shortness of breath / Coughing, Rapid weight loss / gain, Kidney Disease, Hernia, Take supplements/vitamins, Irregular Heartbeat, Knocked out / Concussion, Heat related problems, Single Testicle, Heart Disease, Recent Mononucleosis, High Blood Pressure, Diabetes, Enlarged Spleen, Dizzy / Fainting, Liver Disease, Sickle Cell Trait/Anemia, Organ Loss (kidney, spleen, etc), Tuberculosis, Overnight in hospital, Surgery, Prescribed EPI PEN, Allergies (Food, Drugs), Medications.
List Dates for Last Tetanus Shot, Measles Immunization and Meningitis Vaccine

List Dates for: Last Tetanus Shot, Measles Immunization, Meningitis Vaccine.
Parents' Waiver Form

1. If, in the judgment of a school representative, the named student-athlete needs care or treatment as a result of an injury or sickness, I do hereby request, consent and authorize for such care as may be deemed necessary: Yes No.
2. I understand that if the medical status of my child changes in any significant manner after his/her physical examination, I will notify his/her principal of the change immediately: Yes No.
3. I give my permission for the athletic trainer to release information concerning my child's injuries to the head coach/athletic director/principal of his/her school: Yes No.
4. By my signature in Signature of Parent, I am agreeing to allow my child's medical history/exam form and all eligibility forms to be reviewed by the LHSAA or its representative(s) or the associated medical personnel: Yes No. Then fill in Date Signed by Parent, Signature of Parent and Typed or Printed Name of Parent.
Name, Date of Birth, Age, School, Grade and Sport(s) on page 2
Enter Name, Date of Birth, Age, Date, School, Grade and Sport(s).
Height, Weight, Blood Pressure and Pulse

Enter Height, Weight, Blood Pressure and Pulse.
Completed annually by MD, DO, APRN or PA: General Medical Exam, Orthopaedic Exam and Medically eligible
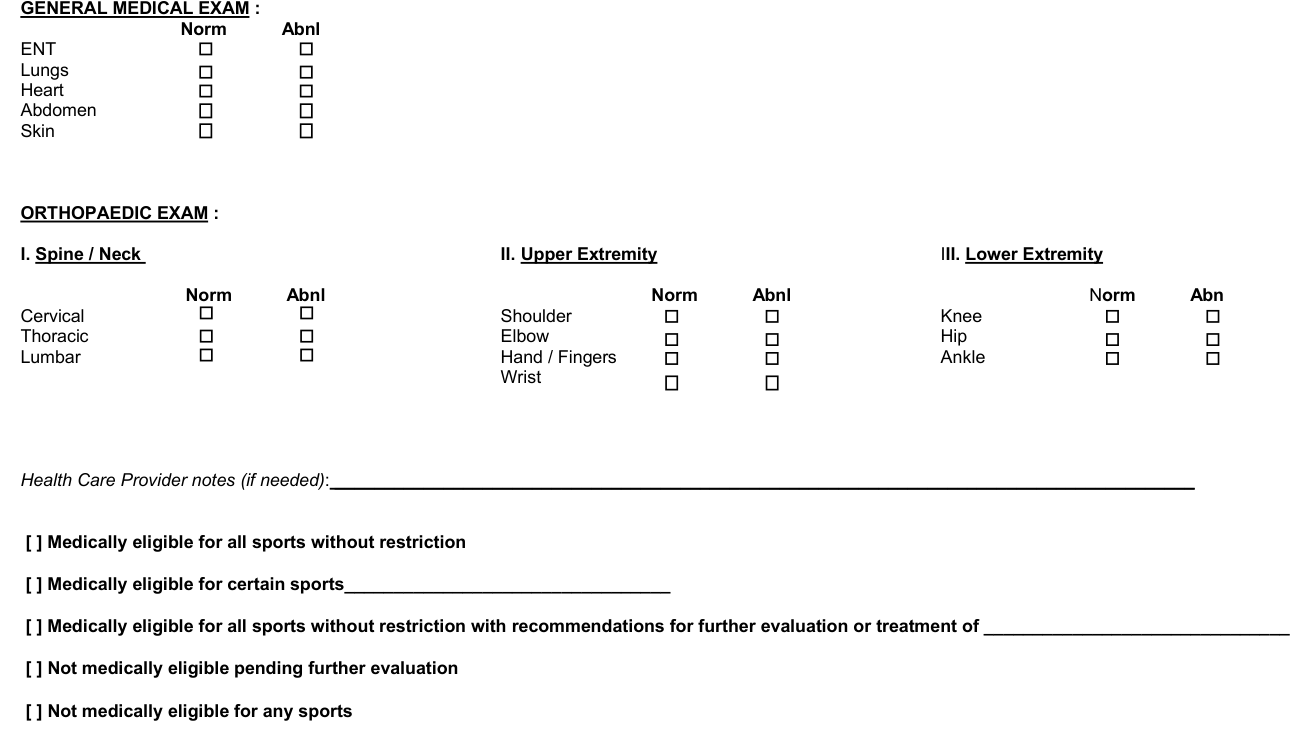
Section II is completed annually by Medical Doctor (MD), Osteopathic Dr. (DO), Nurse Practitioner (APRN) or Physician's Assistant (PA). General Medical Exam: for ENT, Lungs, Heart, Abdomen and Skin, mark Norm or Abnl. Orthopaedic Exam: for I. Spine / Neck (Cervical, Thoracic, Lumbar), II. Upper Extremity (Shoulder, Elbow, Hand / Fingers, Wrist) and III. Lower Extremity (Knee, Hip, Ankle), mark Norm or Abnl. Health Care Provider notes (if needed). Medically eligible for all sports without restriction; Medically eligible for certain sports; Medically eligible for all sports with recommendations for further evaluation or treatment of; Not medically eligible pending further evaluation; Not medically eligible for any sports. This recommendation is from a limited screening.
Printed Name, Signature and Date of Medical Examination

Enter Printed Name of MD, DO, APRN or PA, Signature of MD, DO, APRN or PA and Date of Medical Examination.
Common questions about LHSAA Medical History Evaluation
Is there a deadline?
This physical expires 13 months from the date it was signed and dated by the MD, DO, APRN or PA.
Sources
[1] LHSAA Medical History Evaluation (Revised 5/23), Louisiana High School Athletic Association (the Official source link on this page).