

Medical and Dental History at a glance
What it is: University of Washington School of Dentistry, Medical and Dental History: Name, Date, Chart and General Information.
Who signs: Write your signature on the Patient's Signature line and the Date.
The blank Medical and Dental History: print it and complete it by hand
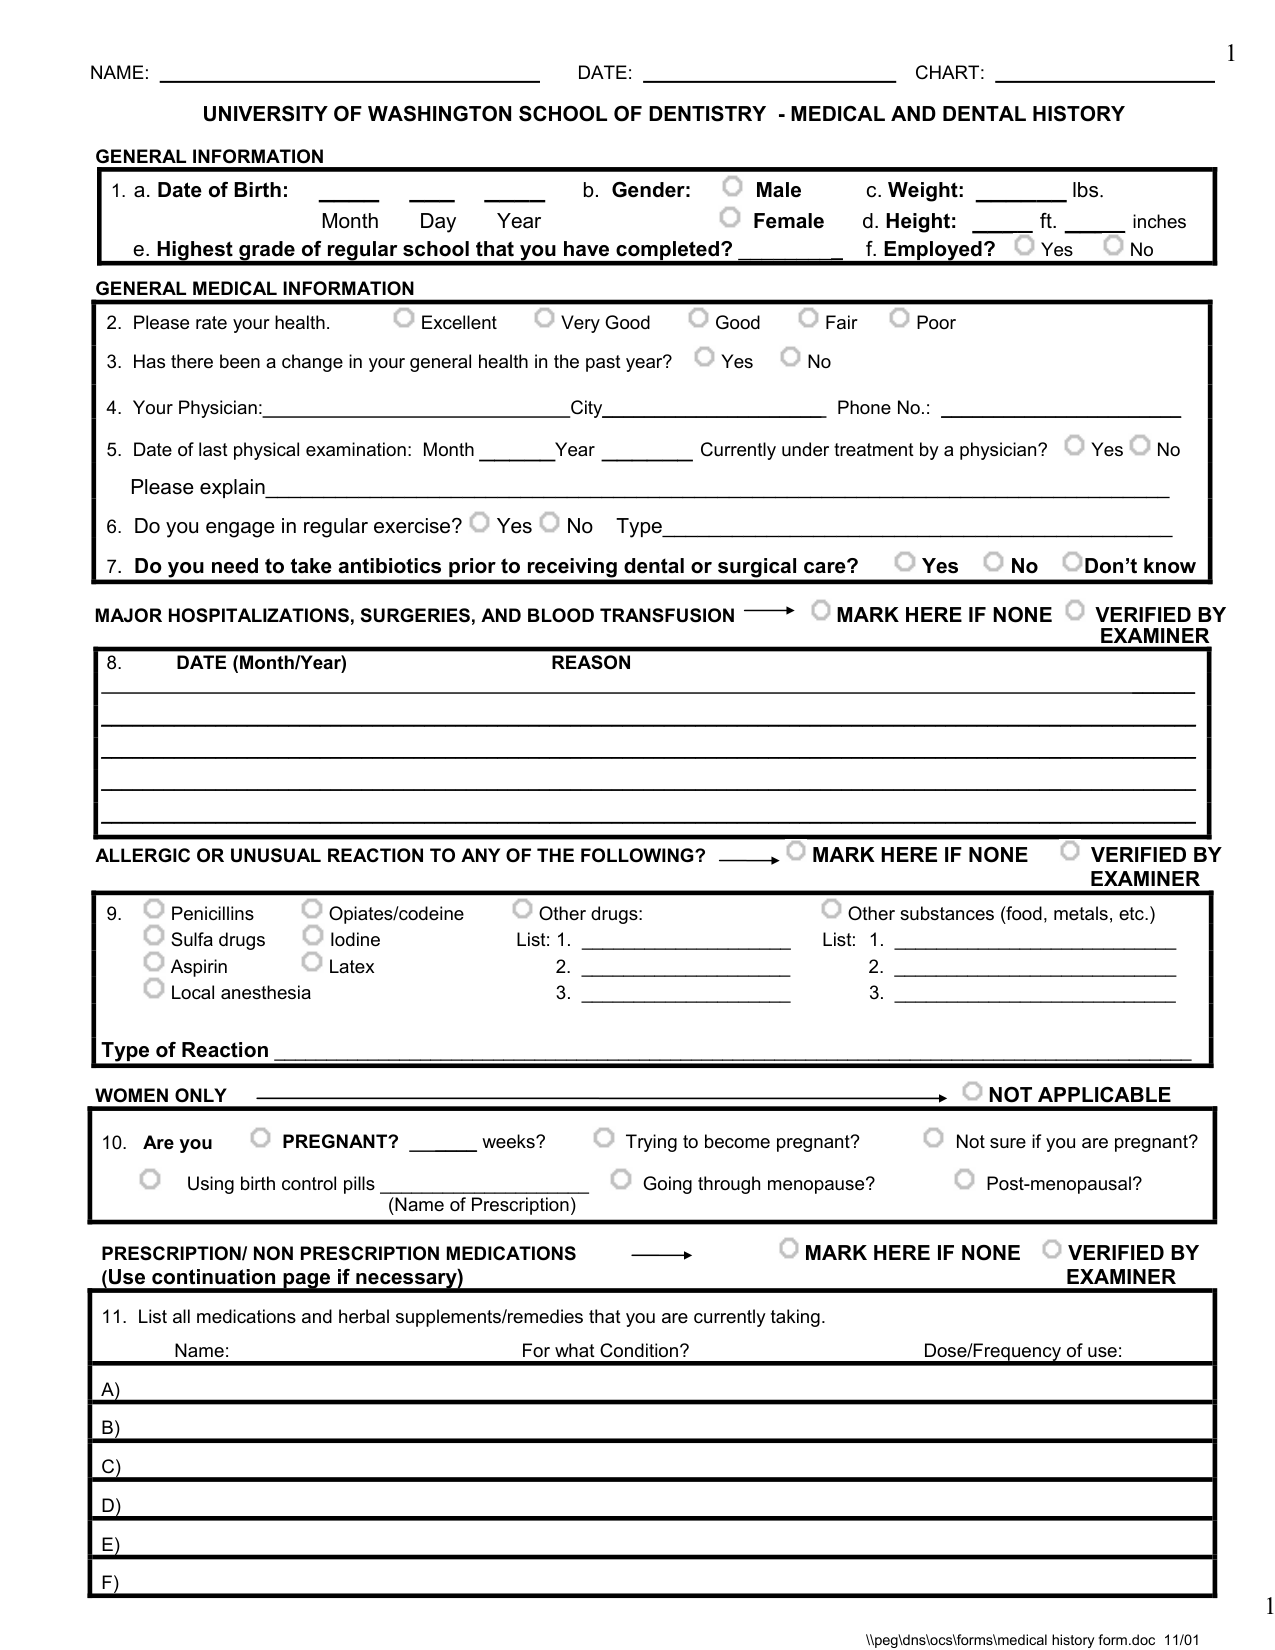
How to fill out Medical and Dental History, box by box
Date of Birth, Gender, Weight, Height, school and Employed
In box 1, write your date of birth (month, day, year), gender, weight in lbs., height in ft. and inches, and the highest grade of regular school that you have completed, and mark Yes or No for Employed.
Your health, Physician, exercise and antibiotics
In box 2, rate your health: Excellent, Very Good, Good, Fair or Poor.
In box 3, mark Yes or No: has there been a change in your general health in the past year?
In box 4, write your physician's City and Phone No.
In box 5, write the month and year of your date of last physical examination, mark Yes or No for currently under treatment by a physician, and on the Please explain line explain that treatment.
In box 6, mark Yes or No for regular exercise and write the Type.
In box 7, mark Yes, No or Don't know: do you need to take antibiotics prior to receiving dental or surgical care?
Major hospitalizations, allergic reactions, women only and medications
In box 8, write the date (month/year) and the reason for each major hospitalization, surgery and blood transfusion, or mark here if none.
In box 9, mark any allergic or unusual reaction to Penicillins, Aspirin, Local anesthesia, Sulfa drugs, Iodine, Opiates/codeine or Latex, list other drugs and other substances (food, metals, etc.) and write the Type of Reaction, or mark here if none.
Women only, in box 10: mark Are you pregnant (write the weeks), Trying to become pregnant, Not sure if you are pregnant, Using birth control pills (write the Name of Prescription), Going through menopause or Post-menopausal, or mark not applicable.
In box 11, list all medications and herbal supplements/remedies that you are currently taking, with the name, for what condition and the dose/frequency of use, and use the continuation page if necessary, or mark here if none.
Symptoms you experience, Weight loss and Weight gain
Mark symptom(s) that you now experience or have recently experienced.
Mark here if none, and leave verified by examiner to the examiner; for General, write the Lbs. for Weight loss and Weight gain, and over what time period.
Medical problems of parents, brothers/sisters or close relatives
Darken the circle beside medical problems that have been present in your parents, brothers/sisters, or close relatives: genetic (inherited) disease, liver/kidney disease, immune system disease, diabetes, bleeding disorders, tuberculosis, neurologic disease or other (include cancer).
Illnesses you currently have or have had in the past
Darken the circle for illnesses that you currently have or have had in the past, or mark here if none, leaving verified by examiner to the examiner: Cancer & Neoplastic Disease (Cancer, Leukemia/Lymphoma), Gastrointestinal Disorders (Acid-reflux/Heartburn, Ulcer/Gastritis, Irritable bowel syndrome/Colitis) and Genetic (inherited) Disease, and the other illnesses.
Caffeinated, alcoholic and carbonated beverages and street or recreational drugs
Mark the number of caffeinated beverages you drink in a day: 0, 1-2, 3-5 or 5+.
Mark the number of alcoholic beverages you drink in a week: 0, 1-2, 3-5, 6-10 or 10+.
Mark the number of carbonated beverages a day: 0, 1-2, 3-5 or 5+.
Mark No or Yes for currently using any street or recreational drugs and write the Type if Yes; mark here if none for all the beverages and other substances, and leave verified by examiner to the examiner.
Tobacco and dental history
Mark No or Yes for have you ever used tobacco; if yes, mark what type: Cigarette, Pipe/Cigar or Smokeless.
Mark No or Yes for do you currently use tobacco; if yes, write the average number of uses per day and for how many years. In box 16, darken the circle beside items that describe your past dental problems and dental care: regular dental care, occasional dental care, wisdom tooth extractions, orthodontics, gum disease (pyorrhea, gingivitis or periodontal disease), treatment for jaw trauma/fracture (write the Type), had an adverse reaction to dental treatment (describe it) and dental fears or anxiety. In box 17, rate your oral health in general.
Mark how good a job you feel you are doing in taking care of your oral health.
Oral problems of close relatives and Patient's Signature
Write the month and year of your date of last regular dental visit and the name and address of your dentist. In box 20, darken the circle beside oral problems that have been present in your parents, brothers/sisters, or close relatives.
Write your signature on the Patient's Signature line and the Date.
Sources
[1] University of Washington School of Dentistry Medical and Dental History form served on this page (no issuer file) (the Official source link on this page).