

Form PF-06-010 at a glance
What it is: The Louisiana DHH Nursing Facility Client Face Sheet for LOCET and the Level of Care Eligibility Tool for Nursing Facilities is a hardcopy version for use in the Nursing Facility Admission Process.
Who signs: Signature of Applicant / Informant: Date Signature of Intake Analyst: My signature indicates that I attest to the fact that I have conducted the LOCET interview recorded within this document, and that the Intake Analyst Registration number shown in Item J19.C.c. has been issued to me by the Office of Aging and Adult Services.
A filled-in Form PF-06-010 example: an intake analyst fills out the face sheet

How to fill out Form PF-06-010, box by box
A1. Client's Name, A.3.a. Social Security #, b. Medicaid #, c. Private Insurance #, d. Veteran's Administration #, e. Medicare #, B.2. DHH Region #, C.1. Gender, C.2. Birthdate, C.3. Race/Ethnicity and C.4. Marital Status
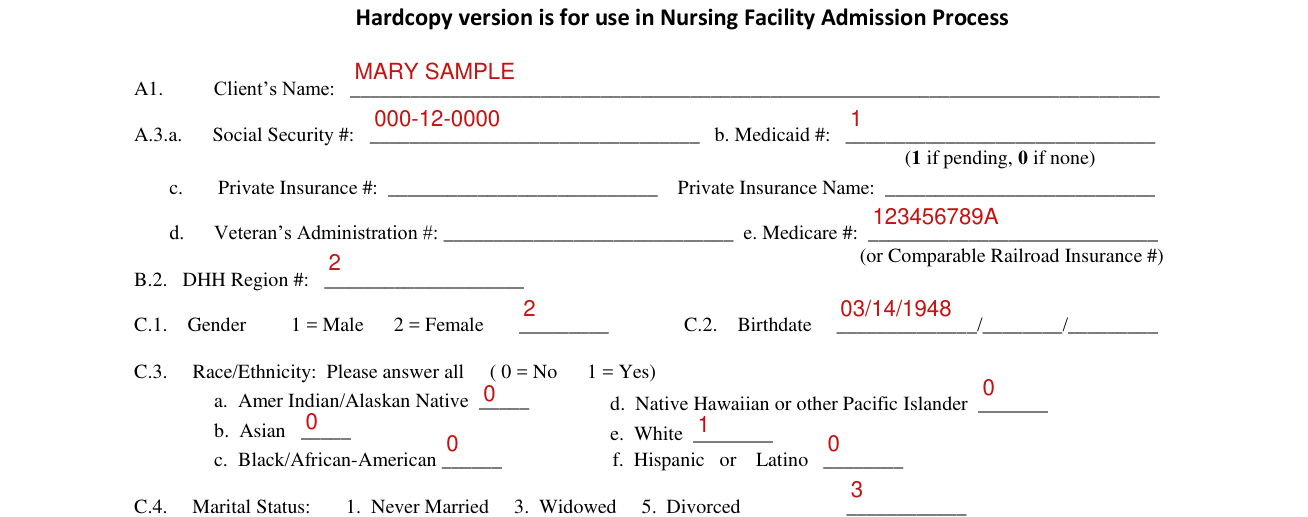
Enter the Client's Name (A1), the Social Security # (A.3.a), the Medicaid # (b; 1 if pending, 0 if none), the Private Insurance # and Private Insurance Name (c), the Veteran's Administration # (d) and the Medicare # (or Comparable Railroad Insurance #) (e), then the DHH Region # (B.2). For C.1. Gender, enter 1 = Male or 2 = Female, then enter the C.2. Birthdate. For C.3. Race/Ethnicity, please answer all with 0 = No or 1 = Yes: a. Amer Indian/Alaskan Native, b. Asian, c. Black/African-American, d. Native Hawaiian or other Pacific Islander, e. White and f. Hispanic or Latino. For C.4. Marital Status, enter 1. Never Married, 2. Married, 3. Widowed, 4. Separated, 5. Divorced or 6. Other.
Home Address, Address 2, City, State, Zip, Home Tel, Facility Name if known and Parish
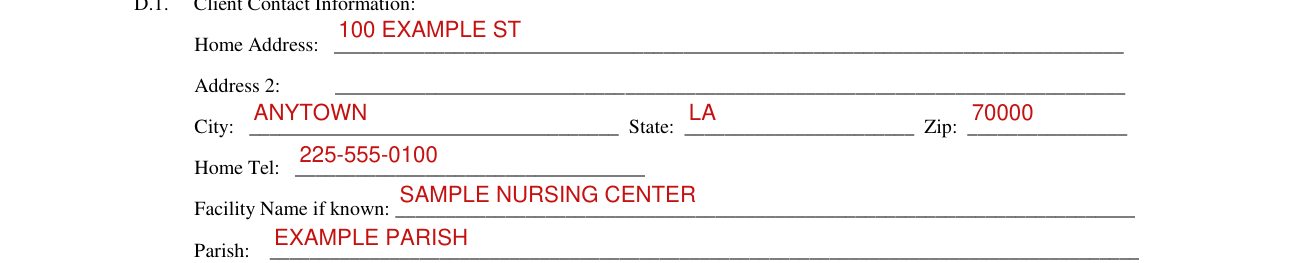
Enter the Home Address, Address 2, City, State and Zip.
Enter the Home Tel, the Facility Name if known and the Parish.
Mailing Address (if different from Home Address)

Under Mailing Address (if different from Home Address), enter the Name, Address 1, Address 2, City, State and Zip; leave this section blank if same as Home Address.
D.4. Other Contact Information

Under D.4. Other Contact Information, enter the Type of Other Contact as 1. Personal Representative, 2. Tutor, 3. Curator, 4. Power of Attorney or 5. Other (specify).
Enter the Name, Address, Address 2, City, State, Zip and Telephone.
Applicant Name and Last 4 digits of Applicant SSN

Enter the Applicant Name and the Last 4 digits of Applicant SSN.
SECTION A. SETTING THE STAGE

SECTION A. SETTING THE STAGE 1. The intake analyst will discuss the eligibility determination process/issues generally with the informant, then read the statement to the informant and ask if he/she understands, clarify any misunderstandings, and finally, select the answer given. "I (informant) understand that the purpose of this interview is to determine if the person being assessed (applicant) meets medical eligibility criteria for publicly funded long-term care services, and that I am expected to provide objective and accurate information about the applicant to assist in this determination." 2. "The following issued have been explained to me:
b. The information I provide will be used to determine medical eligibility for long-term care services funded through the Louisiana Department of Health and Hospitals. 0. No 1. Yes
c. The results of this interview, and information about how to appeal the results, will be provided in writing to the applicant. 0. No 1. Yes
d. The Louisiana Department of Health and Hospitals will conduct in-person interviews on a random sample of individuals who have applied to assess the accuracy of the information provided. 0. No 1. Yes
e. All program requirements must be met for eligibility to any particular program." 0. No 1. Yes
3. Informant indicates that eligibility determination process/issues have been adequately explained: 0. No 1. Yes **ACS/RO Users - SKIP TO SECTION EE
Signature of Applicant / Informant: Date
SECTION EE. Initial Call and LOCET Type

SECTION EE. Initial Call and LOCET Type 1. LOCET Initiated by: 1 = Applicant
2. Date/Time LOCET Initiated: : Type of LOCET : 1. Initial Determination
SECTION FF. Program Choice 1.h. Client chooses Nursing Facility Admission: 0=NO 1=YES
SECTION GG. Diagnoses
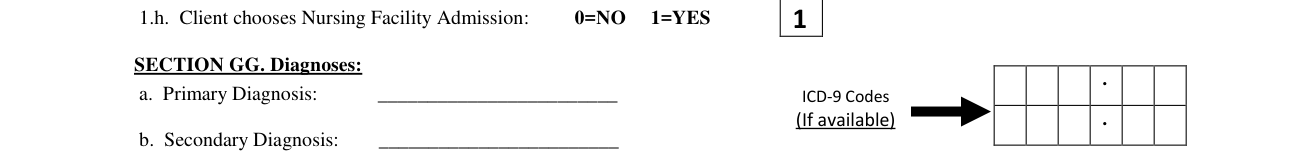
SECTION GG. Diagnoses: a. Primary Diagnosis: b. Secondary Diagnosis: ICD-9 Codes (If available)
SECTION B. Items/information to collect at beginning of interview process

SECTION B. Items/information to collect at beginning of interview process 4. Relationship of informant to applicant (select only one): 0. Self (Skip to Item B.7) 5. Hospital discharge planner 1. Spouse 6. Nursing Home admissions staff 2. Child or child-in-law 7. Other health care professional. Specify. 3. Other relative 4. Friend/neighbor 8. Other. Please specify.
Items to be filled out by intake analyst after completing LOCET form

Items to be filled out by intake analyst after completing LOCET form: J19A. How many minutes did this contact and interview take? J19B. Date LOCET completed J19C.b.
J19C.a. Signature of Intake Analyst
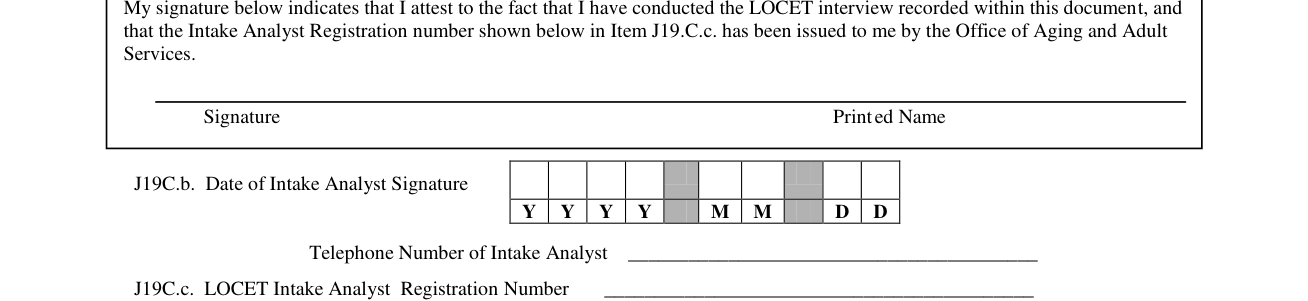
Date of Intake Analyst Signature Telephone Number of Intake Analyst J19C.a. Signature Printed Name J19C.c. LOCET Intake Analyst Registration Number
Sources
[1] OAAS PF-06-010 (Revised 05/10/2010), Louisiana DHH Nursing Facility Client Face Sheet for LOCET and Level of Care Eligibility Tool for Nursing Facilities, as served (the Official source link on this page).
