


Lost Wages/Earnings Claim Form at a glance
What it is: The Lost Wages/Earnings Claim Form is the form for Lost Wage Claims.
Who signs: Sign on Claimant Signature, and fill in the Date and the Print Name.
An innocent victim of violent crime who either physically or mentally is unable to immediately return to work due to the crime may be eligible; the victim must have had gainful employment immediately prior to the crime, have an offer of employment, or be a seasonal employee.
A parent/guardian who must miss work to take a minor or dependent to a medical or mental health provider due to the dependent being an innocent victim of a violent crime or whose dependent was critically injured due to being an innocent victim of a violent crime and must be cared for by the parent/guardian may be eligible.
What to bring and attach to Lost Wages/Earnings Claim Form
Employment Verification Form (filled out by employer, unless the victim is self-employed).
Lost Wages/Earnings Claim Form (filled out by victim/claimant).
Claim Form for Disability Verification: it must be submitted when more than one week of work is missed, must be completed and signed by the victim's doctor, and Disability Dates MUST be filled in.
Proof of income: two or three payroll check stubs for the periods immediately prior to the crime; if payroll check stubs are not possible, submit a copy of the previous year's federal income tax return; if the claimant was self-employed, a copy of the most recent tax return prior to the crime date must be submitted.
Proof of any disability income.
If lost wages reimbursement is being claimed to take a child to a medical or mental health provider, paperwork documenting the visit(s) must be attached.
A filled-in Lost Wages/Earnings Claim Form example: a victim claims three weeks of lost wages

How to fill out Lost Wages/Earnings Claim Form, box by box
CVR number, victim, claimant and claim investigator

Fill in the CVR NUMBER, the Victim Name, the Claimant Name, and Your claim investigator with Phone #.
Who is claiming lost wage reimbursement

Mark The Victim or The Parent/Guardian under Who is Claiming Lost Wage Reimbursement?
Answer the following questions about lost wages/earnings
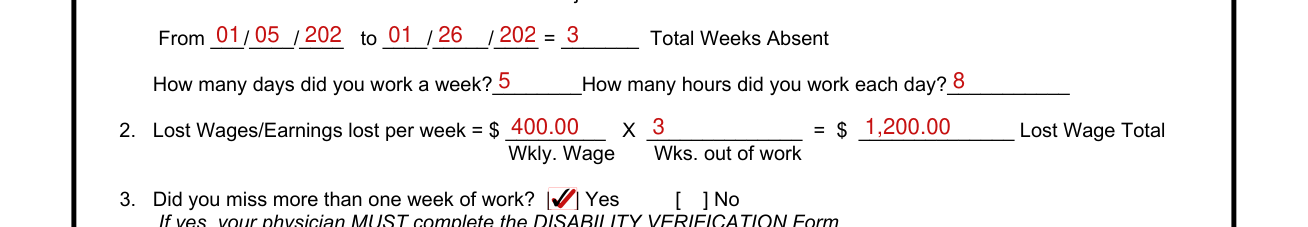
1. Fill in the Dates absent from work due to crime-related injuries: From to, the Total Weeks Absent, How many days did you work a week and How many hours did you work each day. 2. Fill in Lost Wages/Earnings lost per week = $ X = $ with the Wkly. Wage, the Wks. out of work and the Lost Wage Total. 3. Did you miss more than one week of work? Mark Yes or No. If you missed more than one week of work, you must have your physician complete the attached DISABILITY VERIFICATION form and attach it to the claim form when complete. Otherwise, only one week can be reimbursed.
Wages/earnings covered by other sources
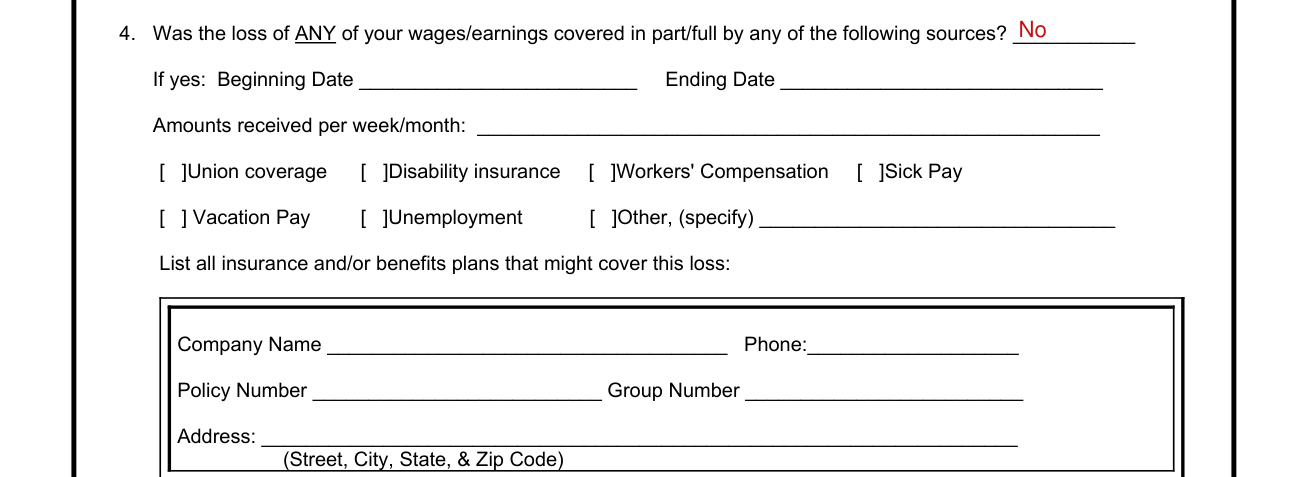
Was the loss of ANY of your wages/earnings covered in part/full by any of the following sources? If yes, fill in the Beginning Date, the Ending Date and the Amounts received per week/month.
Mark Union coverage, Disability insurance, Workers' Compensation, Sick Pay, Vacation Pay, Unemployment or Other, (specify), and list all insurance and/or benefits plans that might cover this loss with the Company Name, Phone, Policy Number, Group Number and Address (Street, City, State, & Zip Code).
If any type of coverage is available, you must apply for those benefits before filing with the CVR program.
Claimant Signature, Date and Print Name
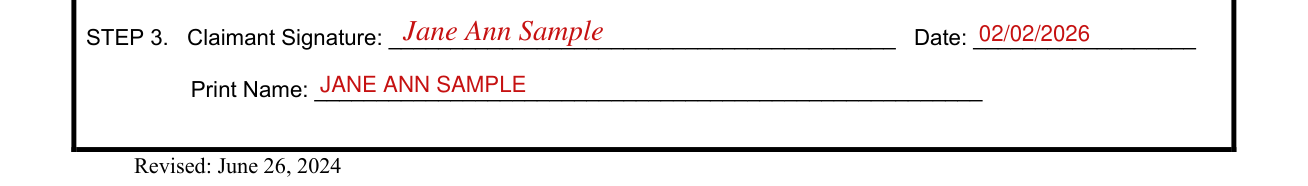
Sign on Claimant Signature, and fill in the Date and the Print Name.
More rules for Lost Wages/Earnings Claim Form
The CVR Board does NOT guarantee full payment of your lost wages.
If your situation is different
You are self-employed
If you are self-employed, you must submit a copy of your tax return from the year prior to the crime incident and any contracts, bids, estimates, or other documents which might help verify your earnings and attach them to this claim form.
You are not self-employed
If you are not self-employed, you must also include 3-4 pay stubs or your last tax return and/or W-2 with your claim.
Your employer completes the EMPLOYMENT VERIFICATION FORM
Have employer complete the EMPLOYMENT VERIFICATION FORM. 1) Ask the victim's employer to complete and return this form to you. 2) Give completed form to your claim investigator.
EMPLOYER INSTRUCTIONS: 1) A claim is being made for wages lost as a result of an injury of the victim referenced to the left, and caused by a crime on the date shown. 2) Complete this form, verifying the actual earnings lost and return to the claimant.
Your doctor completes the CLAIM FORM FOR DISABILITY VERIFICATION
1) Have the victim's doctor or dentist complete this CLAIM FORM FOR DISABILITY VERIFICATION and return it to you. 2) Attach the completed form to your claim. 3) Give to your claim investigator.
Only a surgeon, medical doctor, oral surgeon, psychiatrist, or an ophthalmologist may determine disability.
PROVIDERS: Please fully complete this form on behalf of victim and return to victim/claimant. Note: You may attach additional remarks or write on the back of this form.
Sources
[1] Lost Wage Claims, Lost Wages/Earnings Claim Form (Revised June 26, 2024), Louisiana Crime Victims Reparations Board (the Official source link on this page).