

Form M11Q at a glance
What it is: This form is the Medical Request for Home Care.
Who signs: The M-11Q must be signed by a NY State licensed physician.
Provide the Eight Helpful Hints sheet (HCSP-712b 12/09/2014) to the physician filling out the Medical Request for Home Care (M-11Q).
A filled-in Form M11Q example: a physician completes page 1
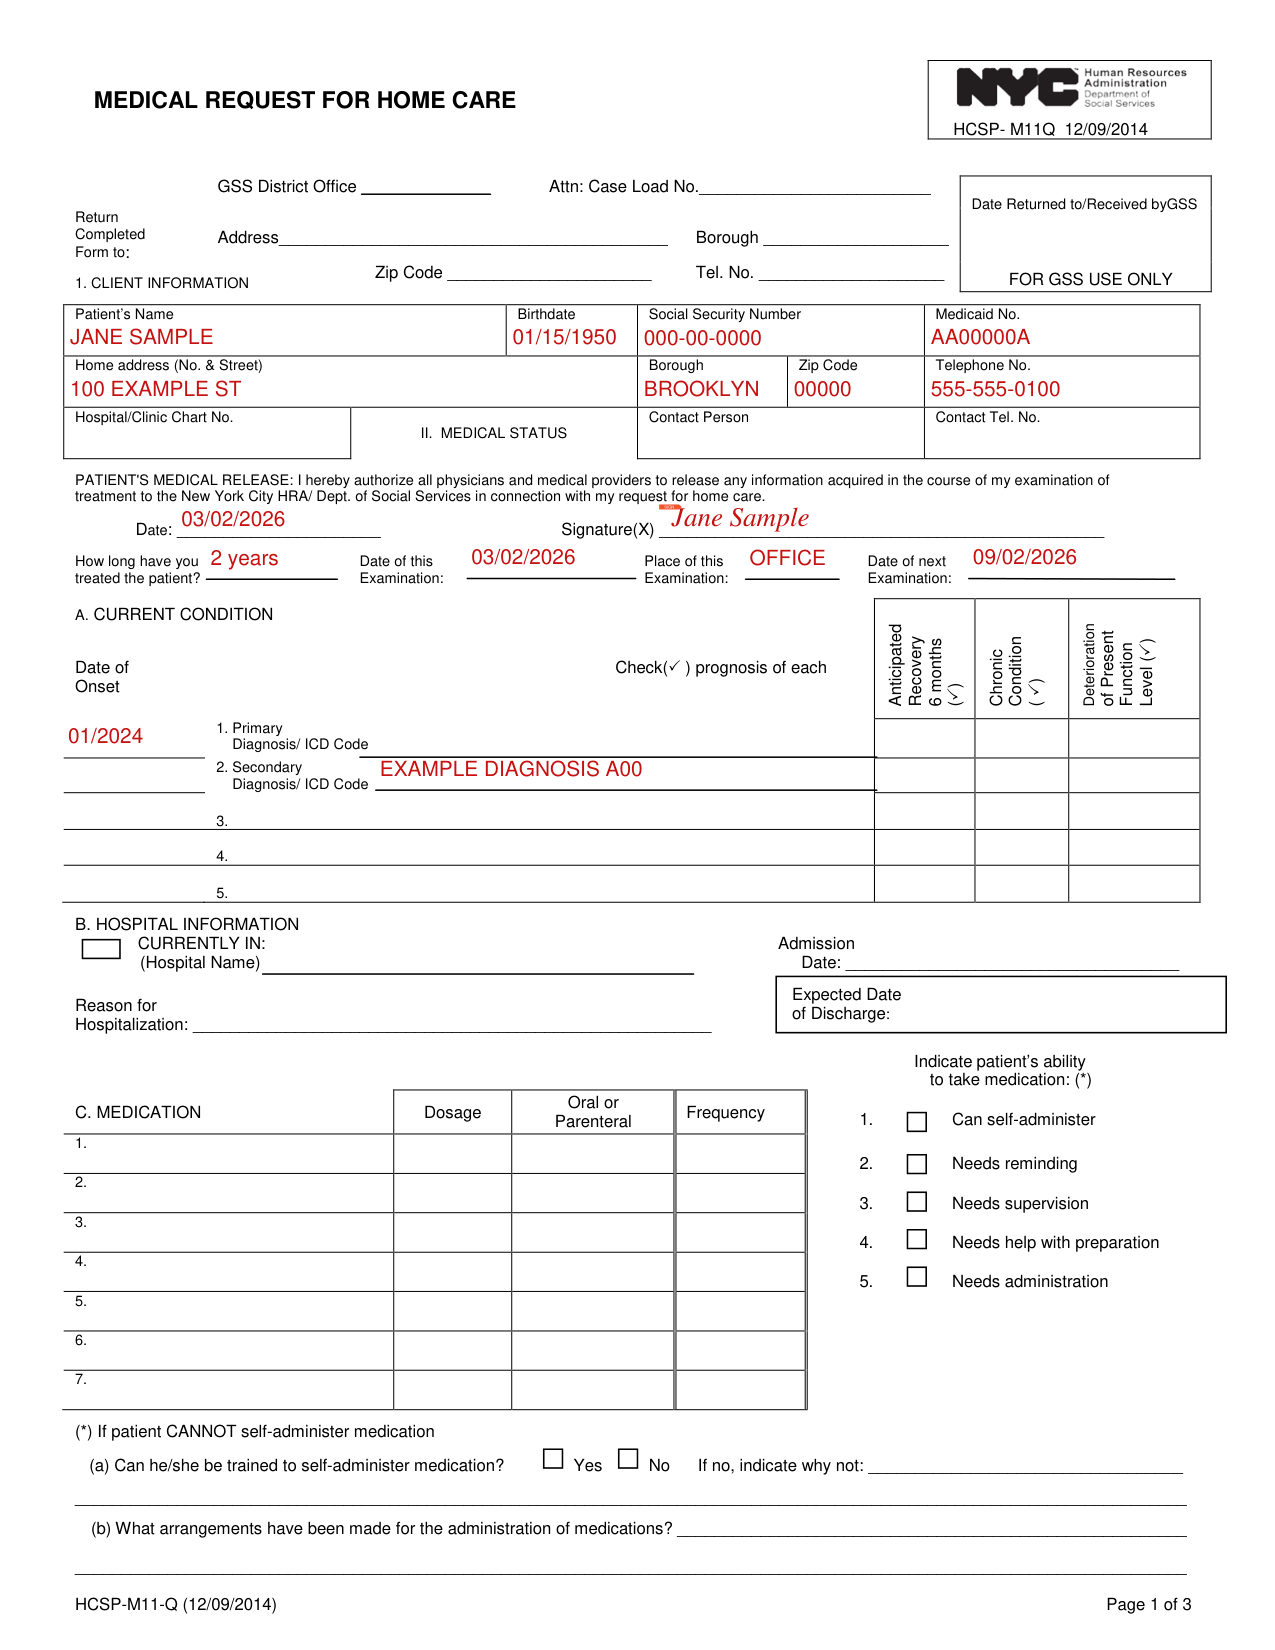
How to fill out Form M11Q, box by box
Client information
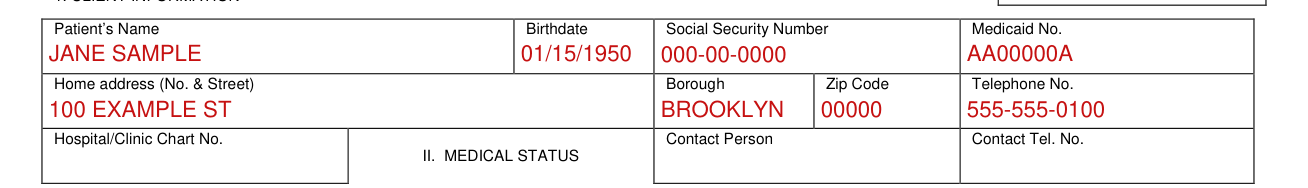
The client's name, address and Social Security number must be provided.
Under 1. CLIENT INFORMATION, enter the Patient's Name, Birthdate, Social Security Number, Medicaid No., Home address (No. & Street), Borough, Zip Code, Telephone No., Hospital/Clinic Chart No., Contact Person and Contact Tel. No.
Medical release and medical status

In the PATIENT'S MEDICAL RELEASE, the patient authorizes all physicians and medical providers to release any information acquired in the course of examination of treatment to the New York City HRA/ Dept. of Social Services in connection with the request for home care; the patient fills in the Date and signs the Signature(X).
Under II. MEDICAL STATUS, fill in How long have you treated the patient?, the Date of this Examination, the Place of this Examination and the Date of next Examination.
The date of the examination must be provided.
Current condition

Under A. CURRENT CONDITION, enter the Date of Onset, the 1. Primary Diagnosis/ ICD Code and the 2. Secondary Diagnosis/ ICD Code, and Check ( ) prognosis of each: Anticipated Recovery 6 months (), Chronic Condition or Deterioration of Present Function Level ().
Hospital information
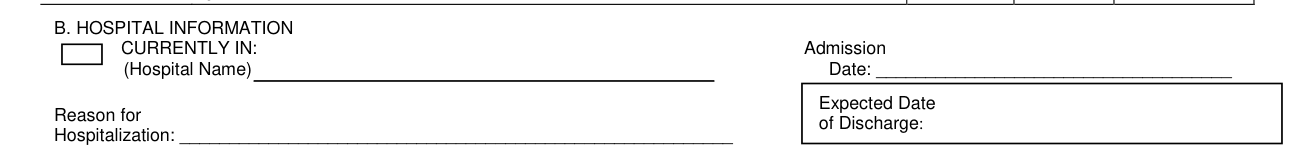
Under B. HOSPITAL INFORMATION, if the patient is CURRENTLY IN a hospital, enter the Hospital Name, Admission Date, Reason for Hospitalization and Expected Date of Discharge.
Medication
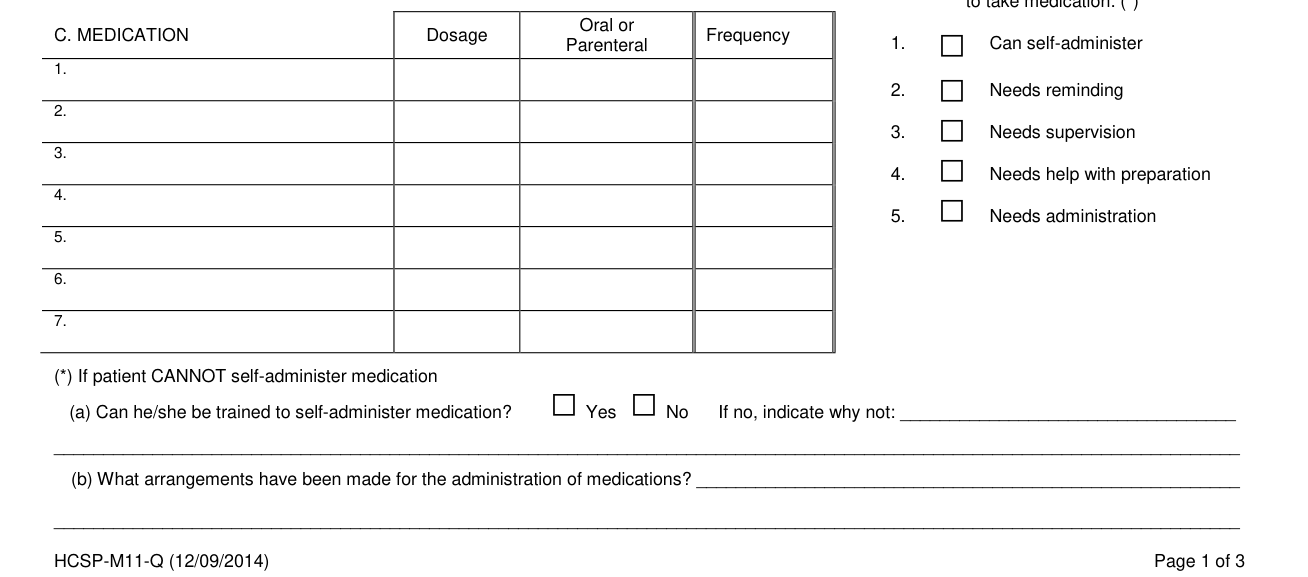
Under C. MEDICATION, list each medication with its Dosage, Oral or Parenteral and Frequency, and Indicate patient's ability to take medication (*): Can self-administer, Needs reminding, Needs supervision, Needs help with preparation or Needs administration.
(*) If patient CANNOT self-administer medication: Can he/she be trained to self-administer medication? Yes No If no, indicate why not. What arrangements have been made for the administration of medications?
Medical treatment
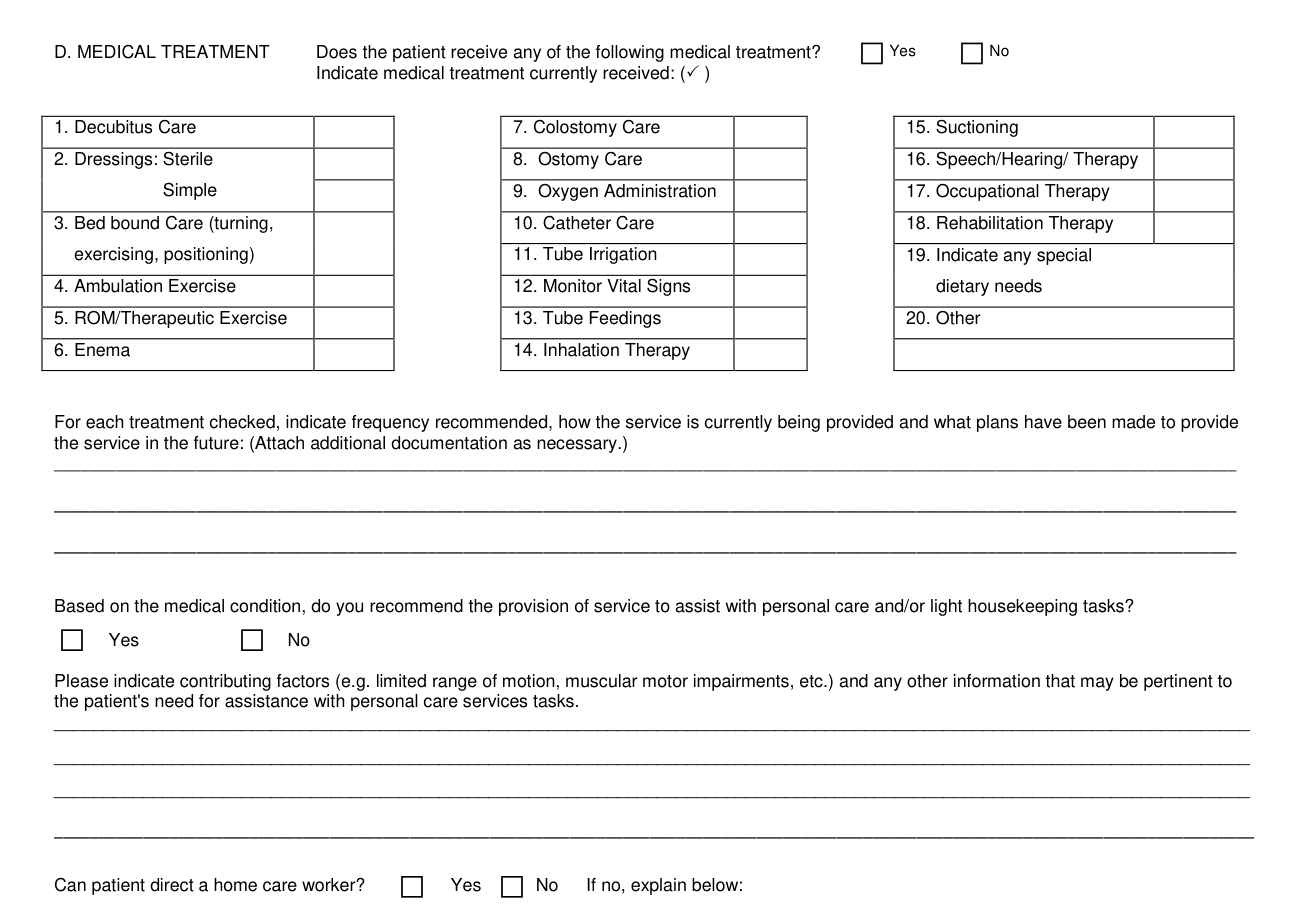
Under D. MEDICAL TREATMENT, does the patient receive any of the following medical treatment? Yes No Indicate medical treatment currently received.
Yes No 1. Decubitus Care, Dressings: Sterile Simple, Bed bound Care (turning, exercising, positioning), Ambulation Exercise, ROM/Therapeutic Exercise, Enema, Colostomy Care, Ostomy Care, Oxygen Administration, Catheter Care, Tube Irrigation, Monitor Vital Signs, Tube Feedings, Inhalation Therapy, Suctioning, Speech/Hearing/ Therapy, Occupational Therapy, Rehabilitation Therapy, Indicate any special dietary needs and Other.
For each treatment checked, indicate frequency recommended, how the service is currently being provided and what plans have been made to provide the service in the future (Attach additional documentation as necessary.).
Based on the medical condition, do you recommend the provision of service to assist with personal care and/or light housekeeping tasks? Yes No Please indicate contributing factors (e.g. limited range of motion, muscular motor impairments, etc.) and any other information that may be pertinent to the patient's need for assistance with personal care services tasks.
Can patient direct a home care worker? Yes No If no, explain.
Equipment and supplies

Under E. EQUIPMENT/SUPPLIES, Please indicate which equipment/supplies the client has, needs or has been ordered. If any needed equipment was not ordered, what other plans have been made to meet this need?
Referrals

Under F. REFERRALS, has a referral been made to any of these agencies: Certified Home Health Agency, Hospital-Based Home Care Agency, Hospice, a Health Related Facility (HRF), a Skilled Nursing Facility (SNF) or the Lombardi Program? Yes No *IDENTITY AGENCY SERVICE STATUS OF SERVICE REFERRAL DATE
Additional comments
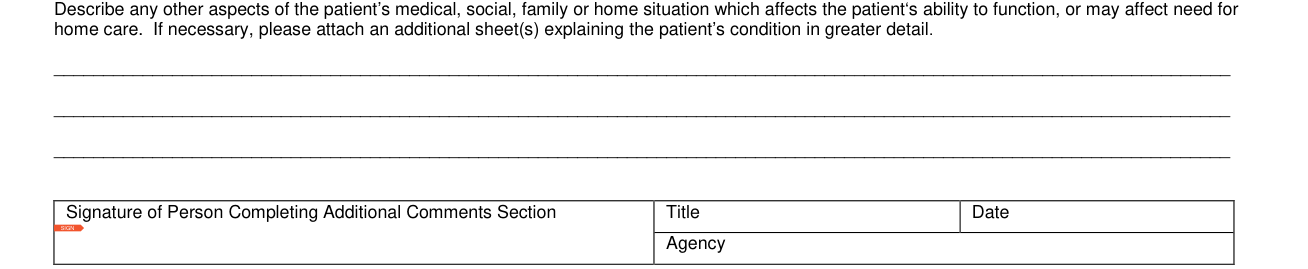
Under G. ADDITIONAL COMMENTS, describe any other aspects of the patient's medical, social, family or home situation which affects the patient's ability to function, or may affect need for home care. If necessary, please attach an additional sheet(s) explaining the patient's condition in greater detail. Signature of Person Completing Additional Comments Section, Title, Date and Agency.
Physician's certification
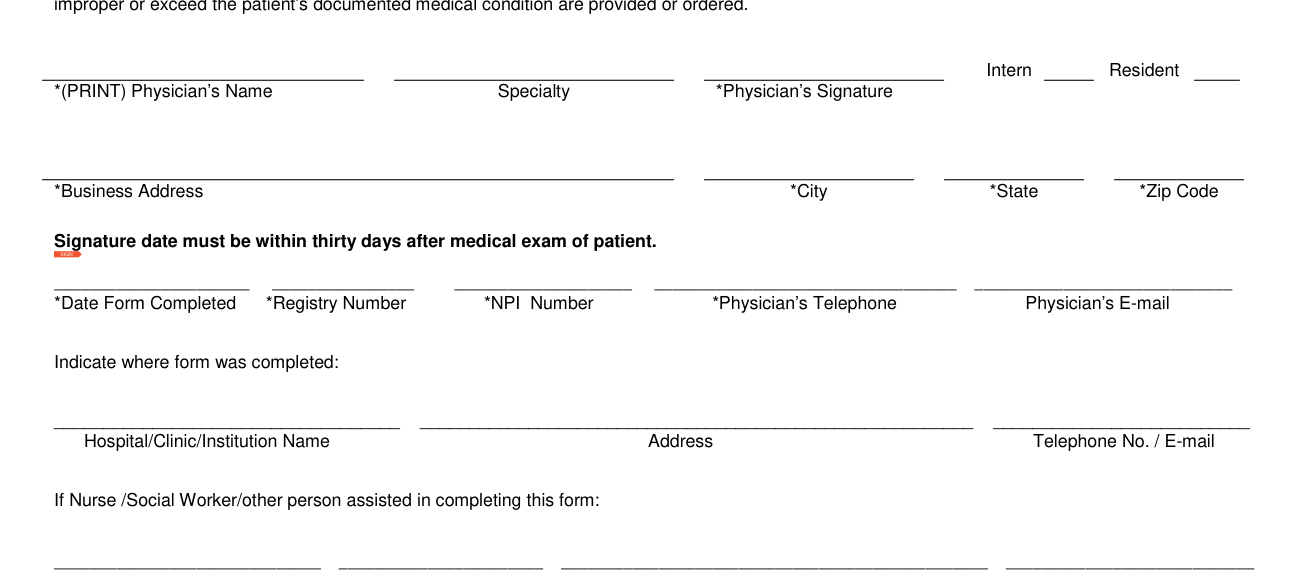
The M-11Q must be signed by a NY State licensed physician.
The medical professional must not recommend or request the number of hours of personal care services.
The physician must sign and date the M-11Q within 30 days after the exam date.
The registry number, NPI (national provider ID), and the complete business address of the physician must be indicated.
By signing the Physician's Certification, the physician certifies that this patient can be cared for at home, and that he or she has accurately described his or her medical condition, needs and regimens, including any medication regimens, at the time he or she examined him or her.
The completed signed copy of the M-11Q must be forwarded within 30 calendar days after the medical examination.
The physician's order is subject to the New York State Department of Health regulations at part 515, 516, 517, and 518 of title 18 NYCRR, which permit the department to impose monetary penalties on, or sanction and recover overpayments from, providers or prescribers of medical care, services or supplies when medical care, services or supplies that are unnecessary, improper or exceed the patient's documented medical condition are provided or ordered.
Intern Resident *(PRINT) Physician's Name Specialty *Physician's Signature *Business Address *City *State *Zip Code *Date Form Completed *Registry Number *NPI Number *Physician's Telephone Physician's E-mail. Signature date must be within thirty days after medical exam of patient. Indicate where form was completed: Hospital/Clinic/Institution Name Address Telephone No. / E-mail. If Nurse /Social Worker/other person assisted in completing this form: Name Title Address Telephone No. / E-mail *Mandatory
More rules for Form M11Q
Under Return Completed Form to, enter the Address and the Borough.
Sources
[1] Form M11Q (12/09/2014), Medical Request for Home Care, New York City Human Resources Administration (the Official source link on this page).
