

Massachusetts MOLST form at a glance
What it is: MOLST, the Massachusetts Medical Orders for Life-Sustaining Treatment form, is a MA DPH-approved standardized medical order form for use by licensed Massachusetts physicians, nurse practitioners and physician assistants.
Who signs: The patient or the patient's representative signs Section D, and a physician, nurse practitioner or physician assistant signs Section E.
A filled-in Massachusetts MOLST form example: a patient and a clinician sign page 1
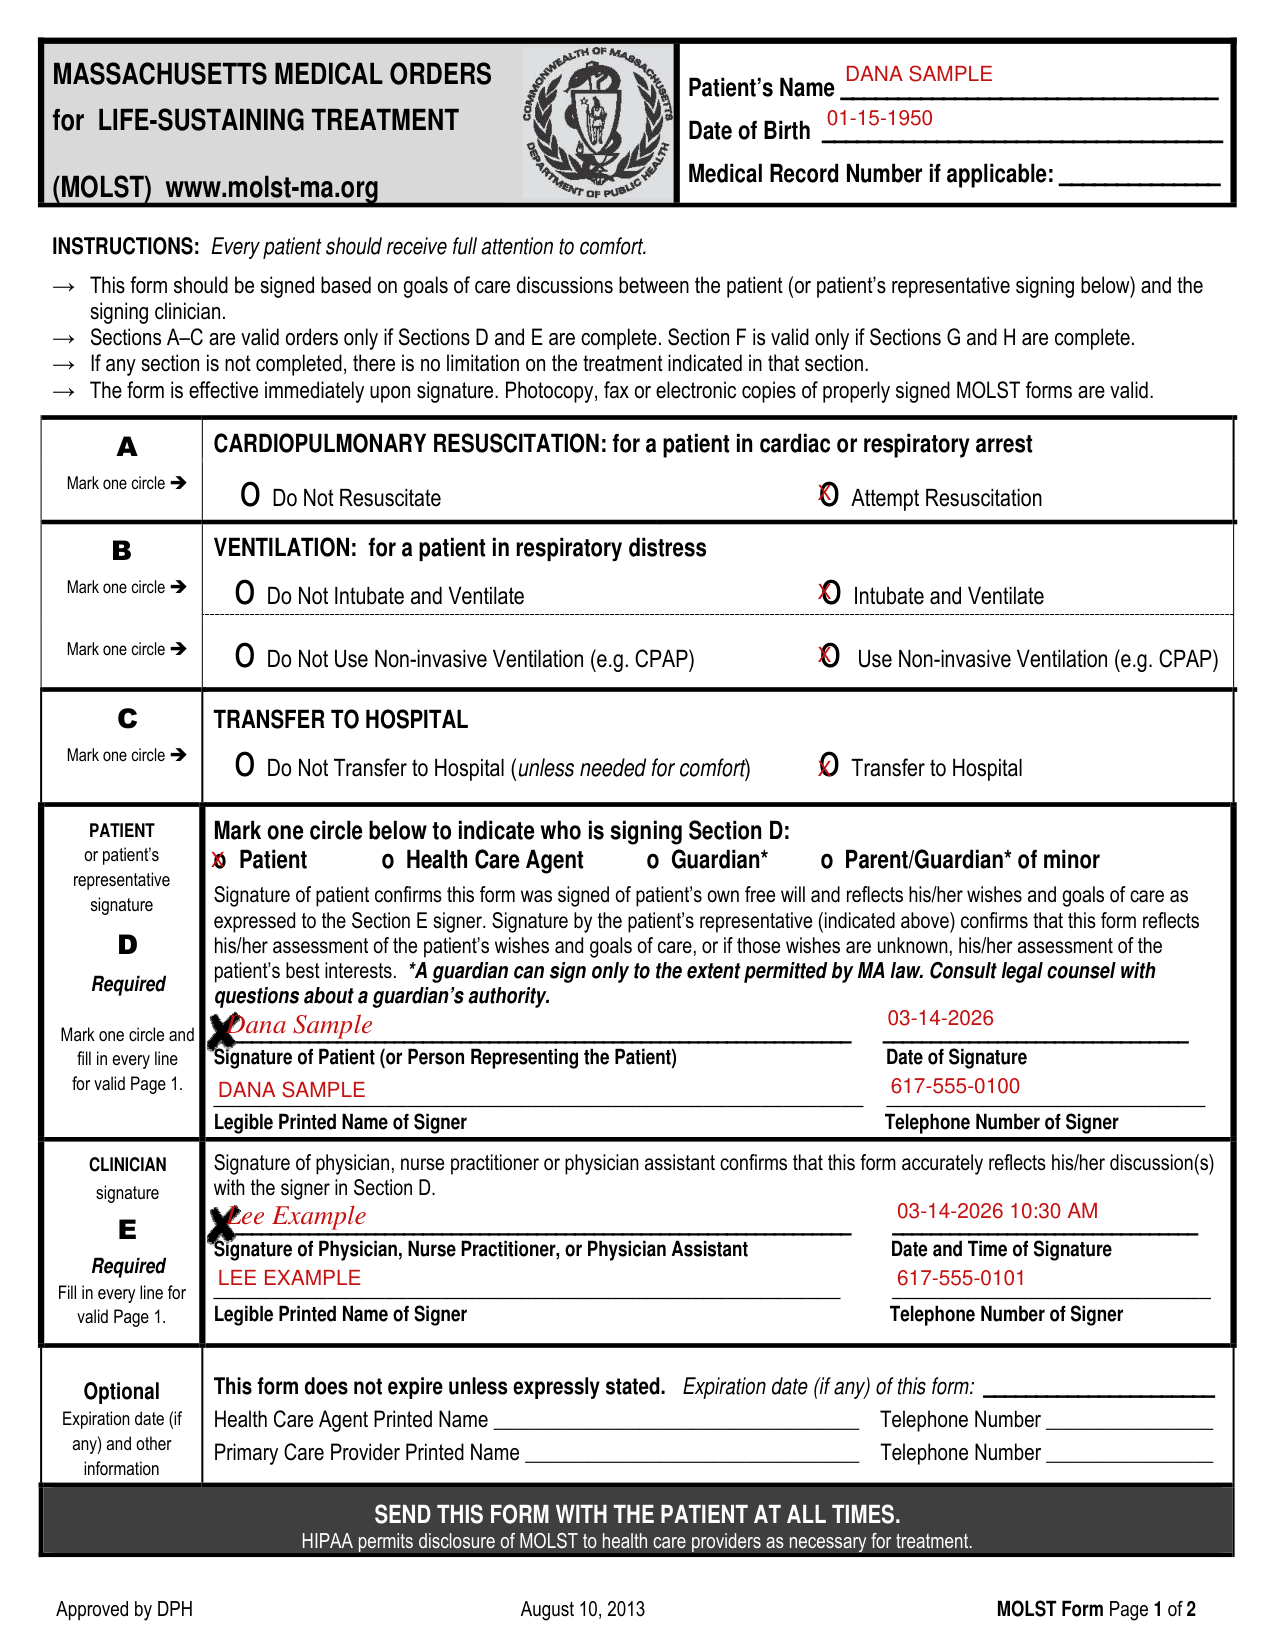
How to fill out Massachusetts MOLST form, box by box
Patient’s Name, Date of Birth and Medical Record Number

Enter the Patient's Name, Date of Birth and Medical Record Number if applicable.
Section A, Cardiopulmonary Resuscitation

Section A, Cardiopulmonary Resuscitation, is for a patient in cardiac or respiratory arrest: mark one circle, Do Not Resuscitate or Attempt Resuscitation.
Ventilation

Ventilation is for a patient in respiratory distress: mark one circle, Do Not Intubate and Ventilate or Intubate and Ventilate, and mark one circle, Do Not Use Non-invasive Ventilation (e.g. CPAP) or Use Non-invasive Ventilation (e.g. CPAP).
Section C, Transfer to Hospital

Section C, Transfer to Hospital: mark one circle, Do Not Transfer to Hospital (unless needed for comfort) or Transfer to Hospital.
Section D, patient or representative signature

Mark one circle to indicate who is signing Section D: Patient, Health Care Agent, Guardian or Parent/Guardian of minor. Mark one circle and fill in every line for valid Page 1.
Sign on the Signature of Patient (or Person Representing the Patient) line, and fill in the Date of Signature, the Legible Printed Name of Signer and the Telephone Number of Signer.
A patient's signature confirms this form was signed of the patient's own free will and reflects the patient's wishes and goals of care as expressed to the Section E signer. A signature by the patient's representative confirms that this form reflects the representative's assessment of the patient's wishes and goals of care, or if those wishes are unknown, the representative's assessment of the patient's best interests. A guardian can sign only to the extent permitted by MA law. Consult legal counsel with questions about a guardian's authority.
Section E, clinician signature

The signature of a physician, nurse practitioner or physician assistant in Section E confirms that this form accurately reflects the signer's discussion(s) with the signer in Section D.
Required: fill in every line for valid Page 1: the Signature of Physician, Nurse Practitioner, or Physician Assistant, the Date and Time of Signature, the Legible Printed Name of Signer and the Telephone Number of Signer.
MOLST requires a physician, nurse practitioner, or physician assistant signature to be valid.
Expiration date (if any) and other information

Optional: enter the Expiration date (if any) of this form, the Health Care Agent Printed Name and Telephone Number, and the Primary Care Provider Printed Name and Telephone Number. This form does not expire unless expressly stated.
Section F, Statement of Patient Preferences for Other Medically-Indicated Treatments
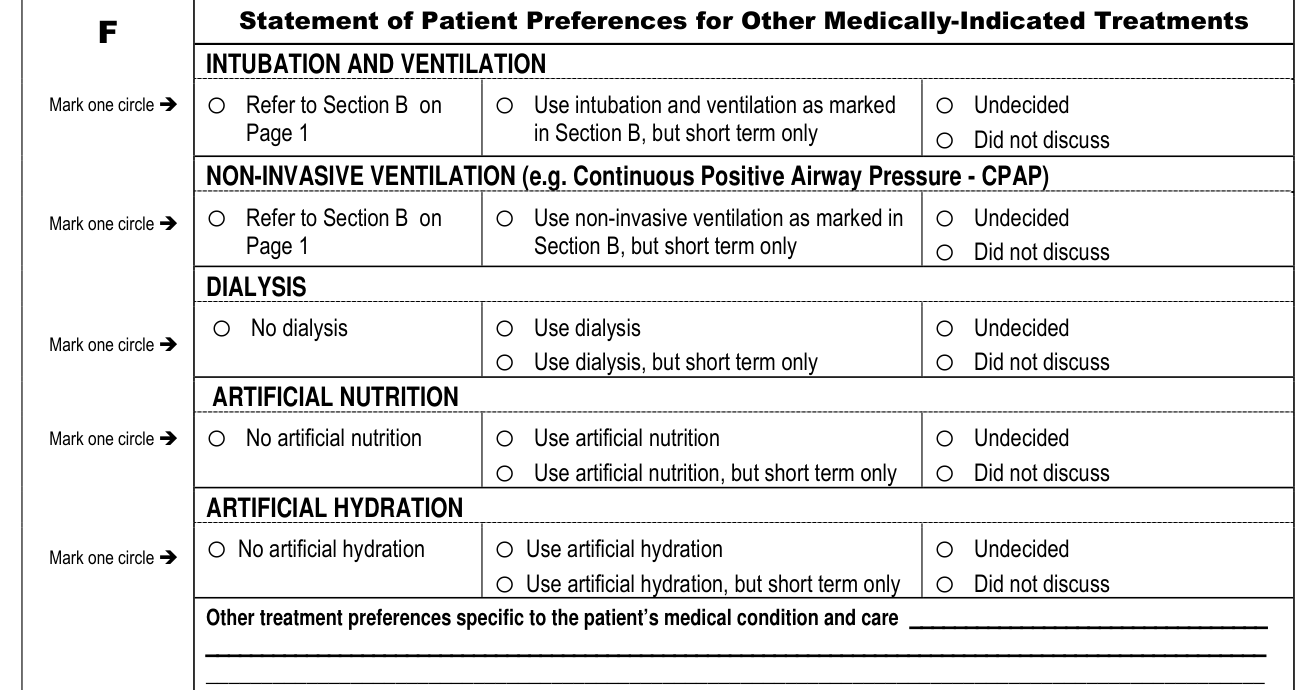
Section F, Statement of Patient Preferences for Other Medically-Indicated Treatments: for Intubation and Ventilation and for Non-invasive Ventilation, mark one circle each: Refer to Section B on Page 1, Use as marked in Section B but short term only, Undecided or Did not discuss.
For Dialysis, Artificial Nutrition and Artificial Hydration, mark one circle each: No, Use, Use but short term only, Undecided or Did not discuss. Write Other treatment preferences specific to the patient's medical condition and care on the lines.
Section G, patient or representative signature on page 2

For Section G, mark one circle for who is signing (Patient, Health Care Agent, Guardian or Parent/Guardian of minor) and fill in every line for valid Page 2.
Section H, clinician signature on page 2

The signature of a physician, nurse practitioner or physician assistant in Section H confirms that this form accurately reflects the signer's discussion(s) with the signer in Section G. Required: fill in every line for valid Page 2: the Signature of Physician, Nurse Practitioner, or Physician Assistant, the Date and Time of Signature, the Legible Printed Name of Signer and the Telephone Number of Signer.
More rules for Massachusetts MOLST form
Every patient should receive full attention to comfort. This form should be signed based on goals of care discussions between the patient (or patient's representative signing) and the signing clinician. Sections A-C are valid orders only if Sections D and E are complete. Section F is valid only if Sections G and H are complete. If any section is not completed, there is no limitation on the treatment indicated in that section. The form is effective immediately upon signature. Photocopy, fax or electronic copies of properly signed MOLST forms are valid.
Send this form with the patient at all times. HIPAA permits disclosure of MOLST to health care providers as necessary for treatment.
Follow orders listed in A, B and C and honor preferences listed in F until there is an opportunity for a clinician to review as described in Additional Instructions For Health Care Professionals. Any change to this form requires the form to be voided and a new form to be signed. To void the form, write VOID in large letters across both sides of the form.
If no new form is completed, no limitations on treatment are documented and full treatment may be provided.
The patient or health care agent (if the patient lacks capacity), guardian, or parent/guardian of a minor can revoke the MOLST form at any time and/or request and receive previously refused medically-indicated treatment, and a guardian can sign only to the extent permitted by MA law.
Do not alter the MOLST form. Print original Massachusetts MOLST forms on bright or fluorescent pink paper for maximum visibility, and print the MOLST form (pages 1 and 2) as a double-sided form on a single sheet of paper.
Sources
[1] Massachusetts Medical Orders for Life-Sustaining Treatment (MOLST) form, approved by DPH August 10, 2013 (the Official source link on this page).
