

MassHealth Casualty Recovery Unit PSI Form at a glance
What it is: The MassHealth/Casualty Recovery Unit Permission to Share Information (PSI) Form: use this form if you want the Casualty Recovery Unit to share the information about you with another person or organization.
Where and when to file: If you are authorizing the sharing of only medical claims information send the PSI to: Commonwealth of Massachusetts Casualty Recovery Unit, P. O. Box 15205, Worcester, MA 01615-0205, or Fax: 1-508-856-7672.
A filled-in MassHealth Casualty Recovery Unit PSI Form example: a member names one attorney

How to fill out MassHealth Casualty Recovery Unit PSI Form, box by box
Name of MassHealth member

Enter the Name of MassHealth member, the member whose information listed in Section 2 is to be shared, with the Street and City/State/Zip.
Enter the Date of Birth and the Telephone number.
Enter the Masshealth ID number. If you do not have a Masshealth ID number, please use your social security number.
What information do you want shared?

Under What information do you want shared?, check the box or boxes that apply.
Check the first box for “I am giving the Casualty Recovery Unit permission to share Masshealth Claims information pertaining to my accident”, and enter the Masshealth claims from and to (month/year).
Check other (please be specific) and be specific.
Please be aware that the information you are requesting to be shared on your behalf may include financial information.
Drug and alcohol treatment information

Check Yes, Share drug and alcohol treatment information, or No, Do not share drug and alcohol treatment information.
Whom do you want us to share information with?
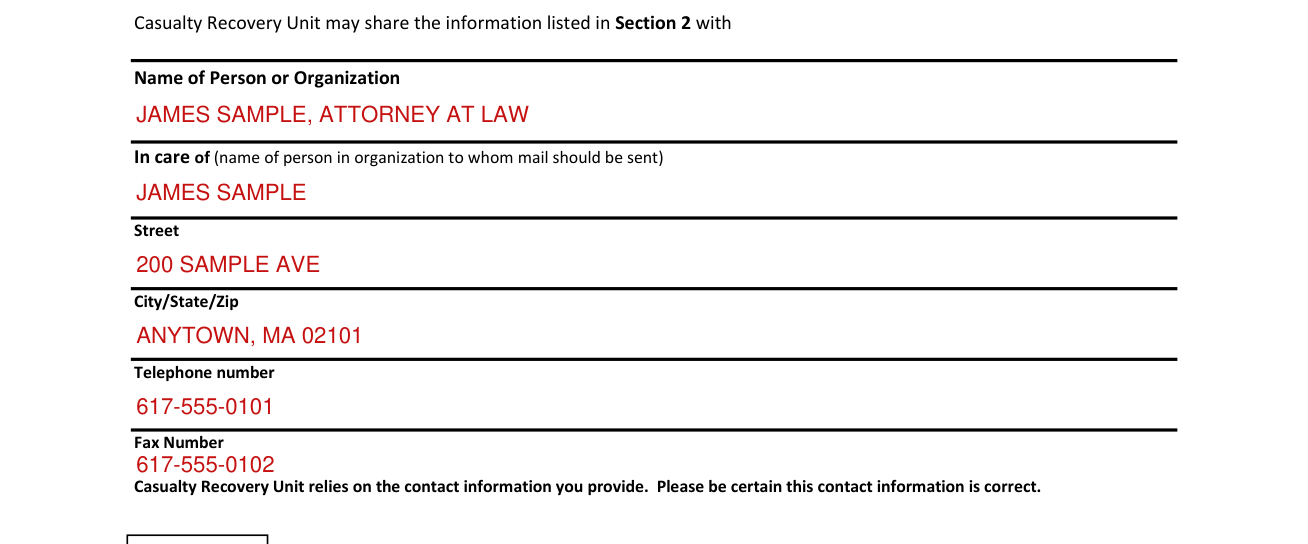
Under Whom do you want to share information with?, list the name of ONLY ONE person or organization in this section.
You must fill out another PSI form if you want to name more than one person or organization.
The Casualty Recovery Unit may share the information listed in Section 2 with the Name of Person or Organization, In care of (name of person in organization to whom mail should be sent), Street, City/State/Zip, Telephone number and Fax Number.
The Casualty Recovery Unit relies on the contact information you provide. Please be certain this contact information is correct.
Why do you want us to share your information?

Under Why do you want your information shared?, tell why you want to share the information listed in Section 2.
End of Permission

This PSI will end in 18 months unless you specify an end date in End of Permission.
Signature of Member

Print the Name of Member. If you do not give the Casualty Recovery Unit Permission to share information, or if you cancel your permission to share information with the person or organization named in Section 3, your MassHealth benefits will not be affected in any way.
Sign under Signature of Member and enter the Date. Fill out the Signature/Legal Guardian section if this form is being filled out by someone who has the legal authority to act on behalf of the applicant or member (such as the parent of a minor-child, an eligibility representative, or a legal guardian).
Signature/Legal Guardian: someone with legal authority fills out the form

Enter the Printed name of person filling out this form, sign the Signature of person filling out this form, and enter the Date, the Address, the Telephone number and the Authority of person filling out this form to act on behalf of member. If this form is being filled out by someone who has been appointed by a court as a legal guardian or conservator or who has power of attorney or health-care proxy, a copy of the applicable legal document must be attached.
More rules for MassHealth Casualty Recovery Unit PSI Form
Use this form for sharing with, such as: a family member, friend, or other relative; an attorney representing you; a social worker, lawyer, or health-care advocacy group; an insurance company settling a case on your behalf.
When the person or organization named in Section 3 gets this information from the Casualty Recovery Unit, that person or organization may be able to share it with others without your permission. If they do so, federal and state privacy laws may not protect the information.
You may cancel this permission at any time by sending a letter to: Casualty Recovery Unit, P.O. Box 15205, Worcester, MA 01615-0205. Even if you cancel this permission, the Casualty Recovery Unit cannot take back any information that it shared when it had your permission to do so.
Common questions about MassHealth Casualty Recovery Unit PSI Form
Where do I file it?
Send this PSI to the address on the front page.
Sources
[1] MassHealth/Casualty Recovery Unit Permission to Share Information (PSI) Form, MassHealth, Commonwealth of Massachusetts (the Official source link on this page).