


Form DOH-4220 at a glance
What it is: Form DOH-4220 is the application for Health Insurance for Older Adults, People With Disabilities and Certain Other Populations.
Who signs: Each applying adult must sign this application.
Where and when to file: Remember to send the application to the local department of social services in the county in which you reside.
This application, along with Supplement A, must be filled out completely if you are 65 years old or older, certified blind, certified disabled or institutionalized, and/or if you are applying for coverage of nursing home care.
This application is also used when applying through a provider, for individuals who are pregnant or under 19.
Any other Medicaid applicants must apply through NY State of Health.
Complete this application if you want health insurance to cover medical expenses. This application can be used to apply for Medicaid, the Family Planning Benefit Program, or for assistance paying your health insurance premiums.
You can apply for yourself and/or immediate family members living with you.
What to bring and attach to Form DOH-4220
Whenever you see the words SEND PROOF on the application refer to the "Documents Needed When You Apply for Health Insurance" section for a listing of acceptable supporting documents, pages 4-6.
You do not need to show all of these documents. Only documents that apply to you or others who are applying are needed.
You need to provide proof of Identity, U.S. Citizenship and/or Immigration Status and Date of Birth.
Please do not mail original U.S. Citizenship or identity documents.
One proof for each type of income you have is required. Provide the most recent proof of income before taxes and any other deductions.
The proof must be dated, include the employee's name and show gross income for the pay period. The proof must be for the last four weeks, whether you get paid weekly, bi-weekly, or monthly.
Proof of Home Address: the proof must match the home address that you write in Section A of the application and be dated within 6 months of when you signed the application.
A filled-in Form DOH-4220 example: a first-time Medicaid applicant fills in Section A
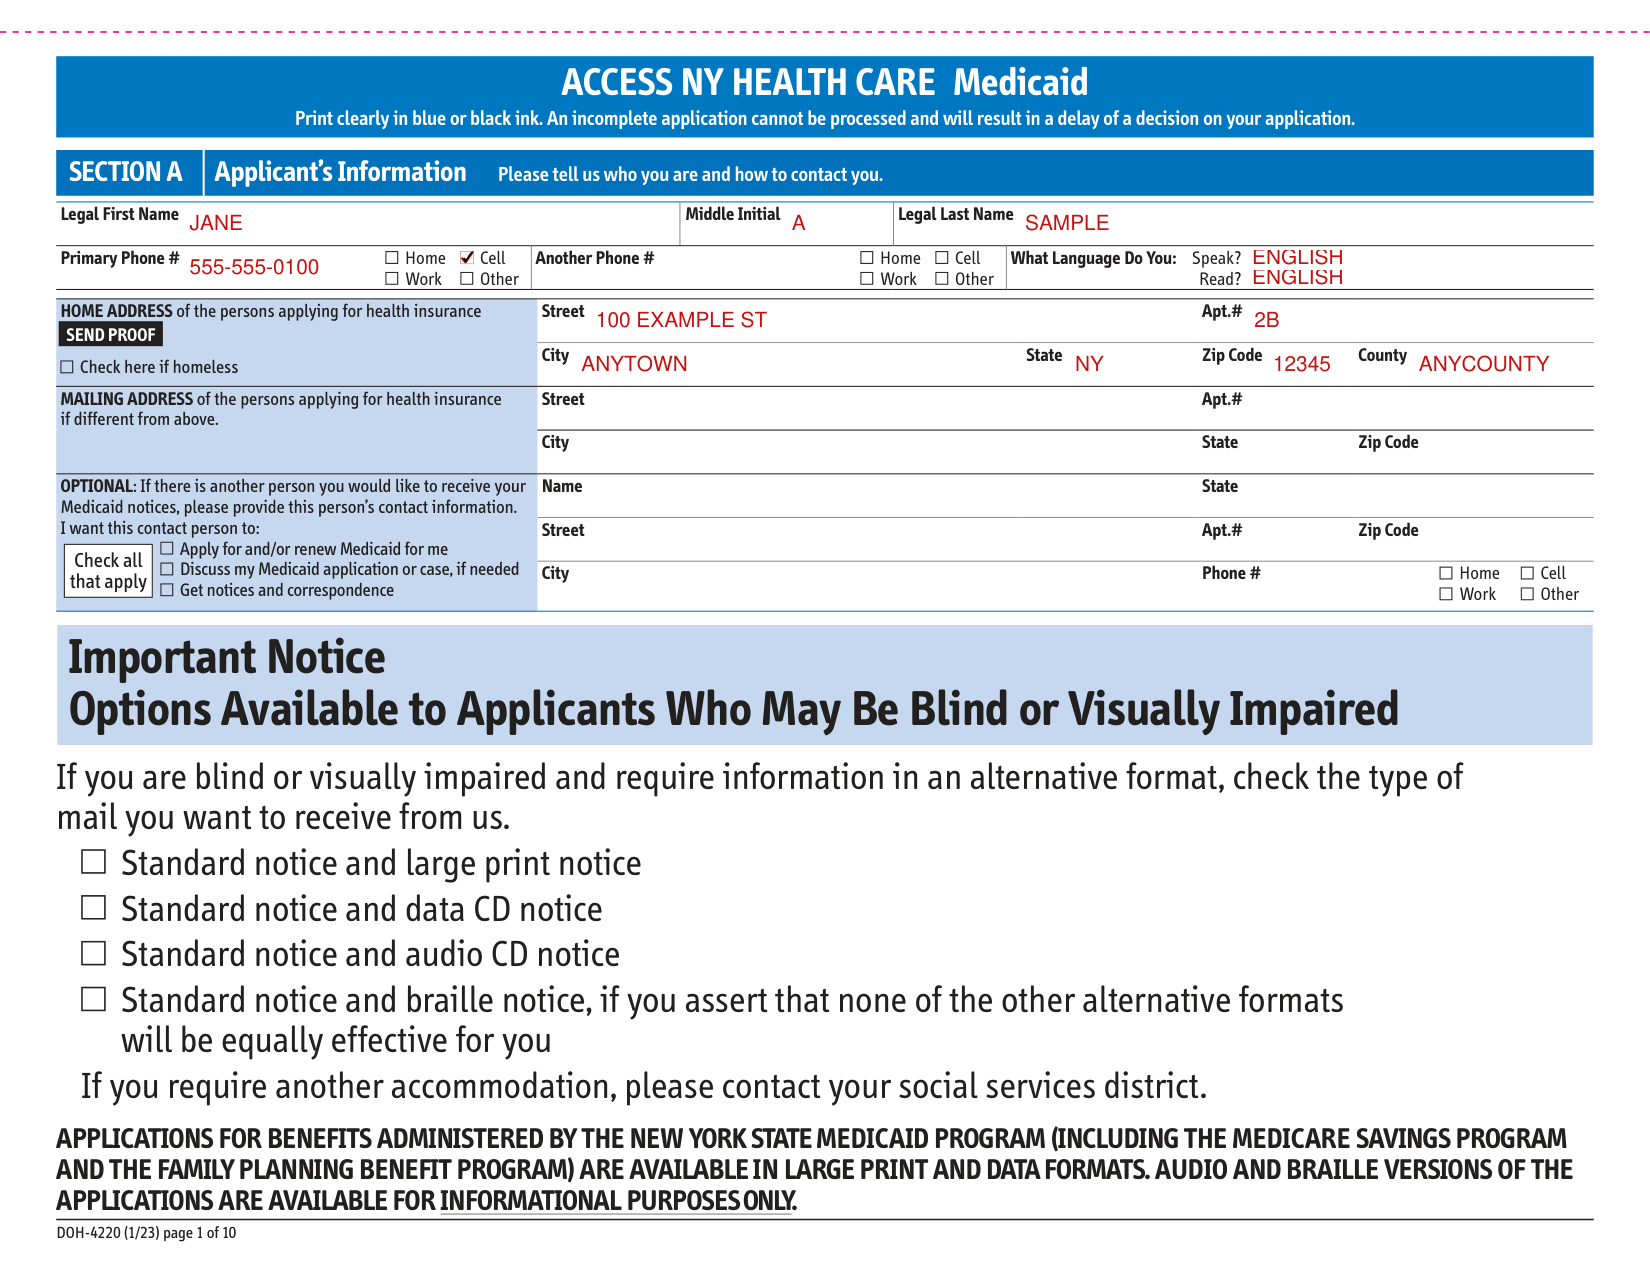
How to fill out Form DOH-4220, box by box
Section A: your name, phone and language

Print clearly in blue or black ink. An incomplete application cannot be processed and will result in a delay of a decision on your application.
In Section A, enter your Legal First Name, Middle Initial and Legal Last Name.
Enter your Primary Phone # and mark Home, Cell, Work or Other.
Enter What Language You Speak and Read.
Home address and mailing address

The home address is where the people applying for health insurance live.
Under HOME ADDRESS of the persons applying for health insurance, enter the Street, Apt.# City, State, Zip Code and County.
Under MAILING ADDRESS of the persons applying for health insurance if different, enter the Street, Apt.# City, State and Zip Code.
Section B: Family Information
In Section B, include information for everyone who lives with you even if they are not applying for health insurance.
If you live in the household, start with yourself. If you do not, start with any adults who live in the household.
You must provide information for family members including: parents, step-parents, and spouses.
A Social Security Number should be provided for all persons applying, if the person has one. If the person does not have a Social Security Number, leave this box blank.
The citizenship information is needed only for those people applying for health insurance. To be eligible for health insurance, persons age 19 and over must be U.S. citizens or be lawfully present.
Section C: Family Income
In Section C, write the types of money and the amount received by everyone listed in Section B.
Earnings from Work: Includes wages, salaries, commissions, tips, overtime, self-employment. If you are self-employed, check the box for that. If you have no earnings from work, check the box for that.
For each person, enter the Name of Person, Type of Income/Employer Name, How Much? (before taxes) and How Often? (weekly, monthly).
Unearned Income: Includes Social Security Benefits, disability payments, unemployment payments, interest and dividends, veterans' benefits, Workers' Compensation, child support payments/alimony, rental income, pension, annuities and trust income. If no unearned income, check here.
Sections D to G: Medicare, housing and medical bills
Does anyone who is applying have Medicare? Mark No or Yes. If yes, include a copy of your card (red, white and blue card), for each Medicare beneficiary.
Monthly housing payment such as rent or mortgage, including property taxes (just your share).
If you are blind, disabled, chronically ill or need nursing home care, you will need to complete Supplement A. If neither you nor anyone applying is blind, disabled, chronically ill or in a nursing home, go to Section G.
Does anyone applying have paid or unpaid medical or prescription bills for this month or the three months before this month? Medicaid may be able to pay these bills or reimburse you.
Include copies of the medical bills with this application.
Section H: Parent or Spouse Not Living with the Family
Pregnant applicants and families who are applying only for their children are NOT required to fill out this section. All other people who are applying and are age 21 or over must be willing to provide information about a parent of an applying minor or a spouse living outside the home to be eligible for health insurance, unless there is good cause.
If you fear physical or emotional harm as a result of providing information about a parent or spouse not living in the home, you may be excused from providing this information. This is called Good Cause.
Section J: Signature
Please read the paragraph in this section carefully and read the Terms, Rights and Responsibilities section. You must then sign and date the application.
Each applying adult must sign this application.
"I certify under penalty of perjury that everything on this application is the truth as best I know."
More rules for Form DOH-4220
When applying for public health insurance, you DO NOT need to visit your local department of social services or an Assistor for an interview, but you MAY come in or contact an Assistor for help filling out this application. ALL HELP IS FREE.
If your situation is different
The application is for a pregnant person or a child under 19
If the application is for a pregnant person or child under 19, only Sections A thorough G, I, and J must be completed.
You are not a U.S. Citizen
If you are not a U.S. Citizen, ONE of the following documents is needed to prove Immigration Status, Identity and your Date of Birth. You must prove all three.
Immigration Status/Identity: I-551 Permanent Resident Card (“Green Card”) or I-688B or I-766 Employment Authorization Card.
Immigration Status, but require an additional Identity document: I-94 Arrival/Departure Record or USCIS Form I-797 Notice of Action.
DOB/Identity, but require an additional immigration status document: Visa or U.S. Passport.
You are blind or visually impaired
If you are blind or visually impaired and require information in an alternative format, check the type of mail you want to receive.
You are in receipt of Medicare, or choosing a health plan in Section I
If you are in receipt of Medicare, skip this section.
Most people with Medicaid must choose a health plan; if you don't choose a health plan you may be automatically enrolled in one unless it is determined you are exempt.
Common questions about Form DOH-4220
Where do I file it?
Remember to send the application to the local department of social services in the county in which you reside.
Is there a penalty?
I understand that anyone who knowingly lies or hides the truth in order to receive services under these programs is committing a crime and subject to federal and state penalties and may have to repay the amount of benefits received and pay civil penalties.
Sources
[1] Form DOH-4220 (1/23), Health Insurance for Older Adults, People With Disabilities and Certain Other Populations, application, New York State Department of Health (the Official source link on this page).