
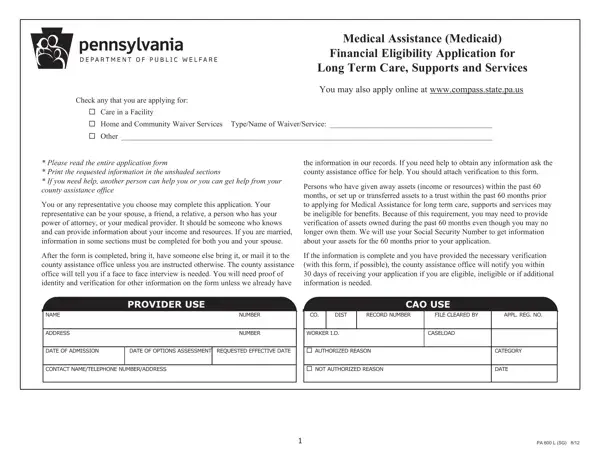
After the form is completed, bring it, have someone else bring it, or mail it to the county assistance office unless you are instructed otherwise.
Verification: you should attach verification to this form.
Assets: persons who have given away assets within the past 60 months prior to applying for Medical Assistance for long term care may be ineligible for benefits.
SSN: you must provide an SSN for each person for whom you are applying.
Changes: any changes you are required to report must be reported within 10 days of the change.
Hearing: you have 30 days from the mailing date of the notice to ask for a hearing.
| Question | Answer |
|---|---|
| Form Name | Form PA 600 L |
| Form Length | 12 pages |
| Fillable? | Yes |
| Fillable fields | 487 |
| Avg. time to fill out | 60+ min |
| Edition | 3/26 |
| Where to bring or mail it | The county assistance office |
| Apply online | www.dhs.pa.gov/compass |
| Other names | PA 600 L, PA600L, PA 600L, PA-600-L, Form PA 600 L, Medicaid Application PA 600 L |
| Official source | Form PA 600 L (Rev 3/26), Department of Human Services |
Medicaid Application Pa 600L Form isn’t the one you’re looking for?