

Medi-Cal Choice Form at a glance
What it is: The Medi-Cal Choice Form is the form you fill in and sign when choosing how to get your Medi-Cal health care.
Where and when to file: Mail To: California Dept. of Health Services Health Care Options Box 989009 West Sacramento, CA 95798-9850
A filled-in Medi-Cal Choice Form example: a head of household enrolls herself
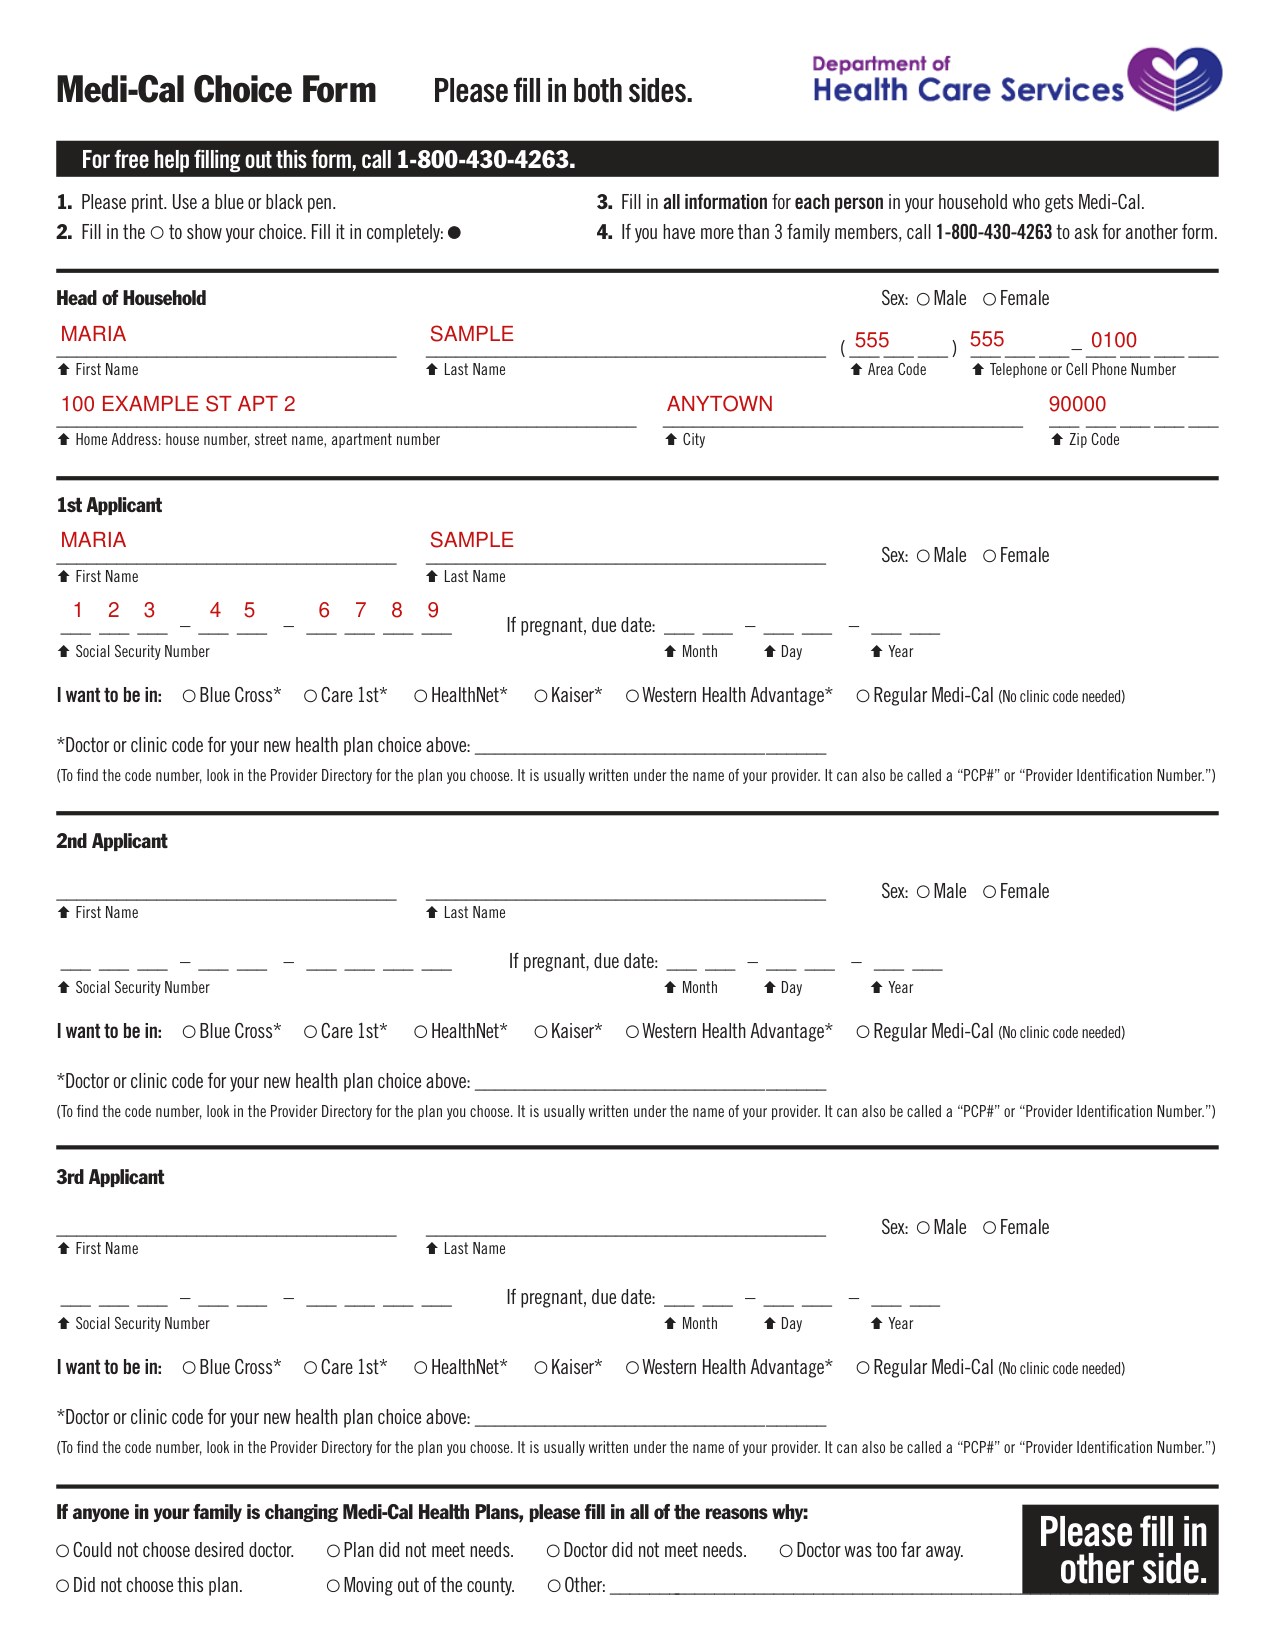
How to fill out Medi-Cal Choice Form, box by box
Head of Household
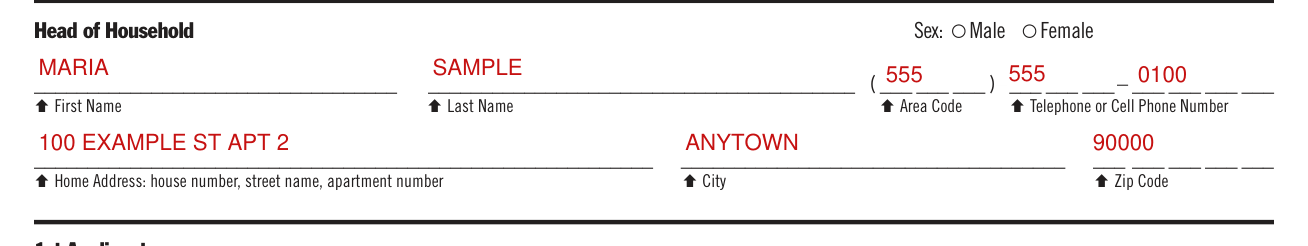
Under Head of Household, fill in the First Name, Last Name, Sex, Area Code, Telephone or Cell Phone Number, Home Address: house number, street name, apartment number, City and Zip Code.
1st Applicant, 2nd Applicant and 3rd Applicant
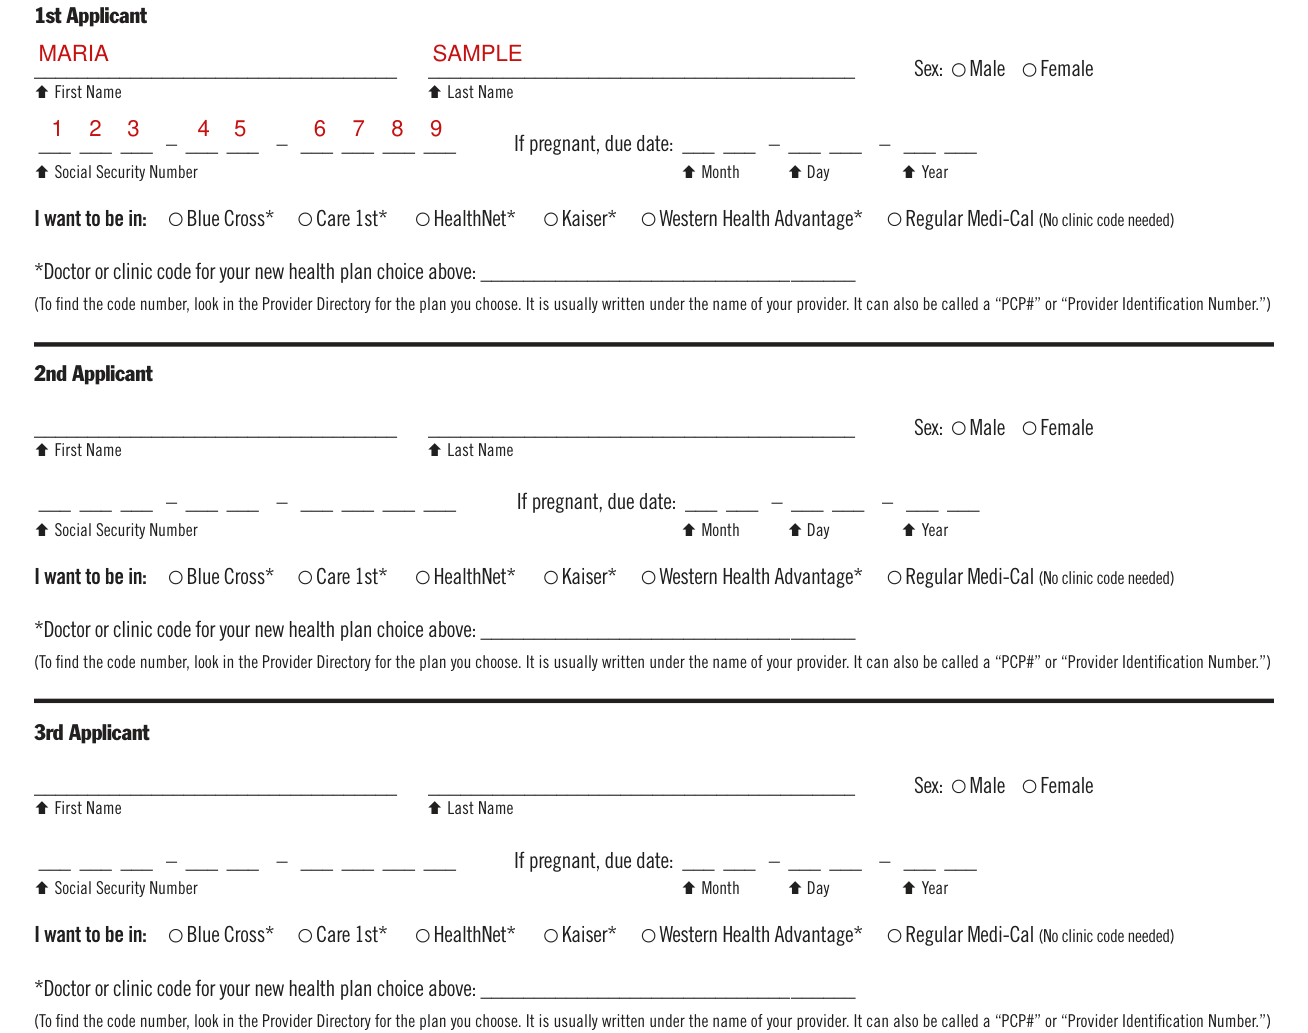
Please print. Use a blue or black pen. Fill in all information for each person in your household who gets Medi-Cal. If you have more than 3 family members, call 1-800-430-4263 to ask for another form. Fill in the First Name, Last Name, Sex and Social Security Number under 1st Applicant, and under 2nd Applicant and 3rd Applicant if a person in your household gets Medi-Cal. If pregnant, fill in the due date: Month, Day and Year. Fill in your choice completely. Under I want to be in, your choice is: Blue Cross*, Care 1st*, Health Net*, Kaiser*, Western Health Advantage* or Regular Medi-Cal (No clinic code needed). For Blue Cross*, Care 1st*, Health Net*, Kaiser* and Western Health Advantage*, fill in the “*Doctor or clinic code for your new health plan choice above”.
To find the code number, look in the Provider Directory for the plan you choose. It is usually written under the name of your provider. It can also be called a “PCP#” or “Provider Identification Number.”
Please Sign Below

The Head of Household signs on the Signature line and fills in the Date: Month, Day and Year. For the 1st Applicant, the 2nd Applicant and the 3rd Applicant, if under 18 years, the parent or guardian signs.
By filling out and signing this form, you are choosing how to get your Medi-Cal health care. If you chose a Medi-Cal Health Plan, by signing, you state that you have read the description of the plan you want to join.
More rules for Medi-Cal Choice Form
Please fill in both sides.
For free help filling out this form, call 1-800-430-4263.
If anyone in your family is changing Medi-Cal Health Plans, please fill in all of the reasons why: Could not choose desired doctor, Plan did not meet needs, Doctor did not meet needs, Doctor was too far away, Did not choose this plan, Moving out of the county, or Other.
If you join Kaiser, Kaiser requires binding arbitration. This means that you give up your right to a jury or court trial for medical malpractice and other disagreements about benefits and services. Instead, you would help choose independent professionals who would make a decision about the problem. You can still ask for a Medi-Cal State Hearing.
The Department of Health Care Services will keep the information on this form. They will only use it to enroll or disenroll you from a Medi-Cal Health Plan. Other government agencies that serve Medi-Cal members can also see this information.
Common questions about Medi-Cal Choice Form
Where do I file it?
Mail To: California Dept. of Health Services Health Care Options Box 989009 West Sacramento, CA 95798-9850
Sources
[1] Medi-Cal Choice Form, California Department of Health Care Services (the Official source link on this page).
