

Medicare Health History Form for Annual Wellness Visit at a glance
What it is: Medicare Health History Form for Annual Wellness Visit: complete this checklist before seeing your doctor or nurse. Your responses will help you receive the best health care possible.
Where and when to file: Please give the completed form to your doctor or nurse.
What to bring and attach to Medicare Health History Form for Annual Wellness Visit
Checklist to bring to your appointment: Medical records, including immunization records; Family health history in as much detail as possible; Full list of medications, supplements-how often & how much taken; Full list of current providers & suppliers involved in your care.
A filled-in Medicare Health History Form for Annual Wellness Visit example: a patient fills out the health history

How to fill out Medicare Health History Form for Annual Wellness Visit, box by box
Your name, today's date and your date of birth
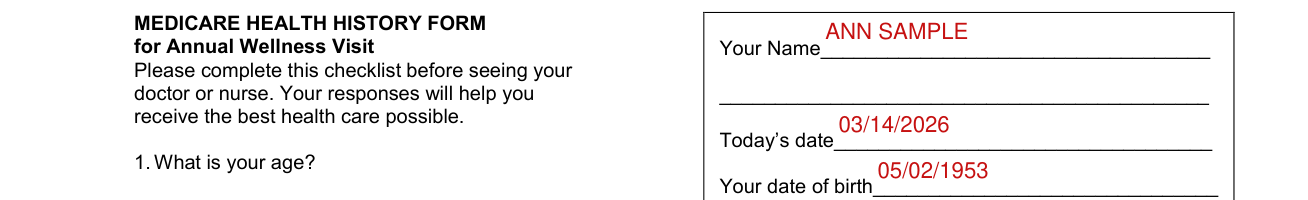
Your Name. Today's date. Your date of birth.
Your age, female or male

What is your age? 65-69 / 70-79 / 80 or older.
Are you a female or a male? Male / Female.
Emotional problems and social activities in the past four weeks

During the past four weeks, how much have you been bothered by emotional problems such as feeling anxious, depressed, irritable, sad, or downhearted and blue? During the past four weeks, has your physical and emotional health limited your social activities with family friends, neighbors, or groups? Not at all / Slightly / Moderately / Quite a bit / Extremely.
Bodily pain in the past four weeks

During the past four weeks, how much bodily pain have you generally had? No pain / Very mild pain / Mild pain / Moderate pain / Severe pain.
Someone available to help you

During the past four weeks, was someone available to help you if you needed and wanted help? (For example, if you felt very nervous, lonely or blue; got sick and had to stay in bed; needed someone to talk to; needed help with daily chores; or needed help just taking care of yourself.) Yes, as much as I wanted / Yes, quite a bit / Yes, some / Yes, a little / No, not at all.
The hardest physical activity you could do

During the past four weeks, what was the hardest physical activity you could do for at least two minutes? Very heavy / Heavy / Moderate / Light / Very light.
Getting to places, shopping, meals and housework

Can you get to places out of walking distance without help? (For example, can you travel alone on buses, taxis, or drive your own car?) Yes / No.
Can you go shopping for groceries or clothes without someone's help? Yes / No.
Can you prepare your own meals? Yes / No.
Can you do your housework without help? Yes / No.
Personal care and your own money

Because of any health problems, do you need the help of another person with your personal care needs such as eating, bathing, dressing, or getting around the house? Yes / No.
Can you handle your own money without help? Yes / No.
Your health in general

During the past four weeks, how would you rate your health in general? Excellent / Very good / Good / Fair / Poor.
Patient Name and how things have been going for you

Patient Name. How have things been going for you during the past four weeks? Very well; could hardly be better / Pretty well / Good and bad parts about equal / Pretty bad / Very bad; could hardly be worse.
Driving your car
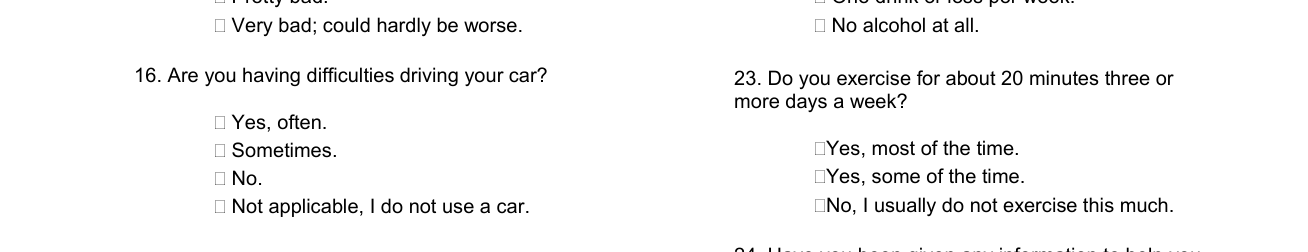
Are you having difficulties driving your car? Yes, often / Sometimes / No / Not applicable, I do not use a car.
Fastening your seat belt, problems, falling and a smoker
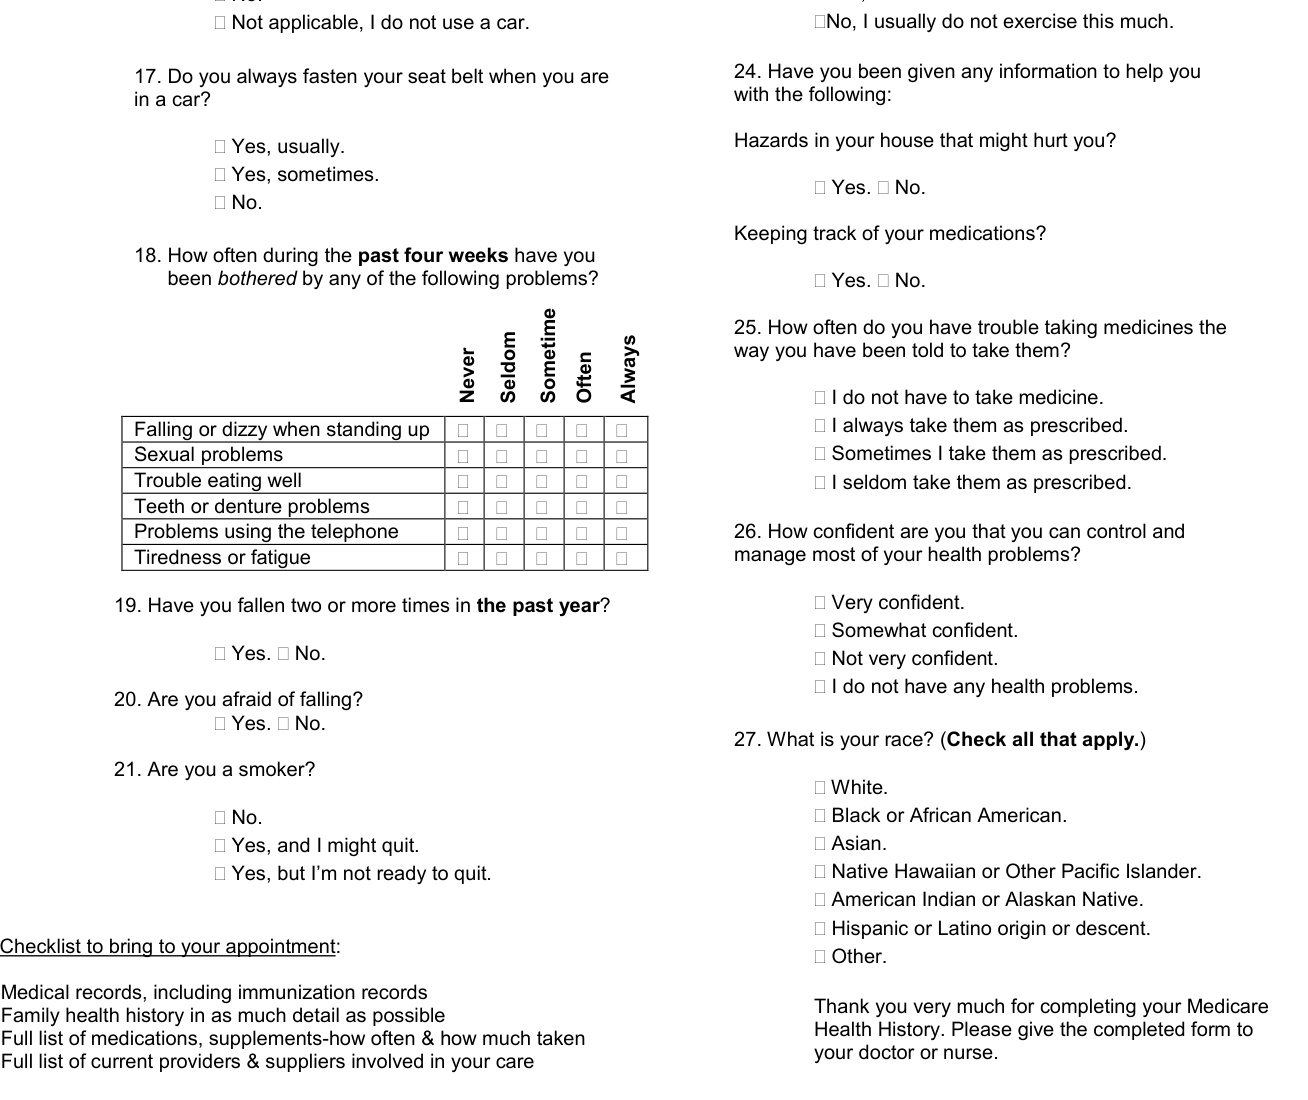
Do you always fasten your seat belt when you are in a car? Yes, usually / Yes, sometimes / No. How often during the past four weeks have you been bothered by any of the following problems? Never / Seldom / Sometime / Often / Always.
Falling or dizzy when standing up / Sexual problems / Trouble eating well / Teeth or denture problems / Problems using the telephone / Tiredness or fatigue. Have you fallen two or more times in the past year? Yes / No. Are you afraid of falling? Yes / No. Are you a smoker? No / Yes, and I might quit / Yes, but I'm not ready to quit.
DOB, Today's Date and alcoholic beverages

DOB. Today's Date. During the past four weeks, how many drinks of wine, beer, or other alcoholic beverages did you have? 10 or more drinks per week / 6-9 drinks per week / 2-5 drinks per week / One drink or less per week / No alcohol at all.
Exercise
Do you exercise for about 20 minutes three or more days a week? Yes, most of the time / Yes, some of the time / No, I usually do not exercise this much.
Information to help you with hazards, medications and taking medicines

Have you been given any information to help you with the following:
Hazards in your house that might hurt you? Yes / No.
Keeping track of your medications? Yes / No. How often do you have trouble taking medicines the way you have been told to take them? I do not have to take medicine / I always take them as prescribed / Sometimes I take them as prescribed / I seldom take them as prescribed.
How confident you are that you can control and manage most of your health problems

How confident are you that you can control and manage most of your health problems? Very confident / Somewhat confident / Not very confident / I do not have any health problems.
Your race

What is your race? (Check all that apply.) White / Black or African American / Asian / Native Hawaiian or Other Pacific Islander / American Indian or Alaskan Native / Hispanic or Latino origin or descent / Other.
Sources
[1] Medicare Health History Form for Annual Wellness Visit (PN 900) (the Official source link on this page).
