

Michigan DHS-4574 at a glance
What it is: This is the Michigan Department of Health and Human Services application for health care coverage for a patient of a nursing facility.
Who signs: You must sign the application.
Complete this form if you are in a nursing facility.
A filled-in Michigan DHS-4574 example: a nursing facility patient fills in the top of page 3
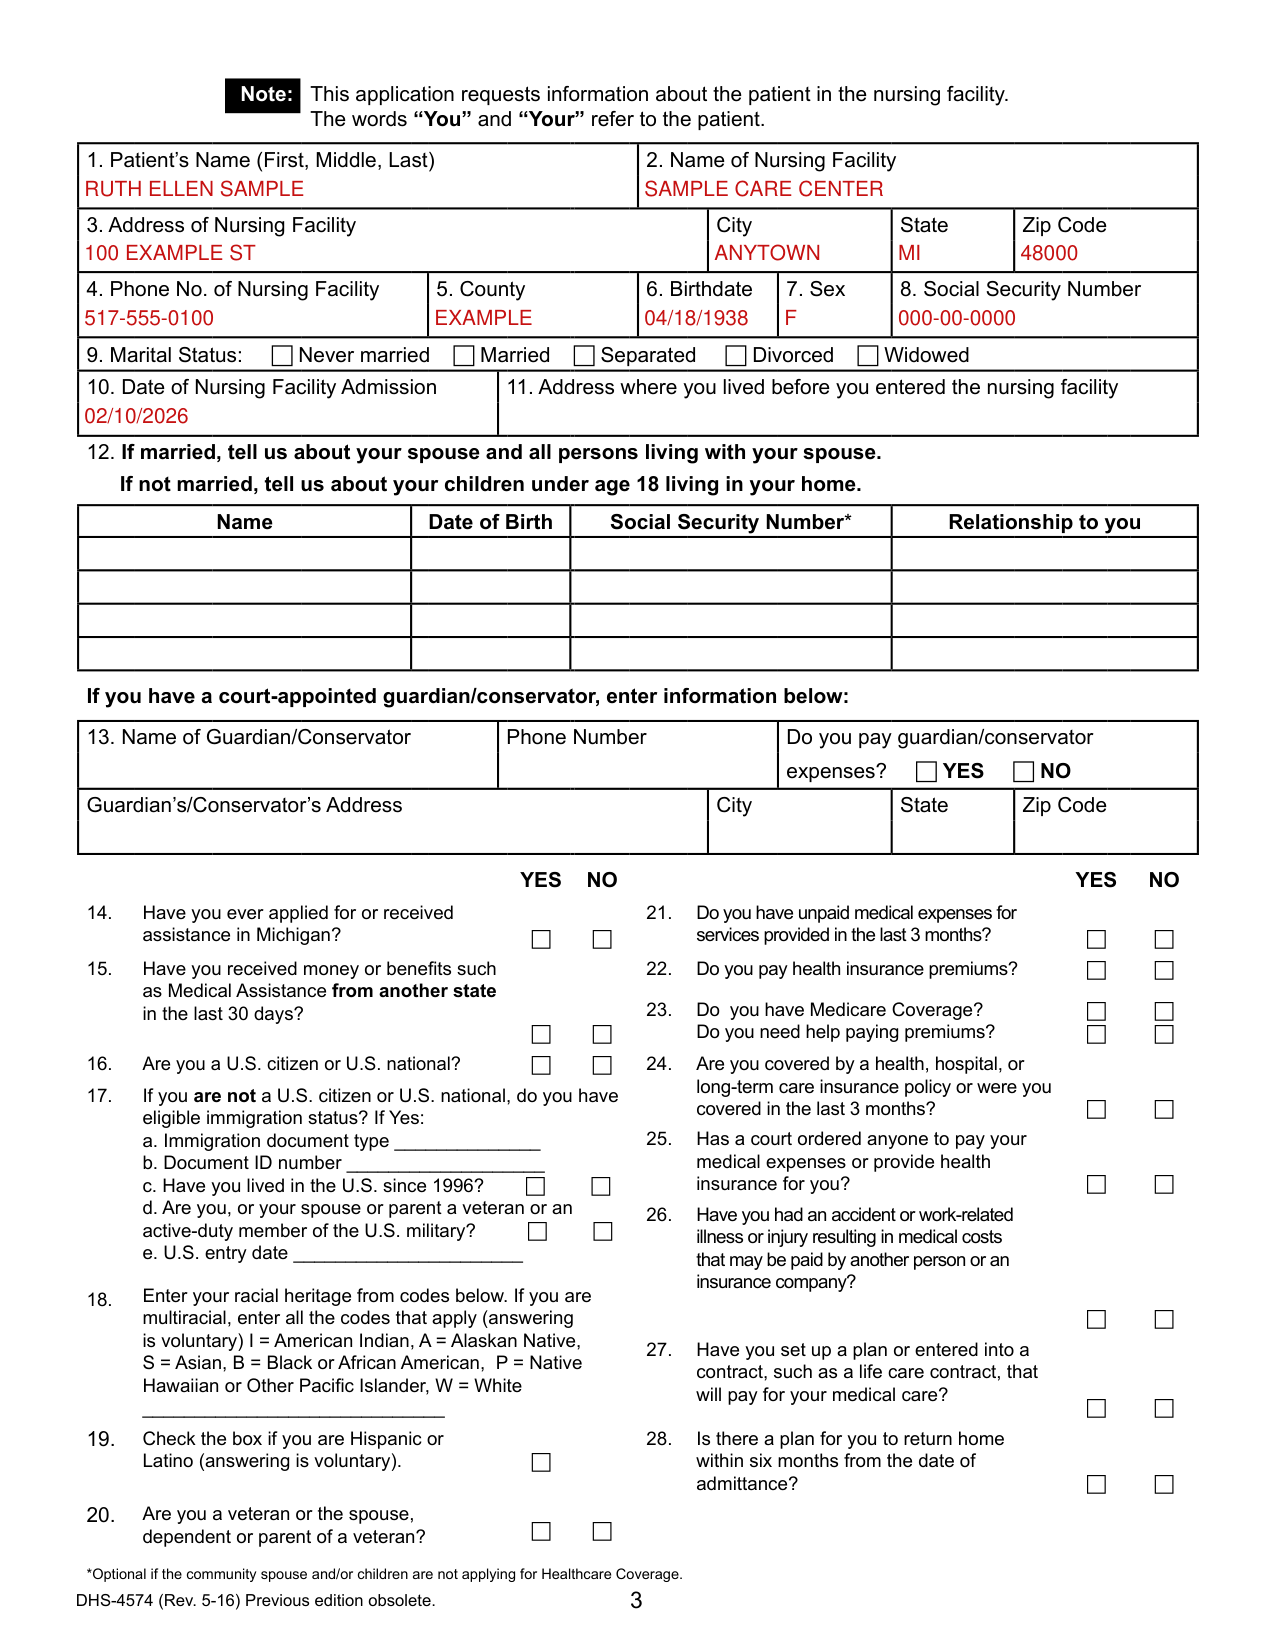
How to fill out Michigan DHS-4574, box by box
Patient, nursing facility and admission
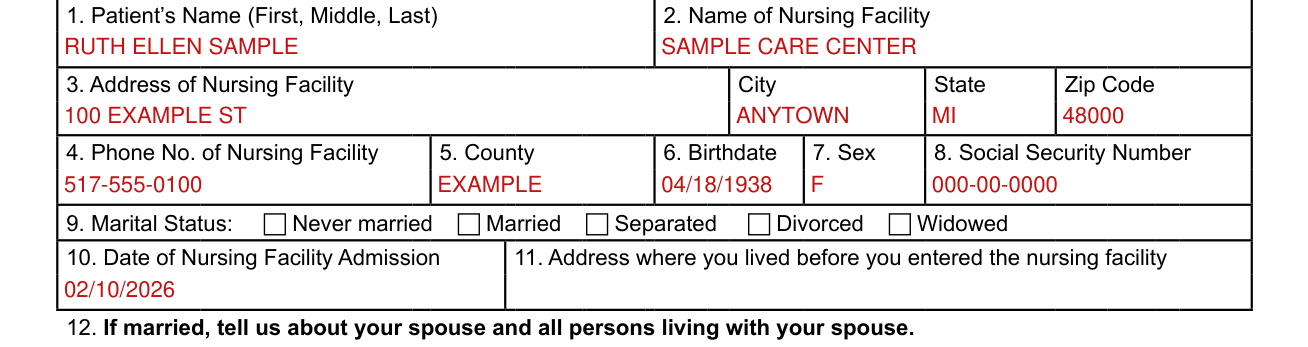
This application requests information about the patient in the nursing facility. The words “You” and “Your” refer to the patient.
Enter 1. Patient's Name (First, Middle, Last), 2. Name of Nursing Facility, 3. Address of Nursing Facility with City, State and Zip Code, 4. Phone No. of Nursing Facility, 5. County, 6. Birthdate, 7. Sex and 8. Social Security Number.
Enter 10. Date of Nursing Facility Admission.
More rules for Michigan DHS-4574
Use DCH-1426, Application for Health Coverage and Help Paying Costs, if other family members want help with medical expenses.
If you need an interpreter, the Department will provide one free of charge or you may use one of your choice.
If you are refused help in filling out the application, call 855-275-6424 or 855-789-5610.
Skip the Assets Declaration for Patient and Spouse if no spouse.
The asset limit is $2,000 (checked October 30, 2026).
If you need help with past, unpaid medical expenses, Healthcare Coverage may begin three months before you apply.
Transfers that occur up to 60 months (5 years) before, or any time after, your first date of application for Healthcare Coverage while in a nursing facility are looked at.
You must report changes in income, assets or health insurance coverage to the department within 10 days of the change.
Common questions about Michigan DHS-4574
Who signs it?
Sign on Signature (Patient or Representative) and enter the Date. Two Witnesses only if signed by X. If you are signing this application on behalf of someone else, complete Name of person completing application, Phone Number, Relationship to patient, Street Address, City, State and Zip Code.
Is there a deadline?
Your application must be approved or denied within 45 days, or 90 days if disability is a factor in determining your health care coverage eligibility.
Where do I file it?
You can apply for health care coverage by mailing or having someone take this form into your local Michigan Department of Health and Human Services (MDHHS).
Is there a penalty?
Completion: Voluntary. Penalty: No Healthcare Coverage.
What am I certifying when I sign?
By signing you certify, under penalty of perjury, that all information that you have written on this form or told to a specialist is true.
Sources
[1] Form DHS-4574 (Rev. 5-16), Application for Health Care Coverage, Patient of Nursing Facility, Michigan Department of Health and Human Services (the Official source link on this page).
