

Form NIH-527 at a glance
What it is: Authorization for the Release of Medical Information, MEDICAL RECORD form of the National Institutes of Health, Clinical Center Health Information Management Division.
Where and when to file: For more information or to submit this form electronically, visit https://www.cc.nih.gov/dcri/medical-record-request. Phone: (888) 790-2133 or (301) 496-3331 FAX: (301) 480-9982.
A filled-in Form NIH-527 example: a patient adds a care provider

How to fill out Form NIH-527, box by box
Patient information

In 1. PATIENT INFORMATION, enter the Patient Name, Phone Number and Date of Birth.
Complete a separate form for each requestor.
Action

In 2. ACTION, up to two outside care providers can have permanent authorization to obtain copies of medical records. If the named individual is not a healthcare provider, please skip this step.
Add New Care Provider gives the named care provider access to your medical records. Replace Authorized Care Provider replaces the existing care provider ___________ with the named care provider. Remove Authorized Care Provider removes the named care provider's access.
Release information to
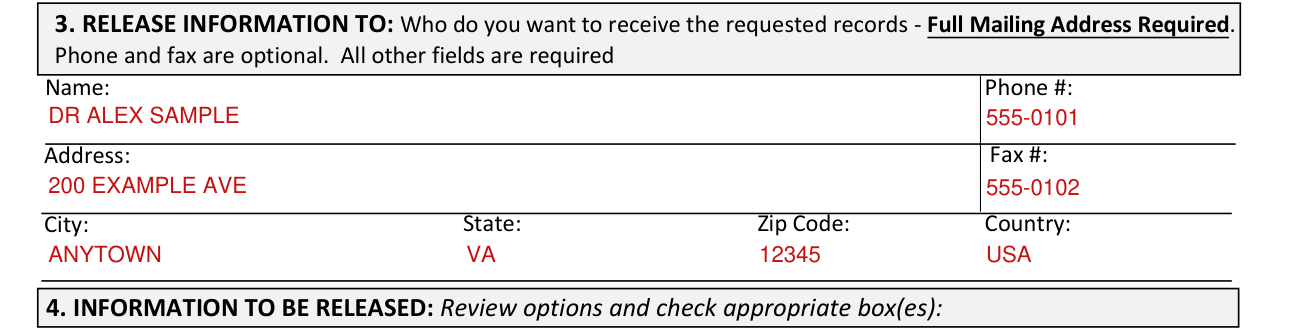
In 3. RELEASE INFORMATION TO, enter Name and Phone #: who do you want to receive the requested records. Full Mailing Address Required. Phone and fax are optional. All other fields are required.
Enter the Address, Fax #, City, State, Zip Code and Country.
Information to be released
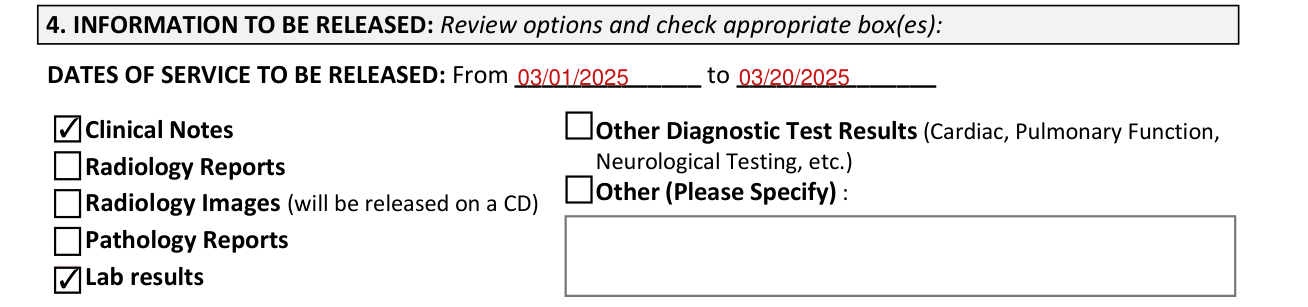
In 4. INFORMATION TO BE RELEASED, review options and check appropriate box(es).
Under DATES OF SERVICE TO BE RELEASED, enter the From and to dates.
The boxes are Clinical Notes, Radiology Reports, Radiology Images (will be released on a CD), Pathology Reports, Lab results, Other Diagnostic Test Results (Cardiac, Pulmonary Function, Neurological Testing, etc.) and Other (Please Specify).
The purpose or need for disclosure

In 5. THE PURPOSE OR NEED FOR DISCLOSURE, enter the purpose (Continued Care, Personal Use,etc).
Authorization

In 6. AUTHORIZATION, you certify by signing and submitting this form that you are the individual who you claim to be. A request for records other than those about you (or those of whom I have legal authority to obtain, e.g., your minor child) is a criminal offense under the Privacy Act subject to a $5,000 fine (checked November 8, 2026). Submission of this form authorizes future disclosures to the same individual and/or entity within one year from date of signature.
Sign on the Patient/Authorized Signature line, then enter the Print Name and the Date.
Common questions about Form NIH-527
Where do I file it?
For more information or to submit this form electronically, visit https://www.cc.nih.gov/dcri/medical-record-request.
Sources
[1] Form NIH-527 (5-24), Authorization for the Release of Medical Information, National Institutes of Health Clinical Center (the Official source link on this page).
