


Form DS-1 at a glance
What it is: Form DS-1 is the New Jersey Temporary Disability Benefits Application, for disability leave.
Who signs: You sign at Sign Here and enter the Date. Enter the Witness signature if claimant writes an "X". The healthcare provider certifies the patient's disability period and enters Print Name, Signature and Date.
Where and when to file: You have 30 days from the first day of your disability to file your claim. Fax this completed form to 609-984-4138.
You must complete the first 2 pages of the form (Parts A and B).
Part C must be completed by your healthcare provider.
Your employer is not required to complete this form but you can ask them to help you with any questions on Part B.
What to bring and attach to Form DS-1
You will need to provide your employer's Federal Employer Identification Number on Part B. You can get this number from either your last year's W-2 form or your Human Resources office.
A filled-in Form DS-1 example: a worker with a broken wrist
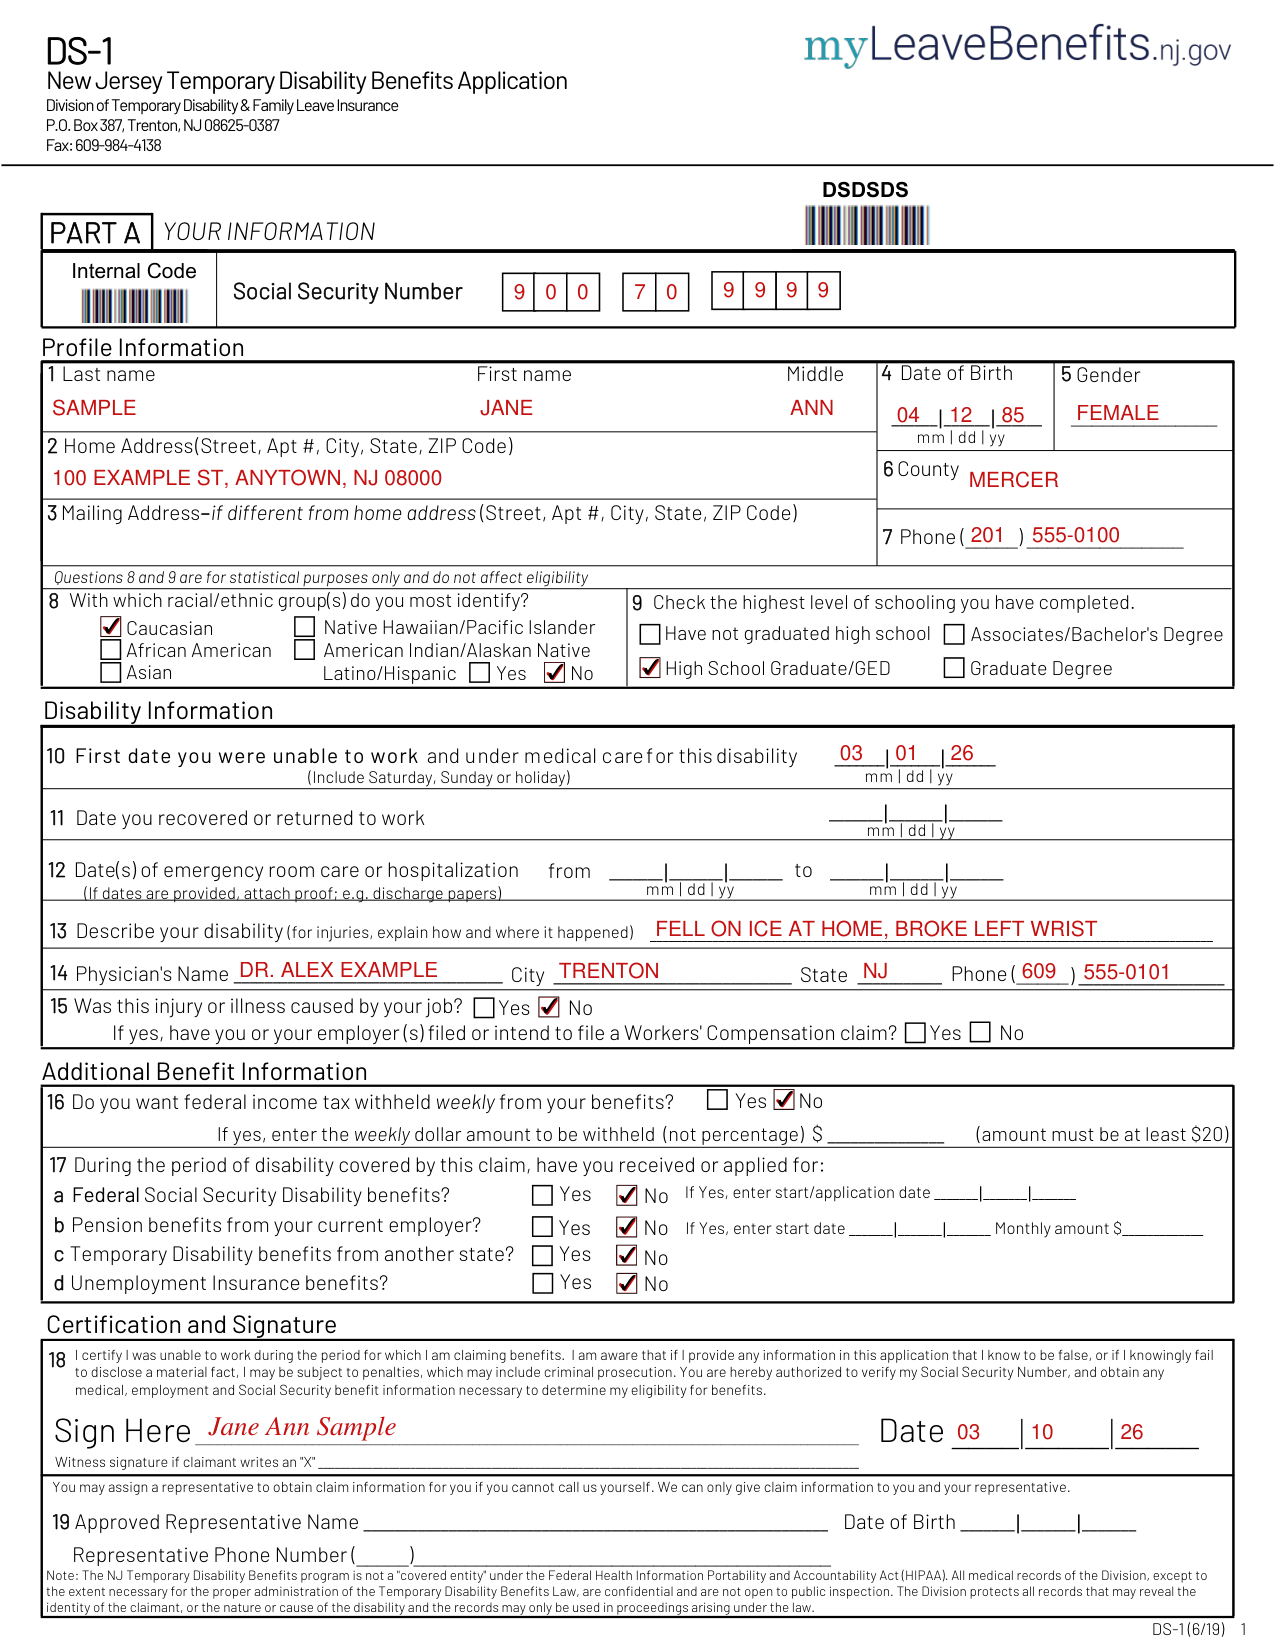
How to fill out Form DS-1, box by box
Part A: your information, boxes 1 to 7
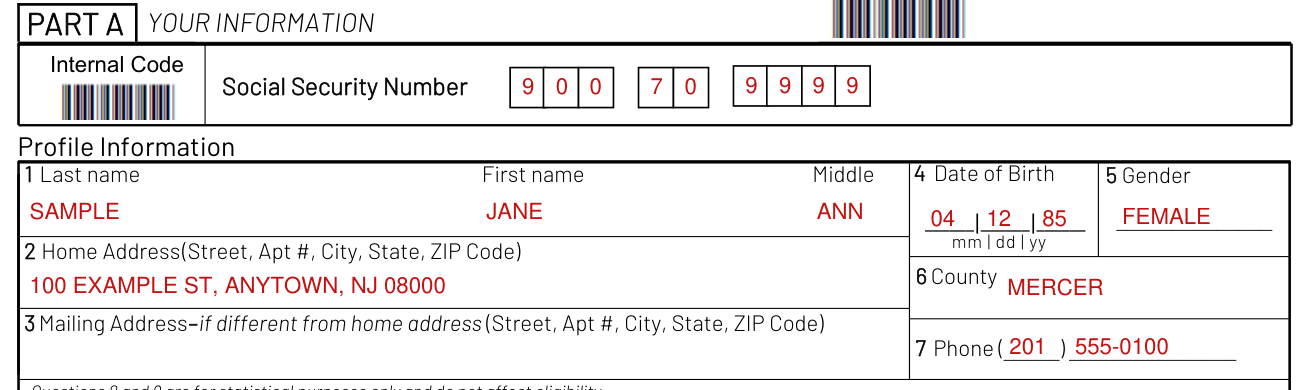
Enter your Social Security Number.
In box 1, enter your Last name, First name and Middle.
In box 2, enter your Home Address. In box 3, enter your Mailing Address if different from home address. Use Street, Apt #, City, State, ZIP Code for each.
In boxes 4 and 5, enter your Date of Birth and Gender.
In box 6, enter your County. In box 7, enter your Phone.
Questions 8 and 9
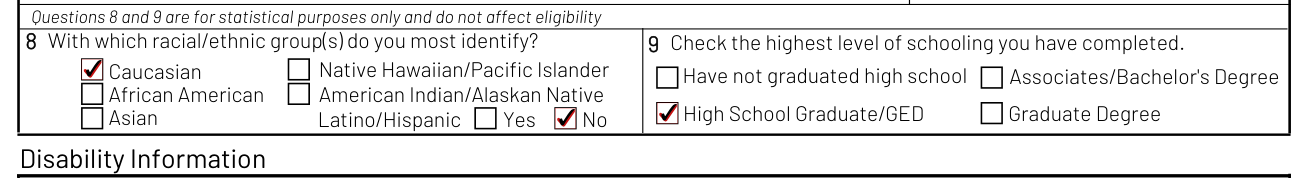
Questions 8 and 9 are for statistical purposes only and do not affect eligibility.
In box 8, check the racial/ethnic group(s) you most identify with. For Latino/Hispanic, check Yes or No.
In box 9, check the highest level of schooling you have completed.
Disability information, boxes 10 to 15
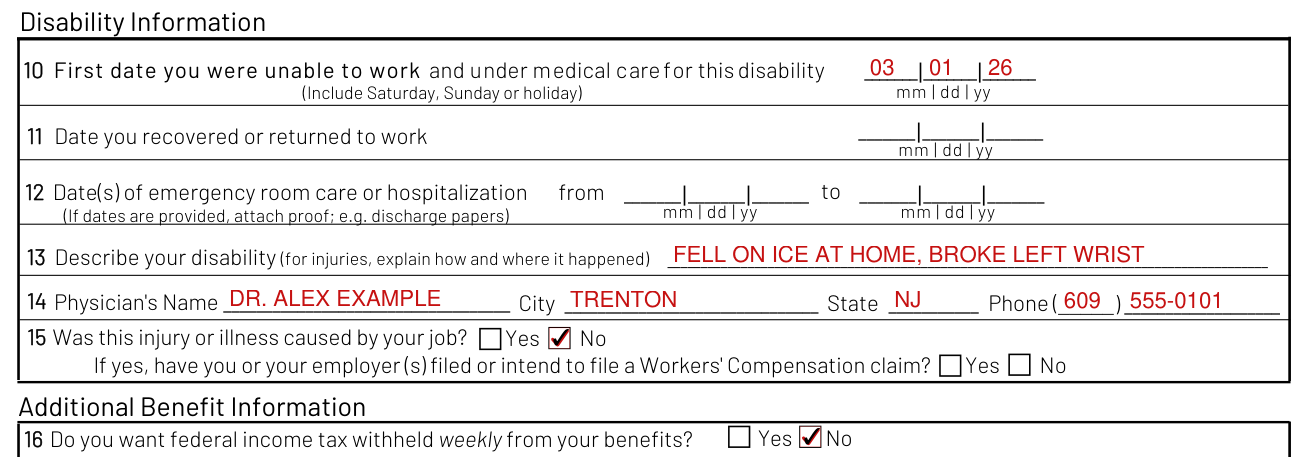
In box 10, enter the First date you were unable to work and under medical care for this disability (Include Saturday, Sunday or holiday).
In box 11, enter the Date you recovered or returned to work.
In box 12, enter the Date(s) of emergency room care or hospitalization, from and to. If dates are provided, attach proof, for example discharge papers.
In box 13, describe your disability (for injuries, explain how and where it happened).
In box 14, enter the Physician's Name, City, State and Phone.
In box 15, check Yes or No: Was this injury or illness caused by your job? If yes, check Yes or No: have you or your employer(s) filed or intend to file a Workers' Compensation claim?
Additional benefit information, boxes 16 and 17

In box 16, check Yes or No: Do you want federal income tax withheld weekly from your benefits?
If yes, enter the weekly dollar amount to be withheld (not percentage); the amount must be at least $20 (checked October 19, 2026).
In box 17, check Yes or No for each of the following: During the period of disability covered by this claim, have you received or applied for: a Federal Social Security Disability benefits, b Pension benefits from your current employer, c Temporary Disability benefits from another state, d Unemployment Insurance benefits?
Under a, if Yes, enter the start/application date. Under b, if Yes, enter the start date and the Monthly amount.
Certification and signature, boxes 18 and 19
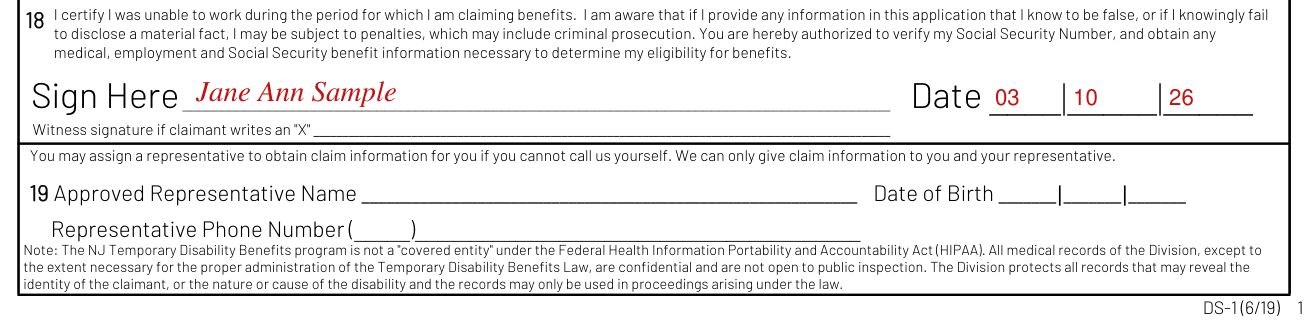
In box 18, you certify you were unable to work during the period for which you are claiming benefits.
If you provide any information in this application that you know to be false, or if you knowingly fail to disclose a material fact, you may be subject to penalties, which may include criminal prosecution.
You are hereby authorized to verify your Social Security Number, and obtain any medical, employment and Social Security benefit information necessary to determine your eligibility for benefits.
You sign at Sign Here and enter the Date.
You may assign a representative to obtain claim information for you if you cannot call yourself.
In box 19, enter the Approved Representative Name, Date of Birth and Representative Phone Number.
Part B: employment information, most recent employer
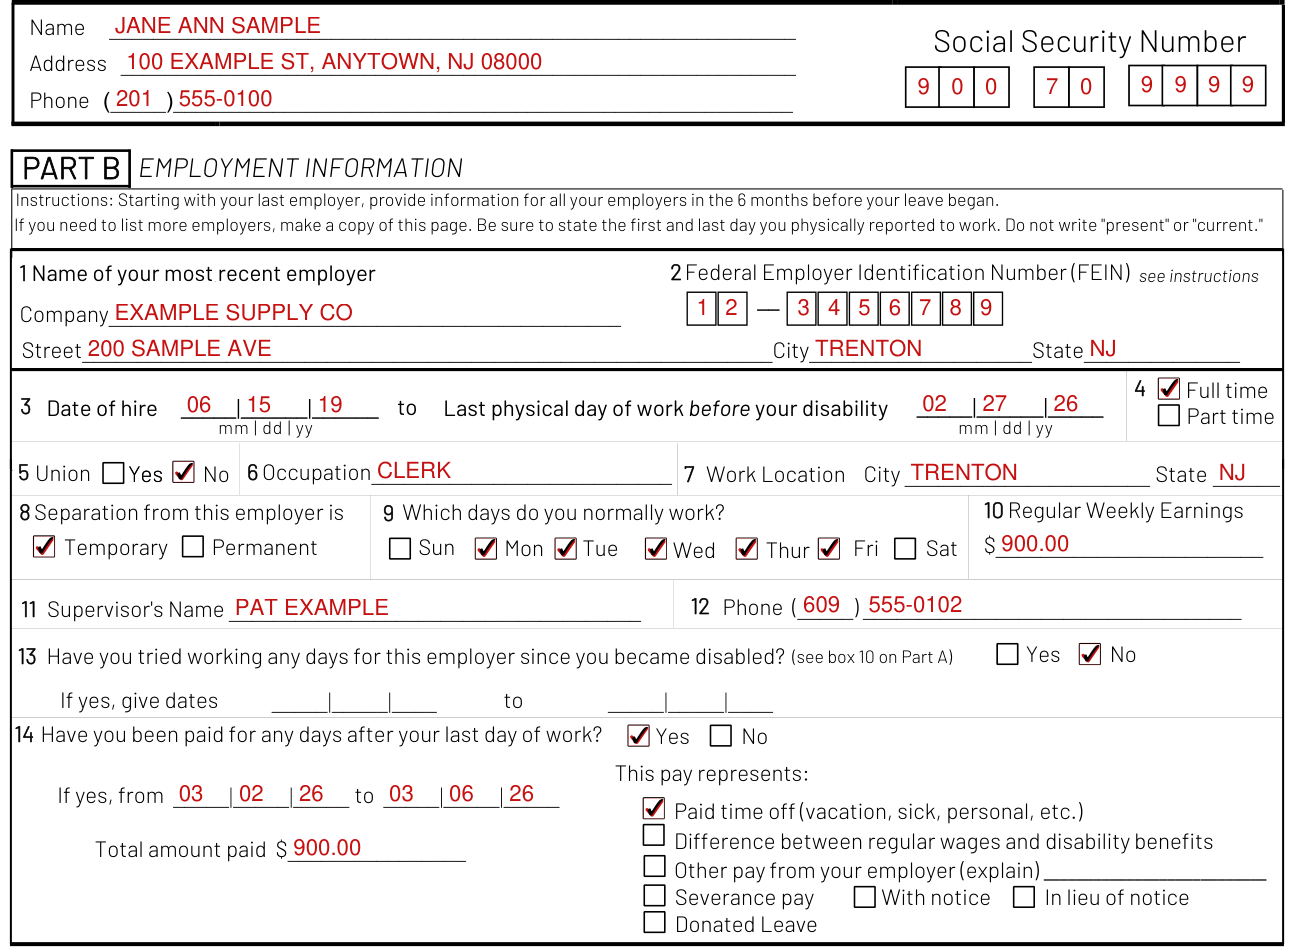
Starting with your last employer, provide information for all your employers in the 6 months before your leave began.
In box 1, enter the Name of your most recent employer. In box 2, enter its Federal Employer Identification Number (FEIN).
Enter the Company, and the Street, City and State.
In box 3, enter the Date of hire and the Last physical day of work before your disability.
Be sure to state the first and last day you physically reported to work.
Exact dates must be given. Do not write "present" or "current."
In box 4, check Full time or Part time. In box 5, check Yes or No for Union.
In box 6, enter your Occupation. In box 7, enter the Work Location City and State.
In box 8, check Temporary or Permanent for Separation from this employer. Then check Which days do you normally work: Sun, Mon, Tue, Wed, Thur, Fri or Sat.
In box 10, enter the Regular Weekly Earnings. In box 11, enter the Supervisor's Name and Phone.
In box 13, check Yes or No: Have you tried working any days for this employer since you became disabled? If yes, give dates.
Check Yes or No: Have you been paid for any days after your last day of work? If yes, enter from and to.
Check what This pay represents: Paid time off, Difference between regular wages and disability benefits, Other pay from your employer (explain), Severance pay (With notice or In lieu of notice) or Donated Leave. Enter the Total amount paid.
If you need to list more than 2 employers, make a copy of Part B to list additional employment.
More rules for Form DS-1
You must complete every question accurately and write legibly.
Any missing information may cause your claim to be denied.
Write your name and Social Security number on each page of your claim and on all attachments.
Benefits may be reduced or denied for late applications.
If your situation is different
Claiming benefits for family caregiving or bonding
If you wish to claim benefits for family caregiving or bonding, complete the application for Family Leave Benefits (form FL-1).
After being approved for Temporary Disability benefits
You may receive a form (P-30). Use this form to claim additional benefits.
You return to work while you are claiming Temporary Disability benefits
If you return to work while you are claiming Temporary Disability benefits, report this date immediately to the Division of Temporary Disability Insurance to avoid overpayment.
You filed your claim online
If you filed your claim online, do not also submit a paper application.
Common questions about Form DS-1
Is there a deadline?
You have 30 days from the first day of your disability to file your claim. If your claim form is received more than 30 days from the first day of your leave, you must provide a reason why the claim was not filed on time.
Where do I file it?
There are 2 options for you to submit this form. Fax this completed form to 609-984-4138. Mail this completed form to: Division of Temporary Disability Insurance / P.O. Box 387 / Trenton, NJ 08625-0387. Choose only one, as sending multiple copies will delay processing.
Are there fees?
N.J.S.A 12:18-1.6 prohibits charging a fee to complete this form.
Where to get help with Form DS-1
You can find information and check your claim status at myLeaveBenefits.nj.gov
For more help on your claim, call Customer Service at 609-292-7060.
Sources
[1] Form DS-1 (6/19), Temporary Disability Benefits Application, New Jersey Department of Labor and Workforce Development (the Official source link on this page).