


AHCA Form 5000-3008 at a glance
What it is: AHCA Form 5000-3008 is the Medical Certification for Medicaid Long-Term Care Services and Patient Transfer Form.
Who signs: Sign the Physician/ARNP/PA Signature line (AHCA Form: * marks sections required for Medicaid).
What to bring and attach to AHCA Form 5000-3008
Attach the list of all medications; the AHCA Form marks it * as data required for Medicaid.
A filled-in AHCA Form 5000-3008 example: a hospital nurse transfers a patient

How to fill out AHCA Form 5000-3008, box by box
A. Patient information

Enter the Patient Name, Last 4 SSN and DOB. Mark Male or Female for Gender, and Yes or No for Hispanic Ethnicity (AHCA Form: * marks data required for Medicaid).
For Race, mark White, Black or Other and write the Other; for Language, mark English or Other and write the Other (AHCA Form: * marks data required for Medicaid).
B. Sight and hearing

For Sight, mark Normal, Impaired or Blind; for Hearing, mark Normal, Impaired, Deaf or Hearing Aid, and mark L or R for a Hearing Aid (AHCA Form: * marks data required for Medicaid).
C. Decision making capacity

Under Decision Making Capacity (Patient), mark Capable to make healthcare decisions or Requires a surrogate.
D. Emergency contact

Enter the Name and Phone of the emergency contact, then the Name and Phone of a second one (AHCA Form: * marks data required for Medicaid).
E. Medical condition

Enter the Primary diagnosis and the Other diagnoses.
If Hospitalized, enter the Primary diagnosis at discharge and the Reason for transfer. List the Surgical procedures performed.
F. Infection control issues

Under Infection Control Issues, for PPD Status, mark Positive, Negative or Not known, and enter the Screening date.
Under Associated Infections/resistant organisms, mark MRSA, VRE, ESBL, MDRO, C-Diff or Other, and enter the Site.
For Isolation Precautions, mark Contact, Droplet, Airborne or None.
G. Patient risk alerts

Under Patient Risk Alerts, mark None Known, Elopement, Pressure Ulcers, Difficulty swallowing, Seizures, Other, Harm to self, Harm to others or Falls (AHCA Form: * marks data required for Medicaid).
For RESTRAINTS, mark Yes or No and enter the Reasons for use.
For ALLERGIES, mark None Known or Yes and list them in the ALLERGIES box.
Mark Yes or No for Latex Allergy and for Dye Allergy/Reaction, and enter the Latex Allergy and the Dye Allergy/Reaction.
H. Advance care planning

Please attach any relevant documentation. Mark Yes or No for Advance Directive, Living Will, DO NOT Resuscitate (DNR) and DO NOT Intubate. Mark Yes or No for DO NOT Hospitalize, No Artificial Feeding and Hospice.
I. Transferred from
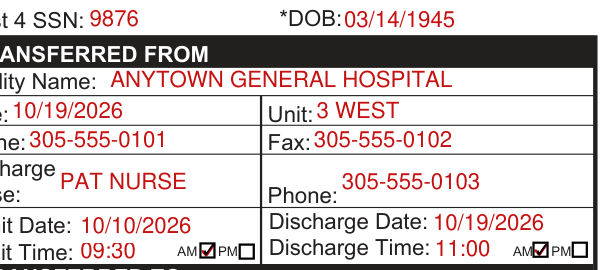
Under Transferred From, enter the Facility Name, Date, Unit, Phone, Fax, Discharge Nurse and Phone.
Enter the Admit Date, Admit Time, Discharge Date and Discharge Time, and mark AM or PM for each time.
J. Transferred to

Under Transferred To, enter the Facility Name, Address 1, Address 2, Phone and Fax.
K. Physician contacts

Under Physician Contacts, enter the Primary Care Name and Phone, and the Hospitalist Name and Phone.
L. Time sensitive condition specific information
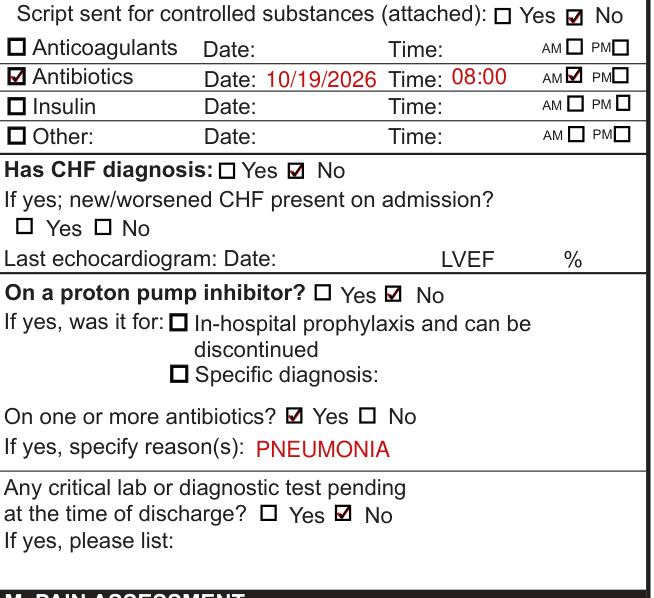
Under Time Sensitive Condition Specific Information, for Medication due near time of transfer, mark Anticoagulants, Antibiotics, Insulin or Other, and enter the Date and Time it was last administered, marking AM or PM.
Mark Yes or No for Script sent for controlled substances (attached).
Mark Yes or No for Has CHF diagnosis. If yes, mark Yes or No for new/worsened CHF present on admission.
Enter the Date of the Last echocardiogram and the LVEF %.
Mark Yes or No for On a proton pump inhibitor. If yes, was it for: mark In-hospital prophylaxis and can be discontinued, or mark Specific diagnosis and enter it.
Mark Yes or No for On one or more antibiotics. If yes, specify reason(s).
Mark Yes or No for any critical lab or diagnostic test pending at the time of discharge. If yes, please list.
M. Pain assessment

Enter the Pain Level (between 0 - 10) and the Last administered Date and Time, marking AM or PM.
N. Following reports attached

Under Following Reports Attached, mark each report attached: Physicians Orders, Discharge Summary, Medication Reconciliation, Discharge Medication List, PASRR Forms, Treatment Orders, History & Physical or Social and Behavioral History, and Includes Wound Care, Lab reports, X-ray, EKG, MRI or CT (AHCA Form: * marks data required for Medicaid).
O. Vital signs
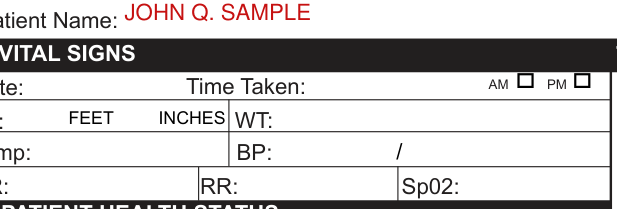
Enter the Date and Time Taken, marking AM or PM, then HT in FEET and INCHES, WT, BP, Temp, HR, RR and Sp02.
P. Patient health status
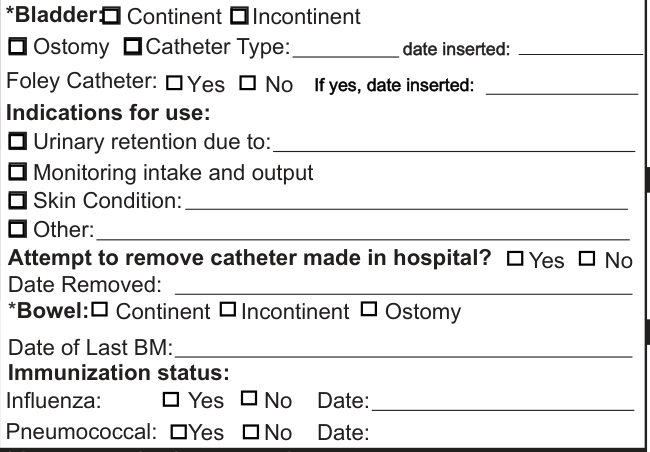
Under Patient Health Status, for Bladder, mark Continent, Incontinent, Ostomy or Catheter, and enter the Catheter Type and date inserted. For Foley Catheter, mark Yes or No; If yes, enter the date inserted (AHCA Form: * marks sections required for Medicaid).
For Indications for use, mark Urinary retention due to, Monitoring intake and output, Skin Condition or Other, and enter what each is due to.
Mark Yes or No for Attempt to remove catheter made in hospital, and enter the Date Removed. For Bowel, mark Continent, Incontinent or Ostomy.
Enter the Date of Last BM. For Immunization status, mark Yes or No and enter the Date for Influenza and for Pneumococcal.
Q. Nutrition and hydration

Under Nutrition / Hydration, enter the Dietary Instructions. For Tube Feeding, mark G-tube, J-tube or PEG and enter the PEG Insertion Date (AHCA Form: * marks sections required for Medicaid).
For Supplements (type), mark TPN or Other and enter the Supplements. For Eating, mark Self, Assistance or Difficulty Swallowing.
R. Treatments and frequency

Under Treatments and Frequency, mark PT, OT, Speech or Dialysis and enter its Frequency.
S. Physical function

For Ambulation, mark Not ambulatory, Ambulates independently, Ambulates with assistance or Ambulates with assistive device (AHCA Form: * marks sections required for Medicaid).
For Transfer, mark Self, Assistance, 1 Assistant or 2 Assistants.
For Devices, mark the Wheelchair (type), Appliances, Prosthesis or Lifting Device and enter its type.
For Weight-bearing, mark Full, Partial or None for Left and for Right.
T. Skin care stage and assessment

Under Pressure Ulcers, indicate the stage and location(s) of lesions using corresponding number on lines 1, 2 and 3, and list any other lesions or wounds.
U. Mental cognitive status at transfer
Mark the status: Alert, oriented, follows instructions; Alert, disoriented, but can follow simple instructions; Alert, disoriented, and cannot follow simple instructions; or Not Alert (AHCA Form: * marks sections required for Medicaid).
V. Treatment devices
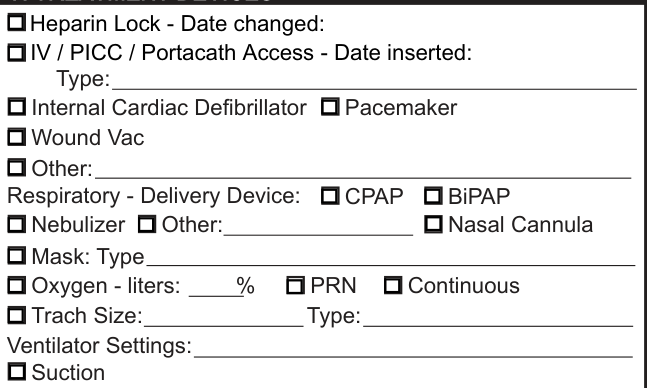
Under Treatment Devices, mark IV / PICC / Portacath Access or Heparin Lock, and enter its Date inserted or Date changed.
Mark Internal Cardiac Defibrillator, Pacemaker, Wound Vac or Other, and enter the Type. Under Respiratory - Delivery Device, mark CPAP, BiPAP, Nasal Cannula, Nebulizer Mask, Oxygen, PRN, Continuous or Suction, and enter the Ventilator Settings.
W. Personal items

Mark Artificial Eye, Prosthetic, Contacts, Cane, Eyeglasses, Crutches, Dentures, Walker, Hearing Aids or Other.
X. Comments

Enter Comments (Optional).
Y. Physician certification
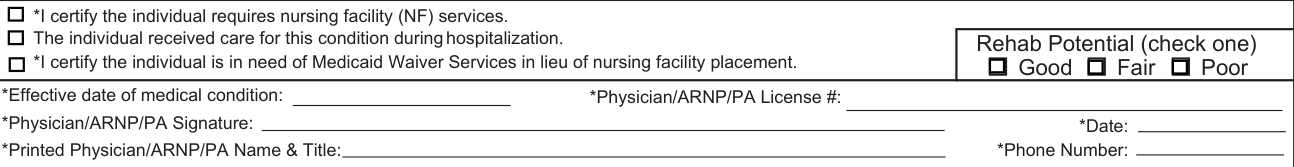
Check the box for each of these that applies: the individual requires nursing facility (NF) services; the individual received care for this condition during hospitalization; the individual is in need of Medicaid Waiver Services in lieu of nursing facility placement (AHCA Form: * marks sections required for Medicaid).
Check one Rehab Potential: Good, Fair or Poor.
Under Physician Certification, enter the Physician/ARNP/PA License #, the Effective date of medical condition, the Date, the Phone Number, and the Printed Physician/ARNP/PA Name & Title (AHCA Form: * marks sections required for Medicaid).
Z. Person completing form

Enter the Name, Date and Phone Number of the Person Completing Form.
More rules for AHCA Form 5000-3008
On AHCA Form 5000-3008, * marks data required for Medicaid on the first page and sections required for Medicaid on the second page.
Sources
[1] AHCA Form 5000-3008 (JUN 2016), Medical Certification for Medicaid Long-Term Care Services and Patient Transfer Form, Florida Agency for Health Care Administration (the Official source link on this page).