Ny Ambulance Call PDF Details

In the bustling metropolis of New York City, the Fire Department's Public Records Unit / ACR Section provides an essential service through the Ambulance Call Report/Prehospital Care Report Request Form. Located at 9 MetroTech Center in Brooklyn, this form is a critical tool for individuals seeking to obtain records of ambulance services provided by the city. It meticulously outlines the process for requesting these reports, emphasizing the need for accurate customer and patient information, including names, addresses, and detailed descriptions of the incident. Importantly, the form underscores the necessity of accompanying the request with a check or money order payable to the NYC Fire Department, alongside a self-addressed envelope for the response. Moreover, it stresses the importance of not sending cash and provides clear guidelines on submitting proof of relationship to the patient, whether it be through notarized letters, proof of guardianship for minors, or court documents for estate executors. With a nominal fee of $1.50 per report, this document symbolizes a blend of bureaucratic procedure and the vital need for access to one's medical records, encapsulating the city's commitment to transparency and individual rights in prehospital care scenarios.

QuestionAnswer
Form NameNy Ambulance Call
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesambulance request form, fillable ambulance call report request form, ambulance call report, fdny ambulance call report

How to Fill Out Ambulance Call Report / Prehospital Care Report Request Form

Ambulance Call Report / Prehospital Care Report Request Form at a glance

What it is: Request Form for the Ambulance Call Report / Prehospital Care Report of the Fire Department - City of New York.

Where and when to file: Public Records Unit / ACR Section, Fire Department - City of New York, 9 MetroTech Center, Brooklyn, New York 11201-3857, (718) 999-1998 or 1999.

A filled-in Ambulance Call Report / Prehospital Care Report Request Form example: a patient requests her own report

Ambulance Call Report / Prehospital Care Report Request Form example filled out, example: a patient requests her own report
Jane Sample requests her own ambulance call report from the Fire Department. She was taken to a hospital at 9:30 PM and is not a minor, so she checks NO. YES stays empty because she is not a minor. PM is checked and AM stays empty because the incident was at 9:30 PM. Because she is the patient, she checks Self / Patient, so the other relationship boxes stay empty and nothing goes in Other. The picture shows the filled form, and every value in it is made up.

How to fill out Ambulance Call Report / Prehospital Care Report Request Form, box by box

Customer information

Ambulance Call Report / Prehospital Care Report Request Form example filled out, customer information

Under Section A, Customer Information, print the required information: Name, Telephone Number, Address, State and Zip Code.

Patient information and the incident
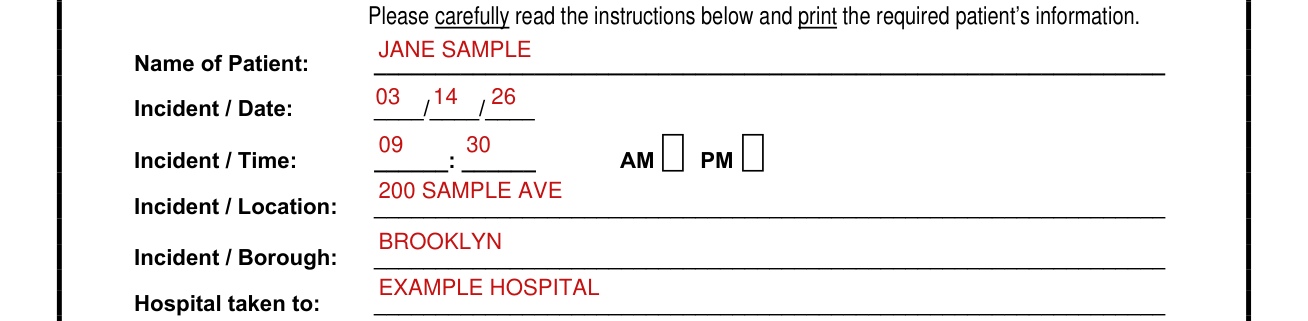
Ambulance Call Report / Prehospital Care Report Request Form example filled out, patient information and the incident

Under Section B, Patient Information, print the required patient's information: Name of Patient, Incident / Date, Incident / Time (AM or PM), Incident / Location, Incident / Borough and Hospital taken to.

Is the patient a minor, date of birth and Social Security Number

Ambulance Call Report / Prehospital Care Report Request Form example filled out, is the patient a minor, date of birth and Social Security Number

Is the patient a minor (please check only one box)? YES or NO.

Enter the Date of Birth, the Last 4 digits of Social Security Number and, if you have the ACR/PCR, please provide ACR/PCR number.

Relationship to the patient

Ambulance Call Report / Prehospital Care Report Request Form example filled out, relationship to the patient

Check only one box for the requester's relationship to the patient: Self / Patient, Parent / Guardian, Executor / Administrator of Estate or Other.

If your situation is different

Customer - please read and submit the required items

Submit the required items: An original notarized letter from the patient authorizing the release of this information. Proof of parental status or guardianship, if the patient is a minor. Acceptable proof is a copy of the patient's birth certificate or a court document showing custody / guardianship. Proof that a court has appointed you executor or administrator of the patient's estate, if the patient is deceased (Letters testamentary or letters of administration). Payment in the form of a check or money order in the amount of $1.50 for each report (checked November 14, 2026).

Common questions about Ambulance Call Report / Prehospital Care Report Request Form

Where do I file it?

Complete this form and attach all required documents. Enclose a check or money order made payable to the NYC Fire Department and a stamped self-addressed envelope (with postage). Mail checks or money orders directly to the Public Records Unit / ACR Section, 9 MetroTech Center, Brooklyn, New York 11201-3857. Only money orders or checks will be accepted for Requests (no exceptions). DO NOT MAIL CASH.

Sources

[1] Ambulance Call Report / Prehospital Care Report Request Form (PR1 July-08), Fire Department - City of New York (the Official source link on this page).

Please rate Ny Ambulance Call

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .