

Form C-9 at a glance
What it is: Form C-9 (BWC-1113) is for a request for services, even if services are being provided under the 60-day presumptive authorization, for recommending additional condition(s), or if diagnosis has changed.
Who signs: Physician/provider/authorized signature (required), individual BWC provider number (required), and date of this report (required) are mandatory.
Where to get it: You can obtain additional copies of this form at bwc.ohio.gov or by calling 1-800-644-6292 and listening to the options.
What to bring and attach to Form C-9
Attach copies of current medical reports necessary to support the request. Include any referrals, therapy, medications, diagnostic testing, expected outcomes of medical interventions, results of treatment, and office notes that contain subjective and objective findings and pre-existing conditions.
A filled-in Form C-9 example: a physician requests two services for an injured worker
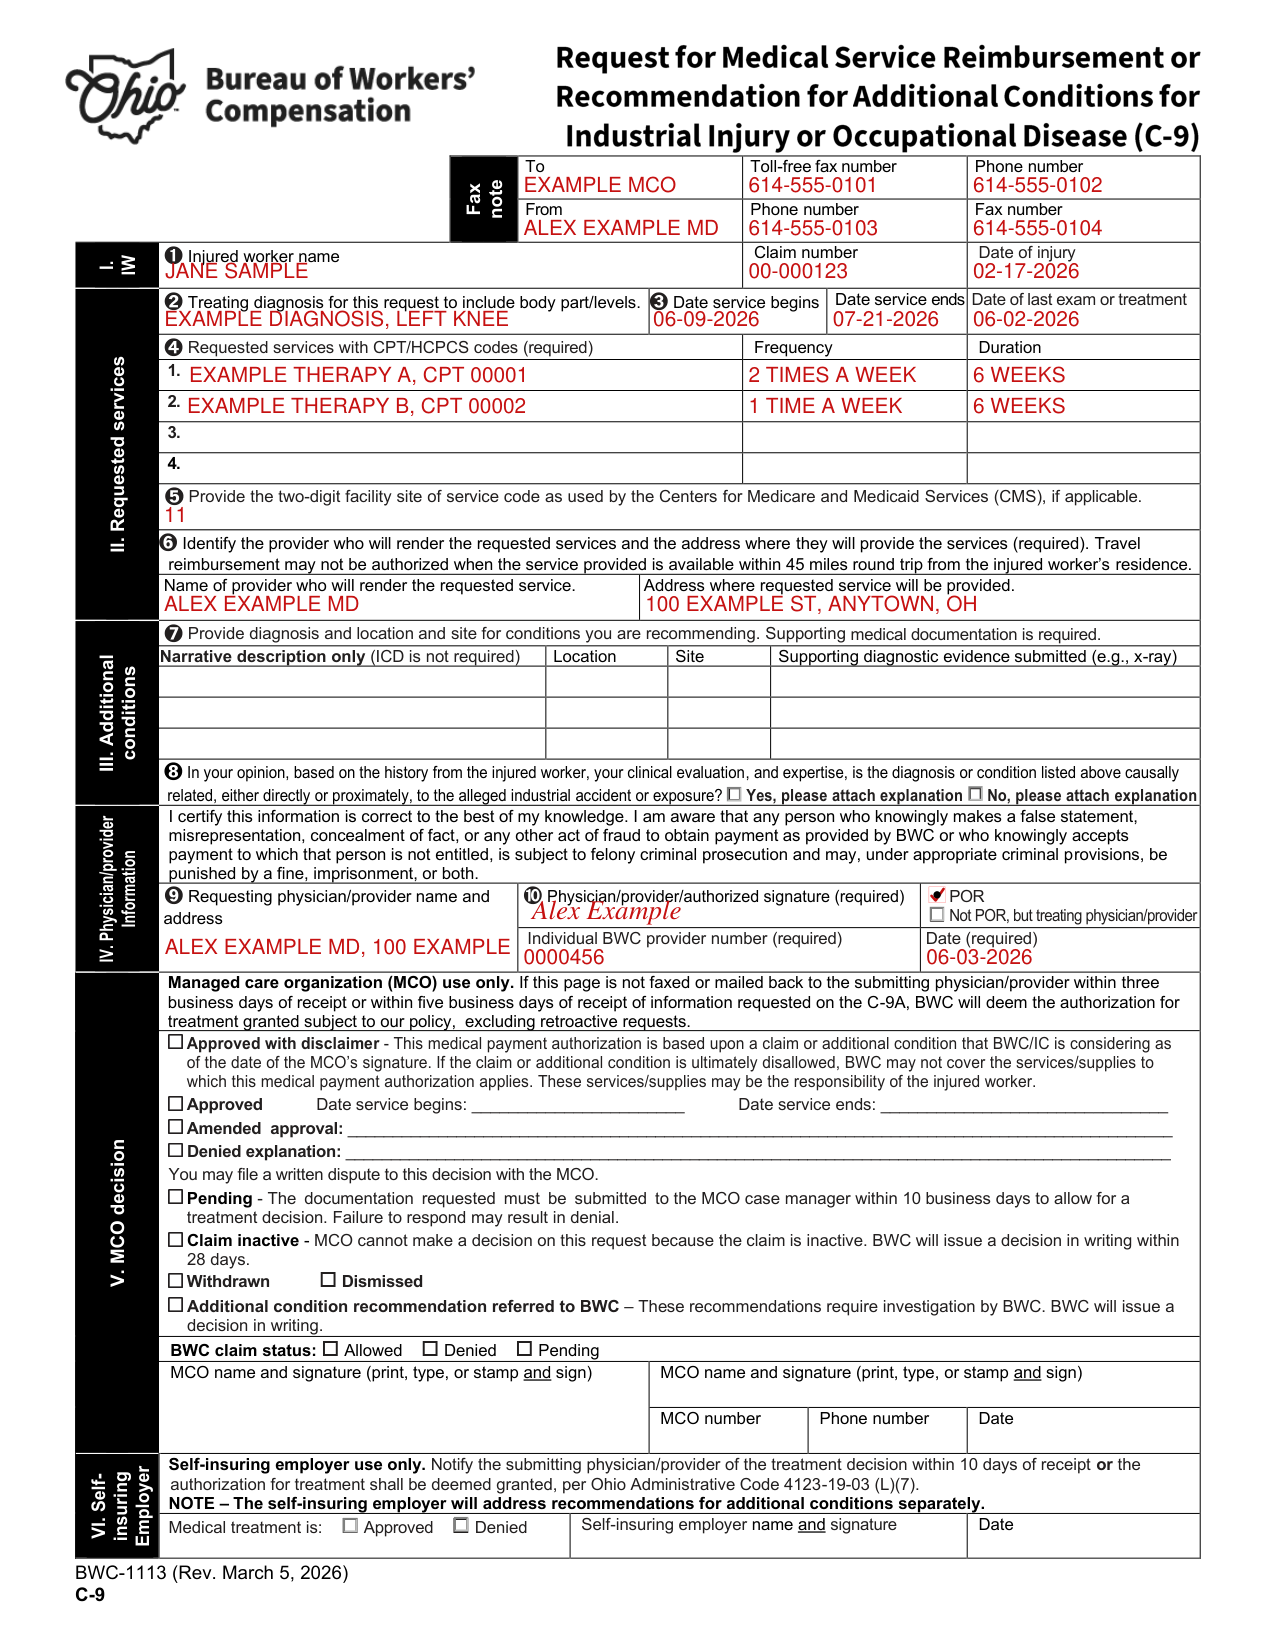
How to fill out Form C-9, box by box
To, From and Injured worker

If the injured worker is employed by a self-insuring employer, complete this form and fax or mail it to their employer. If the injured worker is employed by a state-fund employer, complete this form and fax or mail it to the appropriate managed care organization (MCO).
The assigned MCO can be found at bwc.ohio.gov, or by calling 1-800-644-6292 and listening to the options.
Enter the injured worker's name, BWC claim number, and the date the injured worker was injured or contracted an occupational disease (Date of injury).
Treating diagnosis and the dates of service

Enter the treating diagnosis for this request, to include body part/levels. Indicate the beginning and ending date of the requested service (Date service begins and Date service ends), and the date of the last exam or treatment.
Requested services with CPT/HCPCS codes
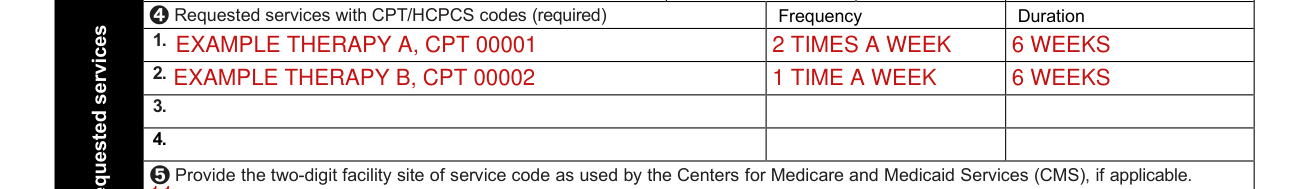
List the requested services with CPT/HCPCS codes (required), including frequency and duration. Failure to add CPT codes may delay processing.
Facility site of service code

Enter the two-digit facility site of service code as used by the Centers for Medicare and Medicaid Services (CMS), if applicable.
Provider who will render the requested services
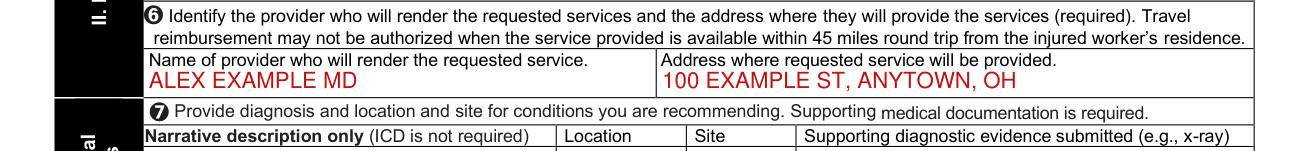
Identify the provider who will render the requested services and the address where they will provide the services (required): the Name of provider who will render the requested service, and the Address where requested service will be provided.
Travel reimbursement may not be authorized when the service provided is available within 45 miles round trip from the injured worker's residence.
Section III, Additional conditions
Complete if you are recommending additional conditions to the claim.
Provide diagnosis and location and site for conditions you are recommending. Provide a narrative diagnosis. Enter the narrative description only (ICD is not required), Location, Site and Supporting diagnostic evidence submitted (e.g., x-ray).
Supporting medical documentation is required for all conditions listed.
For state-fund claims, BWC will notify all parties and the MCO of the decision regarding the additional condition(s) recommendation.
Provide indication of causality by checking yes or no and attach an explanation of your opinion to the C-9. In your opinion, based on the history from the injured worker, your clinical evaluation, and expertise, is the diagnosis or condition listed causally related, either directly or proximately, to the alleged industrial accident or exposure?
Section IV, Physician/provider information

Print, type, or stamp requesting physician/provider name and address.
Physician/provider/authorized signature (required), individual BWC provider number (required), and date of this report (required) are mandatory.
Mark POR or Not POR, but treating physician/provider.
The form prints this certification: I certify this information is correct to the best of my knowledge.
The form prints this statement: I am aware that any person who knowingly makes a false statement, misrepresentation, concealment of fact, or any other act of fraud to obtain payment as provided by BWC or who knowingly accepts payment to which that person is not entitled, is subject to felony criminal prosecution and may, under appropriate criminal provisions, be punished by a fine, imprisonment, or both.
Section V, MCO decision
Managed care organization (MCO) use only. If this page is not faxed or mailed back to the submitting physician/provider within three business days of receipt or within five business days of receipt of information requested on the C-9A, BWC will deem the authorization for treatment granted subject to BWC policy, excluding retroactive requests.
Pending: the documentation requested must be submitted to the MCO case manager within 10 business days to allow for a treatment decision. Failure to respond may result in denial.
Claim inactive: MCO cannot make a decision on this request because the claim is inactive. BWC will issue a decision in writing within 28 days.
Additional condition recommendation referred to BWC: these recommendations require investigation by BWC. BWC will issue a decision in writing.
Approved with disclaimer: this medical payment authorization is based upon a claim or additional condition that BWC/IC is considering as of the date of the MCO's signature. If the claim or additional condition is ultimately disallowed, BWC may not cover the services/supplies to which this medical payment authorization applies. These services/supplies may be the responsibility of the injured worker.
You may file a written dispute to this decision with the MCO.
Section VI, Self-insuring employer
Self-insuring employer use only. Notify the submitting physician/provider of the treatment decision within 10 days of receipt or the authorization for treatment shall be deemed granted, per Ohio Administrative Code 4123-19-03 (L)(7).
The self-insuring employer will address recommendations for additional conditions separately.
Before you go
Please print legibly.
Complete all applicable sections of the form to avoid possible delays in processing this request.
Common questions about Form C-9
What is a C9 form in Ohio?
Form C-9 (BWC-1113) is for a request for services, even if services are being provided under the 60-day presumptive authorization, for recommending additional condition(s), or if diagnosis has changed.
Sources
[1] Form C-9 (BWC-1113) (Rev. March 5, 2026), Ohio Bureau of Workers' Compensation (the Official source link on this page).
