Ohio Form Jfs 02390 PDF Details

The Ohio Jfs 02390 form is an essential document for those seeking authorization for Home Care Attendants (HCAs) to perform skilled tasks as part of home care services. Managed by the Ohio Department of Job and Family Services, this form is a critical tool in ensuring that home care recipients receive proper care tailored to their medical needs. Prospective users of the form are navigated through the process, which requires detailed information about the consumer, including their name, street address, Recipient ID, and a list of skilled tasks for which the attendant is trained. The form mandates the trainer, who could be the consumer or an authorized representative, to list out the medically necessary skilled tasks and ensure the attendant's training on these tasks is completed successfully. The authorization process is rigid, needing initials from an Authorized Health Care Professional (AHP) to validate the tasks once training is completed. Additionally, the form requires signatures from all parties involved, including the consumer or their authorized representative, the home care attendant, the trainer, and the AHP. This detailed documentation process is designed to protect all parties involved and guarantee that the care provided by the HCA meets the specific needs as per the Ohio Administrative Code rules and regulations.

QuestionAnswer
Form NameOhio Form Jfs 02390
Form Length3 pages
Fillable?Yes
Fillable fields71
Avg. time to fill out45 sec
Other namesinitialed, exclusion, CMA, carestar

How to Fill Out Ohio Department of Medicaid Form ODM 02390

Ohio Department of Medicaid Form ODM 02390 at a glance

What it is: This is the Ohio Department of Medicaid Home Care Attendant (HCA) Skilled Task Authorization form.

Who signs: Each team member must complete the section that applies to her/his role.

A filled-in Ohio Department of Medicaid Form ODM 02390 example: a trainer lists two approved skilled tasks
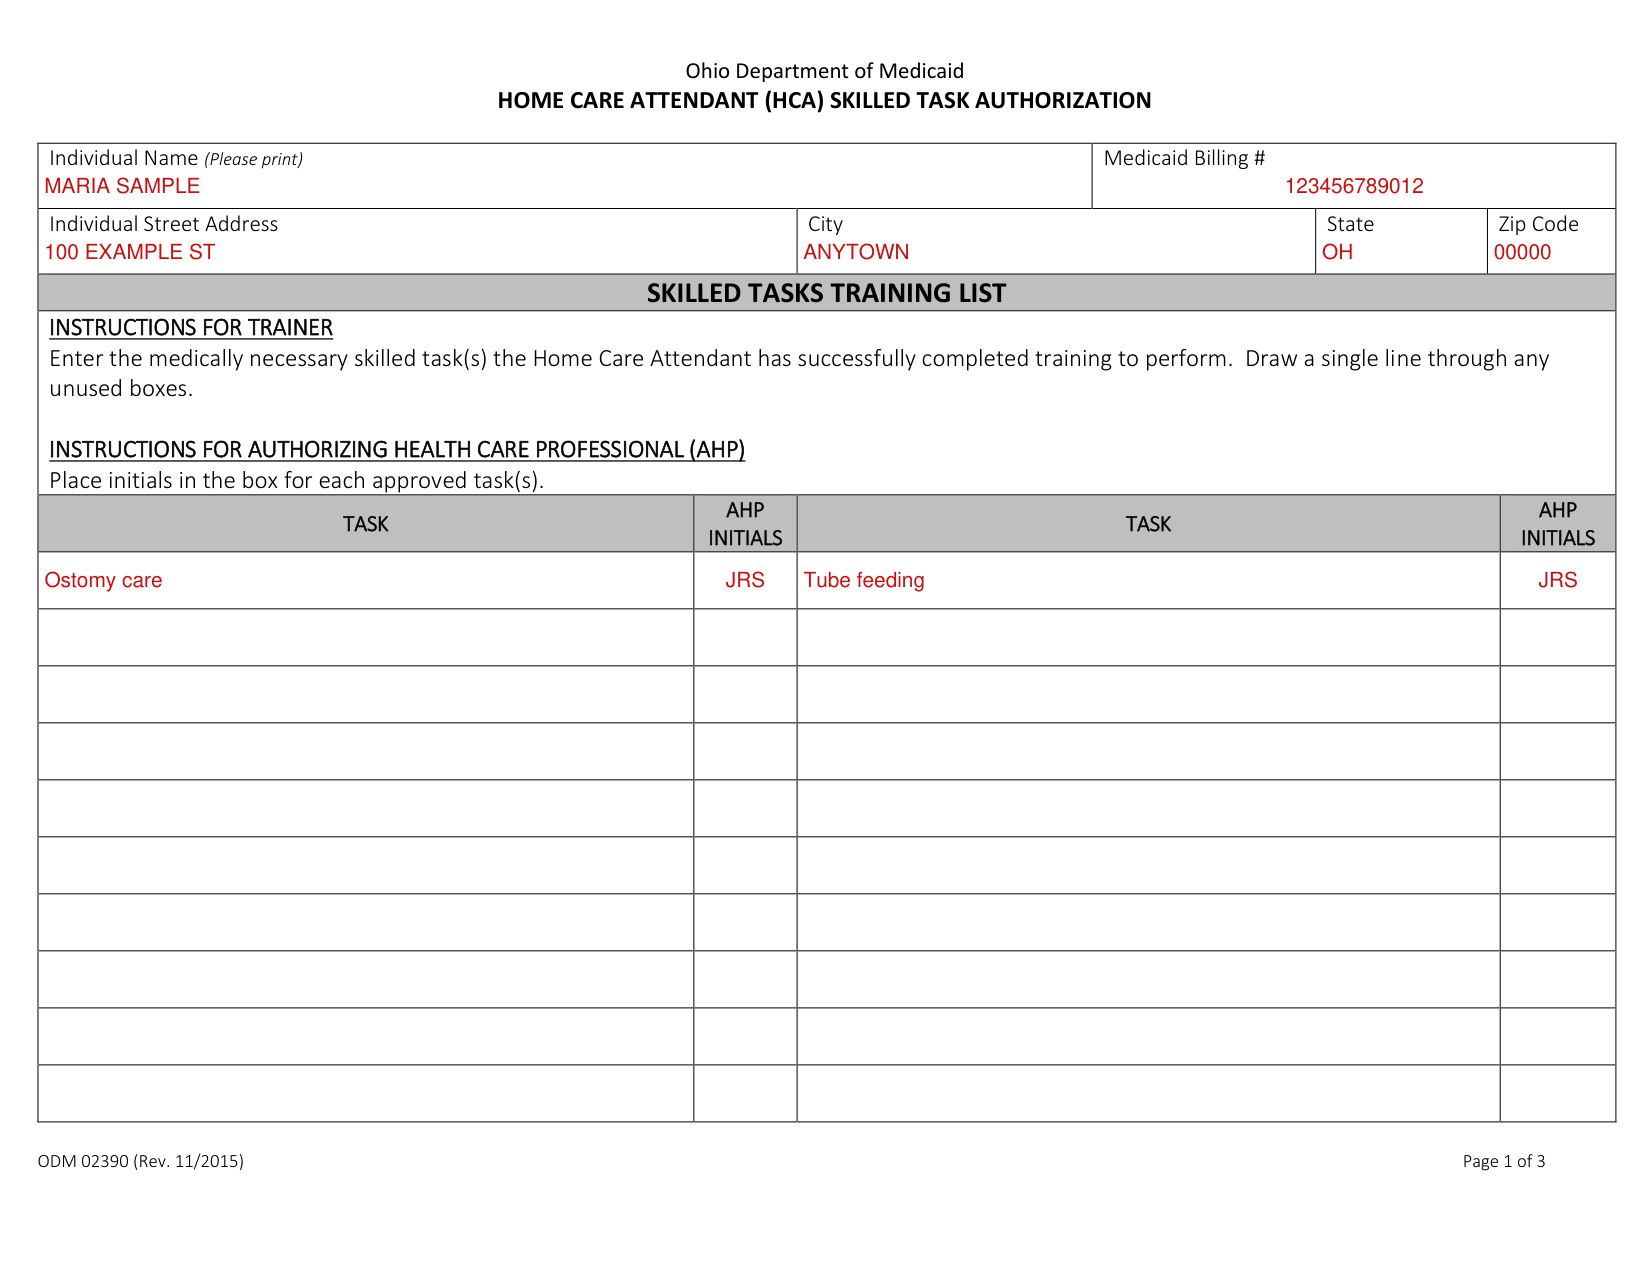
Ohio Department of Medicaid Form ODM 02390 example filled out, example: a trainer lists two approved skilled tasks
A trainer lists two skilled tasks on Maria Sample's authorization form. Two tasks are approved and initialed by her authorizing health care professional. The trainer draws a single line through the unused boxes of the Skilled Tasks Training List by hand after printing. Maria signs and initials as the individual on 01/05/2026, and the effective period runs 12 months from that date. The picture shows page 1 and every value in it is made up.

How to fill out Ohio Department of Medicaid Form ODM 02390, box by box

Individual Name, Medicaid Billing # and address
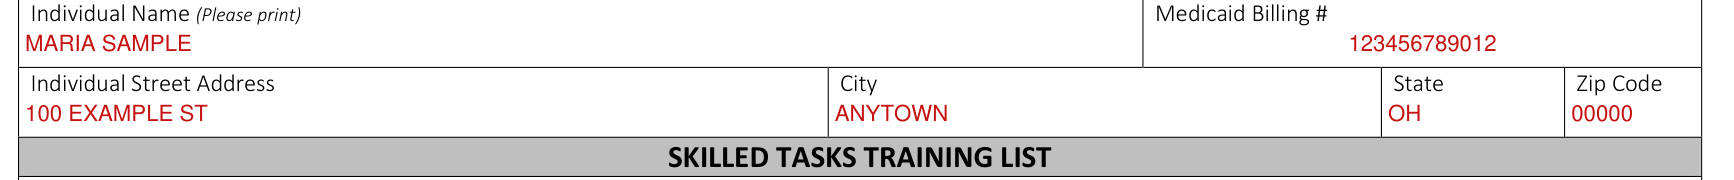
Ohio Department of Medicaid Form ODM 02390 example filled out, individual Name, Medicaid Billing # and address

Print the Individual Name (Please print), then fill in the Medicaid Billing # and the Individual Street Address, City, State and Zip Code.

Skilled Tasks Training List
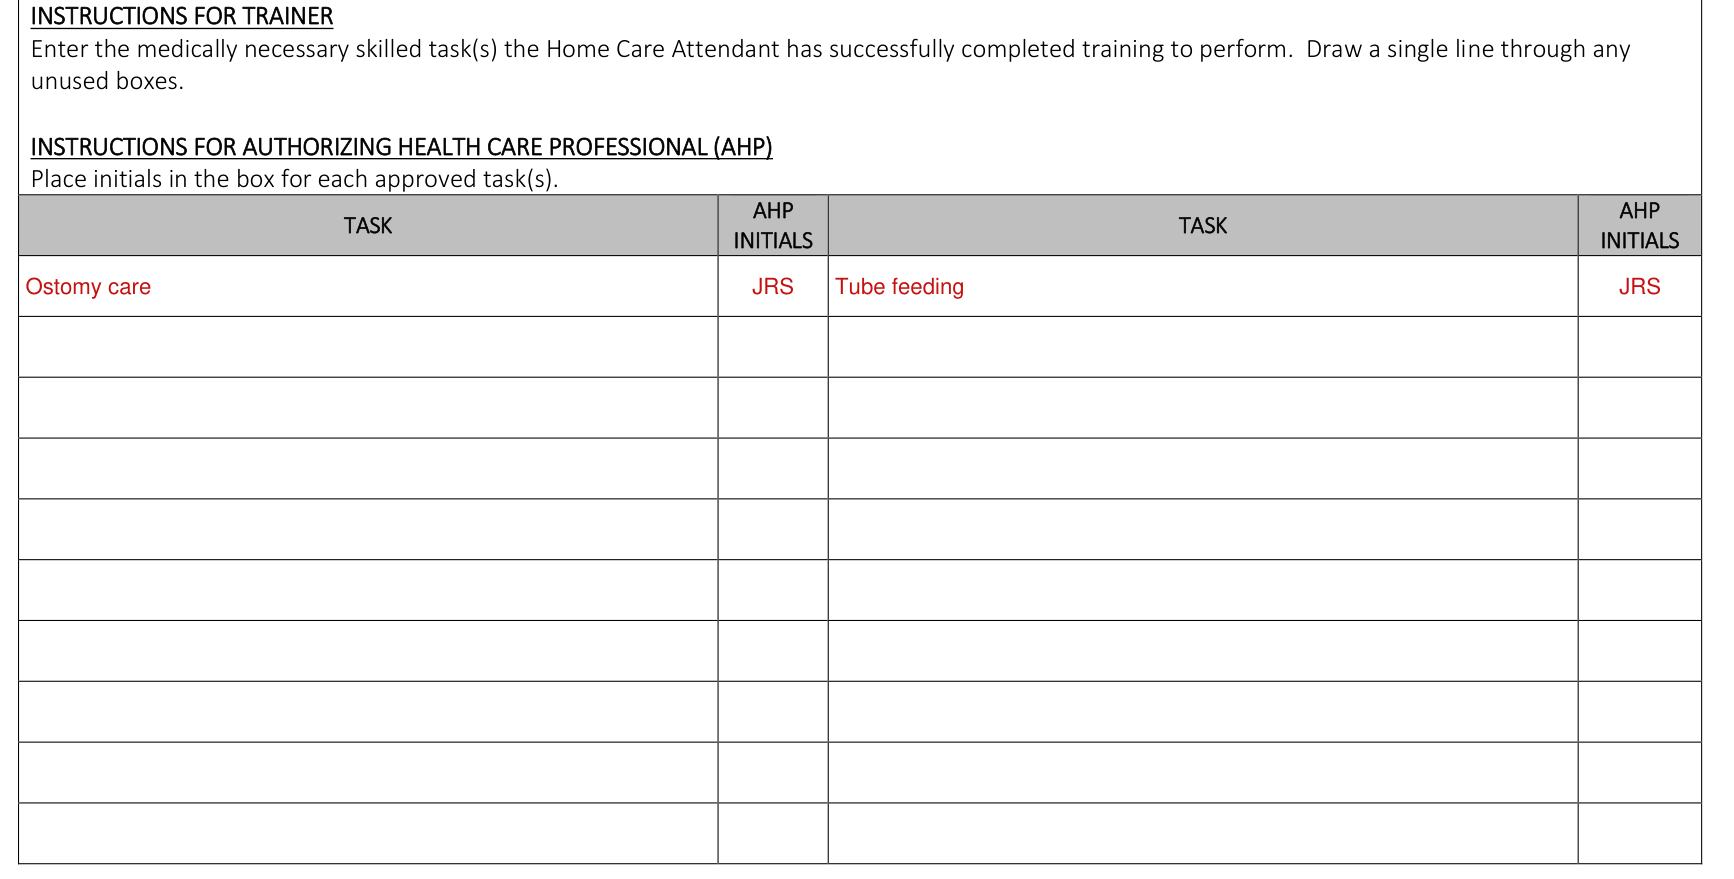
Ohio Department of Medicaid Form ODM 02390 example filled out, skilled Tasks Training List

Trainer: enter the medically necessary skilled task(s) the Home Care Attendant has successfully completed training to perform, and draw a single line through any unused boxes.

Authorizing health care professional (AHP): place initials in the box for each approved task(s).

Individual/Authorized Representative

The individual/authorized representative has received the necessary training and is electing to select, instruct and direct the Home Care Attendant (HCA) to perform the task(s) set forth on this form, and will ensure that the HCA performs the task(s) consistent with her/his training and in accordance with OAC Rule 5160-46-04.1, as appropriate.

This authorization may be revoked at any time by the authorizing health care professional, and the individual is responsible for reporting any changes in health or circumstances to the Case Management Agency (CMA) Case Manager, Trainer, HCA, and Authorizing Health Care Professional.

Individual/Authorized Representative: print Name (Please print), then Signature, Initials and Date Signed.

Home Care Attendant

Under Home Care Attendant, the undersigned has received training in the task(s) set forth on this form and will perform the task(s) in accordance with OAC Rule 5160-46-04.1, as appropriate, and as trained by the individual, authorized representative and/or trainer. The undersigned is approved to perform the listed task(s) for this individual, and understands that ODM may revoke that approval at any time if deemed necessary.

Under Home Care Attendant, the undersigned is responsible for reporting any changes in her/his ability to perform the task(s) to the Individual, CMA Case Manager, Trainer, and Authorizing Health Care Professional.

Home Care Attendant: Name (Please print), Signature, Initials and Date Signed.

Trainer

Under Trainer (Please read before signing and dating), the undersigned verify that the Home Care Attendant has successfully been trained to perform the task(s) set forth on this form.

Trainer Name (Please print), Signature, Initials and Date Signed.

Authorizing Health Care Professional and Trainer

Under Authorizing Health Care Professional and Trainer, the undersigned approves the individual's decision to select, instruct and direct the Home Care Attendant in the performance of the task(s) set forth on this form, and may revoke approval at any time, if deemed necessary, by notifying the Individual/Authorized Representative, CMA Case Manager, and Trainer.

Name (Please print), Signature, Initials, Date Signed, Emergency Phone Number (Including Area Code) and Fax Number (Including Area Code).

Customer/Authorized Representative and Authorizing Health Care Professional initials

In the event that no physician is aware of or supports the individual's decision to use the Home Care Attendant option, the Registered Nurse who is serving as the Authorizing Health Care Professional must be made aware of the physician's exclusion or non-support.

Add the Customer/Authorized Representative (Initials) and the Authorizing Health Care Professional (Initials) on the lines.

Effective Period (not to exceed 12 months)

Fill in the Individual Name (Please print), the Trainer Name (Please print) and the Effective Period (not to exceed 12 months) with a Start Date and an End Date.

Name of Task

Trainer: enter the name of the medically necessary skilled task required by the individual under Name of Task.

Enter the date the Home Care Attendant (HCA) completed training to successfully perform the skilled task, and write a detailed description of how HCA will perform the task, including times or intervals.

If the individual/authorized representative is the trainer, the individual/authorized representative will complete this section.

Check here if CONTINUED on next page.

Authorizing Health Care Professional initials

The HCA is not approved to perform the listed task(s) until though AHP has initialed the Training Detail page.

Authorizing Health Care Professional: My initials indicate approval of this task to be performed by the Home Care Attendant and that the Home Care Attendant has demonstrated the ability to perform the task. Initial here.

Sources

[1] ODM 02390 (Rev. 11/2015), Home Care Attendant (HCA) Skilled Task Authorization, Ohio Department of Medicaid (the Official source link on this page).

Please rate Ohio Form Jfs 02390 Rev. 11-2015

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .