

ODM02374 at a glance
What it is: This is the Ohio Department of Medicaid Private Duty Nursing (PDN) Service Request.
Where and when to file: Individual Completing Form: upload this form into PNM with additional clinical information, and enter the Name, Phone Number and Extension, and Email Address.
A filled-in ODM02374 example: a first request with no waiver
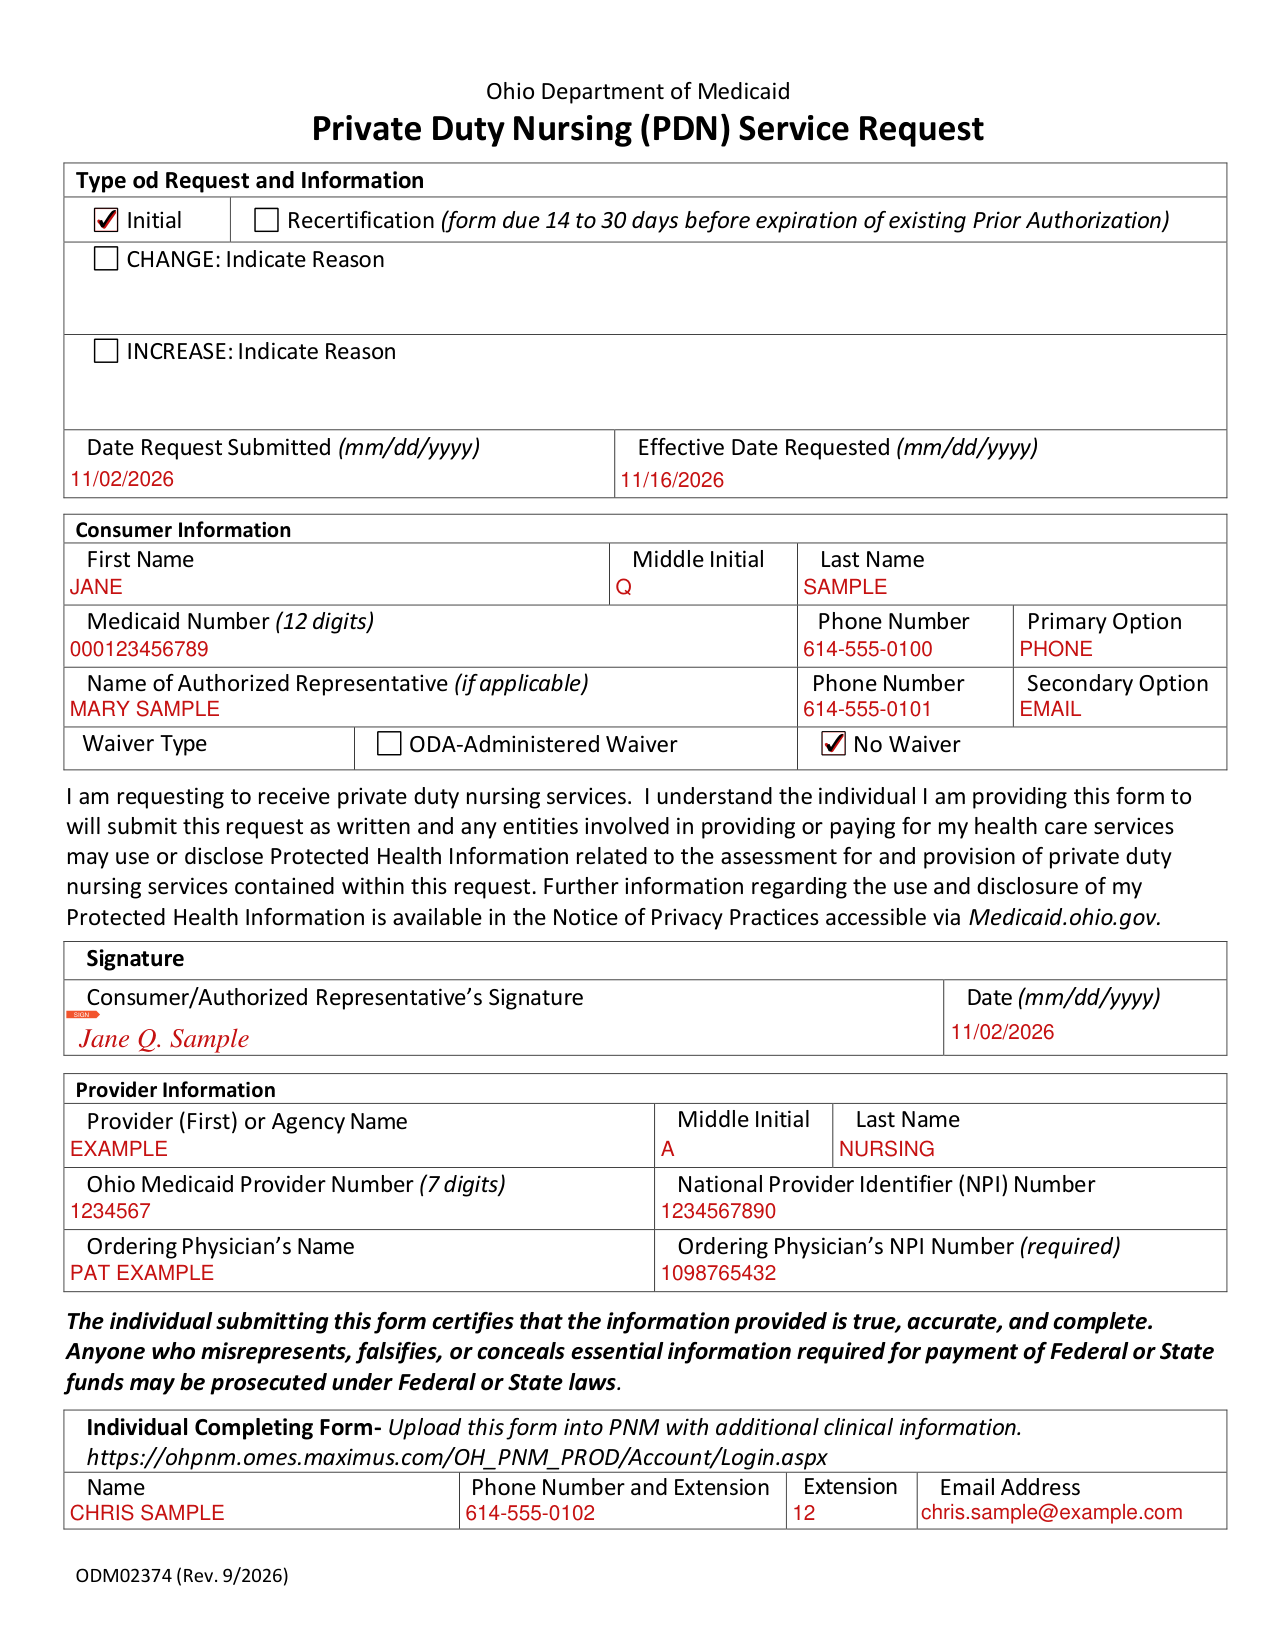
How to fill out ODM02374, box by box
Type of Request and Information
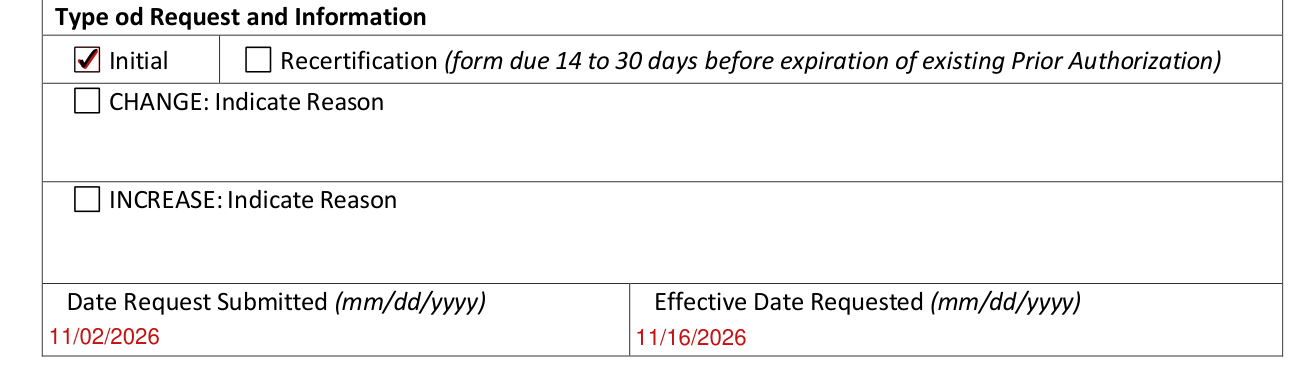
Under Type of Request and Information, mark Initial or Recertification; the Recertification form is due 14 to 30 days before expiration of existing Prior Authorization.
For CHANGE or INCREASE, mark the box and indicate the reason.
Enter the Date Request Submitted and the Effective Date Requested as mm/dd/yyyy.
Consumer Information
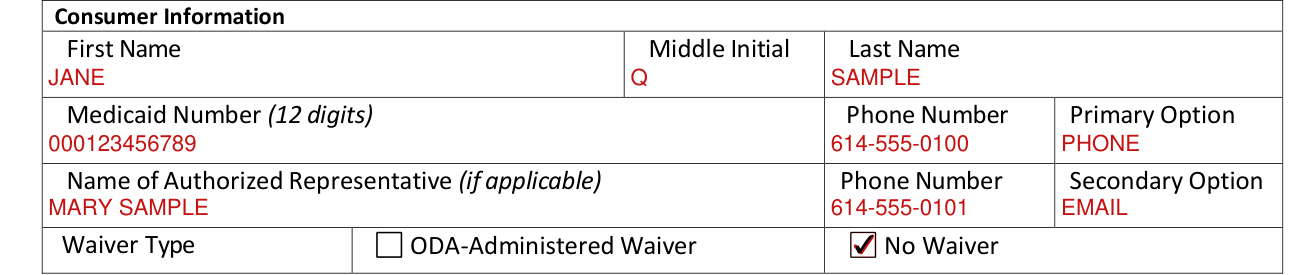
Under Consumer Information, enter the First Name, Middle Initial and Last Name.
Enter the Medicaid Number (12 digits), the Phone Number and the Primary Option.
Enter the Name of Authorized Representative (if applicable), the Phone Number and the Secondary Option.
Under Waiver Type, mark ODA-Administered Waiver or No Waiver.
Signature

The Consumer/Authorized Representative signs and enters the Date (mm/dd/yyyy).
Signature: I am requesting to receive private duty nursing services. I understand the individual I am providing this form to will submit this request as written and any entities involved in providing or paying for my health care services may use or disclose Protected Health Information related to the assessment for and provision of private duty nursing services contained within this request.
Provider Information
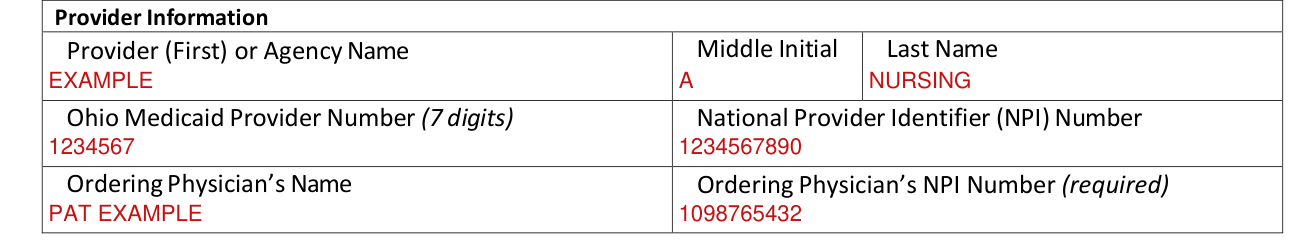
Under Provider Information, enter the Provider (First) or Agency Name, Middle Initial and Last Name.
Enter the Ohio Medicaid Provider Number (7 digits) and the National Provider Identifier (NPI) Number.
Enter the Ordering Physician's Name and the Ordering Physician's NPI Number (required).
Individual Completing Form

The individual submitting this form certifies that the information provided is true, accurate, and complete; anyone who misrepresents, falsifies, or conceals essential information required for payment of Federal or State funds may be prosecuted under Federal or State laws.
Sources
[1] ODM02374 (Rev. 9/2026), Private Duty Nursing (PDN) Service Request, Ohio Department of Medicaid (the Official source link on this page).