

Form DCY 01296 at a glance
What it is: Form DCY 01296 is the Employee Medical Statement for Child Care of the Ohio Department of Children and Youth.
Who signs: For the Signature of Health Care Provider*, this form may be signed by a licensed physician, physician's assistant, advanced practice registered nurse, certified nurse midwife or certified nurse practitioner.
A filled-in Form DCY 01296 example: a new child care staff member and the medical statement
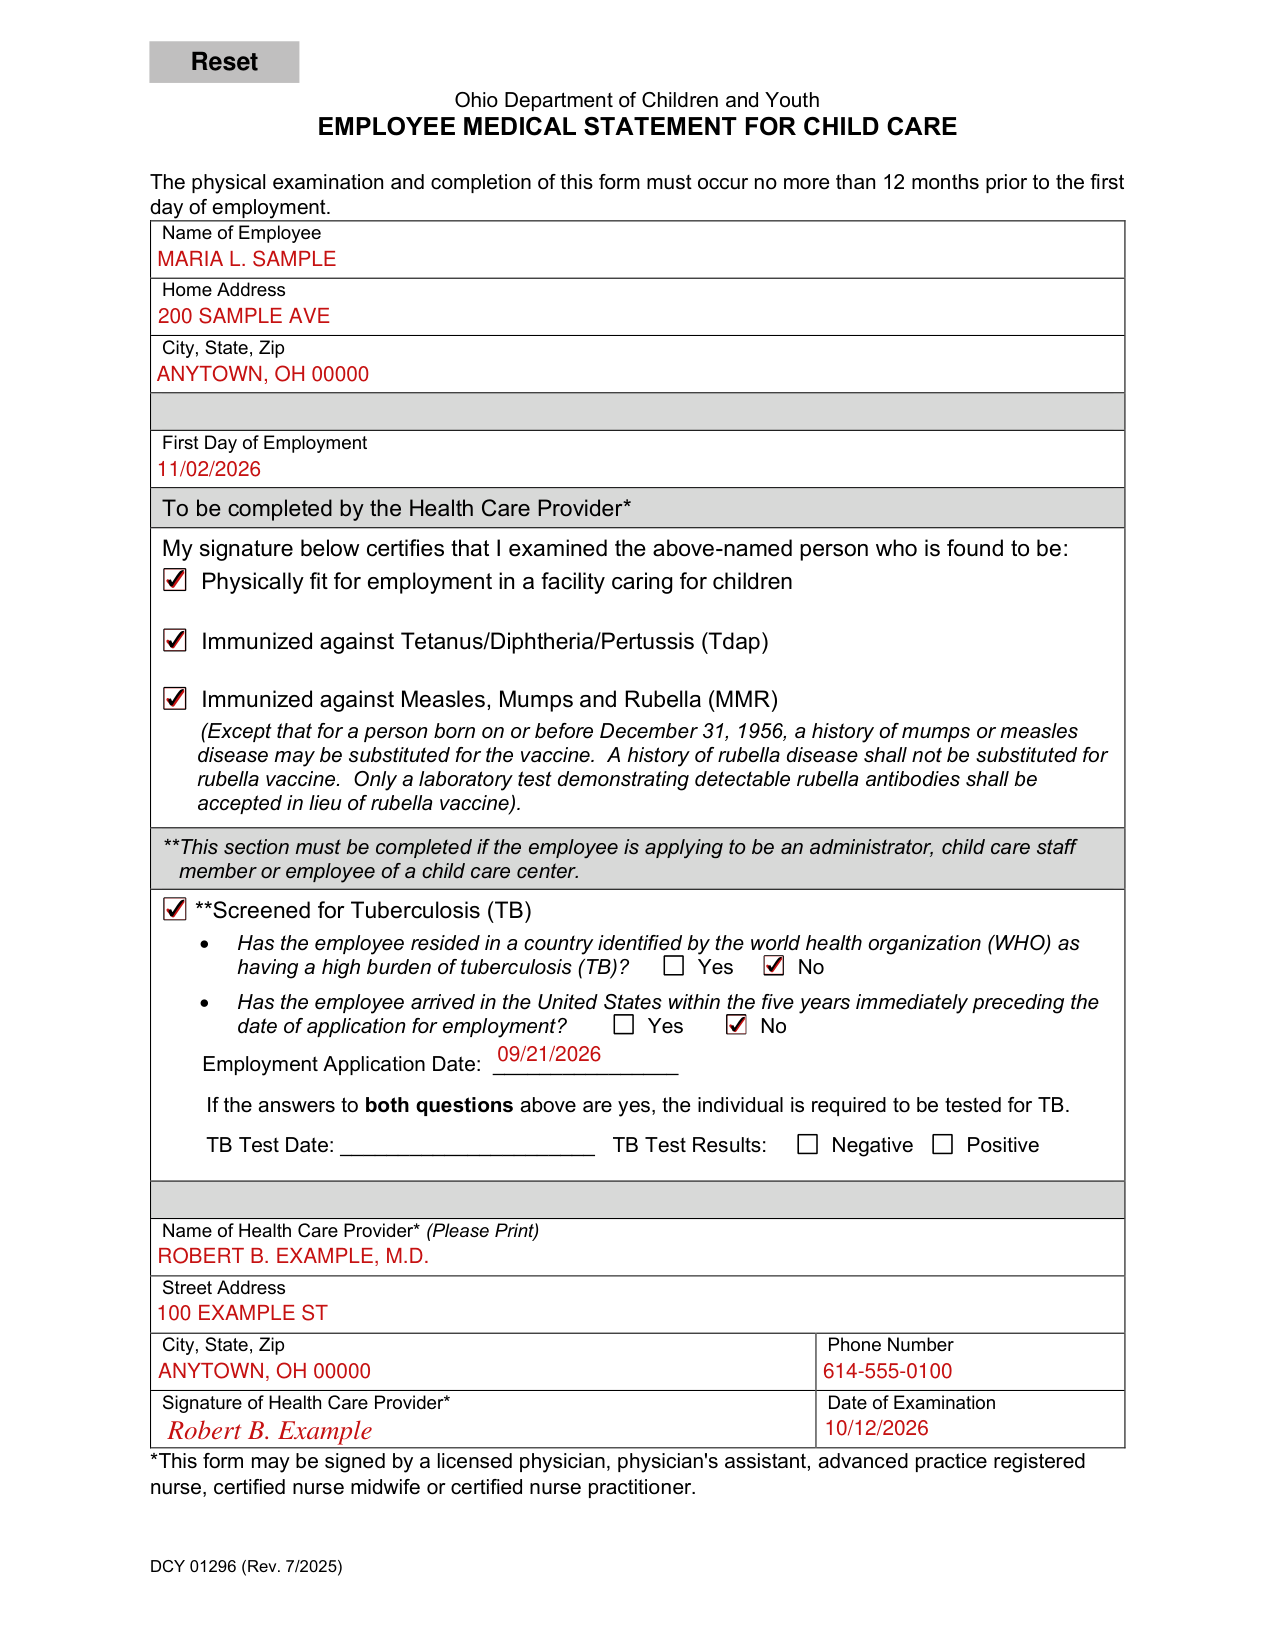
How to fill out Form DCY 01296, box by box
Name of Employee, Home Address, City, State, Zip and First Day of Employment

Enter the Name of Employee, the Home Address, the City, State, Zip and the First Day of Employment.
The physical examination and completion of this form must occur no more than 12 months prior to the first day of employment.
To be completed by the Health Care Provider: Physically fit, Tdap and MMR

Under To be completed by the Health Care Provider, the provider's signature certifies that the provider examined the person named under Name of Employee, who is found to be:
Mark Physically fit for employment in a facility caring for children.
Mark Immunized against Tetanus/Diphtheria/Pertussis (Tdap).
Mark Immunized against Measles, Mumps and Rubella (MMR). Except that for a person born on or before December 31, 1956, a history of mumps or measles disease may be substituted for the vaccine. A history of rubella disease shall not be substituted for rubella vaccine. Only a laboratory test demonstrating detectable rubella antibodies shall be accepted in lieu of rubella vaccine.
Screened for Tuberculosis (TB)
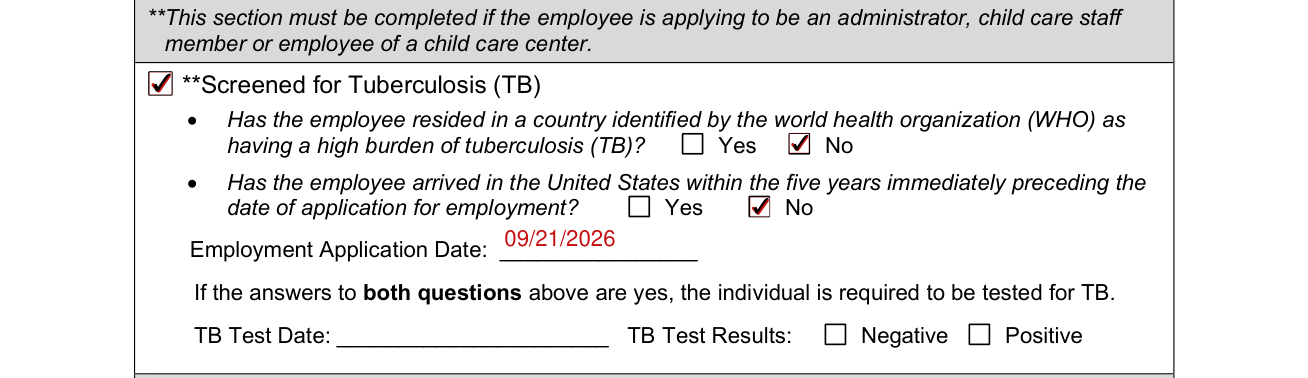
The Screened for Tuberculosis (TB) section must be completed if the employee is applying to be an administrator, child care staff member or employee of a child care center.
Yes or No: has the employee resided in a country identified by the world health organization (WHO) as having a high burden of tuberculosis (TB)? Yes or No: has the employee arrived in the United States within the five years immediately preceding the date of application for employment? Enter the Employment Application Date.
If the answers to both questions are yes, the individual is required to be tested for TB. Enter the TB Test Date and mark the TB Test Results as Negative or Positive.
Health Care Provider, signature and Date of Examination
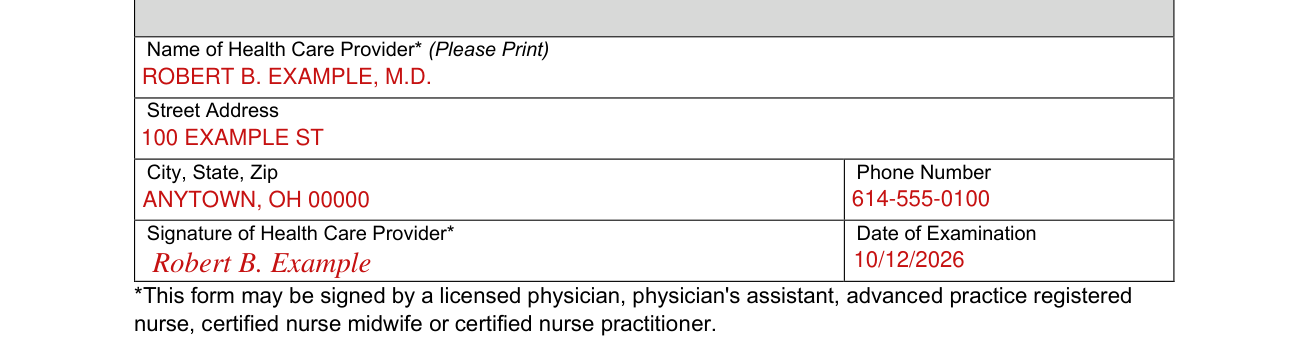
Enter the Name of Health Care Provider (Please Print), the Street Address, the City, State, Zip and the Phone Number.
Signature of Health Care Provider*: This form may be signed by a licensed physician, physician's assistant, advanced practice registered nurse, certified nurse midwife or certified nurse practitioner.
Enter the Date of Examination.
Sources
[1] Form DCY 01296 (Rev. 7/2025), Employee Medical Statement for Child Care, Ohio Department of Children and Youth (the Official source link on this page).