

Optum Rx Prior Authorization Request Form at a glance
What it is: Prior Authorization Request Form for Optum Rx.
Who signs: Prescriber's signature.
A filled-in Optum Rx Prior Authorization Request Form example: a prescriber requests a prior authorization

How to fill out Optum Rx Prior Authorization Request Form, box by box
Member Information (required)

Under Member Information (required), enter the Member Name, Insurance ID#, Date of Birth, Street Address, City, State, Zip and Phone.
Provider Information (required)

Under Provider Information (required), enter the Provider Name, NPI#, Specialty, Office Phone, Office Fax, Office Street Address, City, State and Zip.
Medication Information (required)
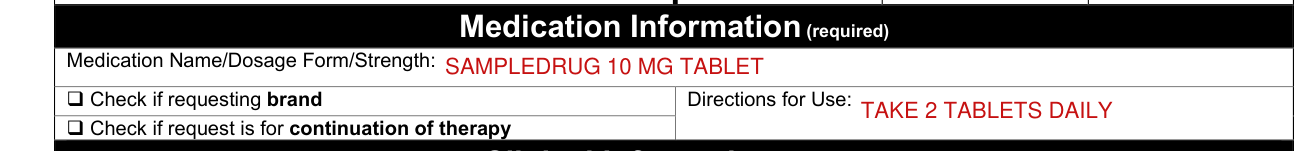
Under Medication Information (required), enter the Medication Name/Dosage Form/Strength.
Enter the Directions for Use. Check if requesting brand. Check if request is for continuation of therapy.
Clinical Information (required)

Under Clinical Information (required), enter What is the patient's diagnosis for the medication being requested? and enter the ICD-10 Code(s).
Enter What medication(s) has the patient tried and had an inadequate response to? Please specify ALL medication(s)/strengths tried, length of trial, and reason for discontinuation of each medication.
Enter What medication(s) does the patient have a contraindication or intolerance to? Please specify ALL medication(s) with the associated contraindication to or specific issues resulting in intolerance to each medication.
Enter Are there any supporting labs or test results? Please specify.
Quantity limit requests

Under Quantity limit requests, enter What is the quantity requested per DAY? and the reason for exceeding the plan limitations.
The reasons are Titration or loading-dose purposes; Patient is on a dose-alternating schedule; Requested strength/dose is not commercially available; There is a medically necessary justification why the patient cannot use a higher commercially available strength to achieve the same dosage and remain within the same dosing frequency, with Please specify; Patient requires a greater quantity for the treatment of a larger surface area [Topical applications only]; or Other.
If the patient exceeds the maximum FDA approved dosing of 4 grams of acetaminophen per day because he/she needs extra medication due to reasons such as going on a vacation, replacement for a stolen medication, provider changed to another medication that has acetaminophen, or provider changed the dosing of the medication that resulted in acetaminophen exceeding 4 grams per day, please have the patient's pharmacy contact the Optum Rx Pharmacy Helpdesk at (800) 788-7871 at the time they are filling the prescription for a one-time override.
Prescriber attestation

Under Prescriber attestation, mark Yes or No: Does the prescriber attest that the information provided is true and accurate to the best of their knowledge and understand that Optum Rx may perform a routine audit and request the medical information necessary to verify the accuracy of the information provided.
Enter the Name of person completing this form, sign on the Prescriber's signature line and enter the Date.
Are there any other comments

Enter Are there any other comments, diagnoses, symptoms, medications tried or failed, and/or any other information the physician feels is important to this review? This coverage determination request is not for a buy and bill drug.
More rules for Optum Rx Prior Authorization Request Form
For urgent or expedited requests please call 1-800-711-4555.
This request may be denied unless all required information is received.
If the patient is not able to meet the standard prior authorization requirements, please call 1-800-711-4555.
Common questions about Optum Rx Prior Authorization Request Form
What is the fax number for Optum Rx prior authorization requests?
Non-urgent requests may be faxed to 1-844-403-1028.
How do I request prior authorization for Optum Rx?
Submit an electronic PA for faster approval at www.ProviderPA.com.
When is this form not the right one?
Optum Rx is not authorized to review requests for medications supplied by the physician's office. For additional information, please contact the patient's medical benefit.
Sources
[1] Prior Authorization Request Form (General_CMS-Comm_2025May), Optum Rx (the Official source link on this page).
