Pharmacy Prior Authorization Form PDF Details

In the complex world of healthcare, obtaining medication isn't always as straightforward as one might hope. A critical step in this process involves the Pharmacy Prior Authorization form, a tool designed to ensure that certain prescribed medications receive approval from a patient's insurance provider before being dispensed. This form serves multiple purposes: it helps manage costs for insurance companies by verifying that the prescribed medication is necessary and falls within the patient's coverage plan; it also plays a vital role in patient care, as it can prompt discussions among healthcare providers about the most effective and safest medication options. The procedure for completing and submitting this form is an intricate dance of communication between healthcare professionals and insurance companies. Despite its potential to delay access to medication, the ultimate goal of the Prior Authorization process is to ensure that patients receive the most appropriate medication, while also keeping healthcare costs in check. This form, though seemingly just another piece of paperwork, is a key player in the healthcare ecosystem, balancing the needs of patients, providers, and payers.

QuestionAnswer
Form NamePharmacy Prior Authorization Form
Form Length1 pages
Fillable?Yes
Fillable fields78
Avg. time to fill out15 min 55 sec
Other namesprior authorization for caresource medical, NDC, caresource, caresource specialty pharmacy prior authorization form

How to Fill Out Specialty Pharmacy Prior Authorization Form

Specialty Pharmacy Prior Authorization Form at a glance

What it is: The Specialty Pharmacy Prior Authorization Form, completed with clinical documentation, is for Pharmacy Benefit Review or Medical Benefit Review.

Who signs: Sign on the Physician Signature line and enter the Date.

A filled-in Specialty Pharmacy Prior Authorization Form example: a physician requests prior authorization
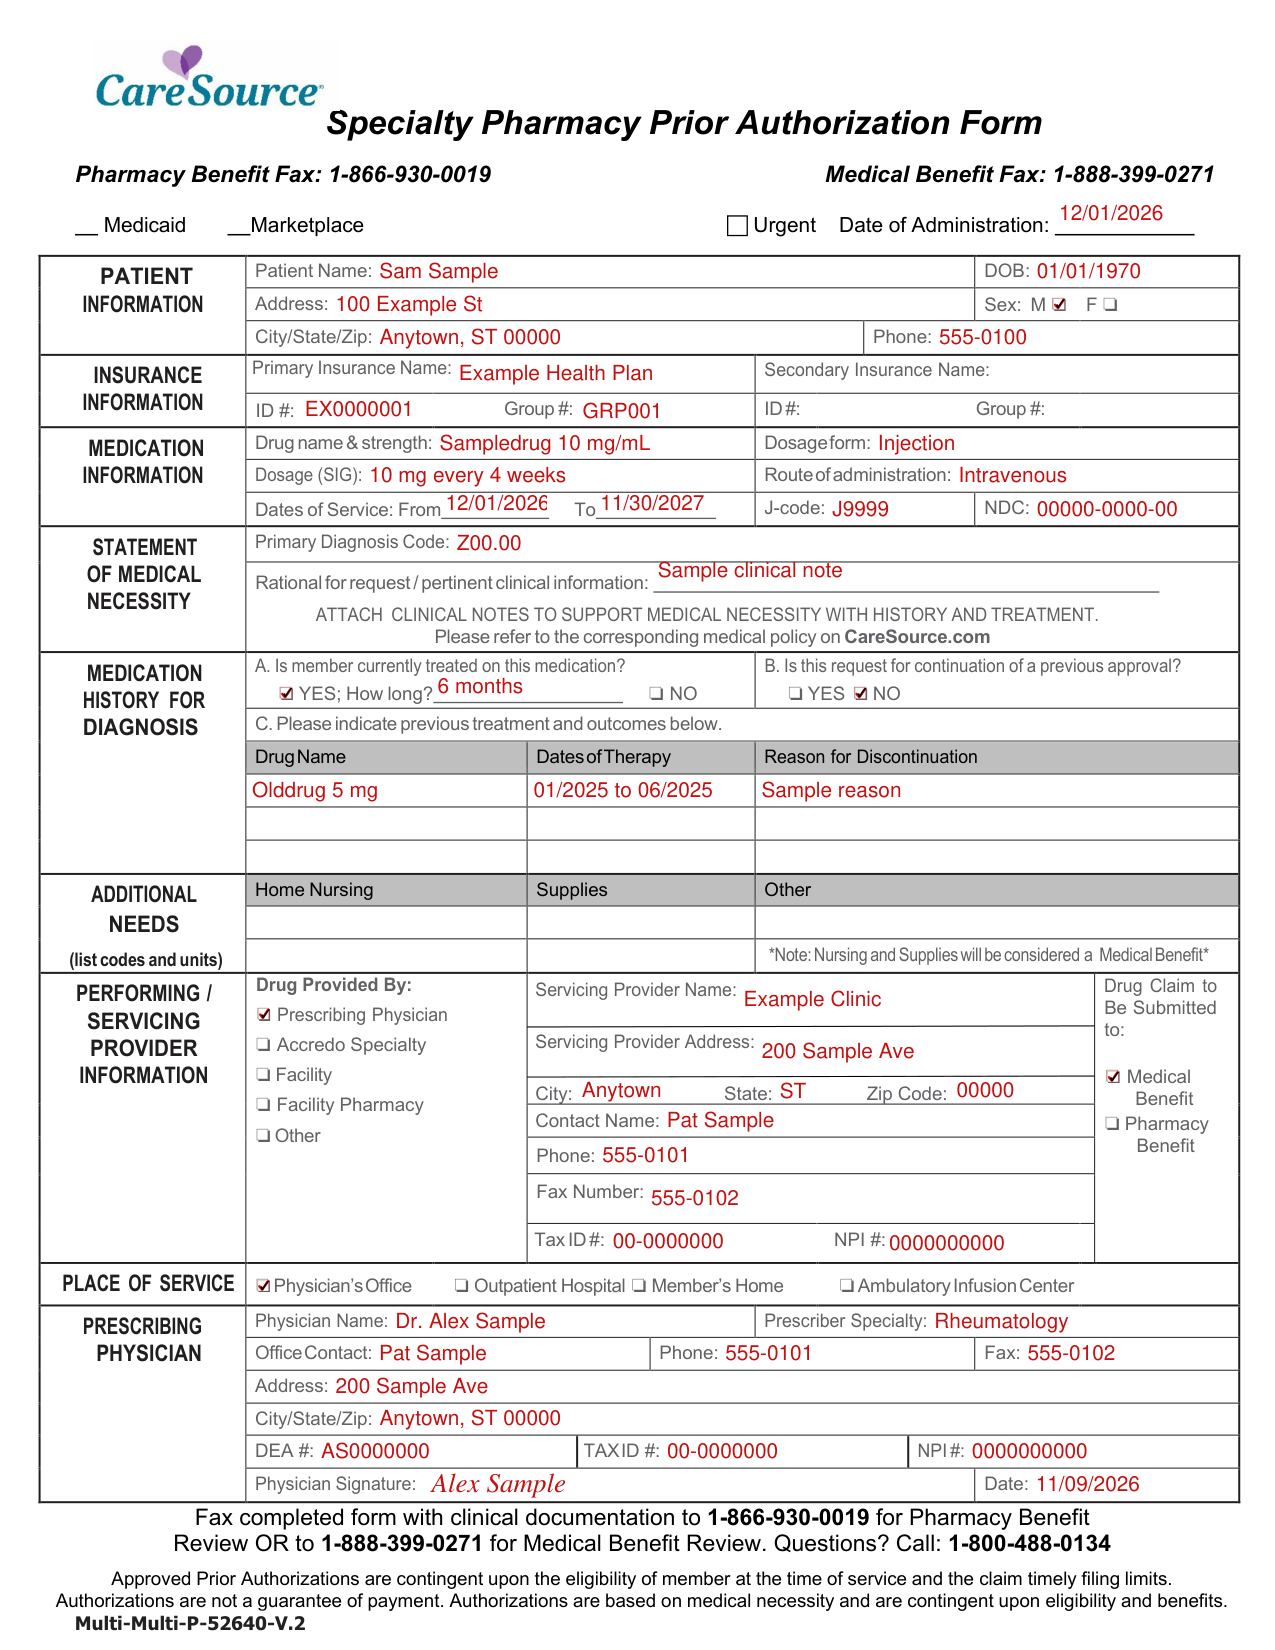
Specialty Pharmacy Prior Authorization Form example filled out, example: a physician requests prior authorization
Dr. Alex Sample asks for prior authorization of a drug for a patient. The Medical Benefit pays the claim, with the Date of Administration set for 12/01/2026. The picture shows page 1, and its names and figures are sample values. The patient is male, so M is ticked, and the patient has one plan, so Secondary Insurance Name stays empty. The patient already takes the drug for 6 months, so A is YES and B is NO. One earlier drug is listed, so the other two rows of MEDICATION HISTORY FOR DIAGNOSIS stay empty. Nothing goes in ADDITIONAL NEEDS because no nursing or supplies are requested. The physician provides the drug in the physician's office, so Prescribing Physician and Physician's Office are ticked.

How to fill out Specialty Pharmacy Prior Authorization Form, box by box

Urgent Date of Administration

Specialty Pharmacy Prior Authorization Form example filled out, urgent Date of Administration

Enter the Urgent Date of Administration.

PATIENT INFORMATION
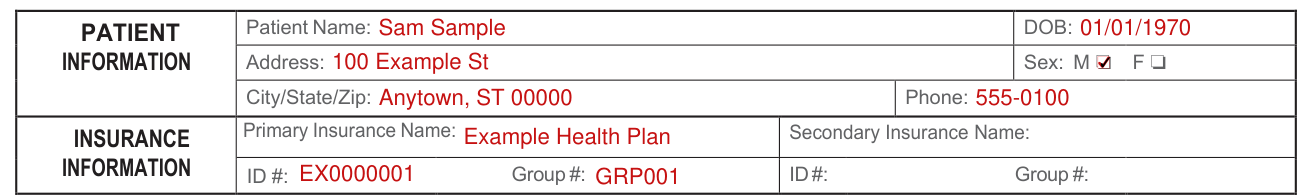
Specialty Pharmacy Prior Authorization Form example filled out, pATIENT INFORMATION

Under PATIENT INFORMATION, enter the Patient Name, DOB, Address, City/State/Zip and Phone, and mark Sex: M or F.

INSURANCE INFORMATION

Specialty Pharmacy Prior Authorization Form example filled out, iNSURANCE INFORMATION

Under INSURANCE INFORMATION, enter the Primary Insurance Name with its ID # and Group #, and, if there is a Secondary Insurance Name, that name with its ID # and Group #.

MEDICATION INFORMATION
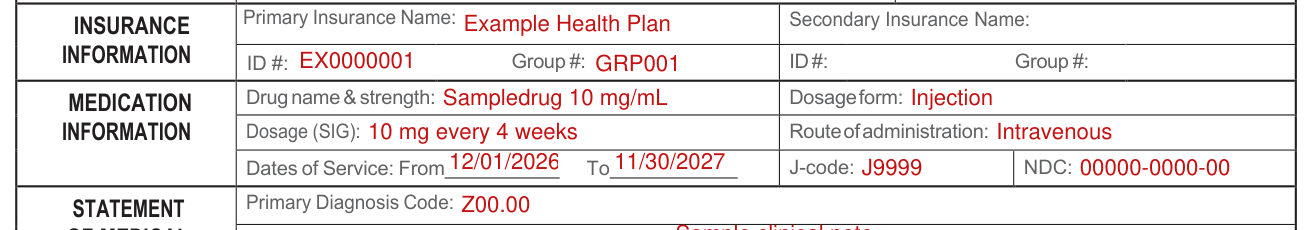
Specialty Pharmacy Prior Authorization Form example filled out, mEDICATION INFORMATION

Under MEDICATION INFORMATION, enter the Drug name & strength, Dosage form, Dosage (SIG), Route of administration, Dates of Service From and To, J-code, NDC and Primary Diagnosis Code.

STATEMENT OF MEDICAL NECESSITY

Specialty Pharmacy Prior Authorization Form example filled out, sTATEMENT OF MEDICAL NECESSITY

Under STATEMENT OF MEDICAL NECESSITY, enter the Rational for request / pertinent clinical information, and attach clinical notes to support medical necessity with history and treatment.

Please refer to the corresponding medical policy on CareSource.com.

MEDICATION HISTORY FOR DIAGNOSIS
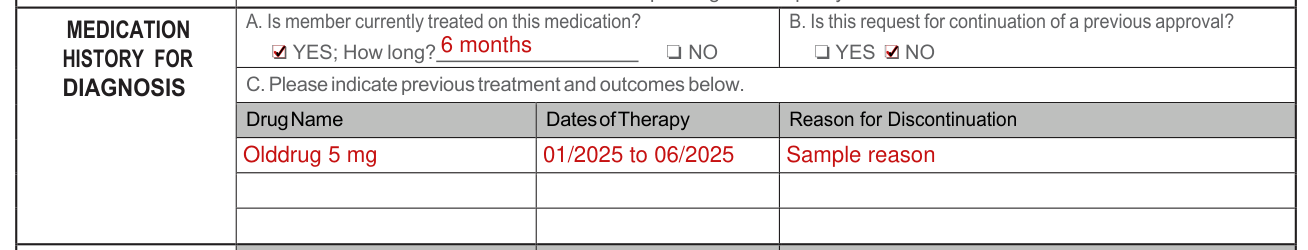
Specialty Pharmacy Prior Authorization Form example filled out, mEDICATION HISTORY FOR DIAGNOSIS

Under MEDICATION HISTORY FOR DIAGNOSIS, for A. Is member currently treated on this medication? mark YES and enter How long, or mark NO, and for B. Is this request for continuation of a previous approval? mark YES or NO.

For C, indicate previous treatment and outcomes: enter the Drug Name, Dates of Therapy and Reason for Discontinuation.

ADDITIONAL NEEDS

Specialty Pharmacy Prior Authorization Form example filled out, aDDITIONAL NEEDS

Under ADDITIONAL NEEDS, list codes and units for Home Nursing, Supplies or Other. Nursing and Supplies will be considered a Medical Benefit.

PERFORMING / SERVICING PROVIDER INFORMATION

Specialty Pharmacy Prior Authorization Form example filled out, pERFORMING / SERVICING PROVIDER INFORMATION

Under PERFORMING / SERVICING PROVIDER INFORMATION, enter the Servicing Provider Name, Servicing Provider Address, City, State and Zip Code.

For Drug Provided By, mark Prescribing Physician, Accredo Specialty, Facility, Facility Pharmacy or Other.

For Drug Claim to Be Submitted to, mark Medical Benefit or Pharmacy Benefit.

Enter the Contact Name, Phone, Fax Number, Tax ID # and NPI #.

PLACE OF SERVICE

Specialty Pharmacy Prior Authorization Form example filled out, pLACE OF SERVICE

Under PLACE OF SERVICE, mark Physician's Office, Outpatient Hospital, Member's Home or Ambulatory Infusion Center.

PRESCRIBING PHYSICIAN
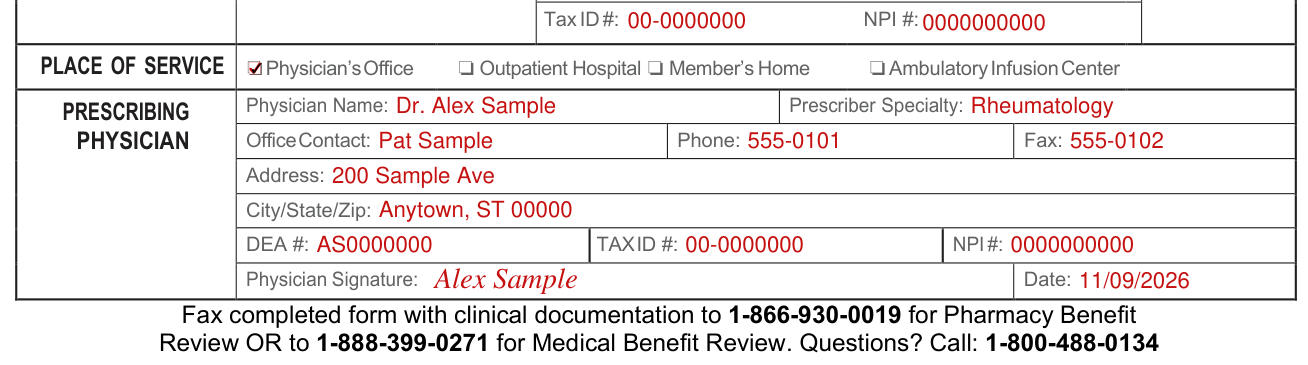
Specialty Pharmacy Prior Authorization Form example filled out, pRESCRIBING PHYSICIAN

Under PRESCRIBING PHYSICIAN, enter the Physician Name, Prescriber Specialty, Office Contact, Phone, Fax, Address, City/State/Zip, DEA #, TAX ID # and NPI #.

Sign on the Physician Signature line and enter the Date.

More rules for Specialty Pharmacy Prior Authorization Form

Approved Prior Authorizations are contingent upon the eligibility of member at the time of service and the claim timely filing limits. Authorizations are not a guarantee of payment. Authorizations are based on medical necessity and are contingent upon eligibility and benefits.

Common questions about Specialty Pharmacy Prior Authorization Form

Where do I file it?

Fax completed form with clinical documentation to 1-866-930-0019 for Pharmacy Benefit Review OR to 1-888-399-0271 for Medical Benefit Review. Questions? Call: 1-800-488-0134.

Sources

[1] Specialty Pharmacy Prior Authorization Form, Multi-Multi-P-52640-V.2 (the served file; no issuer file found) (the Official source link on this page).

Please rate Pharmacy Prior Authorization Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .