Superior Prior Authorization Form PDF Details

Navigating the complexities of healthcare can be a daunting task, both for healthcare providers and patients alike. At the heart of this intricate system, particularly within the realm of prescription medication, is the need for prior authorization, a process that serves as a checkpoint to ensure the appropriateness and necessity of certain medications. The Superior Health Plan in Texas requires the use of a specific Medication Prior Authorization Request Form, a pivotal tool in this process, designed to streamline the submission of requests for medication approval. This form, which explicitly states it should not be used for biopharmaceutical products, facilitates communication between healthcare providers and the authorization department by providing a structured format for submitting the necessary information. Instructions for submitting this comprehensive form are clearly outlined, including fax and mail options, along with a contact number for urgent requests needing a 72-hour medication supply. The form itself is divided into key sections: Provider Information, Member Information, Drug Information, and a section dedicated to the Rationale for Request/Pertinent Clinical Information, which underscores the importance of medical necessity in the authorization process. Additionally, a detailed medication history in relation to the diagnosis is required, underscoring the plan's commitment to informed and responsible medication management. The promise of a response within 24 hours, barring weekends and holidays, illustrates the plan's commitment to prompt service. This form not only exemplifies the administrative aspect of healthcare but also highlights the ongoing efforts to ensure that patients receive the most appropriate and effective medications for their conditions.

QuestionAnswer
Form NameSuperior Prior Authorization Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namessuperior medicaid pa forms, superior medicaid prior authorization form, superior prior auth form, superior health plan pa request form

How to Fill Out Medication Prior Authorization Request Form

Medication Prior Authorization Request Form at a glance

What it is: Medication Prior Authorization Request Form, Superior Health Plan, Texas. Do Not Use This Form for Biopharmaceutical Products.

Who signs: Sign at Provider Signature and fill in Date.

A filled-in Medication Prior Authorization Request Form example: a prescriber asks for approval of a continued drug

Medication Prior Authorization Request Form example filled out, example: a prescriber asks for approval of a continued drug
Dr. Ana Sample fills out the prior authorization request form. The member has taken the drug for 6 months and its dose has not changed. The picture shows the form filled, and none of its entries is real. The request continues an earlier approval, so the previous treatment table stays empty because item D is skipped.

How to fill out Medication Prior Authorization Request Form, box by box

Prescriber name (print) and Member name
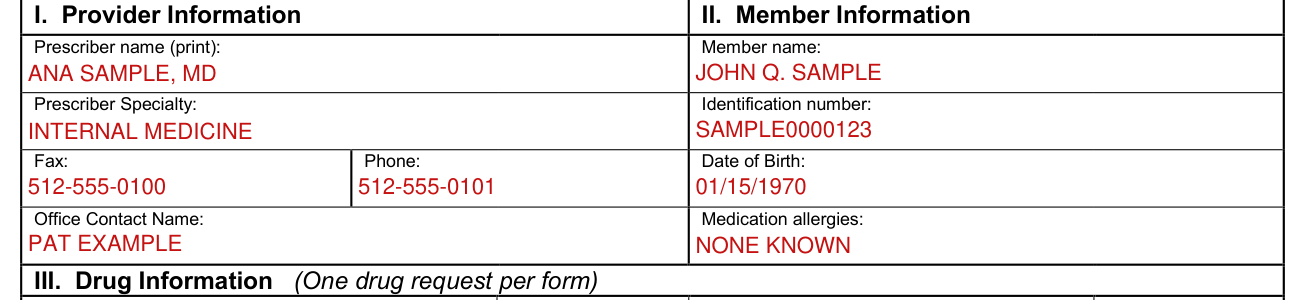
Medication Prior Authorization Request Form example filled out, prescriber name (print) and Member name

Fill in Prescriber name (print), Prescriber Specialty, Fax, Phone and Office Contact Name.

Fill in Member name, Identification number, Date of Birth and Medication allergies.

III. Drug Information (One drug request per form)
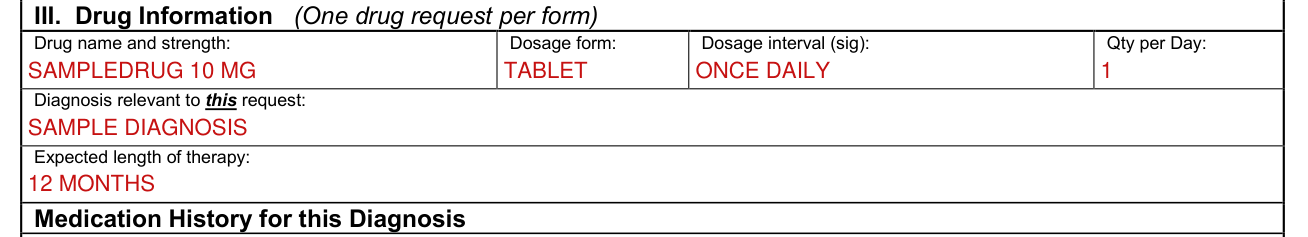
Medication Prior Authorization Request Form example filled out, iII. Drug Information (One drug request per form)

Under III. Drug Information (One drug request per form), fill in Drug name and strength, Dosage form, Dosage interval (sig), Qty per Day, Diagnosis relevant to this request and Expected length of therapy.

Medication History for this Diagnosis, items A to C
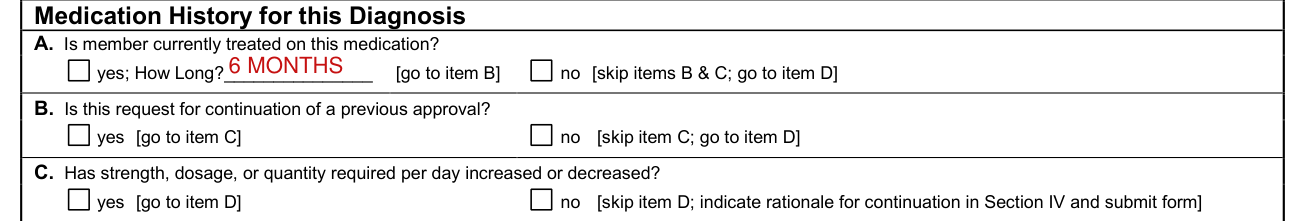
Medication Prior Authorization Request Form example filled out, medication History for this Diagnosis, items A to C

A. Is member currently treated on this medication? yes; How Long? [go to item B]. no [skip items B & C; go to item D].

B. Is this request for continuation of a previous approval? yes [go to item C]. no [skip item C; go to item D].

C. Has strength, dosage, or quantity required per day increased or decreased? yes [go to item D]. no [skip item D; indicate rationale for continuation in Section IV and submit form].

D. Please indicate previous treatment and outcomes below
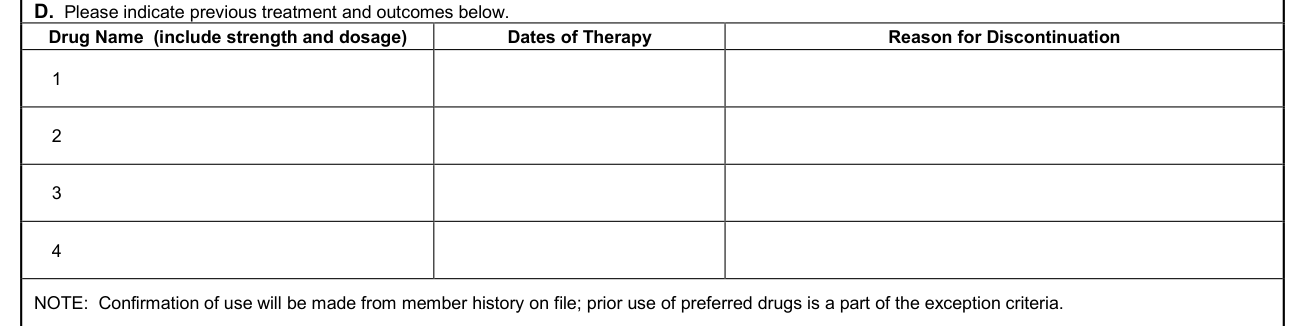
Medication Prior Authorization Request Form example filled out, d. Please indicate previous treatment and outcomes below

D. Please indicate previous treatment and outcomes: Drug Name (include strength and dosage), Dates of Therapy and Reason for Discontinuation.

NOTE: Confirmation of use will be made from member history on file; prior use of preferred drugs is a part of the exception criteria.

IV. Rationale for Request / Pertinent Clinical Information

Medication Prior Authorization Request Form example filled out, iV. Rationale for Request / Pertinent Clinical Information

IV. Rationale for Request / Pertinent Clinical Information (Required for all Prior Authorizations): appropriate clinical information to support the request on the basis of medical necessity must be submitted.

Common questions about Medication Prior Authorization Request Form

When is this form not the right one?

Medication Prior Authorization Request Form, Superior Health Plan, Texas. Do Not Use This Form for Biopharmaceutical Products.

Sources

[1] Medication Prior Authorization Request Form, Superior Health Plan, Texas (MHP Revised 01-2011) (the Official source link on this page).

Please rate Superior Prior Authorization Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .