
Form CD 51 at a glance
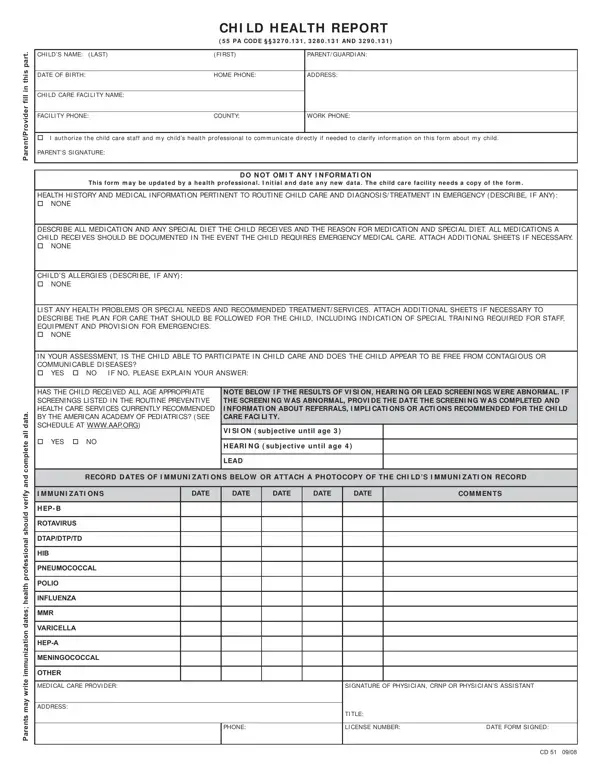
What it is: CD 51 (09/08) is the Child Health Report.
Who signs: The parent signs at PARENT'S SIGNATURE. The physician, CRNP or physician's assistant signs at the signature line.
The blank Form CD 51: print it and complete it by hand
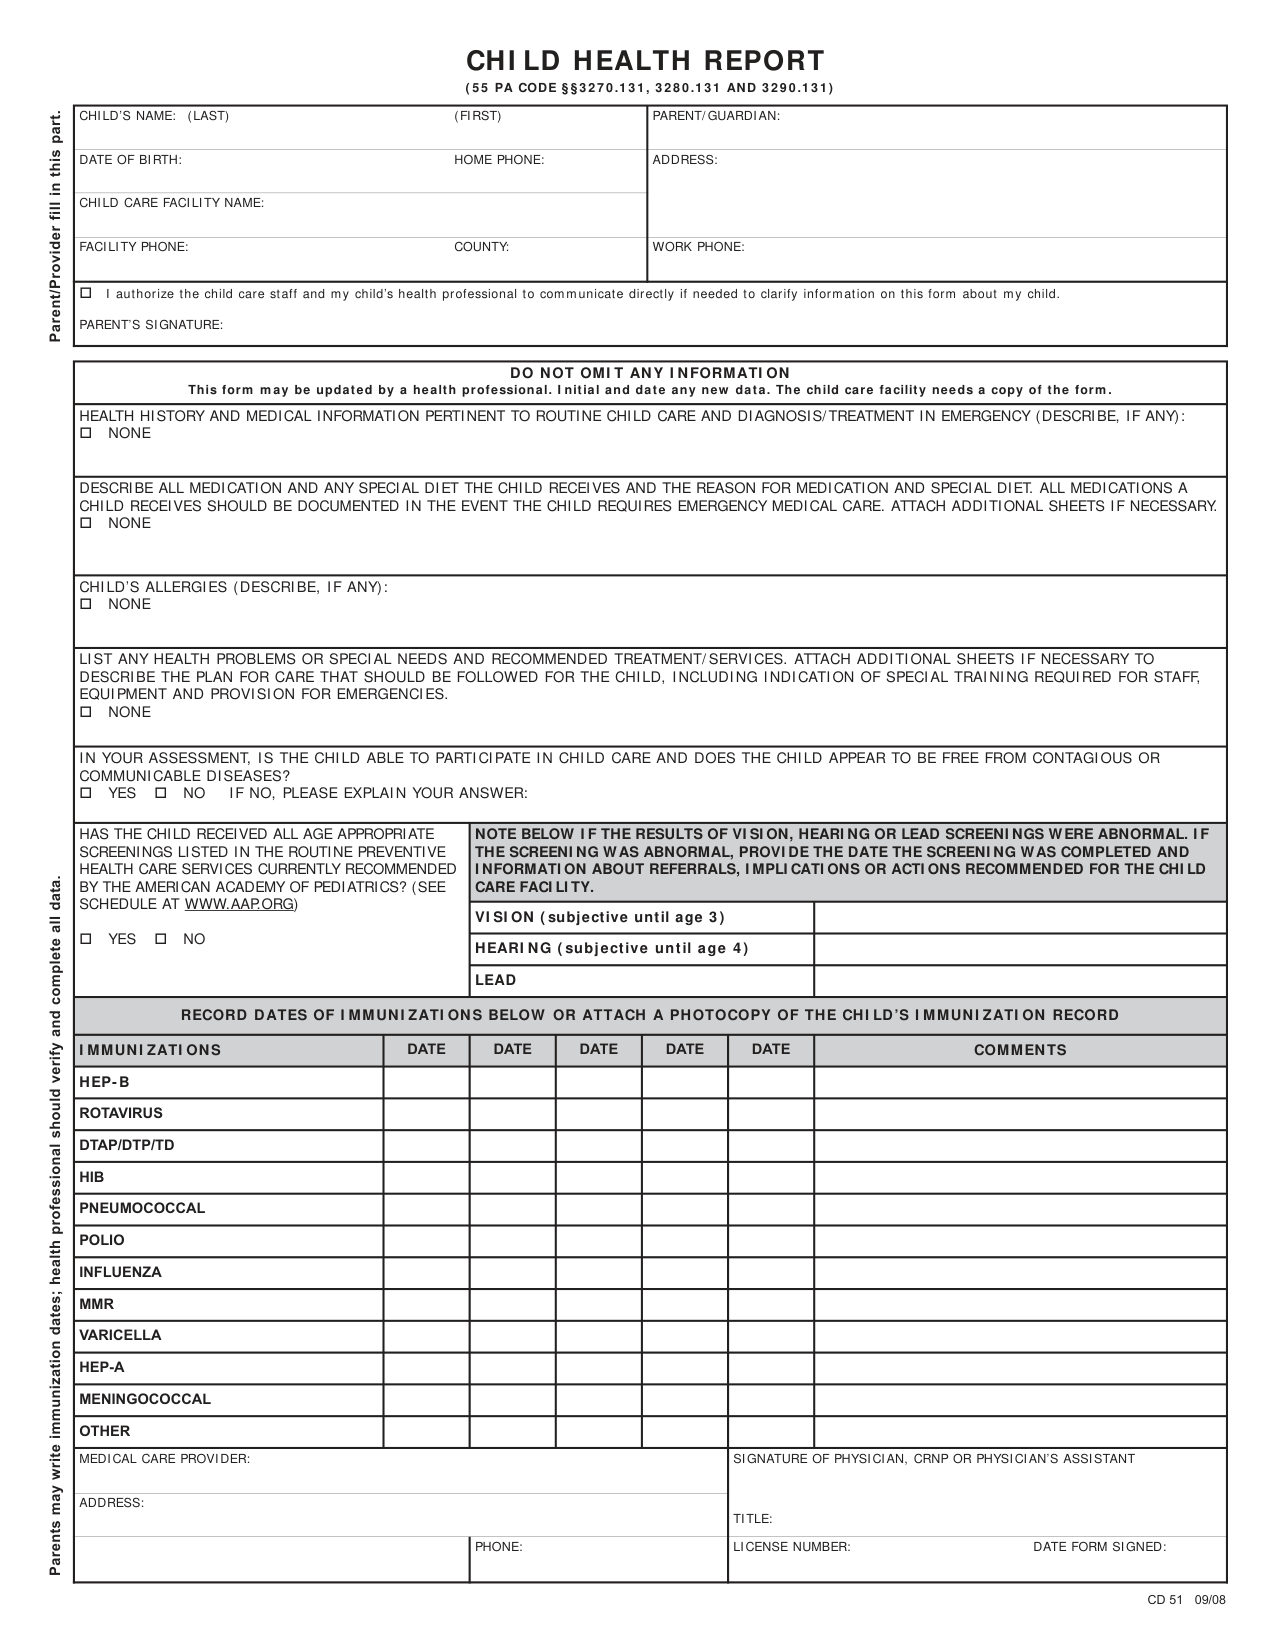
How to fill out Form CD 51, box by box
Parent/Provider fill in this part
Parent/Provider fill in this part: Child's Name (Last) (First), Parent/Guardian, Date of Birth, Home Phone, Address, Child Care Facility Name, Facility Phone, County and Work Phone.
Communicate with the child's health professional
You can mark the box for "I authorize the child care staff and my child's health professional to communicate directly if needed to clarify information on this form about my child."
Do not omit any information
Do not omit any information. This form may be updated by a health professional. Initial and date any new data. The child care facility needs a copy of the form.
Health history, medication, allergies and special needs
Describe any health history and medical information pertinent to routine child care and diagnosis/treatment in emergency, or mark NONE.
Describe all medication and any special diet the child receives and the reason for medication and special diet, or mark NONE. All medications a child receives should be documented in the event the child requires emergency medical care. Attach additional sheets if necessary.
Under CHILD'S ALLERGIES, describe any, or mark NONE.
List any health problems or special needs and recommended treatment/services, or mark NONE. Attach additional sheets if necessary to describe the plan for care that should be followed for the child, including indication of special training required for staff, equipment and provision for emergencies.
Able to participate in child care
The physician, CRNP or physician's assistant marks YES or NO: in their assessment, is the child able to participate in child care and does the child appear to be free from contagious or communicable diseases? If NO, they explain the answer.
Age appropriate screenings: vision, hearing and lead
Mark YES or NO: has the child received all age appropriate screenings listed in the routine preventive health care services currently recommended by the American Academy of Pediatrics (see schedule at www.aap.org)? Under VISION (subjective until age 3), HEARING (subjective until age 4) and LEAD, note if the results of the screenings were abnormal. If the screening was abnormal, provide the date the screening was completed and information about referrals, implications or actions recommended for the child care facility.
Immunizations
Record dates of immunizations or attach a photocopy of the child's immunization record. Write each date and any comments for Hep-B, Rotavirus, DTAP/DTP/TD, Hib, Pneumococcal, Polio, Influenza, MMR, Varicella, Hep-A, Meningococcal or Other.
Parents may write immunization dates; health professional should verify and complete all data.
Medical care provider
Write the medical care provider, address, title, phone, license number and date form signed.
Sources
[1] Form CD 51 (09/08), Child Health Report, Pennsylvania Department of Human Services (the Official source link on this page).