


Patient Enrollment Form at a glance
What it is: The Patient Enrollment Form is for selecting the program offering(s) that best meet your patient's needs.
Who signs: Prescriber signature(s) in Section 7 and 8 and patient signature(s) in Section 12 are required.
A filled-in Patient Enrollment Form example: a prescriber enrolls a patient
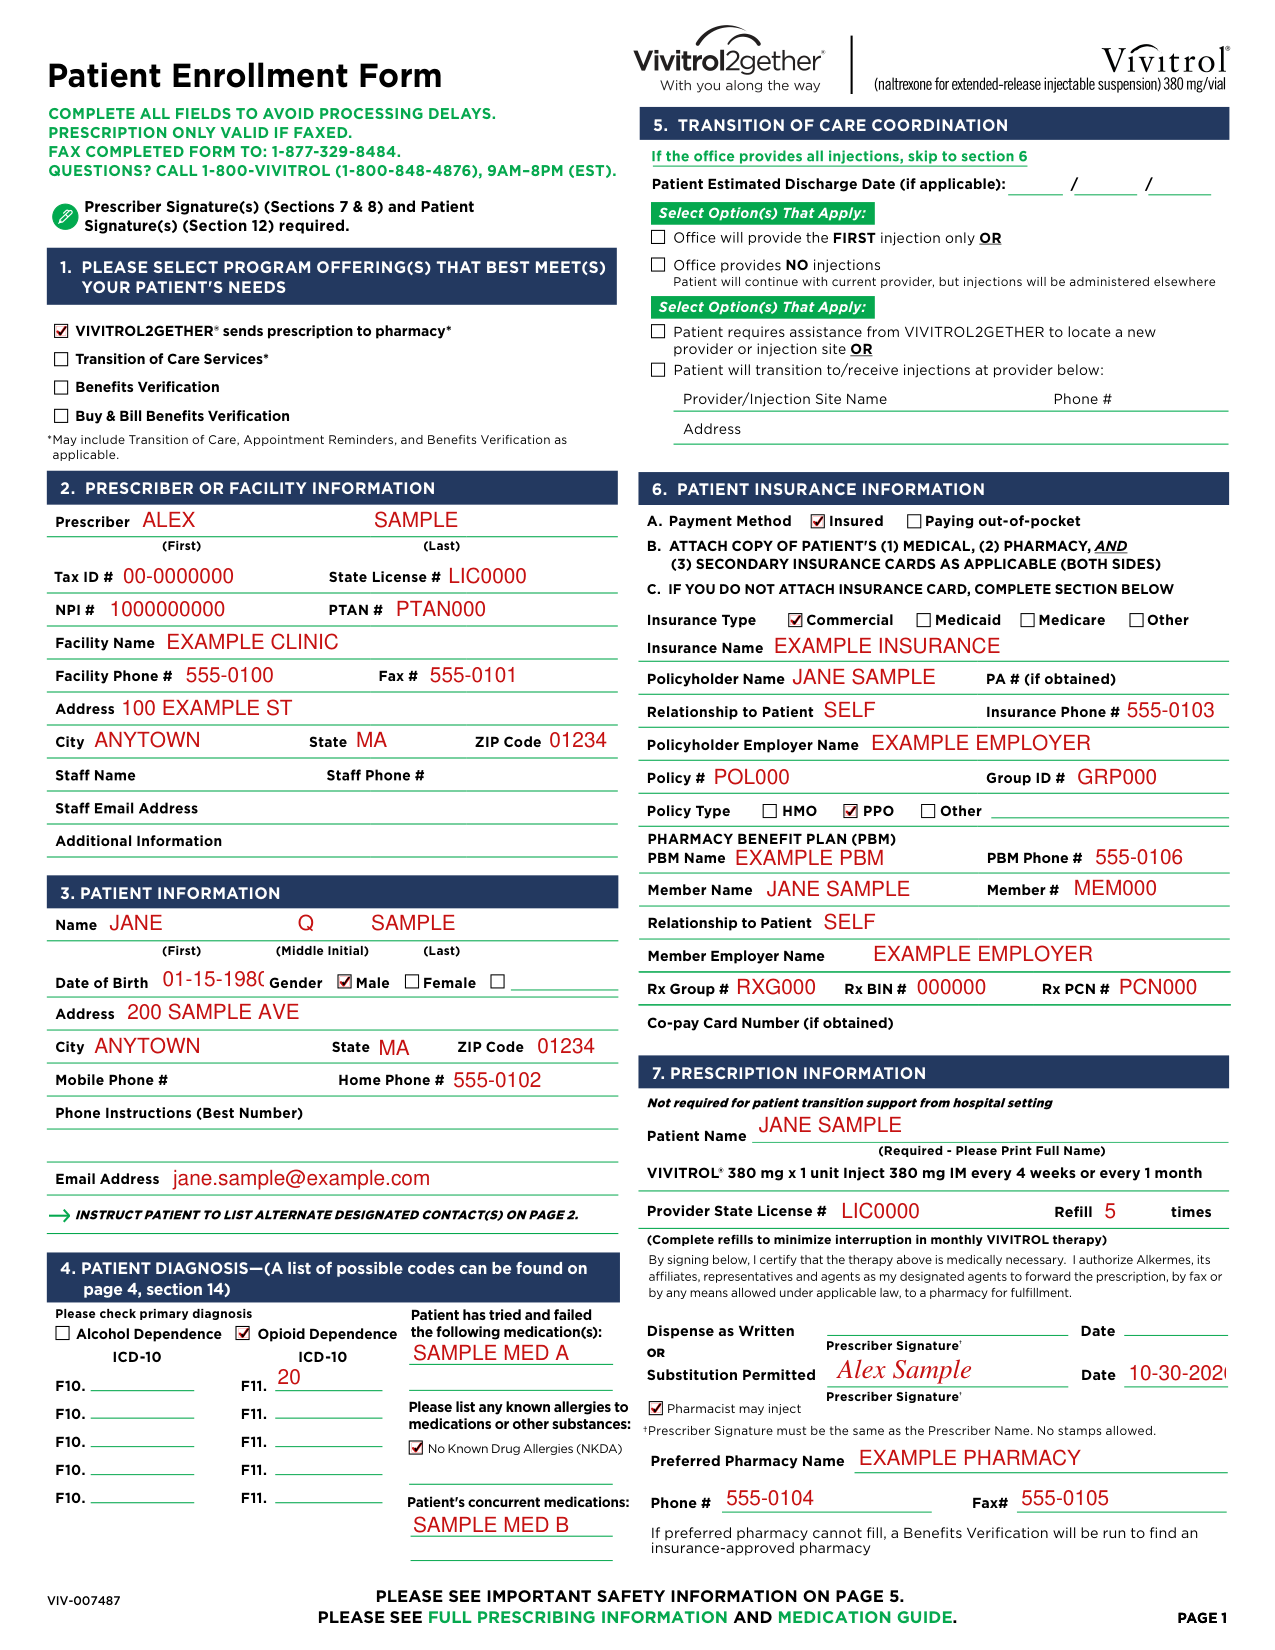
How to fill out Patient Enrollment Form, box by box
Program offering(s)

Select the program offering(s) that best meet your patient's needs: VIVITROL2GETHER sends prescription to pharmacy*, Transition of Care Services*, Benefits Verification, or Buy & Bill Benefits Verification.
* May include Transition of Care, Appointment Reminders, and Benefits Verification as applicable.
Prescriber or facility
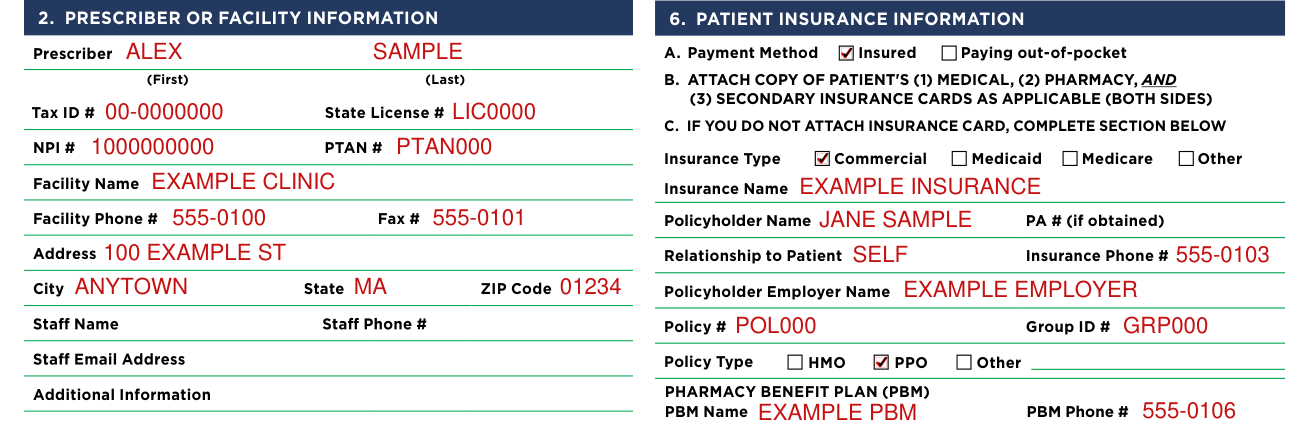
Enter the Prescriber (First) and (Last).
Enter the Tax ID #, NPI # and PTAN #.
Enter the Facility Name, Facility Phone #, Fax #, Address, City, State and ZIP Code.
Patient
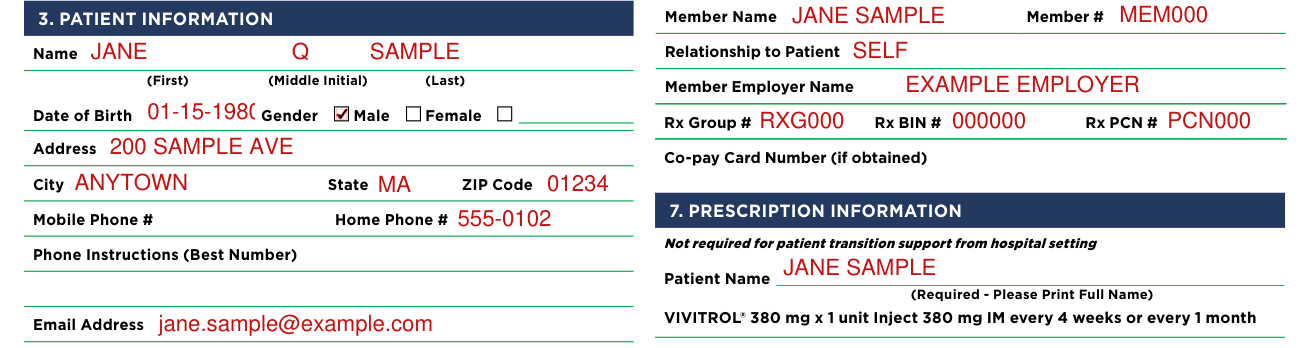
Enter the patient's Name (First) (Middle Initial) (Last) and Date of Birth, and mark Gender Male or Female.
Enter the patient's Address, City, State and ZIP Code.
Enter the Mobile Phone # and Home Phone # and the Email Address. Enter the Phone Instructions (Best Number).
Instruct the patient to list alternate designated contact(s) on page 2.
Patient diagnosis

Check the primary diagnosis, Alcohol Dependence or Opioid Dependence.
Enter the ICD-10 codes; the list includes ICD-10 diagnosis codes that may be relevant for patients treated with VIVITROL, is not exhaustive and additional codes may apply.
The healthcare provider is responsible for determining the appropriate codes to accurately reflect their patient's condition.
List the medication(s) the patient has tried and failed.
List any known allergies to medications or other substances, or check No Known Drug Allergies (NKDA).
List the patient's concurrent medications.
Transition of care coordination
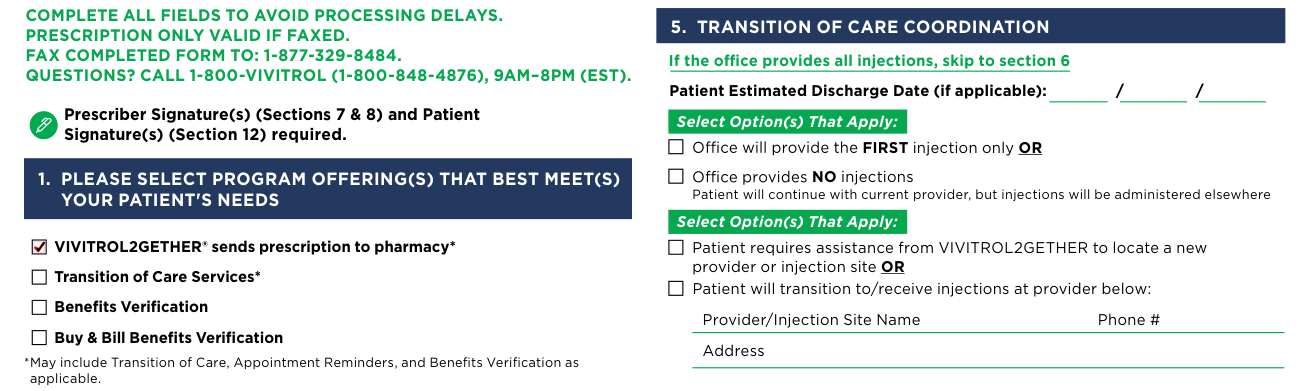
In Transition of Care Coordination, enter the Patient Estimated Discharge Date (if applicable).
Select Option(s) That Apply: FIRST injection only OR NO injections, Patient will continue with current provider, but injections will be administered elsewhere OR Patient requires assistance from VIVITROL2GETHER to locate a new provider or injection site.
If the Patient will transition to/receive injections at provider (Transition of Care Coordination), enter the Provider/Injection Site Name, Phone # and Address.
Patient insurance
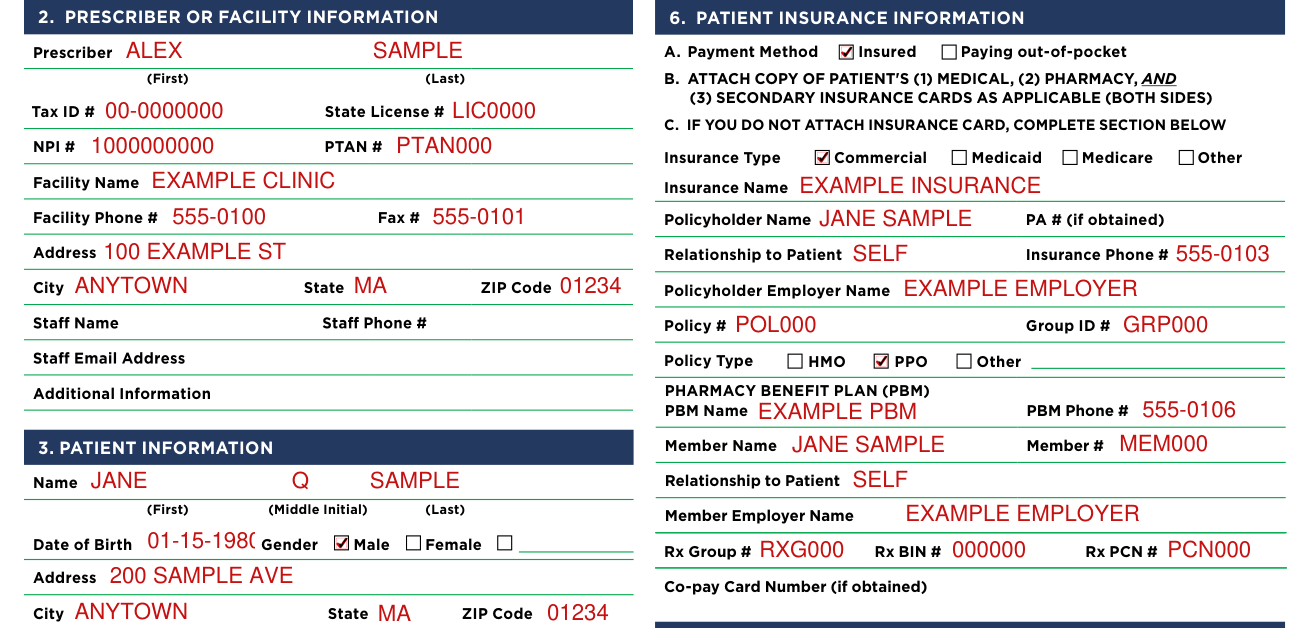
A. Payment Method: Insured or Paying out-of-pocket.
If you do not attach the insurance card, complete the insurance section: Insurance Type (Commercial, Medicaid, Medicare or Other) and Insurance Name.
Enter the Policyholder Name, PA # (if obtained), Relationship to Patient, Insurance Phone #, Policyholder Employer Name, Policy # and Group ID #, and the Policy Type: HMO, PPO or Other.
Under the pharmacy benefit plan (PBM), enter the PBM Name, PBM Phone #, Member Name, Member #, Relationship to Patient and Member Employer Name.
Enter the Rx Group #, Rx BIN #, Rx PCN # and the Co-pay Card Number (if obtained).
Prescription information

Print the Patient Name in full (Required).
Prescription Information is not required for patient transition support from hospital setting.
The Prescription Information is VIVITROL 380 mg x 1 unit: Inject 380 mg IM every 4 weeks or every 1 month.
Enter the Provider State License #.
Enter the Refill times (Complete refills to minimize interruption in monthly VIVITROL therapy).
Sign the Prescriber Signature and enter the Date on the Dispense as Written line OR on the Substitution Permitted line.
The Prescriber Signature must be the same as the Prescriber Name. No stamps allowed.
You can check Pharmacist may inject.
Enter the Preferred Pharmacy Name, Phone # and Fax#.
If preferred pharmacy cannot fill, a Benefits Verification will be run to find an insurance-approved pharmacy.
More rules for Patient Enrollment Form
For patients who require assistance finding a healthcare provider or injection site with experience administering VIVITROL, VIVITROL2GETHER can identify several providers and facilities based on geographic proximity to the patient address provided on this Form using the VIVITROL Provider Locator at VIVITROL.com.
If your situation is different
Section 8, Prescriber Attestation
In Section 8, Prescriber Attestation, sign the Prescriber's Signature line and enter the Date.
The prescriber authorizes Alkermes to act on the prescriber's behalf for the limited purpose of transmitting the prescription(s) and providing the patient information on this form to the appropriate dispensing pharmacy to the extent permitted under applicable law.
Section 9, Designated Patient Contact(s)
In Section 9, Designated Patient Contact(s), list any Designated Contact(s): Designee Name (1) and Designee Name (2), each with Relationship, Phone # and Email; the patient signs and dates.
Section 10, Co-Pay Savings Program Information for Eligible Patients
In Section 10, Co-Pay Savings Program Information for Eligible Patients, the patient certifies: at least 18 years old, commercial insurance (private or non-governmental) or no insurance, and a valid prescription for a Food and Drug Administration (FDA)-approved indication.
If the Patient's insurance changes, the patient will promptly notify VIVITROL2GETHER at 800-848-4876 in order to confirm continued eligibility.
Before you go
Attach a copy of the patient's (1) medical, (2) pharmacy, and (3) secondary insurance cards as applicable (both sides).
Common questions about Patient Enrollment Form
Where do I file it?
Fax the completed form to 1-877-329-8484; a prescription is only valid if faxed. Complete all fields to avoid processing delays. For questions, call 1-800-VIVITROL (1-800-848-4876), 9AM-8PM (EST).
Are there fees?
Participation is free of charge.
Sources
[1] Patient Enrollment Form (VIV-007487), Alkermes, Inc. (the Official source link on this page).