
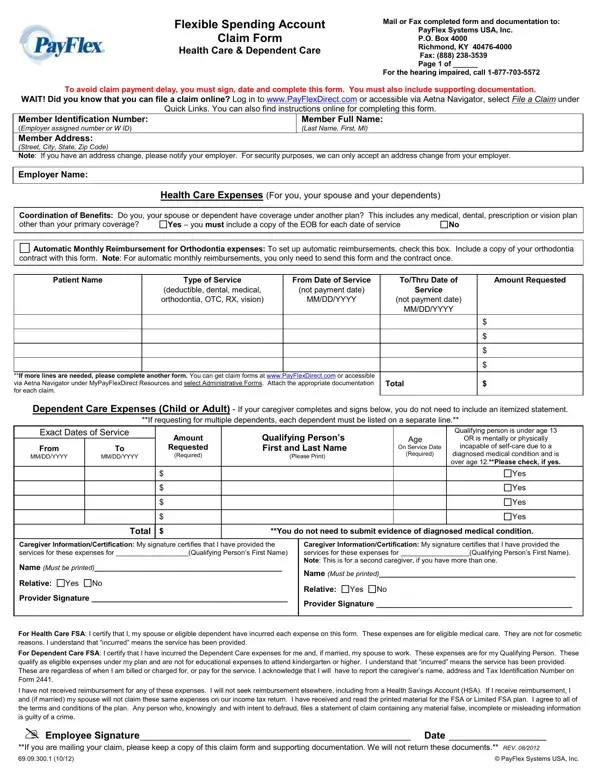
PayFlex Flexible Spending Account Claim Form at a glance
What it is: Flexible Spending Account Claim Form Health Care & Dependent Care.
Where and when to file: To avoid claim payment delay, you must sign, date and complete this form. You must also include supporting documentation.
A filled-in PayFlex Flexible Spending Account Claim Form example: a dental claim with no other coverage
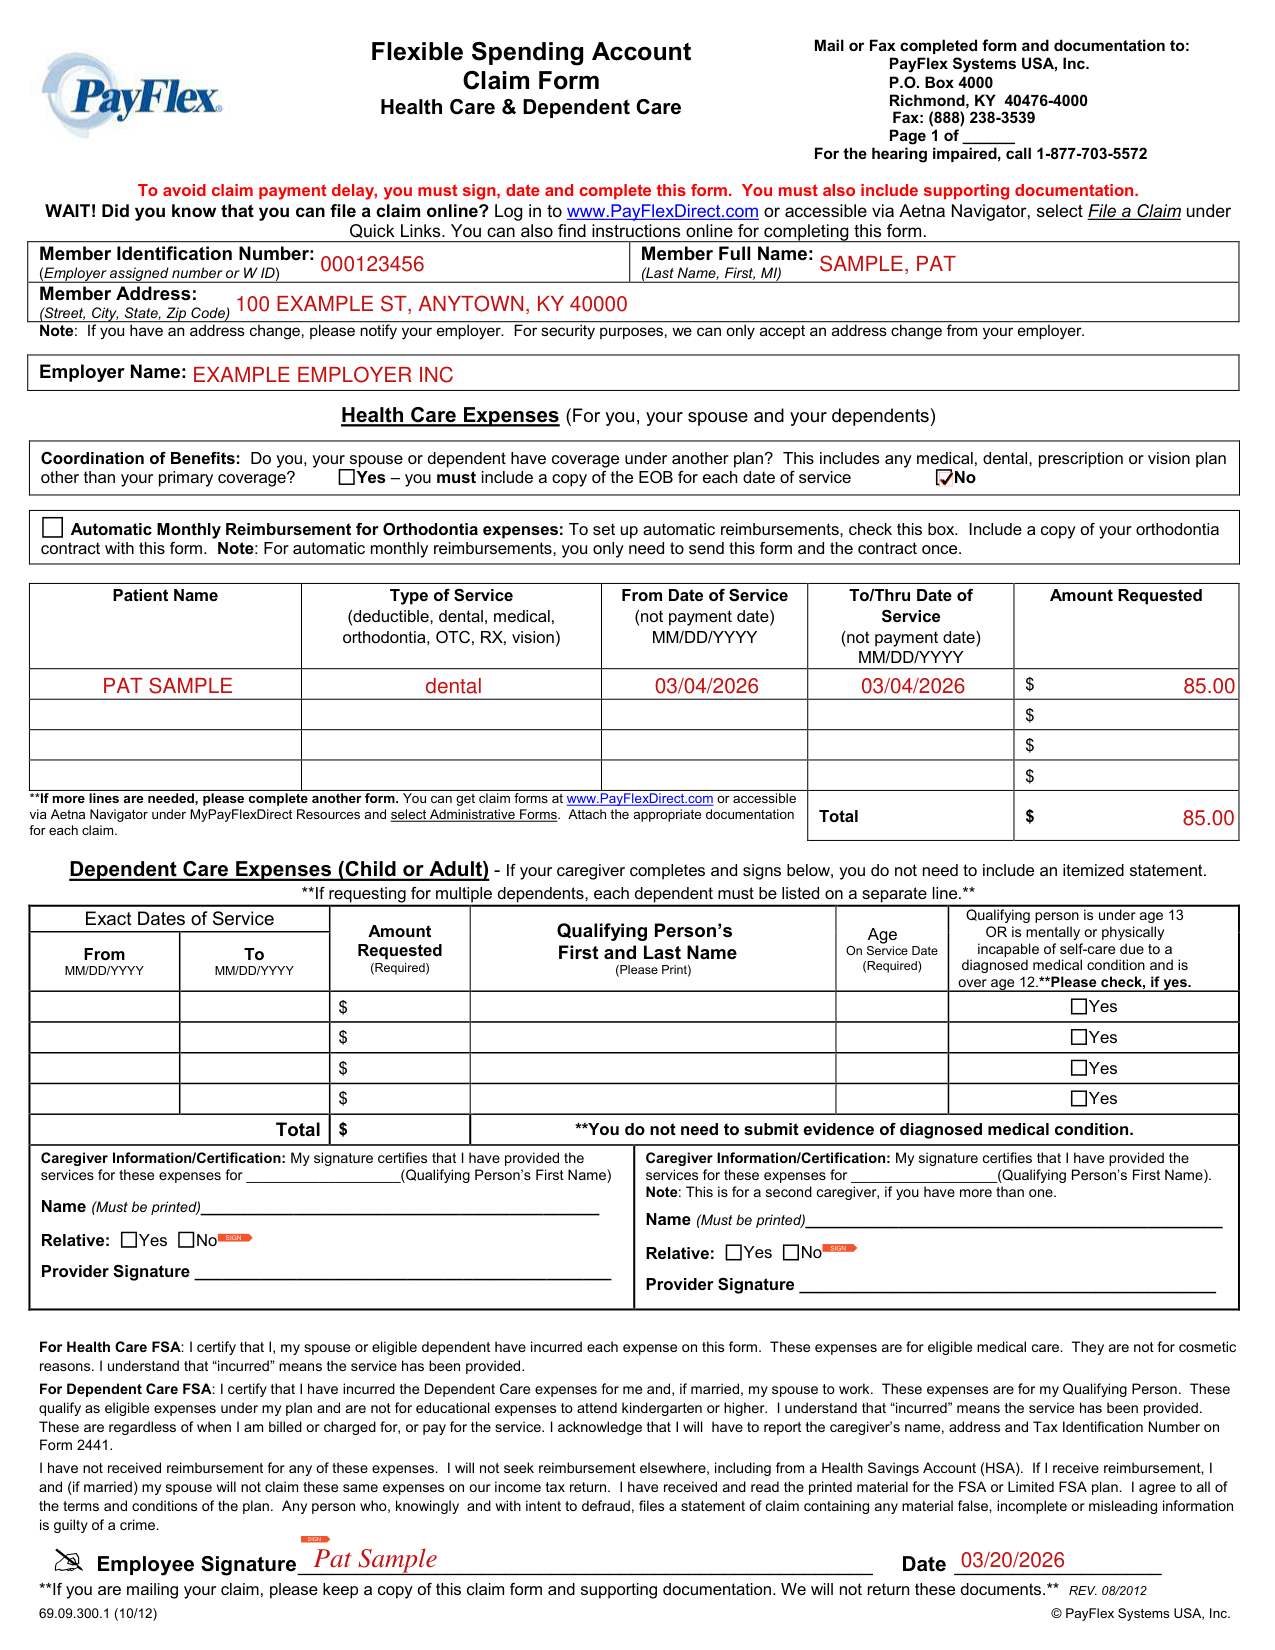
How to fill out PayFlex Flexible Spending Account Claim Form, box by box
Member and employer
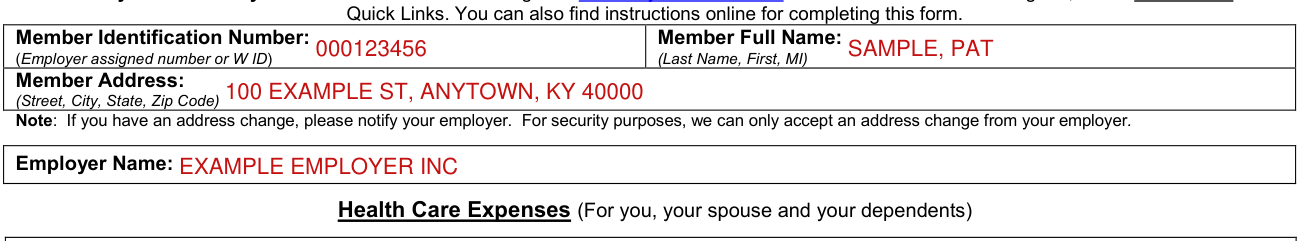
Enter the Member Identification Number: Employer assigned number or WID.
Enter the Member Full Name: Last Name, First, MI, the Member Address: Street, City, State, Zip Code, and the Employer Name.
If you have an address change, please notify your employer.
Coordination of Benefits and the orthodontia box

Coordination of Benefits: Do you, your spouse or dependent have coverage under another plan? This includes any medical, dental, prescription or vision plan other than your primary coverage? Yes - you must include a copy of the EOB for each date of service. No.
To set up automatic reimbursements, check this box. Include a copy of your orthodontia contract with this form. For automatic monthly reimbursements, you only need to send this form and the contract once.
Patient Name, Type of Service and Amount Requested
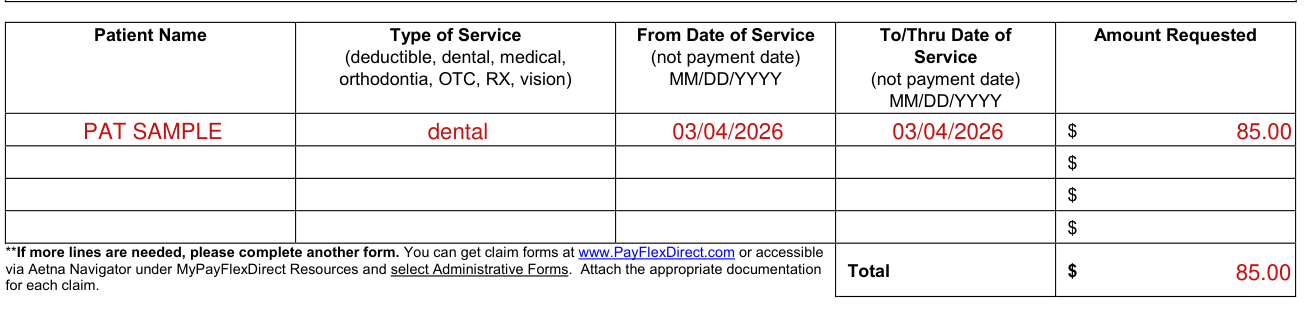
On each line, enter the Patient Name, the Type of Service (deductible, dental, medical, orthodontia, OTC, RX, vision), the From Date of Service (not payment date) MM/DD/YYYY, the To/Thru Date of Service (not payment date) MM/DD/YYYY and the Amount Requested.
If more lines are needed, please complete another form. Attach the appropriate documentation for each claim. Total.
Dependent Care Expenses

Dependent Care Expenses (Child or Adult) - If your caregiver completes and signs the Caregiver Information/Certification, you do not need to include an itemized statement.
If requesting for multiple dependents, each dependent must be listed on a separate line. Enter the Exact Dates of Service From MM/DD/YYYY To MM/DD/YYYY and the Amount Requested (Required).
Enter the Qualifying Person's First and Last Name (Please Print) and the Age On Service Date (Required). Qualifying person is under age 13. OR is mentally or physically incapable of self-care due to a diagnosed medical condition and is over age 12. Please check, if yes.
You do not need to submit evidence of diagnosed medical condition.
Caregiver Information and Certification

Caregiver Information/Certification: My signature certifies that I have provided the services for these expenses for the Qualifying Person's First Name. Name (Must be printed). Relative: Yes No. Provider Signature.
This is for a second caregiver, if you have more than one.
Signing the claim

"For Health Care FSA: I certify that I, my spouse or eligible dependent have incurred each expense on this form. These expenses are for eligible medical care. They are not for cosmetic reasons."
"For Dependent Care FSA: I certify that I have incurred the Dependent Care expenses for me and, if married, my spouse to work. These expenses are for my Qualifying Person. These qualify as eligible expenses under my plan and are not for educational expenses to attend kindergarten or higher. I understand that “incurred” means the service has been provided. These are regardless of when I am billed or charged for, or pay for the service. I acknowledge that I will have to report the caregiver's name, address and Tax Identification Number on Form 2441."
I have not received reimbursement for any of these expenses. I will not seek reimbursement elsewhere, including from a Health Savings Account (HSA).
Any person who, knowingly and with intent to defraud, files a statement of claim containing any material false, incomplete or misleading information is guilty of a crime.
Employee Signature and Date.
If you are mailing your claim, please keep a copy of this claim form and supporting documentation.
More rules for PayFlex Flexible Spending Account Claim Form
You can file a claim online. Log in to www.PayFlexDirect.com. You can also find instructions online for completing this form.
For the hearing impaired, call 1-877-703-5572.
Common questions about PayFlex Flexible Spending Account Claim Form
Where do I file it?
Mail or Fax completed form and documentation to: PayFlex Systems USA, Inc. P.O. Box 4000 Richmond, KY 40476-4000 Fax: (888) 238-3539.
Sources
[1] Flexible Spending Account Claim Form Health Care & Dependent Care (10/12), PayFlex Systems USA, Inc. (the Official source link on this page).