

CIGNA Botulinum Toxin Fax Order Form at a glance
What it is: CIGNA Specialty Pharmacy Services Botulinum Toxin Fax Order Form.
Where and when to file: Requests received after 4 p.m. CT will begin processing the following business day. Fax: 1.800.351.3616.
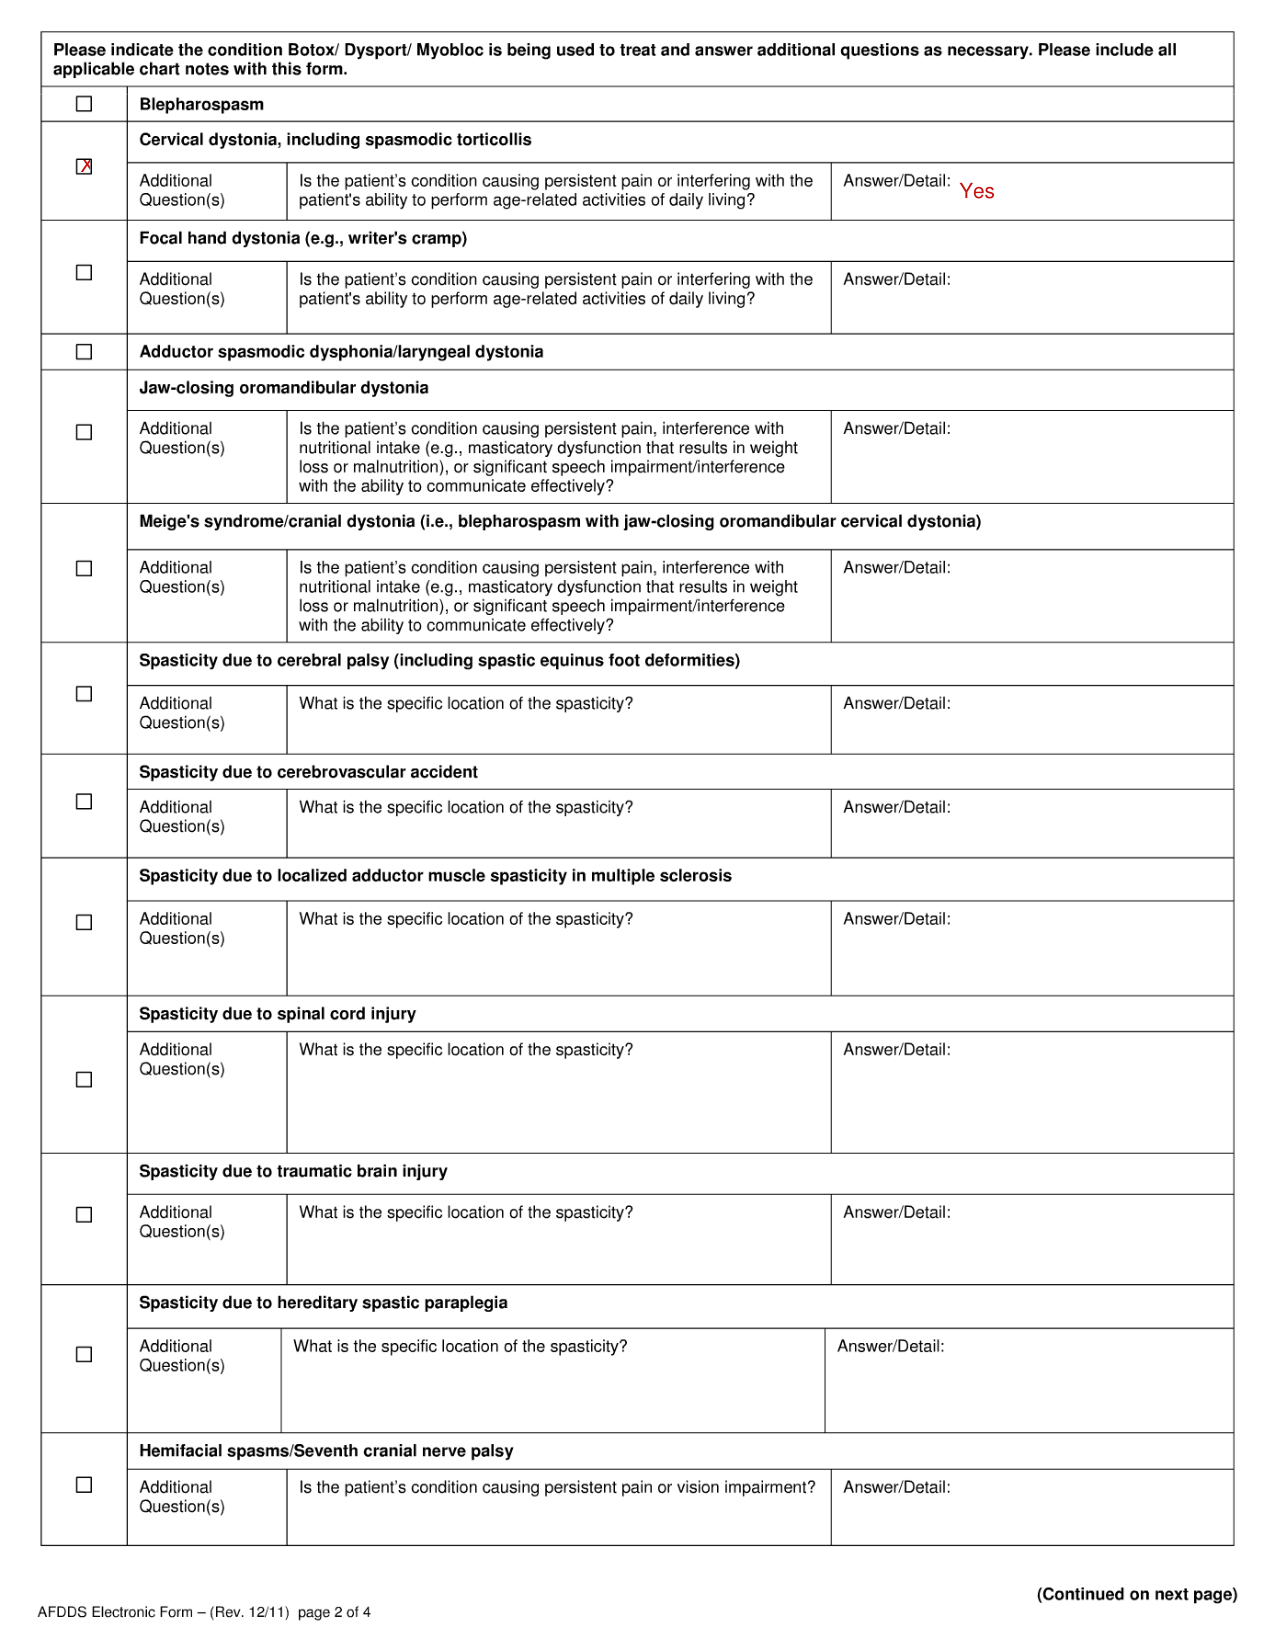
A filled-in CIGNA Botulinum Toxin Fax Order Form example: a cervical dystonia order
How to fill out CIGNA Botulinum Toxin Fax Order Form, box by box
Patient and physician information
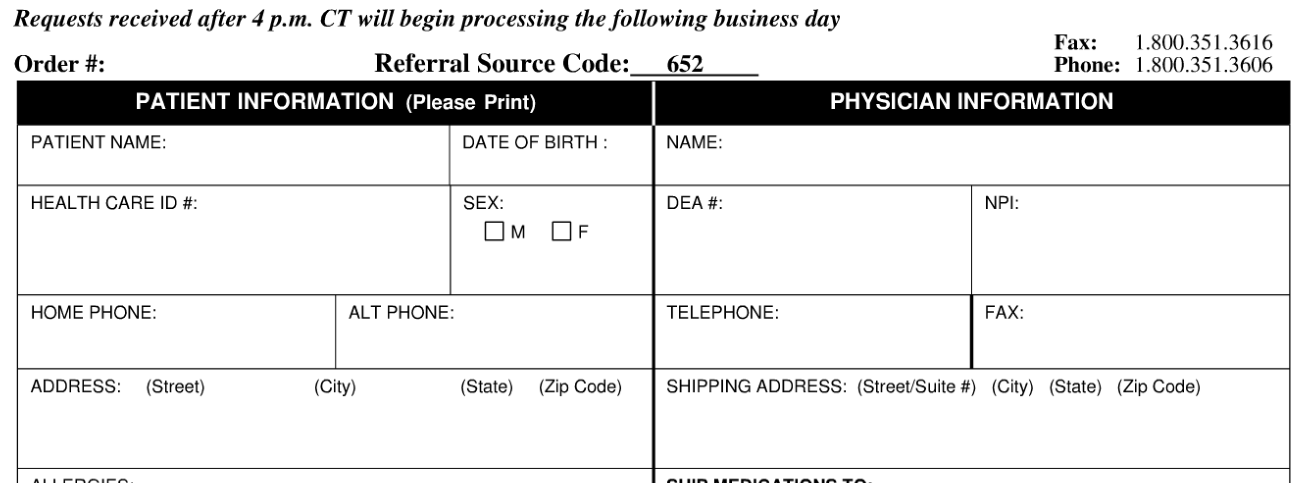
Under PATIENT INFORMATION (Please Print), fill in PATIENT NAME, DATE OF BIRTH, HEALTH CARE ID # and SEX.
Under PHYSICIAN INFORMATION, fill in NAME, DEA # and NPI.
Fill in HOME PHONE, ALT PHONE, TELEPHONE and FAX.
Fill in ADDRESS with (City) (State) (Zip Code), and SHIPPING ADDRESS with (Street/Suite #) (City) (State) (Zip Code).
Allergies, shipping, fax, prescription and signature
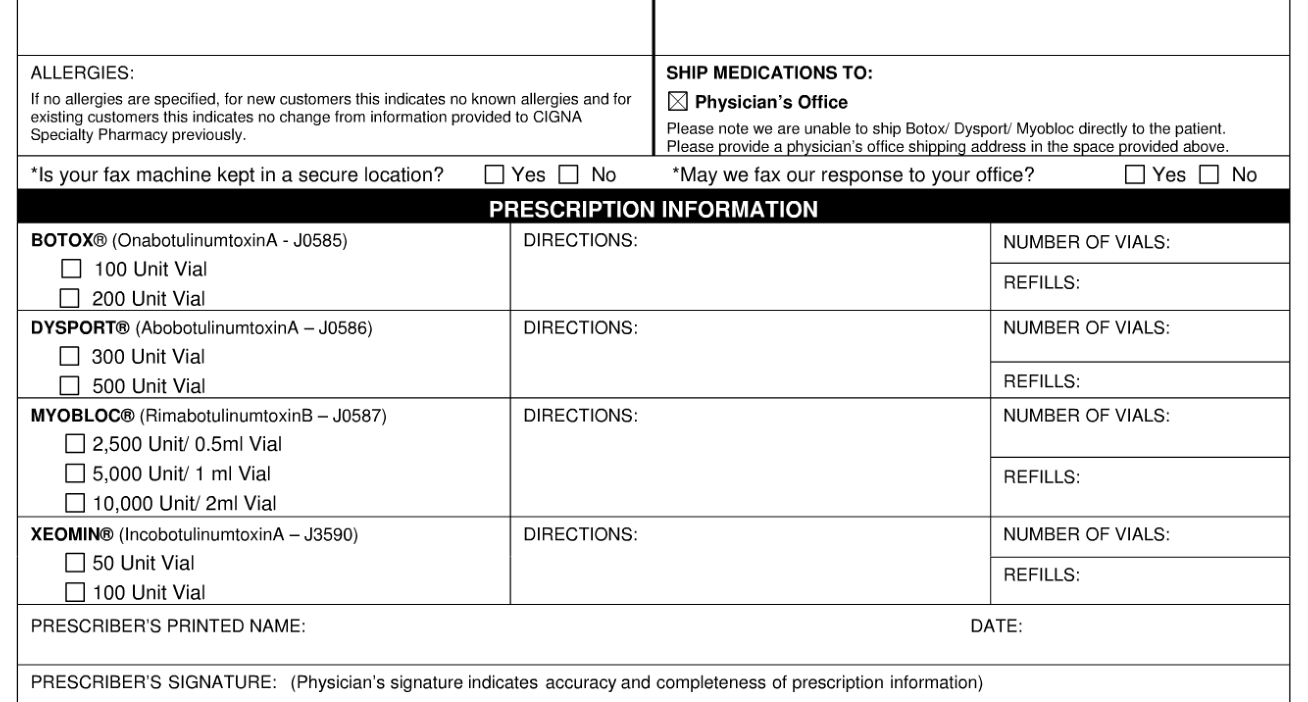
If no allergies are specified, for new customers this indicates no known allergies and for Physician's Office existing customers this indicates no change from information provided to CIGNA Specialty Pharmacy previously. CIGNA Specialty Pharmacy is unable to ship Botox/ Dysport/ Myobloc directly to the patient. Provide an office shipping address under SHIP MEDICATIONS TO. Is your fax machine kept in a secure location? May CIGNA fax its response to your office? Yes No. For BOTOX® (J0585), fill in DIRECTIONS, NUMBER OF VIALS and REFILLS for a 100 Unit Vial or 200 Unit Vial. For DYSPORT® (J0586), fill in DIRECTIONS, NUMBER OF VIALS and REFILLS for a 300 Unit Vial or 500 Unit Vial.
For J0587, fill in DIRECTIONS, NUMBER OF VIALS and REFILLS.
For XEOMIN® (J3590), fill in DIRECTIONS, NUMBER OF VIALS and REFILLS for a 50 Unit Vial or 100 Unit Vial.
Fill in PRINTED NAME and DATE, and sign on the SIGNATURE line; the signature indicates accuracy and completeness of prescription information.
In order for a brand name product to be dispensed, the prescriber must handwrite "Brand Necessary" or "Brand Medically Necessary" on the prescription.
Justification, diagnosis code and injection locations

Include documented progression of disease/prior therapies for justification for the drug.
Fill in the Diagnosis Code (ICD-9).
Specify in what location(s) of the body injections will be given and how many units are being injected into each muscle.
Dystonia conditions
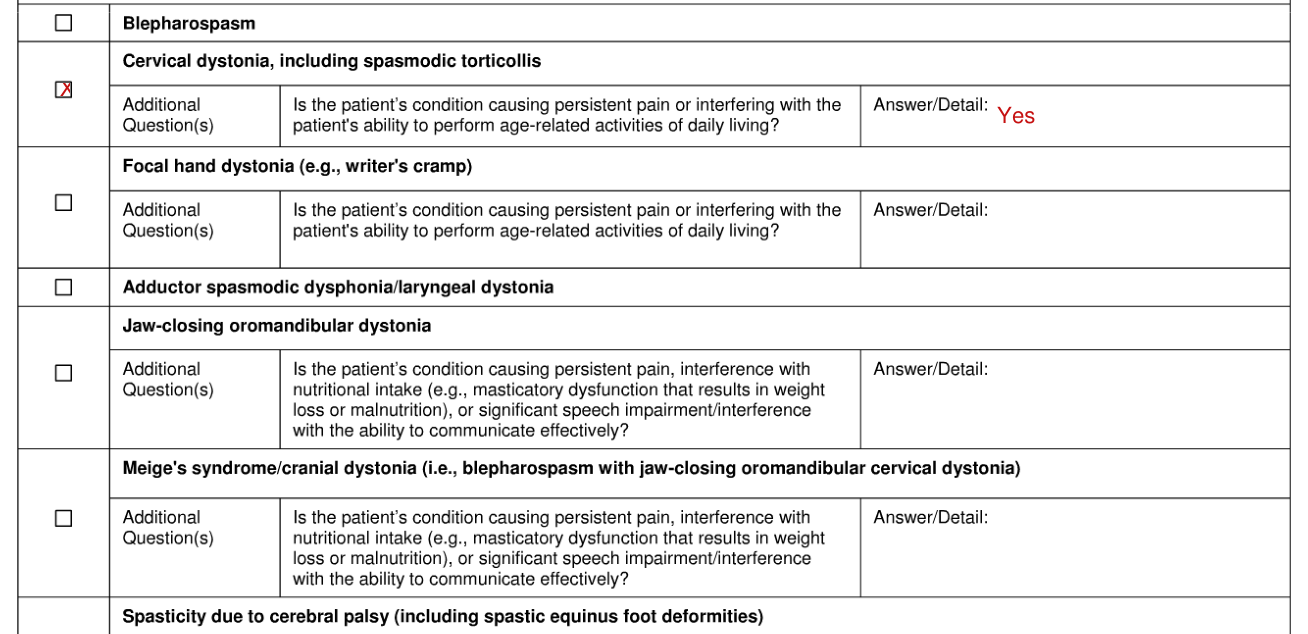
Indicate the condition Botox/ Dysport/ Myobloc is being used to treat and answer additional questions as necessary.
Include all applicable chart notes with this form.
Indicate Blepharospasm if Botox/ Dysport/ Myobloc is being used to treat it.
For Cervical dystonia, including spasmodic torticollis, answer: Is the patient's condition causing persistent pain or interfering with the patient's ability to perform age-related activities of daily living?
For Focal hand dystonia (e.g., writer's cramp), answer: Is the condition causing persistent pain or interfering with the patient's ability to perform age-related activities of daily living?
Indicate Adductor spasmodic dysphonia/laryngeal dystonia if Botox/ Dysport/ Myobloc is being used to treat it.
For Jaw-closing oromandibular dystonia, and for Meige's syndrome/cranial dystonia (i.e., blepharospasm with jaw-closing oromandibular cervical dystonia), answer: Is the patient's condition causing persistent pain, interference with nutritional intake (e.g., masticatory dysfunction that results in weight loss or malnutrition), or significant speech impairment/interference with the ability to communicate effectively?
Spasticity
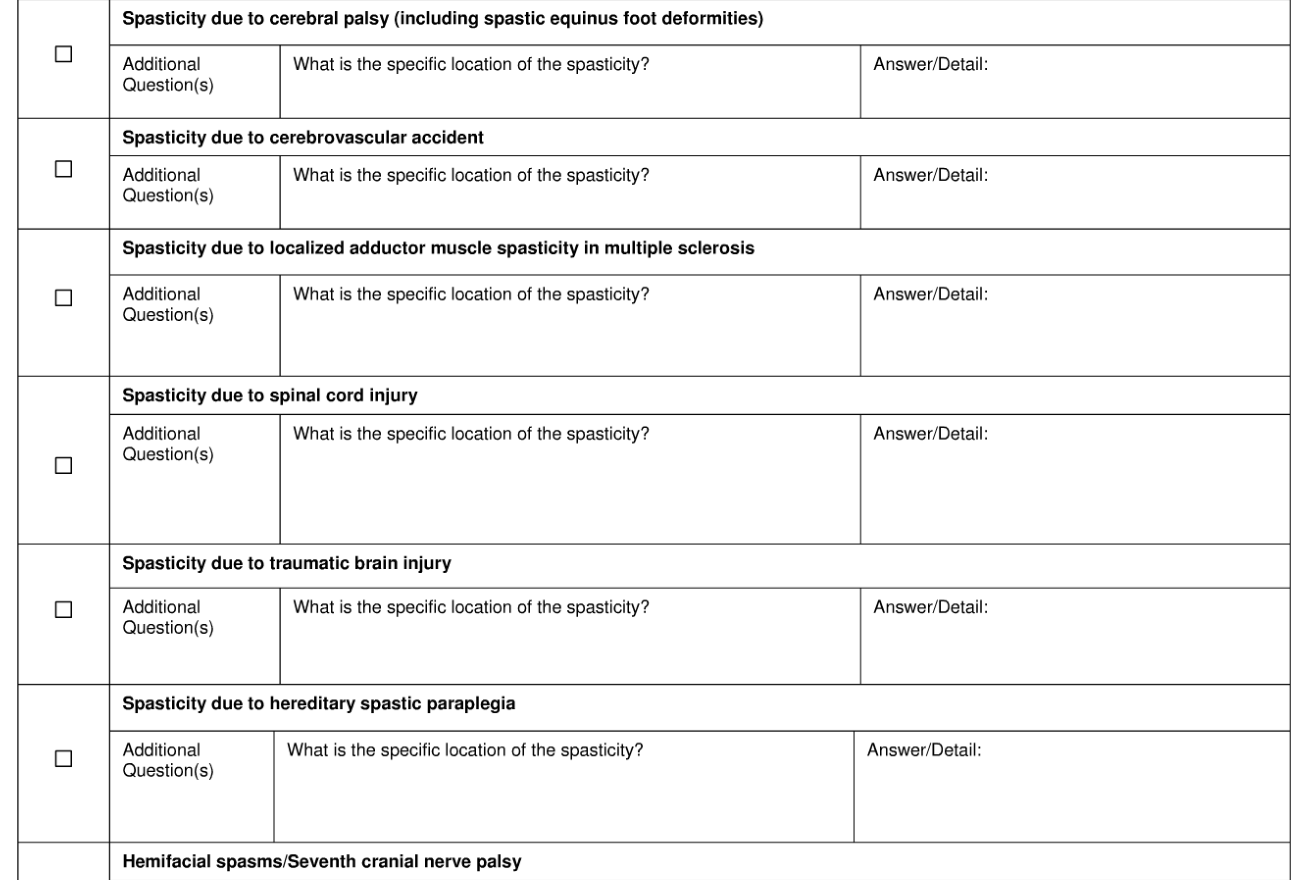
For Spasticity due to cerebral palsy (including spastic equinus foot deformities), answer: What is the specific location of the spasticity?
For Spasticity due to cerebrovascular accident, answer: What is the specific location of the spasticity?
For Spasticity due to localized adductor muscle spasticity in multiple sclerosis, answer: What is the specific location of the spasticity?
For Spasticity due to spinal cord injury, answer: What is the specific location of the spasticity?
For Spasticity due to traumatic brain injury, answer: What is the specific location of the spasticity?
For Spasticity due to hereditary spastic paraplegia, answer: What is the specific location of the spasticity?
Hemifacial spasms and seventh cranial nerve palsy

For Hemifacial spasms/Seventh cranial nerve palsy, answer: Is the condition causing persistent pain or vision impairment?
Strabismus and sixth nerve palsy
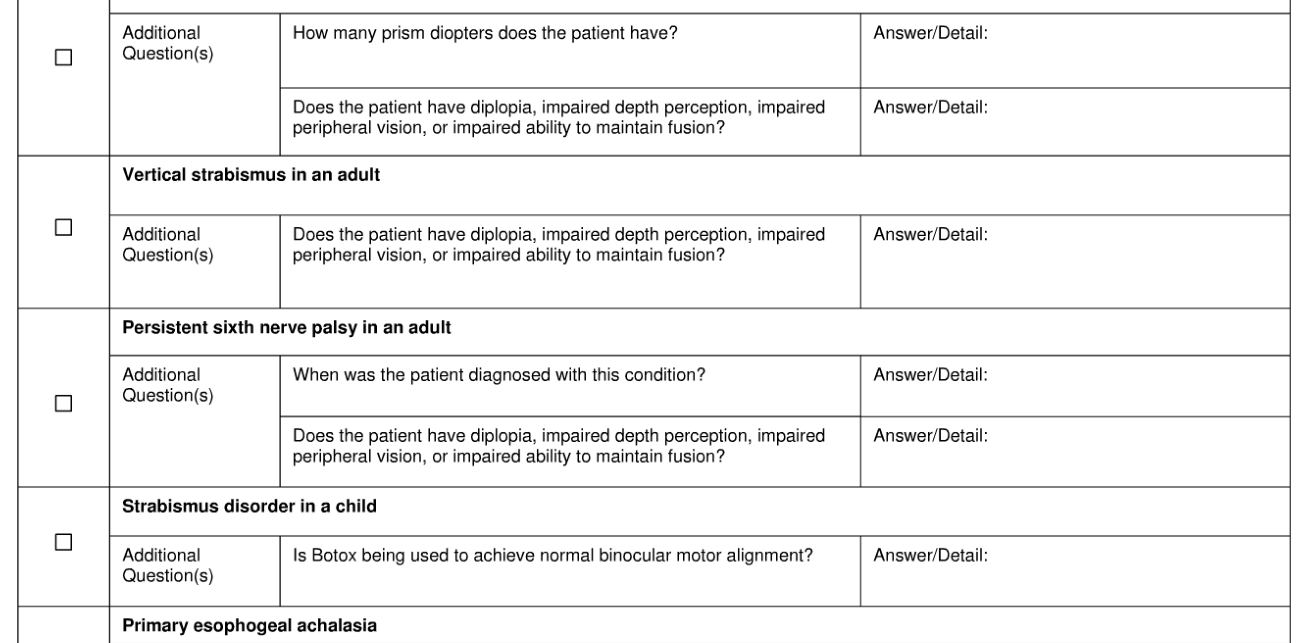
For Horizontal strabismus in an adult, Vertical strabismus in an adult, and Persistent sixth nerve palsy in an adult, answer: Does the patient have diplopia, impaired depth perception, impaired peripheral vision, or impaired ability to maintain fusion? For Horizontal strabismus in an adult, also answer: How many prism diopters does the patient have? For Persistent sixth nerve palsy in an adult, also answer: When was the patient diagnosed with this condition?
For Strabismus disorder in a child, answer: Is Botox being used to achieve normal binocular motor alignment?
Achalasia, anal fissure and hyperhidrosis
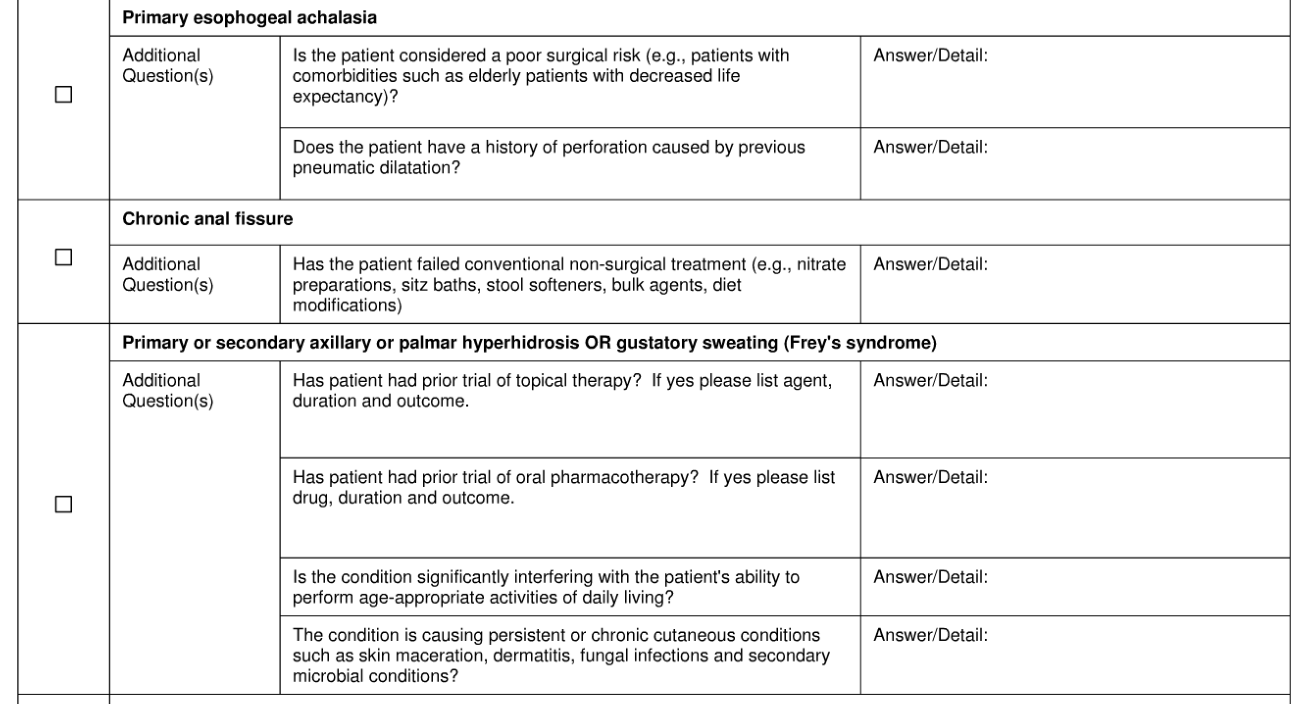
For Primary esophogeal achalasia, answer: Is the patient considered a poor surgical risk (e.g., patients with comorbidities such as elderly patients with decreased life expectancy)? Does the patient have a history of perforation caused by previous pneumatic dilatation?
For Chronic anal fissure, answer: Has the patient failed conventional non-surgical treatment (e.g., nitrate preparations, sitz baths, stool softeners, bulk agents, diet modifications)?
For Primary or secondary axillary or palmar hyperhidrosis OR gustatory sweating (Frey's syndrome), answer: Has patient had prior trial of topical therapy? If yes please list agent, duration and outcome in Answer/Detail. Has patient had prior trial of oral pharmacotherapy? If yes please list drug, duration and outcome in Answer/Detail.
For Primary or secondary axillary or palmar hyperhidrosis OR gustatory sweating (Frey's syndrome), answer: Is the condition significantly interfering with the patient's ability to perform age-appropriate activities of daily living? The condition is causing persistent or chronic cutaneous conditions such as skin maceration, dermatitis, fungal infections and secondary microbial conditions?
Tremor and glandular secretion
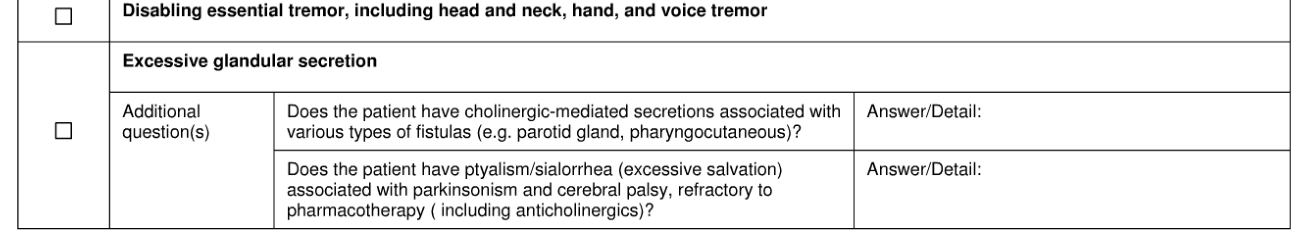
Indicate Disabling essential tremor, including head and neck, hand, and voice tremor if Botox/ Dysport/ Myobloc is being used to treat it.
For Excessive glandular secretion, answer: Does the patient have cholinergic-mediated secretions associated with various types of fistulas (e.g. parotid gland, pharyngocutaneous)? Does the patient have ptyalism/sialorrhea (excessive salvation) associated with parkinsonism and cerebral palsy, refractory to pharmacotherapy (including anticholinergics)?
Voiding dysfunction, migraine and other conditions
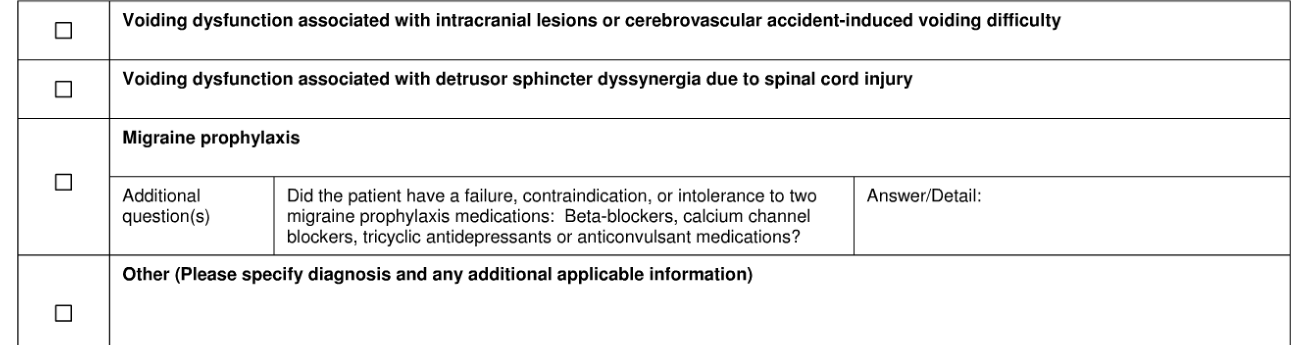
Indicate Voiding dysfunction associated with intracranial lesions or cerebrovascular accident-induced voiding difficulty if Botox/ Dysport/ Myobloc is being used to treat it.
Indicate Voiding dysfunction associated with detrusor sphincter dyssynergia due to spinal cord injury if Botox/ Dysport/ Myobloc is being used to treat it.
For Migraine prophylaxis, answer: Did the patient have a failure, contraindication, or intolerance to two migraine prophylaxis medications: Beta-blockers, calcium channel blockers, tricyclic antidepressants or anticonvulsant medications?
For Other, please specify diagnosis and any additional applicable information.
Common questions about CIGNA Botulinum Toxin Fax Order Form
Is there a deadline?
Requests received after 4 p.m. CT will begin processing the following business day. Phone: 1.800.351.3606.
Where do I file it?
Fax: 1.800.351.3616.
Sources
[1] CIGNA Specialty Pharmacy Services Botulinum Toxin Fax Order Form (Rev. 12/11) (the served file; no issuer file found) (the Official source link on this page).
