Pharmacy Prescription Form PDF Details

In today's digital and fast-paced world, the convenience and efficiency provided by mail-order pharmacies have become indispensable, particularly for those managing chronic conditions or living in remote areas. At the heart of this service lies the Pharmacy Prescription Form, a critical document that bridges patients with their much-needed medications. Managed by institutions like the WellCare Specialty Pharmacy Mail-Order Pharmacy, this form facilitates the seamless ordering and delivery of prescription drugs directly to patients' doorsteps. The form gathers essential member information, including the patient's ID, name, date of birth, gender, and contact details, ensuring that the pharmacy accurately processes and ships the right medication to the right person. It also collects vital data on allergies, further personalizing the care and reducing the risk of adverse reactions. Prescription information, including the drug name, strength, quantity, and refill details, is meticulously detailed to provide clear instructions for the pharmacy staff. The form highlights the commitment to not auto-ship medications without verification, reassuring members that their consent and preferences are paramount. A notable feature of the form is its policy on generic substitutes, promising to dispense FDA-approved generics when possible, which helps in managing healthcare costs without compromising quality. The form concludes with prescriber information, ensuring that every prescription is backed by a health professional's approval, solidifying the trust in the mail-order process. Additionally, the strict warning about the confidentiality of the information provided underscores the pharmacy's dedication to privacy and security, making the Pharmacy Prescription Form a cornerstone of modern pharmacy practice.

QuestionAnswer
Form NamePharmacy Prescription Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other nameswellcare online pharmacy, mail rx wellcare com, https mailrx wellcare com, cvs wellcare pharmacy

How to Fill Out Mail-Order Pharmacy Prescription Form

Mail-Order Pharmacy Prescription Form at a glance

What it is: Mail-Order Pharmacy Prescription Form: please fax completed form to WSP Mail-Order Pharmacy.

Where and when to file: Please fax completed form to WSP Mail-Order Pharmacy: 877-709-1694.

A filled-in Mail-Order Pharmacy Prescription Form example: a doctor orders one 90-day drug
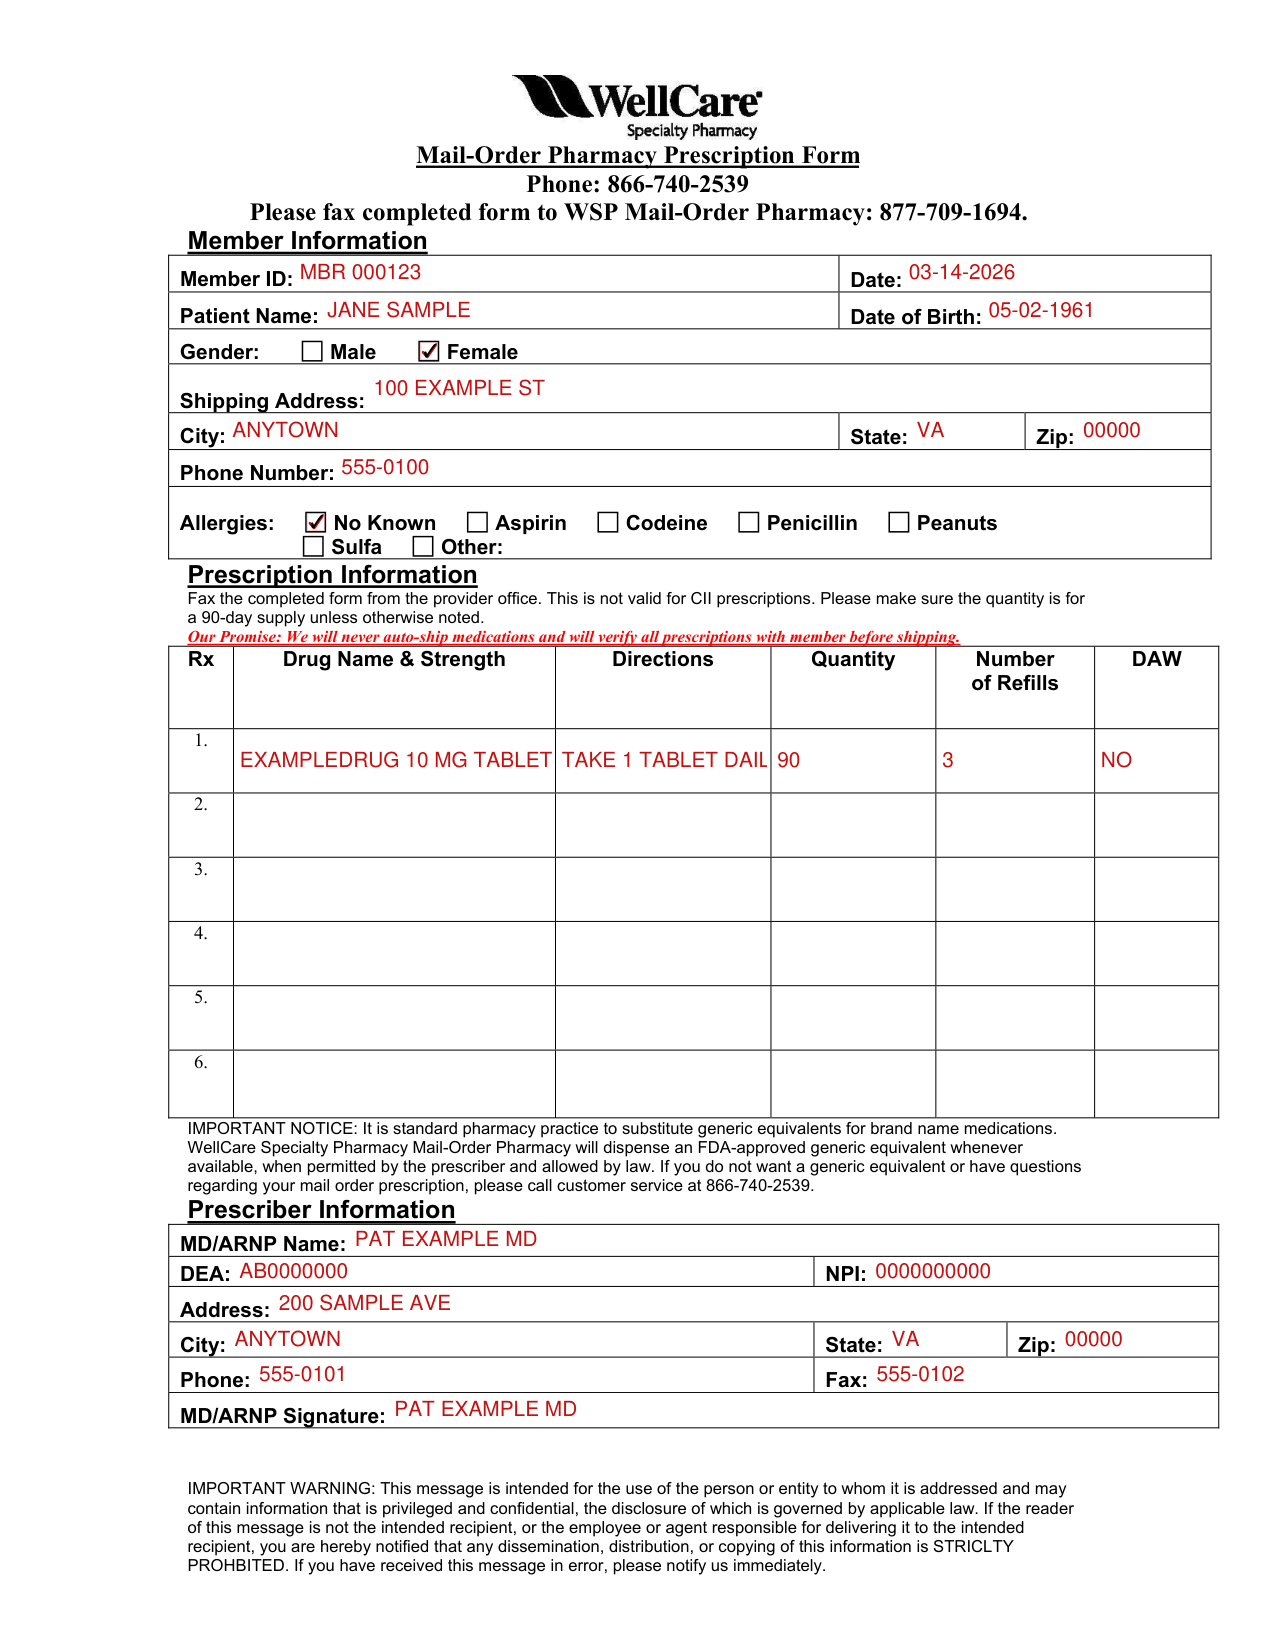
Mail-Order Pharmacy Prescription Form example filled out, example: a doctor orders one 90-day drug
A doctor fills out the Mail-Order Pharmacy Prescription Form for a member. The order is one drug in a 90-day supply for a female patient with no known allergies. The picture shows the finished form, and none of its entries is real.

How to fill out Mail-Order Pharmacy Prescription Form, box by box

Member Information

Mail-Order Pharmacy Prescription Form example filled out, member Information

Under Member Information, enter the Member ID and the Date.

Enter the Patient Name and the Date of Birth.

Mark the Gender, Male or Female, and enter the Shipping Address.

Enter the City, the State and the Zip.

Enter the Phone Number.

Allergies

Mail-Order Pharmacy Prescription Form example filled out, allergies

Under Allergies, mark No Known, Aspirin, Codeine, Penicillin, Peanuts, Sulfa or Other.

Prescription Information
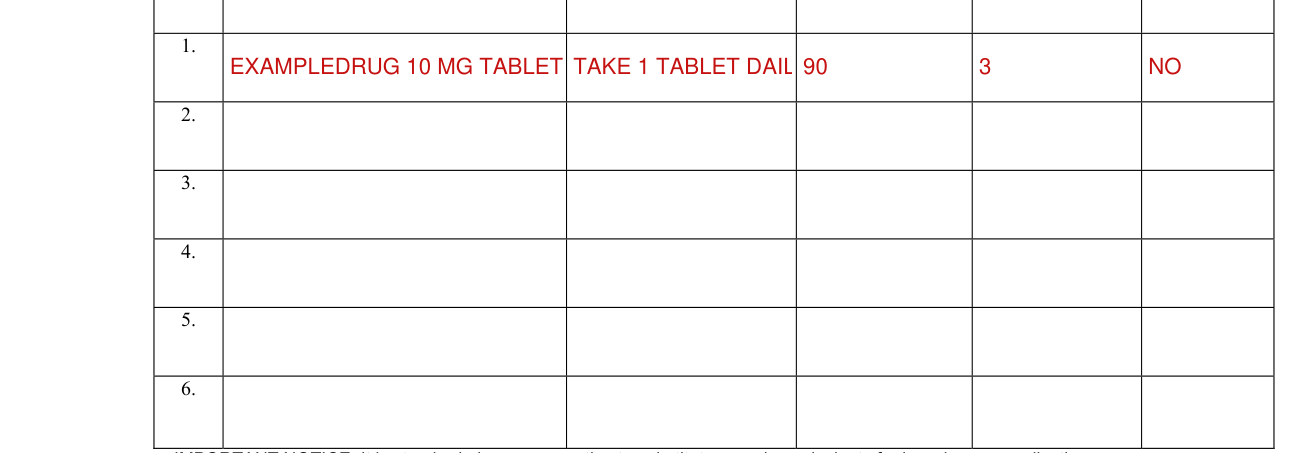
Mail-Order Pharmacy Prescription Form example filled out, prescription Information

Under Prescription Information: fax the completed form from the provider office. This is not valid for CII prescriptions. Please make sure the quantity is for a 90-day supply unless otherwise noted. Promise: never auto-ship medications; verify all prescriptions with member before shipping. For each Rx, enter the Drug Name & Strength, Directions, Quantity, Number of Refills and DAW.

Prescriber Information

Mail-Order Pharmacy Prescription Form example filled out, prescriber Information

Enter the MD/ARNP Name, the DEA and the NPI.

Enter the Address.

Enter the City, the State and the Zip.

Enter the Phone and Fax.

The MD/ARNP signs on the MD/ARNP Signature line.

It is standard pharmacy practice to substitute generic equivalents for brand name medications. WellCare Specialty Pharmacy Mail-Order Pharmacy will dispense an FDA-approved generic equivalent whenever available, when permitted by the prescriber and allowed by law. If you do not want a generic equivalent or have questions regarding your mail order prescription, please call customer service at 866-740-2539.

More rules for Mail-Order Pharmacy Prescription Form

Phone: 866-740-2539.

Sources

[1] Mail-Order Pharmacy Prescription Form (the Official source link on this page).

Please rate Pharmacy Prescription Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .