
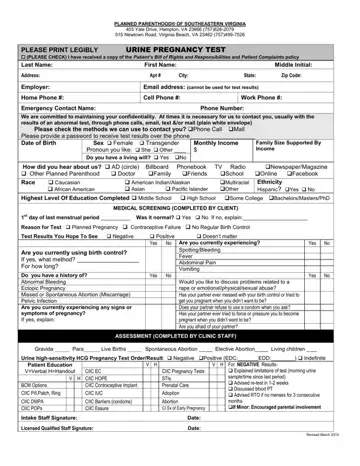
PLANNED PARENTHOOD OF SOUTHEASTERN VIRGINIA URINE PREGNANCY TEST form at a glance
What it is: The PLANNED PARENTHOOD OF SOUTHEASTERN VIRGINIA URINE PREGNANCY TEST form has a MEDICAL SCREENING (COMPLETED BY CLIENT) and an ASSESSMENT (COMPLETED BY CLINIC STAFF).
Who signs: The patient signs, and a witness signs.
A filled-in PLANNED PARENTHOOD OF SOUTHEASTERN VIRGINIA URINE PREGNANCY TEST form example: a patient lists one phone number
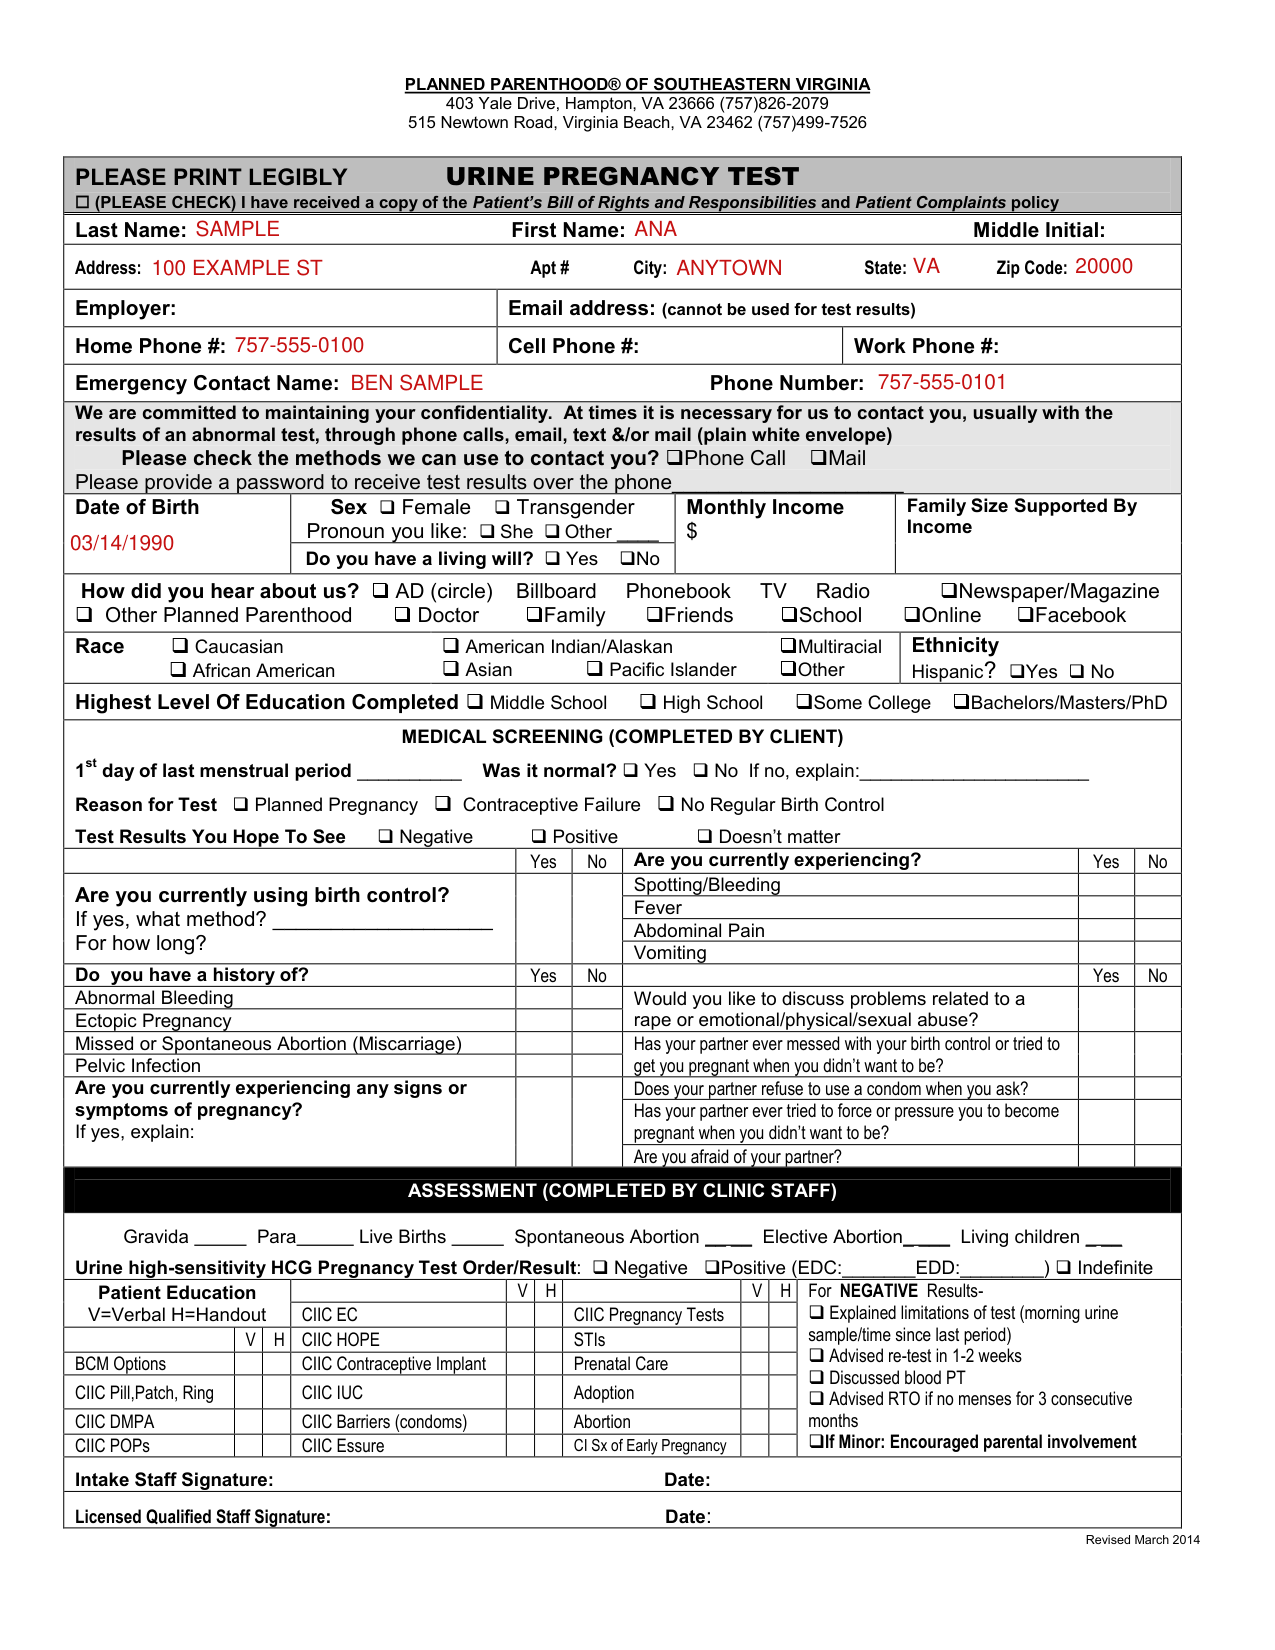
How to fill out PLANNED PARENTHOOD OF SOUTHEASTERN VIRGINIA URINE PREGNANCY TEST form, box by box
Last Name and First Name

Enter the Last Name, First Name and Middle Initial.
Address, City, State and Zip Code

Enter the Address, Apt #, City, State and Zip Code.
Home Phone #, Cell Phone # and Work Phone #

Enter the Home Phone #, Cell Phone # and Work Phone #.
Emergency Contact Name and Phone Number

Enter the Emergency Contact Name and Phone Number.
Date of Birth

Enter the Date of Birth.
Signature of patient and Date

Sign on the Signature of patient line and enter the Date.
Signature of witness and Date

The witness signs: I witness the fact that the patient received the information and said she/he read and understood same and had the opportunity to ask questions, and signs on the Signature of witness line with the Date.
Signature of any other person consenting

Check here if patient's guardian or relative is legally required to sign, and enter the Signature of any other person consenting, Relationship to patient and Date. The witness signs the Signature of witness and Date to witness the fact that the patient's legal guardian (or person consenting in her behalf) received the information and said she read and understood same.
More rules for PLANNED PARENTHOOD OF SOUTHEASTERN VIRGINIA URINE PREGNANCY TEST form
Check the box for I have received a copy of the Patient's Bill of Rights and Responsibilities and Patient Complaints policy.
Enter the Employer and the Email address, which cannot be used for test results.
At times it is necessary to contact you, usually with the results of an abnormal test, through phone calls, email, text &/or mail (plain white envelope). Check the methods to contact you.
Please provide a password to receive test results over the phone.
Under Sex, mark Female or Transgender, and under Pronoun you like, mark She or Other.
Enter the Monthly Income $ and the Family Size Supported By Income.
Mark Yes or No for Do you have a living will?
Mark Race, Ethnicity Hispanic? Yes or No, and Highest Level Of Education Completed.
Under MEDICAL SCREENING (COMPLETED BY CLIENT), enter the 1st day of last menstrual period, mark Was it normal? Yes or No, and if no, explain.
Mark the Reason for Test: Planned Pregnancy, Contraceptive Failure or No Regular Birth Control, and the Test Results You Hope To See: Negative, Positive or Doesn't matter.
Mark Yes or No for each one under Are you currently experiencing?: Spotting/Bleeding, Fever, Abdominal Pain and Vomiting.
Mark Are you currently using birth control? and, if yes, what method and For how long.
Mark Yes or No for each one under Do you have a history of?: Abnormal Bleeding, Ectopic Pregnancy, Missed or Spontaneous Abortion (Miscarriage) and Pelvic Infection.
Mark Yes or No for Has your partner ever messed with your birth control or tried to get you pregnant when you didn't want to be?, Does your partner refuse to use a condom when you ask?, Has your partner ever tried to force or pressure you to become pregnant when you didn't want to be? and Are you afraid of your partner?
Mark Yes or No for Would you like to discuss problems related to a rape or emotional/physical/sexual abuse?
Mark Are you currently experiencing any signs or symptoms of pregnancy? and, if yes, explain.
Clinic staff complete the ASSESSMENT (COMPLETED BY CLINIC STAFF).
You may ask for a copy of this form.
You must tell the staff if language interpreter services are necessary to your understanding of the written or spoken information given during your health care visits.
If tests for certain sexually transmitted infections are positive, reporting of positive results to public health agencies is required by law.
At any time, you can change your mind about receiving medical services at Planned Parenthood.
If referral is needed, you will assume responsibility for obtaining and paying for this care.
Common questions about PLANNED PARENTHOOD OF SOUTHEASTERN VIRGINIA URINE PREGNANCY TEST form
What am I certifying when I sign?
The information you provide is true, accurate, and complete and your healthcare choices will depend on that information.
Sources
[1] Planned Parenthood of Southeastern Virginia, Please Print Legibly Urine Pregnancy Test Revised March 2014 (the Official source link on this page).
