

Form 21-4192 at a glance
What it is: Request for Employment Information in Connection with Claim for Disability Benefits: the veteran named in Item 3 has filed a claim for veterans disability benefits and has stated that he/she was recently employed by you.
Where and when to file: After completing the form, mail to: Department of Veterans Affairs Evidence Intake Center P.O. Box 4444 Janesville, WI 53547-4444.
A filled-in Form 21-4192 example: an employer reports a veteran's last job
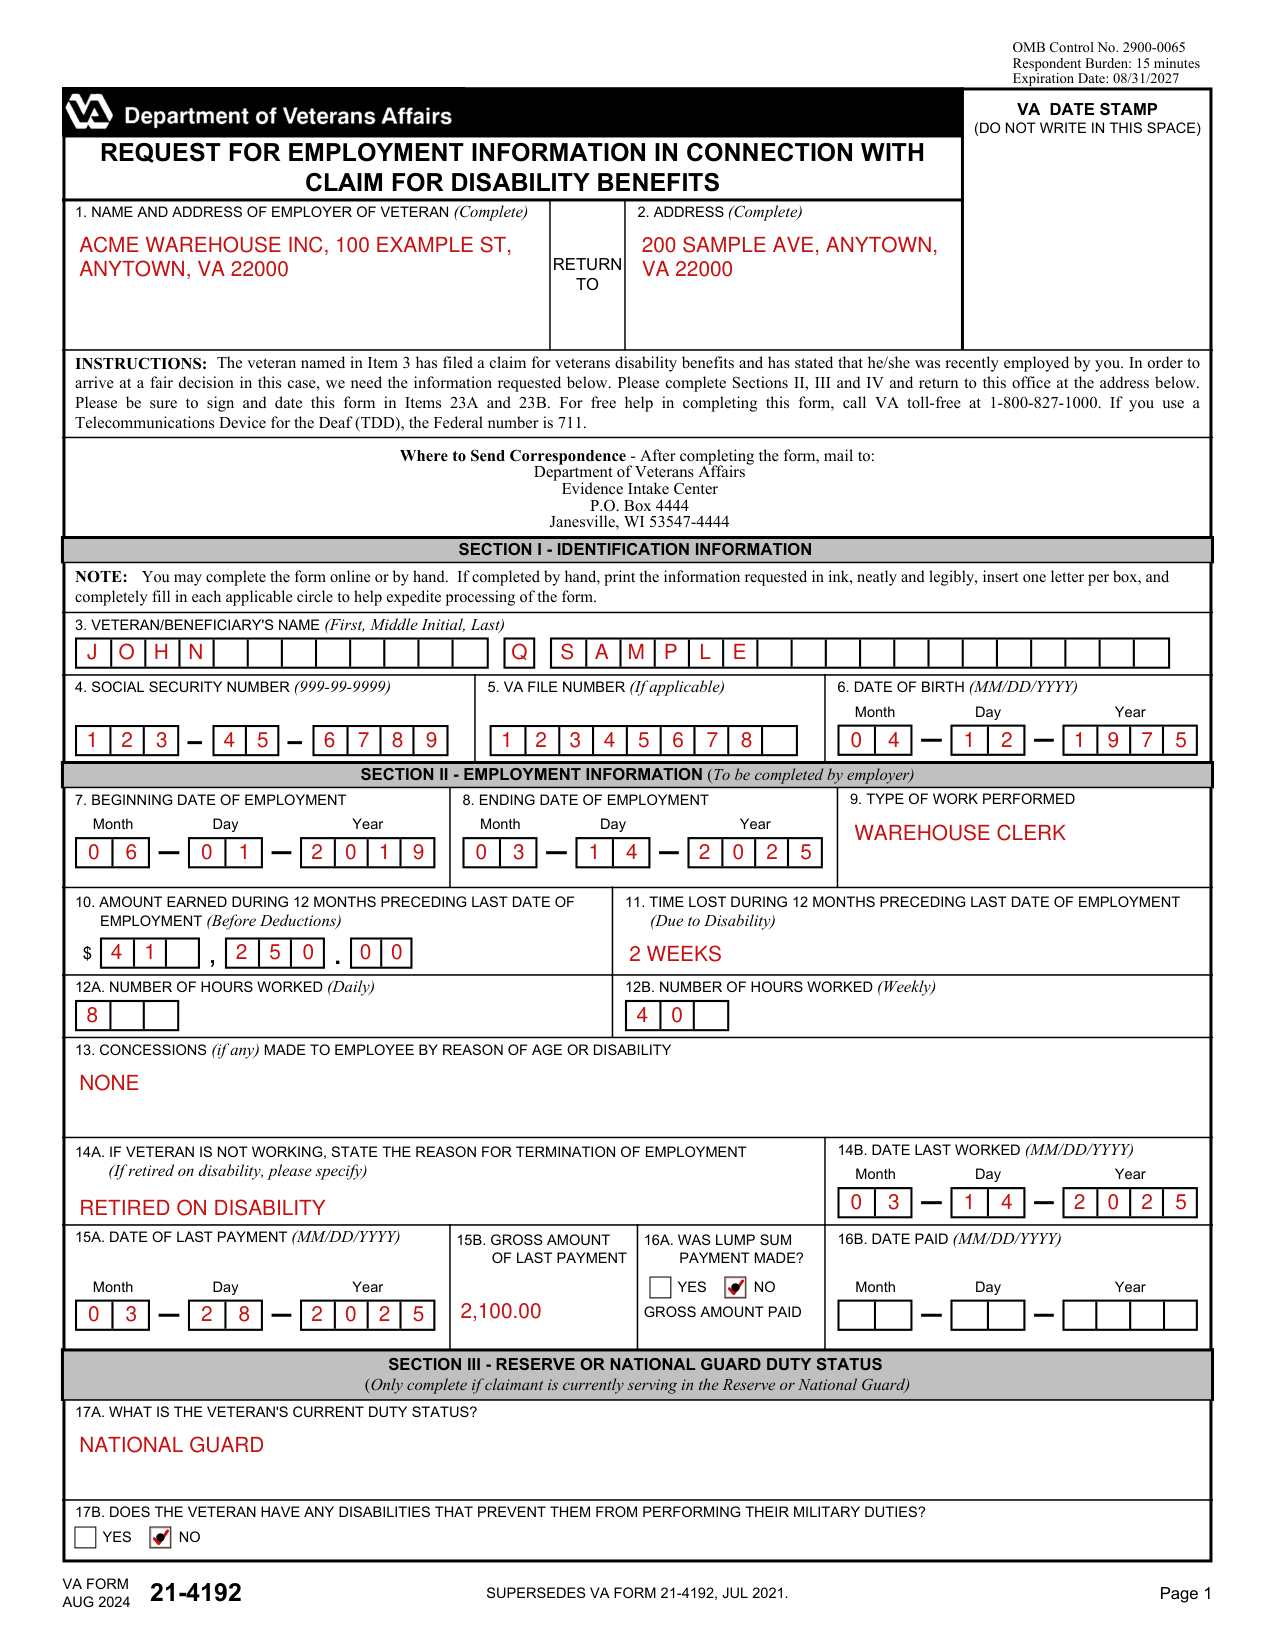
How to fill out Form 21-4192, box by box
Name and address of employer of veteran, and return address

Enter 1. Name and Address of Employer of Veteran (Complete). For RETURN TO, enter 2. Address (Complete).
Section I, veteran's name, social security number and date of birth
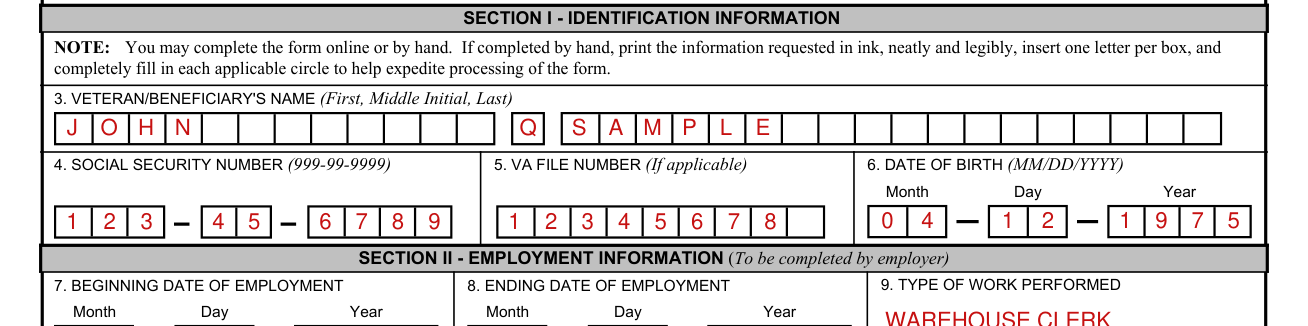
You may complete the form online or by hand. If completed by hand, print the information requested in ink, neatly and legibly, insert one letter per box, and completely fill in each applicable circle to help expedite processing of the form.
In Section I, enter 3. Veteran/Beneficiary's Name (First, Middle Initial, Last), 4. Social Security Number (999-99-9999), 5. VA File Number (If applicable) and 6. Date of Birth (MM/DD/YYYY).
Section II, dates and type of work performed
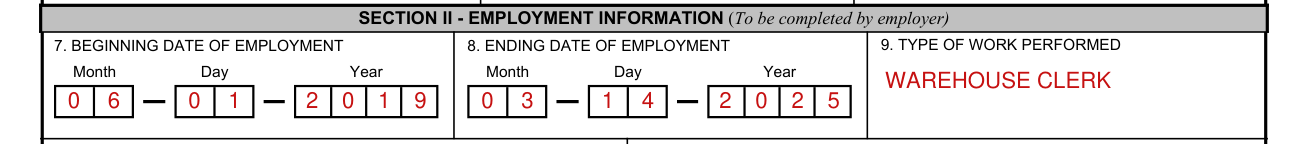
In Section II, enter 7. Beginning Date of Employment, 8. Ending Date of Employment and 9. Type of Work Performed.
Amount earned, time lost, hours worked and concessions
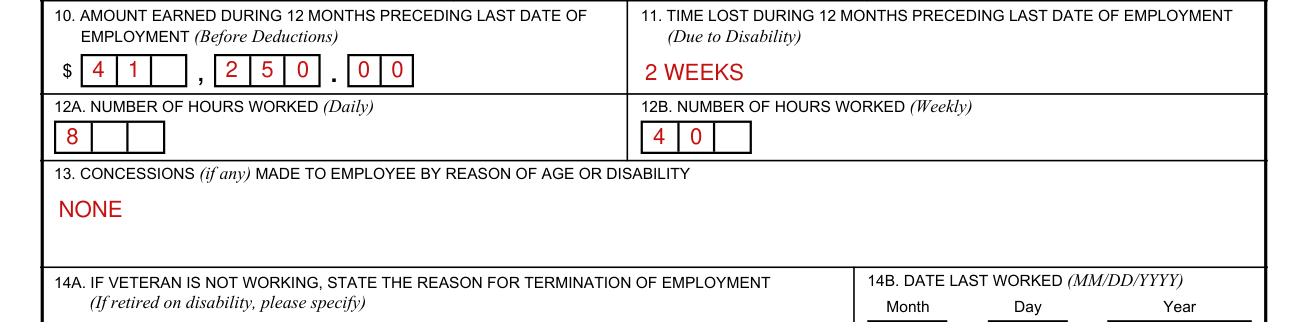
Enter 10. Amount Earned During 12 Months Preceding Last Date of Employment (Before Deductions) and 11. Time Lost During 12 Months Preceding Last Date of Employment (Due to Disability).
Enter 12A. Number of Hours Worked (Daily), 12B. Number of Hours Worked (Weekly) and 13. Concessions (if any) Made to Employee by Reason of Age or Disability.
Reason for termination, date last worked and last payments

14A. If Veteran is Not Working, enter the Reason for Termination of Employment (If retired on disability, please specify). 14B. Enter the Date Last Worked (MM/DD/YYYY).
Enter 15A. Date of Last Payment (MM/DD/YYYY) and 15B. Gross Amount of Last Payment.
16A. Was Lump Sum Payment Made? Mark YES or NO. Enter the Gross Amount Paid and 16B. Date Paid (MM/DD/YYYY).
Section III, Reserve or National Guard duty status

Section III - Reserve or National Guard Duty Status: Only complete if claimant is currently serving in the Reserve or National Guard.
Enter 17A. the Veteran's Current Duty Status. For 17B. Does the Veteran have any disabilities that prevent them from performing their military duties? mark YES or NO.
Section IV, type of benefit, gross monthly amount and dates
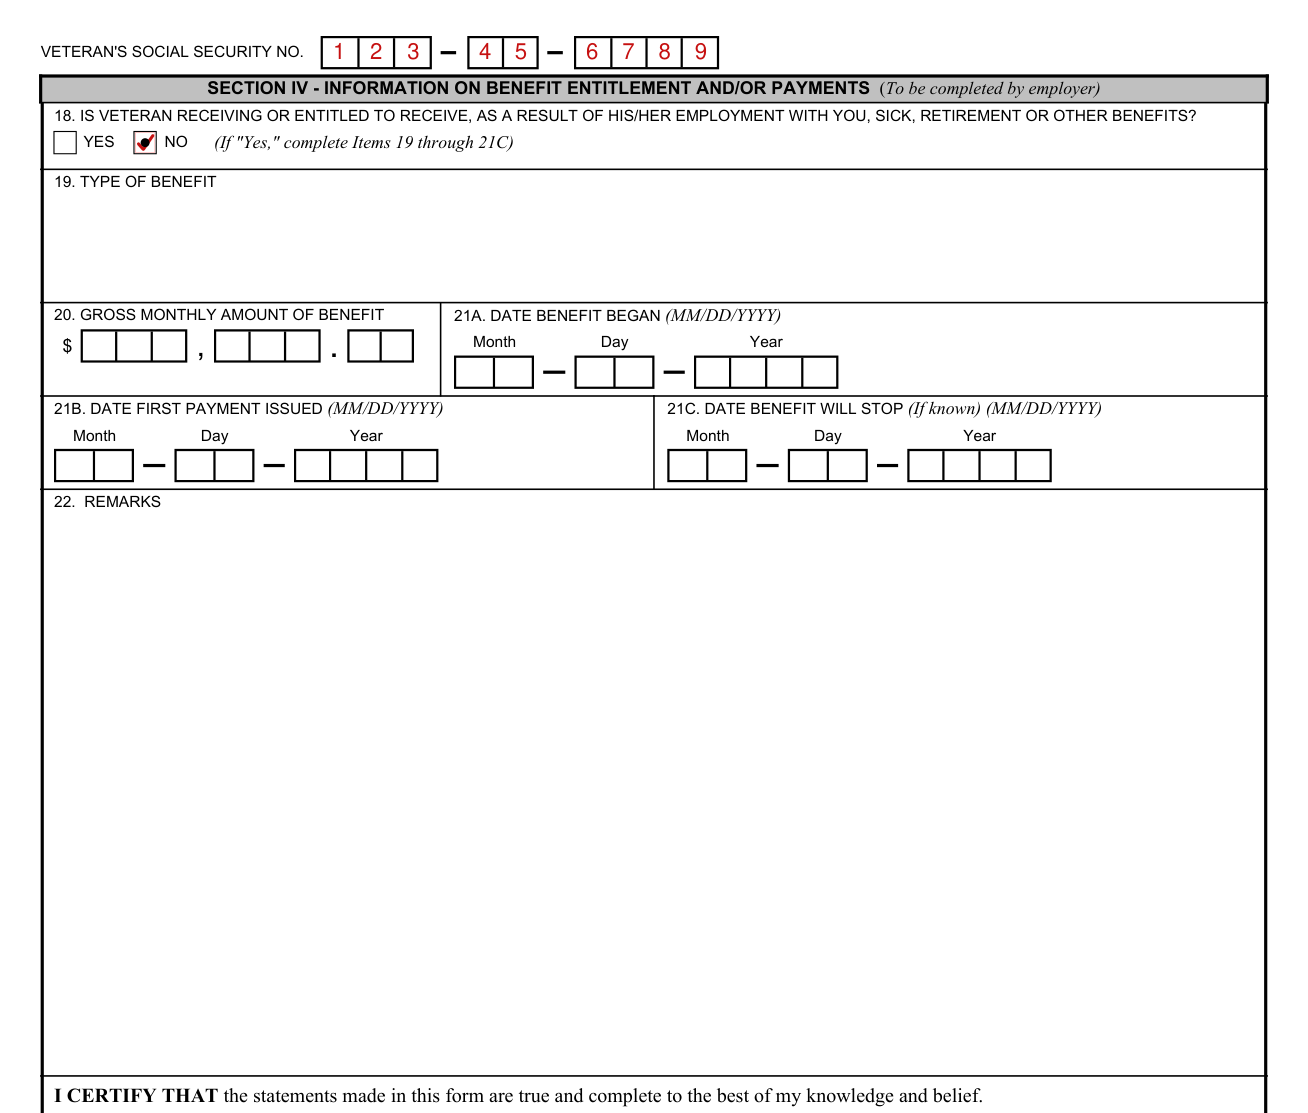
Enter the Veteran's Social Security No.
18. Is Veteran Receiving or Entitled to Receive, as a Result of His/Her Employment With You, Sick, Retirement or Other Benefits? Mark YES or NO. If "Yes," complete Items 19 through 21C.
Enter 19. Type of Benefit and 20. Gross Monthly Amount of Benefit.
Enter 21A. Date Benefit Began (MM/DD/YYYY), 21B. Date First Payment Issued (MM/DD/YYYY) and 21C. Date Benefit Will Stop (If known) (MM/DD/YYYY).
Enter 22. Remarks.
Signature of employer or supervisor and date signed

I CERTIFY THAT the statements made in this form are true and complete to the best of my knowledge and belief. Sign 23A. Signature of Employer or Supervisor (Required) and enter 23B. Date Signed (MM/DD/YYYY).
Please be sure to sign and date this form in Items 23A and 23B.
More rules for Form 21-4192
For free help in completing this form, call VA toll-free at 1-800-827-1000. If you use a Telecommunications Device for the Deaf (TDD), the Federal number is 711.
Common questions about Form 21-4192
Do I need to fill out VA form 21 4192?
The veteran has filed a claim for veterans disability benefits and has stated that he/she was recently employed by you. Please complete Sections II, III and IV.
Where do I file it?
After completing the form, mail to: Department of Veterans Affairs Evidence Intake Center P.O. Box 4444 Janesville, WI 53547-4444.
Is there a penalty?
The law provides severe penalties which include fine or imprisonment, or both, for the willful submission of any statement or evidence of a material fact, knowing it to be false, or for fraudulent acceptance of any payment to which you are not entitled.
Sources
[1] Form 21-4192 (AUG 2024), Request for Employment Information in Connection with Claim for Disability Benefits, Department of Veterans Affairs (the Official source link on this page).
