

Medical Claim Form (SCF0515) at a glance
What it is: The Medical Claim Form is for medical claims.
Where and when to file: Mail Claim Form To: Cigna P. O. Box 188007 Chattanooga, TN 37422
You only need to fill out this form if your health care professional isn't filing the claim for you.
Even if not part of the Cigna PPO network (out-of-network), your health care professional still can file the claim for you.
What to bring and attach to Medical Claim Form (SCF0515)
You need an itemized bill to process the claim correctly. Receipts, balance due statements and cancelled checks can't be accepted in place of the itemized bill.
Itemized bills must include: Member name Type of service/Procedure code Health care professional name/credentials Date of Service (mm/dd/yyyy) Charge for the service Health care professional address Patient name Diagnosis code (ICD format) Health care professional Tax ID number Health care provider signature Health care professional NPI number
A filled-in Medical Claim Form (SCF0515) example: a member files a medical claim for herself
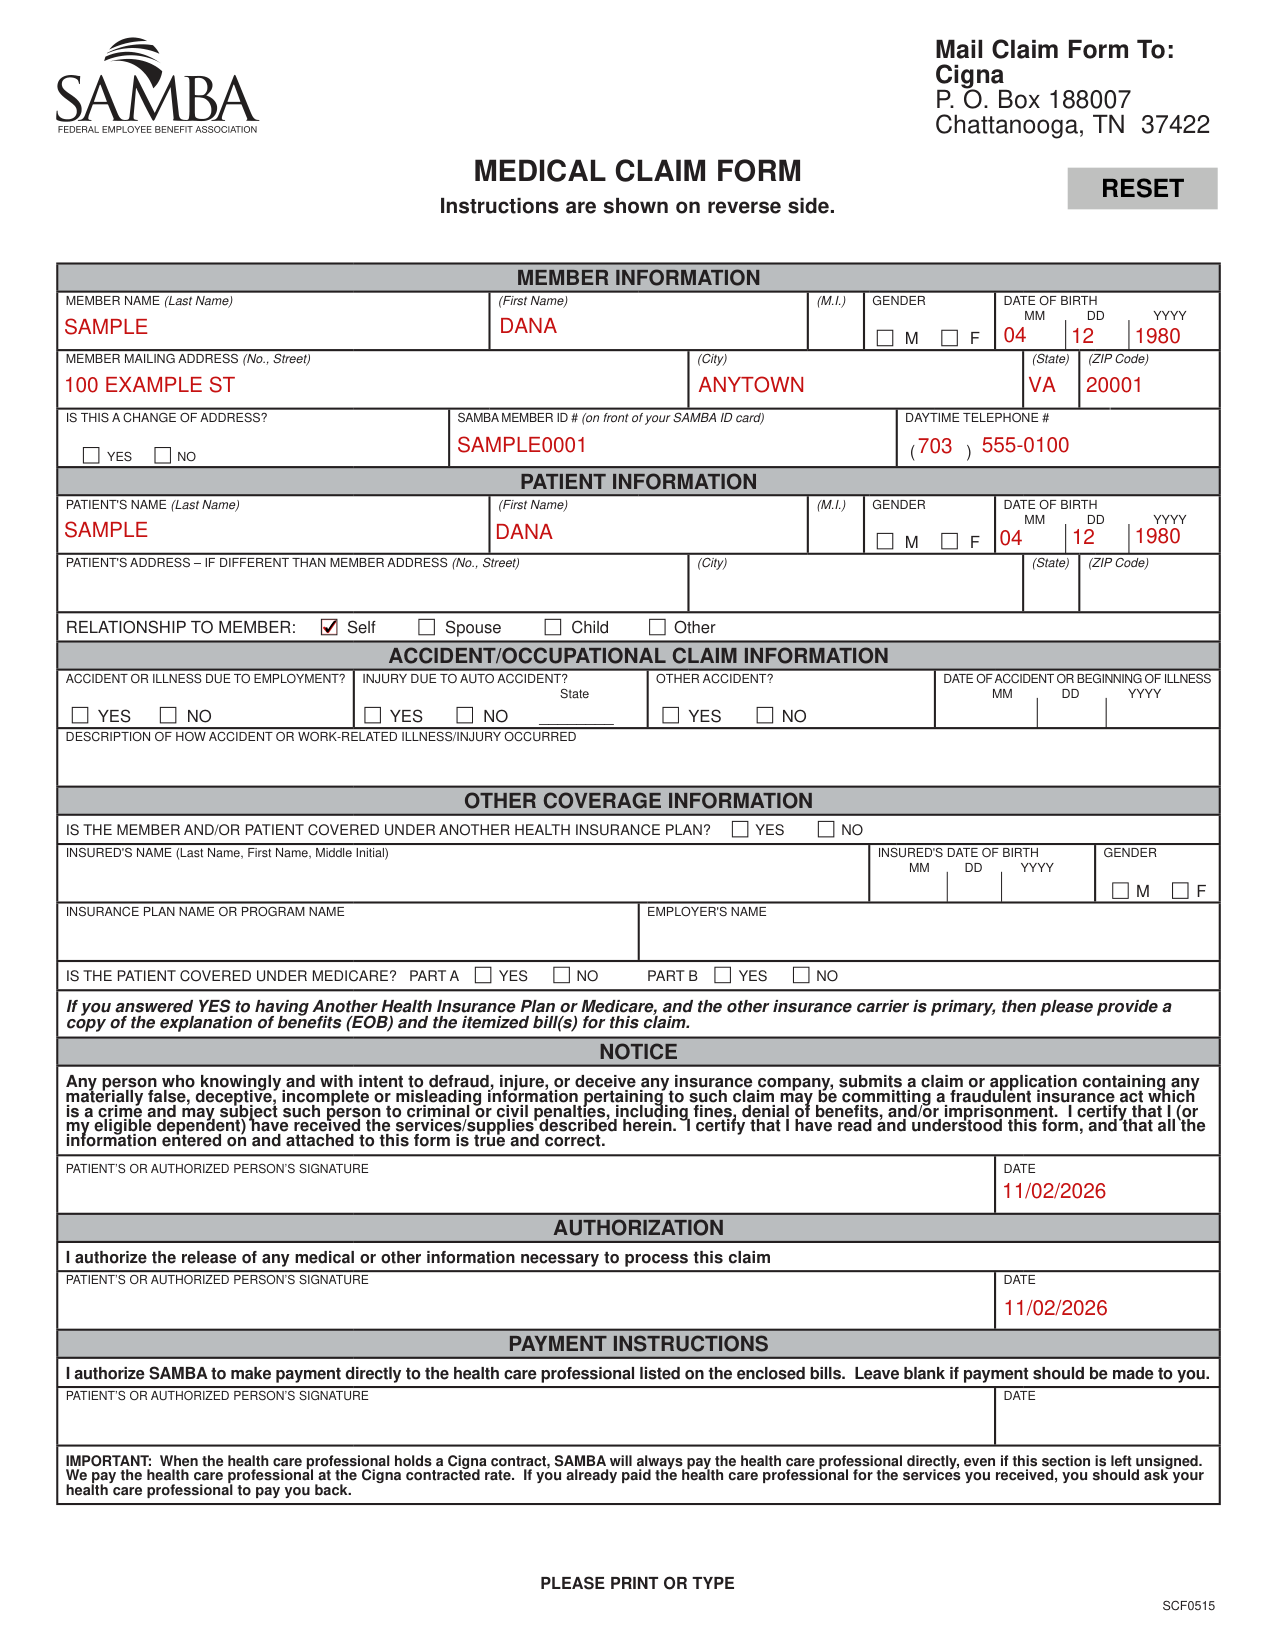
How to fill out Medical Claim Form (SCF0515), box by box
Member information
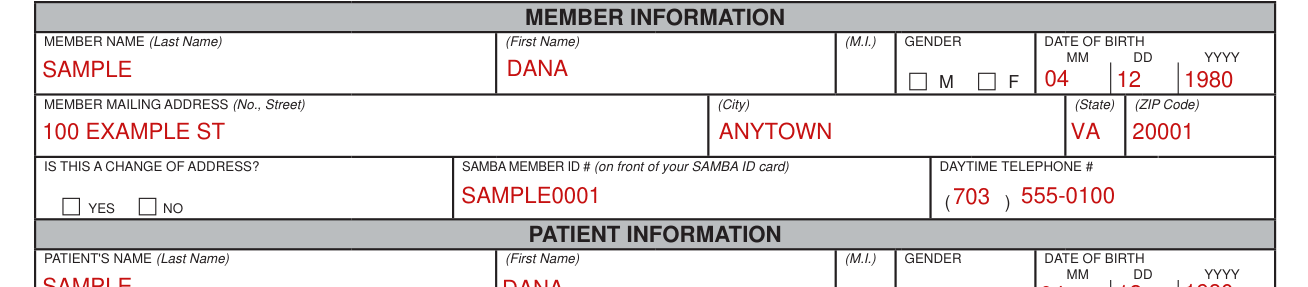
Under MEMBER INFORMATION, fill in the MEMBER NAME (Last Name) (First Name) (M.I.), GENDER and DATE OF BIRTH MM DD YYYY.
Fill in the MEMBER MAILING ADDRESS (No., Street) (City) (State) (ZIP Code) and mark IS THIS A CHANGE OF ADDRESS? YES NO.
To process your claim, SAMBA needs your ID number. It's on the front of your SAMBA ID card.
Fill in the SAMBA MEMBER ID # (on front of your SAMBA ID card) and the DAYTIME TELEPHONE #.
Patient information
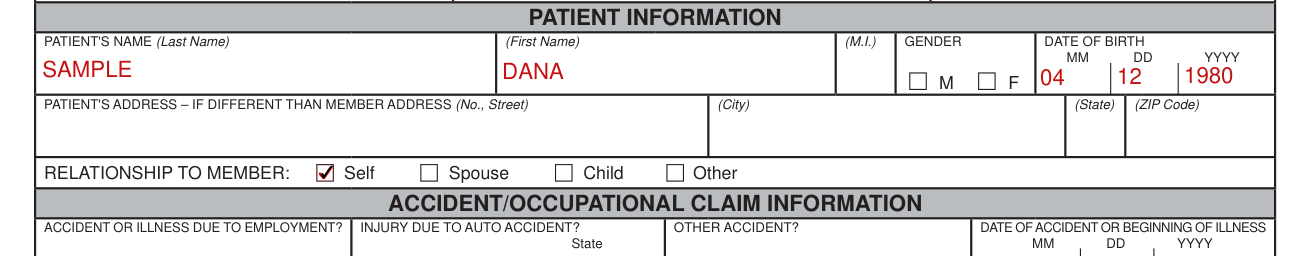
Under PATIENT INFORMATION, fill in the PATIENT'S NAME (Last Name) (First Name) (M.I.), GENDER and DATE OF BIRTH MM DD YYYY.
Mark the RELATIONSHIP TO MEMBER: Self Spouse Child Other.
Patient's address if different than member address

Fill in the PATIENT'S ADDRESS - IF DIFFERENT THAN MEMBER ADDRESS (No., Street) (City) (State) (ZIP Code).
Accident or occupational claim information
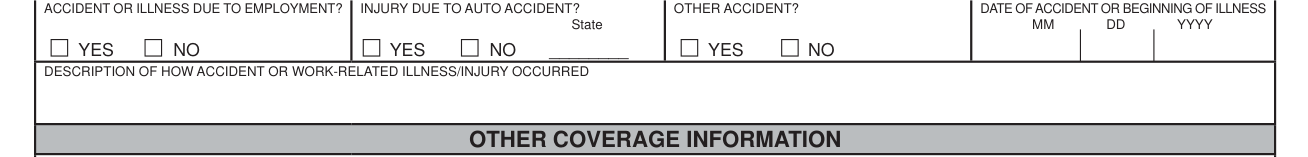
Under ACCIDENT/OCCUPATIONAL CLAIM INFORMATION, mark YES or NO for ACCIDENT OR ILLNESS DUE TO EMPLOYMENT?, INJURY DUE TO AUTO ACCIDENT? State and OTHER ACCIDENT?, then fill in the DATE OF ACCIDENT OR BEGINNING OF ILLNESS MM DD YYYY.
Fill in the DESCRIPTION OF HOW ACCIDENT OR WORK-RELATED ILLNESS/INJURY OCCURRED.
Other coverage information
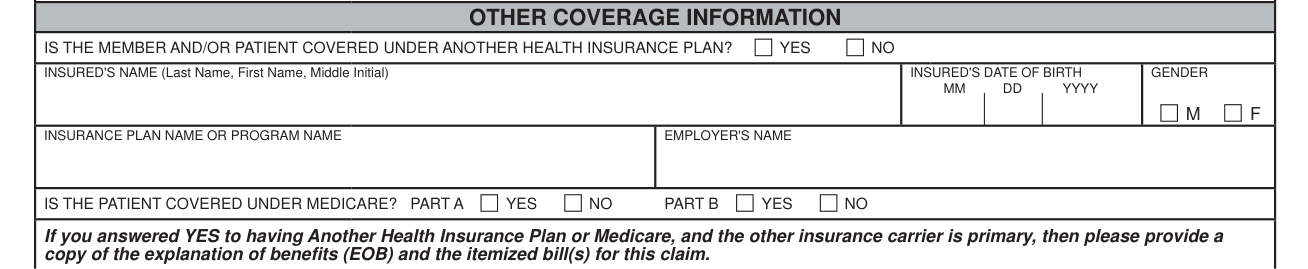
Under Other Coverage Information, mark yes or no: Is the member and/or patient covered under another health insurance plan?
Fill in the INSURED'S NAME (Last Name, First Name, Middle Initial), INSURED'S DATE OF BIRTH MM DD YYYY, GENDER, INSURANCE PLAN NAME OR PROGRAM NAME and EMPLOYER'S NAME.
Mark IS THE PATIENT COVERED UNDER MEDICARE? PART A YES NO PART B YES NO.
If you answered YES to having Another Health Insurance Plan or Medicare, and the other insurance carrier is primary, then please provide a copy of the explanation of benefits (EOB) and the itemized bill(s) for this claim.
If the patient has other health insurance coverage, and that other insurance is primary and SAMBA secondary, SAMBA needs an Explanation of Benefits (EOB) for this service from the other insurance company when you send the completed form and itemized bill.
Signatures and authorization
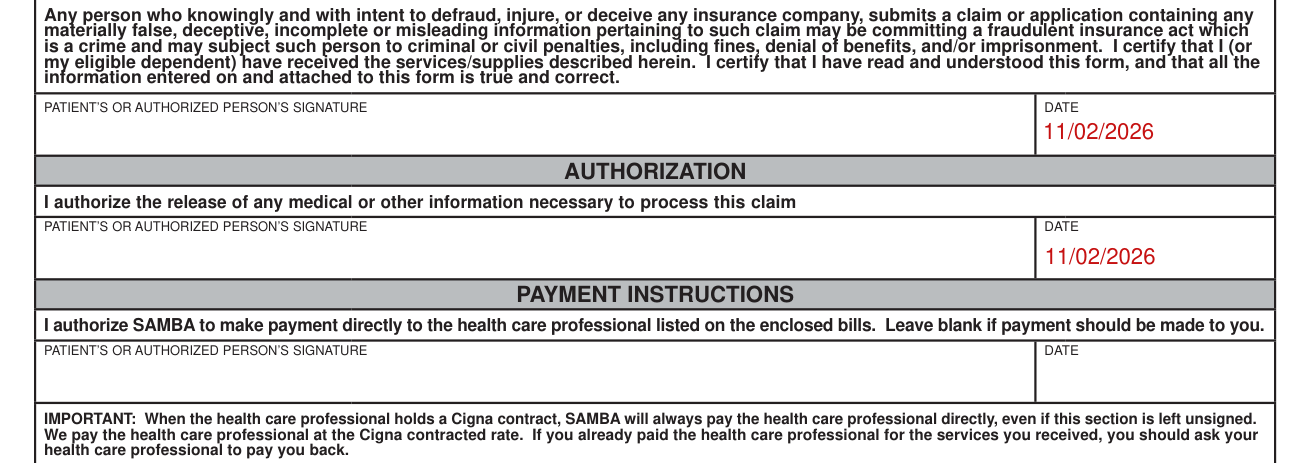
By signing you certify that you (or your eligible dependent) have received the services/supplies described herein, that you have read and understood this form, and that all the information entered on and attached to this form is true and correct.
Sign the PATIENT'S OR AUTHORIZED PERSON'S SIGNATURE and fill in the DATE.
Under AUTHORIZATION, sign the PATIENT'S OR AUTHORIZED PERSON'S SIGNATURE and DATE for: I authorize the release of any medical or other information necessary to process this claim
Payment instructions

Leave the PAYMENT INSTRUCTIONS blank if payment should be made to you. To have SAMBA pay the health care professional directly, sign the PATIENT'S OR AUTHORIZED PERSON'S SIGNATURE and DATE for: I authorize SAMBA to make payment directly to the health care professional listed on the enclosed bills.
When the health care professional holds a Cigna contract, SAMBA will always pay the health care professional directly, even if this section is left unsigned. The health care professional is paid at the Cigna contracted rate. If you already paid the health care professional for the services you received, you should ask your health care professional to pay you back.
More rules for Medical Claim Form (SCF0515)
Please use a separate claim form for each health care professional, and for each member of your family.
If you are sending one claim, please don't staple or paper clip the bills to the claim form. If you are sending more than one claim in the same envelope, then please use a paper clip to keep the claim form and itemized bills together.
If you are filling the form out by hand, use a new printed form instead of a photocopy. That way the form can be processed with no delays. Please print clearly in black ink.
If you received this claim form electronically, click to the right of the each field and type in the information. Once done, remember to click on the Reset button on the bottom of page 1 after printing out the completed form.
You can get a new blank form by going to www.SambaPlans.com or by calling Customer Service toll-free at 1-800-638-6589.
You can find information on how to file Pharmacy or Dental and Vision claims at www.SambaPlans.com.
Make a copy of your bill(s) and your completed claim form for your records.
Once the claim has been processed, you'll receive an Explanation of Benefits (EOB). The EOB will explain the charges applied to your deductible (the amount you pay for covered services before your plan begins to pay) and any charges you owe your health care professional. Please keep your EOB on file in case you need it in the future.
Common questions about Medical Claim Form (SCF0515)
Is there a deadline?
Get your claim in by December 31st of the year after the year you received the service.
Where do I file it?
Mail Claim Form To: Cigna P. O. Box 188007 Chattanooga, TN 37422
Is there a penalty?
Any person who knowingly and with intent to defraud, injure, or deceive any insurance company, submits a claim or application containing any materially false, deceptive, incomplete or misleading information pertaining to such claim may be committing a fraudulent insurance act which is a crime and may subject such person to criminal or civil penalties, including fines, denial of benefits, and/or imprisonment.
Sources
[1] Medical Claim Form (SCF0515), SAMBA (the Official source link on this page).
