

SIB Form D at a glance
What it is: Intent: any pre-existing medical condition or disability which may entitle your employer to reimbursement from the Second Injury Board. This reimbursement in no way affects the benefits owed to you. La. R.S. 23:1021-1361.
Who signs: SIGN: Employee Signature and Date. SIGN: Employer Representative Signature and Date.
A filled-in SIB Form D example: an employee completes page one

How to fill out SIB Form D, box by box
Employer Name, Employee Name, Home Address and Telephone Number
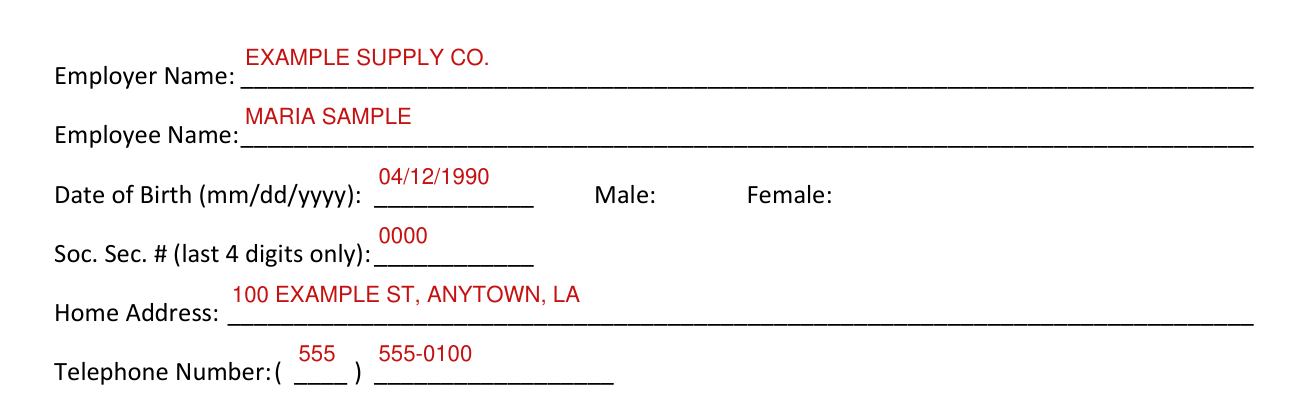
Enter the Employer Name and the Employee Name.
Enter the Date of Birth (mm/dd/yyyy), mark Male or Female, and enter the Soc. Sec. # (last 4 digits only).
Enter the Home Address and the Telephone Number.
Signatures and dates

SIGN: Employee Signature and Date. SIGN: Employer Representative Signature and Date.
Surgical Treatment
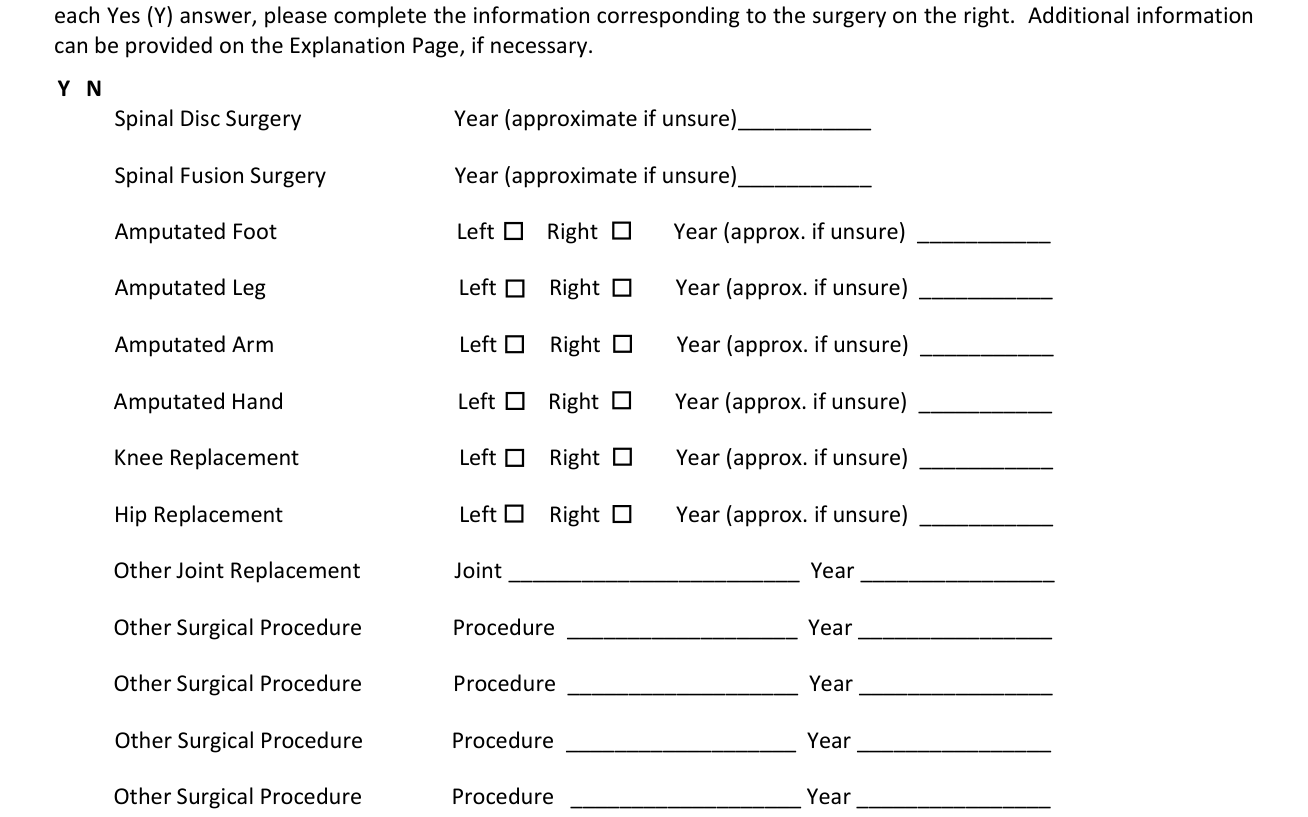
Under Surgical Treatment, check the appropriate box; each illness/injury requires a Yes (Y) or No (N) answer.
For each Yes (Y) answer, complete the information corresponding to the surgery on the right. Additional information can be provided on the Explanation Page, if necessary.
For Spinal Disc Surgery and Spinal Fusion Surgery, enter the Year (approximate if unsure).
For Amputated Foot, Amputated Leg, Amputated Arm, Amputated Hand, Knee Replacement and Hip Replacement, mark Left or Right and enter the Year (approx. if unsure).
For Other Joint Replacement, enter the Joint and the Year.
For each Other Surgical Procedure, enter the Procedure and the Year.
Explanation Page
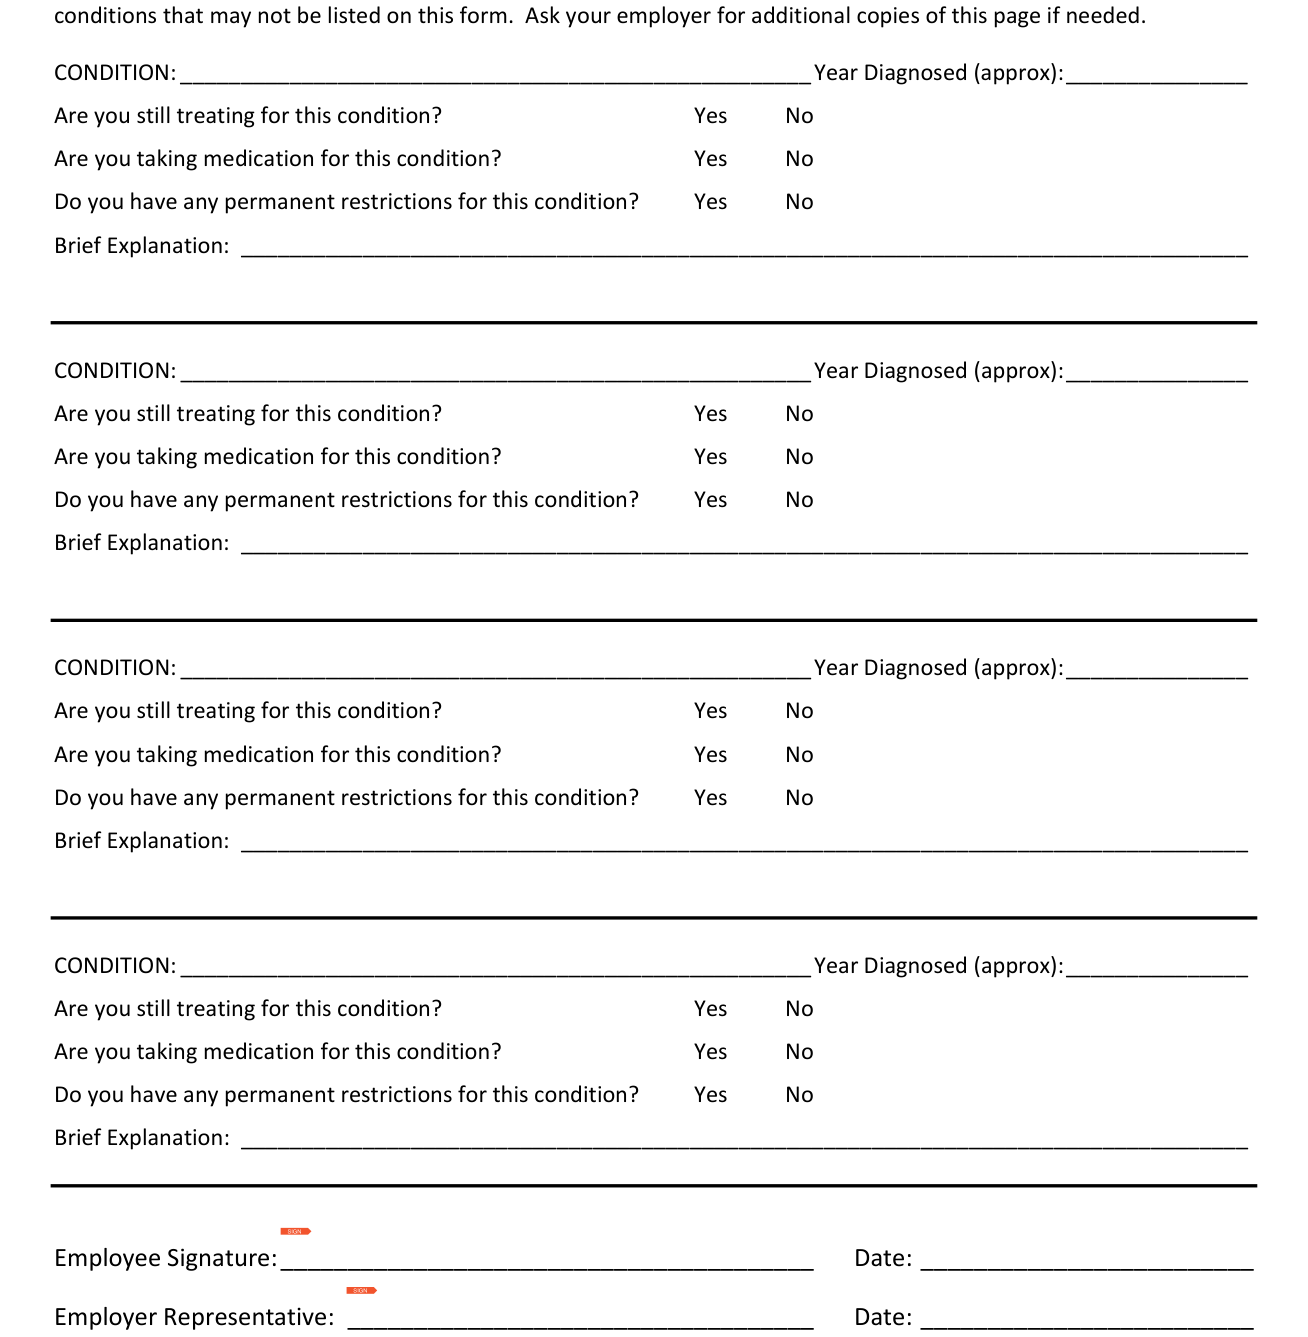
Use the space on the Explanation Page to explain the illnesses and/or conditions that you checked a Yes (Y) or any other medical conditions that may not be listed on this form. Ask your employer for additional copies of the Explanation Page if needed.
Enter the CONDITION and Year Diagnosed (approx), mark Yes or No for Are you still treating for this condition?, Are you taking medication for this condition? and Do you have any permanent restrictions for this condition?, and enter a Brief Explanation.
Please answer the following questions

Please answer the following questions. 1. Has any doctor ever restricted your activities? Yes No If "Yes," please list the restrictions. Were the restrictions: Permanent Temporary Are your activities currently restricted? Yes No What is the medical condition for which you have restrictions?
2. Are you presently treating with a doctor, chiropractor, psychiatrist, psychologist or other health-care provider? Yes or No. Enter the medical condition being treated, the Doctor's Name, the Specialty and the Doctor's Address.
3. If you are currently taking prescription medication other than those listed on the Explanation Page, complete the requested information: the Medication and the Prescribing Doctor.
4. Have you ever had an on the job accident? Yes or No. If you answered YES, provide the date for each injury and the nature of the injury, How long were you on compensation, and the Name of Employer.
5. Has a doctor recommended a surgical procedure, which has not been completed prior to this date, including but not limited to knee, hip or shoulder replacement? Yes or No. If you answered YES, provide the Recommended surgery, the Approximate date of recommendation, the Doctor's Name, the Specialty and the Doctor's Address.
To be completed by employee

To be completed by employee. Employee warning: failure to answer truthfully and/or correctly to any of the questions on this form may result in a forfeiture of any and all workers compensation benefits under La. R.S. 23:1208.1. I have completed this form honestly and to the best of my knowledge. I understand that providing false information or omitting pertinent information could result in loss of my workers compensation benefits should I become injured on the job.
SIGN: Employee Signature and Date, and the Employee Printed Name.
To be completed by employer representative

To be completed by employer representative. Employer warning pursuant to La. R.S. 23:1208 of the Louisiana Workers' Compensation Act: it shall be unlawful for a person, for the purpose of obtaining or defeating any benefit payment under the provisions of this chapter, either for himself or for any other person, to willfully make a false statement or representation. Penalties for violations include imprisonment, fines, and/or the forfeiture of benefits.
The employer representative must certify the following: 1. That I am an authorized representative of the employer designated to obtain and review the information provided by the employee on this questionnaire; 2. That I have provided the employee with as many copies of the Explanation Page as needed and have confirmed the number of and labeled the pages of this questionnaire; 3. That I have provided assistance to the employee (if requested) in responding to the questions on this questionnaire; 4.
That the information sought by this authorization is made on an applicant for employment only after a conditional job offer has been made and accepted, or on a current employee; and 5.
That the information obtained in the authorization will NOT be used to discriminate in any manner against the individual who is the subject of this authorization on any basis, in violation of the Americans with Disabilities Act of 1990, 42 U.S.C. §12101, et seq., or any other state or federal law; 6. That if requested, a photocopy of this fully completed and signed form will be provided to the employee.
SIGN: Employer Representative Signature and Date, the Employer Representative Printed Name and the Title.
More rules for SIB Form D
In order for your employer to be considered for reimbursement from the Second Injury Board, it has to show that it knowingly hired or retained you with a pre-existing medical condition or disability.
Answer ALL questions completely. If a response requires an explanation, provide a brief description on the Explanation Page. If you have any questions or need help in answering the questions on this form, ask for assistance from the Employer Representative signing this form.
Since this questionnaire contains medical information, you can request that the form be kept CONFIDENTIAL and not made part of your personnel file. Let your employer know that you want the completed questionnaire placed in a sealed folder for confidentiality purposes.
Failure to answer truthfully and/or correctly to any of the questions on this form may result in a forfeiture of your workers' compensation benefits under La. R.S. 23:1208.1.
List the Disease and Other Medical Conditions you currently have or have ever had. Check the appropriate box next to each; every illness/injury requires a Yes (Y) or No (N) answer. For all conditions that you check yes, write a brief explanation on the Explanation Page.
Diabetes Cerebral Palsy Arthritis Heart Disease/Heart Attack Silicosis Tuberculosis Parkinson's Congestive Heart Failure Varicose Veins Multiple Sclerosis Brain Damage Vision Loss, one or both eyes Asbestosis Post Traumatic Stress Asthma Disability from Polio Hyperinsulinism Osteomyelitis Dementia Psychoneurotic Disability Alzheimer's Nervous Disorder Thrombophlebitis Ruptured or Herniated Disc Emphysema Muscular Dystrophy Arteriosclerosis Ankylosis or Joint Stiffening Hearing Loss Migraine Headaches Hodgkin's High/Low Blood Pressure COPD Mental Retardation Cancer Carpal Tunnel Syndrome Hypertension Kidney Disorder Double Vision Compressed Air Sequelae Head Injury Loss of Use of Limb Mental Disorders Disease of the Lung Epilepsy Seizure Disorder Hemophilia Coronary Artery Disease Stroke Sickle Cell Disease Bleeding Disorder Heavy Metal Poisoning.
SIGN: Employee Signature and Date. SIGN: Employer Representative and Date.
Sources
[1] SIB Form D (10/17), Post-Hire/Conditional Job Offer Knowledge Questionnaire, Louisiana Workers' Compensation Second Injury Board (the Official source link on this page).
