


Form SOC 426A at a glance
What it is: SOC 426A is the IHSS Program Recipient Designation of Provider: you choose the person listed to be your IHSS provider for some or all of the services authorized by the county.
Who signs: You must sign the acknowledgement in PART C of this form.
You (or your authorized representative) must complete PART A of this form to let the county know who you have chosen to provide your authorized services.
A filled-in Form SOC 426A example: a recipient names her father as provider

How to fill out Form SOC 426A, box by box
Recipient's Name and County IHSS Case #

Enter the Recipient's Name and the County IHSS Case #.
Provider's Name, Address and Telephone Number

Enter the Provider's Name, the Provider's Address, City, State, ZIP Code and the Provider's Telephone Number.
Provider's Date of Birth and Social Security #

Enter the Provider's Date of Birth and the Provider's Social Security #*.
In PART A, for the * after the Provider's Social Security #: the collection of the Social Security Number is required by the Immigration Reform and Control Act of 1986, Public Law 99-603 (8 USC 1324a), for the purposes of verifying the individual's identity and authorization to work in the United States.
Provider's Gender

Check the box for the Provider's Gender: Male or Female.
Provider's Relationship to Recipient (if any)

Provider's Relationship to Recipient (if any): check Parent, Child, Spouse/Domestic Partner, Conservator, Guardian or Other, and write the relationship on the line after Other.
Provider's Start Date

Enter the Provider's Start Date.
PART C. RECIPIENT ACKNOWLEDGMENT
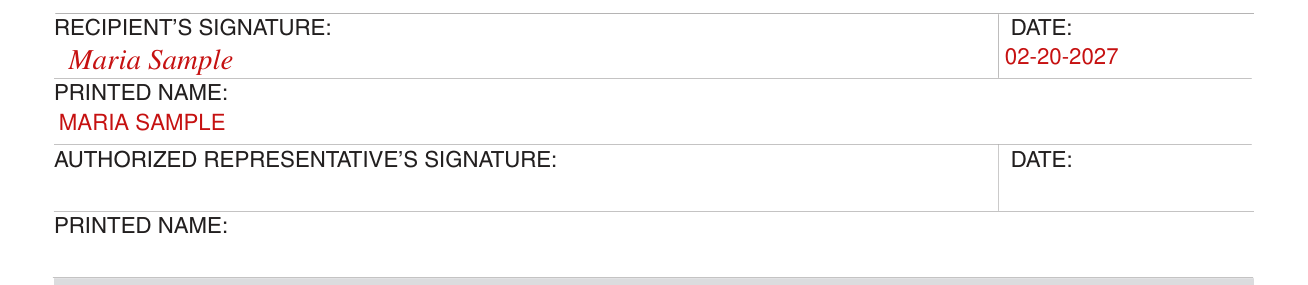
PART C. RECIPIENT ACKNOWLEDGMENT: I understand and agree to follow all of the requirements listed in this form.
Sign as the recipient, add the DATE and write the PRINTED NAME.
AUTHORIZED REPRESENTATIVE'S SIGNATURE, DATE and PRINTED NAME.
FOR COUNTY USE ONLY

FOR COUNTY USE ONLY: WORKER NAME and DATE.
More rules for Form SOC 426A
Use black or blue ink. Print information clearly.
If you have multiple providers, you must fill out a separate form for each person who will be providing authorized services for you.
Neither the county nor the State will be held responsible for any claims and/or losses caused by the person you choose to hire as your IHSS provider. You agree to hold harmless the State and county, their officers, agents, and employees, and to take responsibility for any and all claims and/or losses to any person caused by the named person you choose to hire as your IHSS provider.
The county can provide information about your authorized services and service hours to the person you have chosen as your provider. The county will send your provider the IHSS Provider Notice of Recipient Authorized Hours and Services (SOC 2271).
Your total monthly authorized hours will be divided by 4 to determine your maximum weekly hours. The maximum weekly hours is a guideline telling you the highest number of hours your provider(s) will be able to work for you during a workweek. However, since most months are slightly longer than 4 weeks, you will work with your provider(s) to spread his/her hours throughout the month in order to make sure you have all the service hours you need for the month.
If your situation is different
Your provider is not yet enrolled
The person you have chosen to be your provider cannot be paid federal and/or state money for providing services to you until he/she completes all of the provider enrollment requirements. These requirements include completing, signing, and returning (in person) the Provider Enrollment Form (SOC 426), submitting fingerprints and being cleared of disqualifying crimes through a criminal background check, completing a provider orientation, and returning a signed Provider Enrollment Agreement (SOC 846).
The county will send you a notice telling you if the person you have chosen as your provider does not complete the provider enrollment requirements or if he/she is not eligible to be an IHSS provider.
If you choose to have this person provide services for you before he/she is enrolled as an IHSS provider, and the county sends you a notice telling you that he/she is not eligible to be an IHSS provider, you will have to pay him/her with your own money for the services that he/she provided before he/she was determined ineligible to be a provider and for any services he/she provides after the county notifies you that he/she is ineligible.
Your provider works more than your maximum weekly hours
Sometimes you may need your provider to work more than your maximum weekly hours. You must ask for county approval to adjust your maximum weekly hours only if the change requires your provider to work more overtime hours in the month than he/she would normally work, or more than 40 hours for you in a workweek if your maximum weekly hours are 40 hours or less in a workweek.
If you do not get an approved exception, your provider will get a violation for working more than your maximum weekly hours.
You can never authorize your provider to work more than your total authorized monthly service hours. Therefore, when you authorize your provider to work extra hours in one week, you must have the provider work fewer hours in the other week(s) of the month.
The county will send you a notice each time your provider gets a violation. If your provider gets three violations, he/she will be suspended from providing IHSS for three months. If he/she gets another violation after being reinstated from the three-month suspension, he/she will be terminated as a provider for one year.
Common questions about Form SOC 426A
Where do I file it?
Please return this completed and signed form to the county. The county will keep the original form and give you a copy.
Sources
[1] Form SOC 426A (1/16), IHSS Program Recipient Designation of Provider, California Department of Social Services (the Official source link on this page).