

Form SSA-16 at a glance
What it is: Form SSA-16 is the Social Security Administration application for disability insurance benefits.
Who signs: Signature of applicant: write your signature in ink (first name, middle initial, last name). Enter the date (month, day, year).
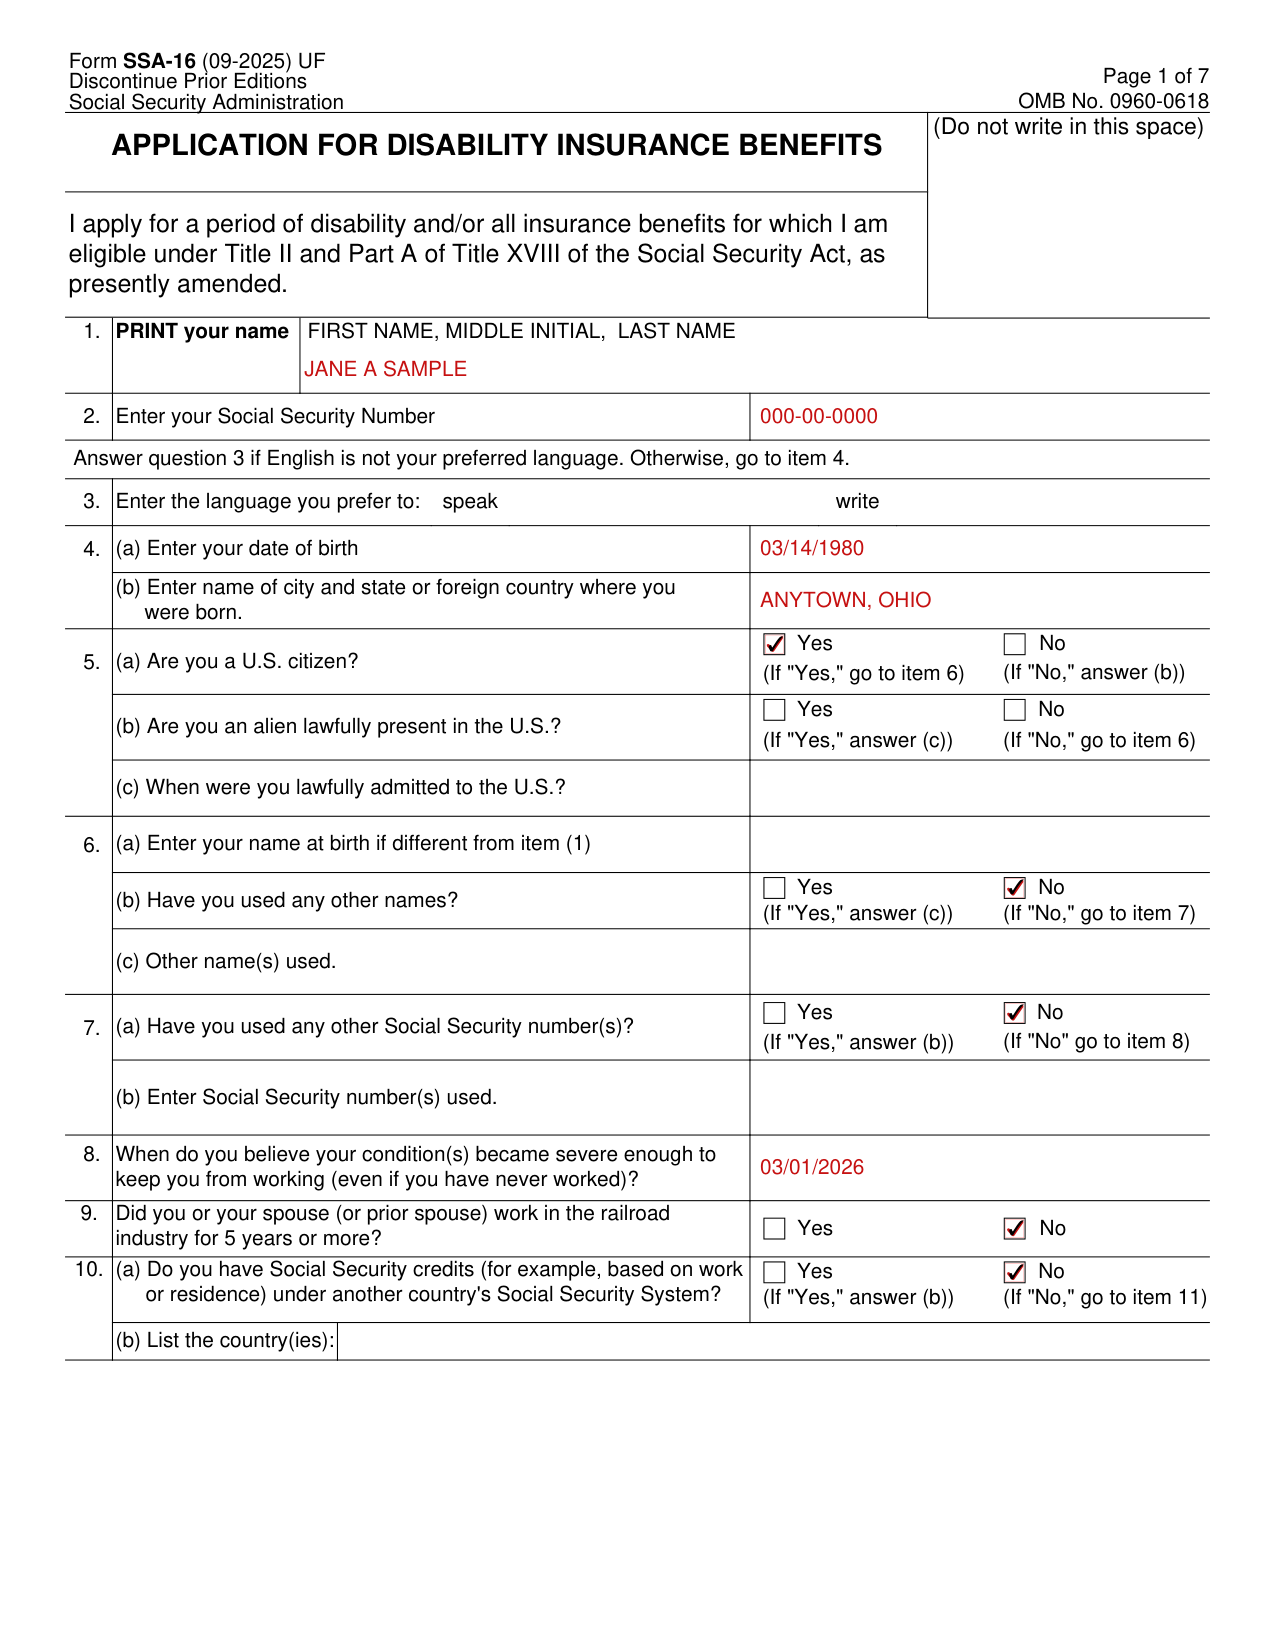
A filled-in Form SSA-16 example: an employee who stopped working applies
How to fill out Form SSA-16, box by box
Items 1 to 4, name, Social Security number, language and birth
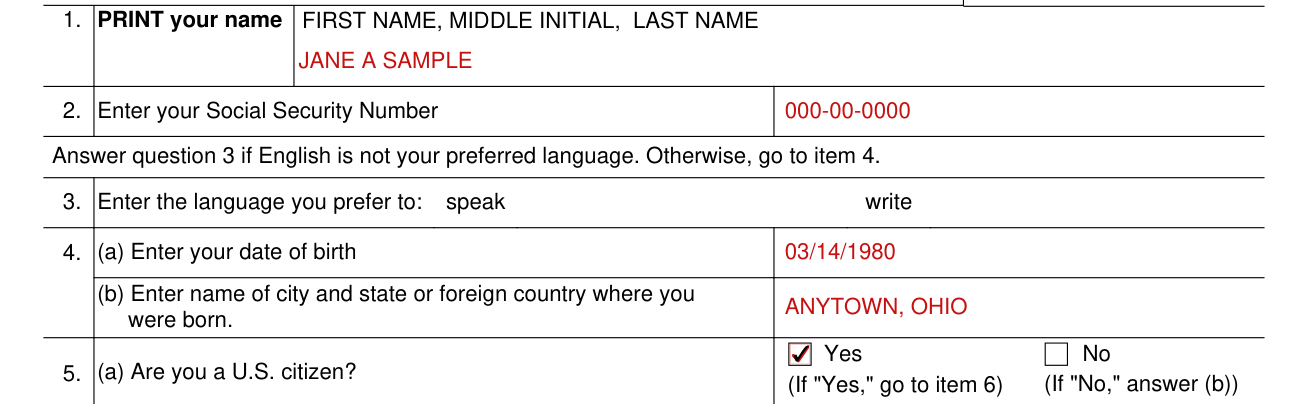
Print your name: first name, middle initial, last name. Enter your Social Security number.
Answer question 3 if English is not your preferred language. Otherwise, go to item 4. Enter the language you prefer to speak and the language you prefer to write.
Enter your date of birth. Enter the name of the city and state or foreign country where you were born.
Item 5, U.S. citizen or alien lawfully present

5(a). Are you a U.S. citizen? If "Yes," go to item 6. If "No," answer (b). 5(b). Are you an alien lawfully present in the U.S.? If "Yes," answer (c). If "No," go to item 6. 5(c). Enter when you were lawfully admitted to the U.S.
Items 6 to 8, other names, other numbers and your condition

6(a). Enter your name at birth if different from item 1. 6(b). Have you used any other names? If "Yes," answer (c). If "No," go to item 7. 6(c). Enter the other name(s) used.
7(a). Have you used any other Social Security number(s)? If "Yes," answer (b). If "No" go to item 8. 7(b). Enter Social Security number(s) used.
8. Enter when you believe your condition(s) became severe enough to keep you from working (even if you have never worked).
Items 9 and 10, railroad work and credits from another country

9. Did you or your spouse (or prior spouse) work in the railroad industry for 5 years or more? Check Yes or No.
10(a). Do you have Social Security credits (for example, based on work or residence) under another country's Social Security System? If "Yes," answer (b). If "No," go to item 11. 10(b). List the country(ies).
Item 11, your marriage

11(a). Have you ever been married? If "Yes," answer (b). If "No," go to item 12. 11(b). Give information about your current marriage: spouse's name (including maiden name), when (month, day, year), where (name of city and state). If not currently married, write "None." If "None," go on to item 11(c).
Also enter the spouse's date of birth (or age), the spouse's Social Security Number (if none or unknown, so indicate), and who performed the marriage: clergyman or public official, or other (explain in Remarks).
Use the "Remarks" space on page 5 for marriage continuation or explanation.
Your children

12. If your claim for disability benefits is approved, your children (including adopted children, and stepchildren) or dependent grandchildren (including stepgrandchildren) may be eligible for benefits based on your earnings record. List full name of all such children who are now or were in the past 12 months unmarried and: under age 18; age 18 to 19 and attending elementary or secondary school full-time; disabled or handicapped (age 18 or over and disability began before age 22).
Items 13 and 14, covered income and employers
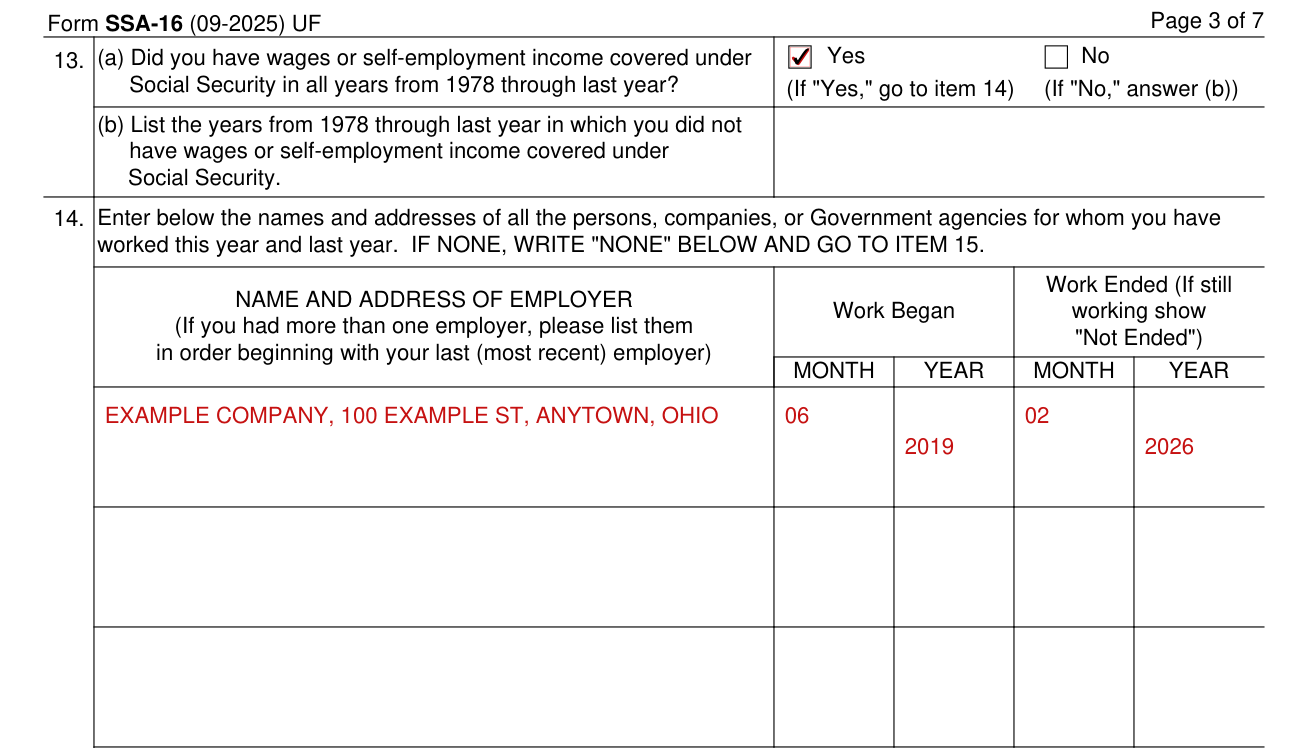
13(a). Did you have wages or self-employment income covered under Social Security in all years from 1978 through last year? If "Yes," go to item 14. If "No," answer (b). 13(b). List the years from 1978 through last year in which you did not have wages or self-employment income covered under Social Security.
14. Enter in item 14 the names and addresses of all the persons, companies, or Government agencies for whom you have worked this year and last year. If none, write "None" in item 14 and go to item 15. Enter the name and address of employer (if you had more than one employer, please list them in order beginning with your last (most recent) employer), the month and year work began, and the month and year work ended (if still working show "Not Ended"). If you need more space, use "Remarks".
Items 15 and 16, self-employment and earnings
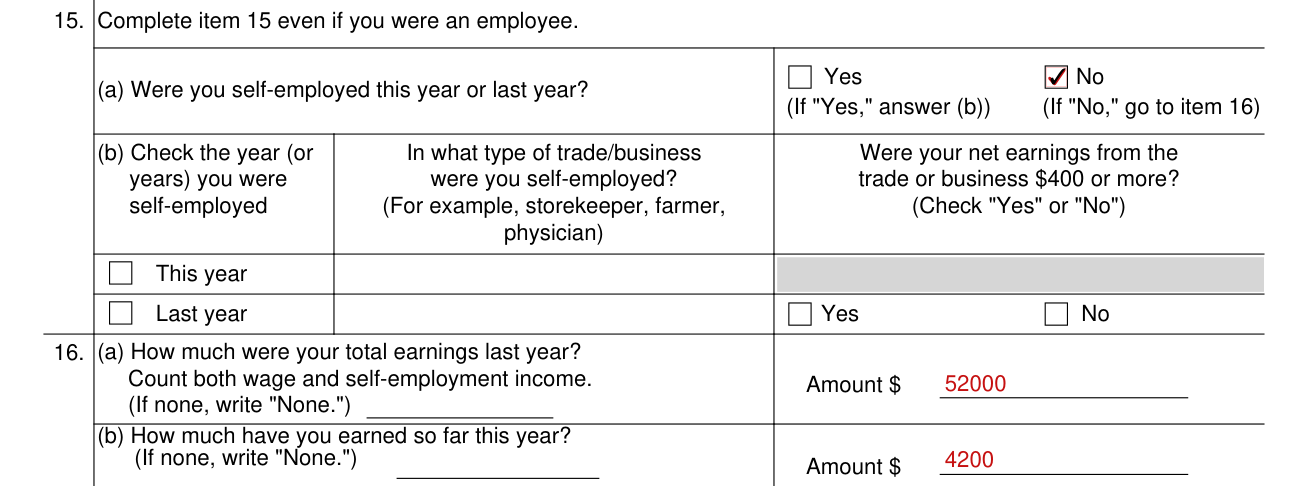
15. Complete item 15 even if you were an employee. 15(a). Were you self-employed this year or last year? If "Yes," answer (b). If "No," go to item 16. 15(b). Check the year (or years) you were self-employed. Check "Yes" or "No": were your net earnings from the trade or business $400 or more? (checked October 19, 2026)
16(a). How much were your total earnings last year? Count both wage and self-employment income. If none, write "None." 16(b). How much have you earned so far this year? If none, write "None."
Items 17 to 19, your illnesses, injuries or conditions
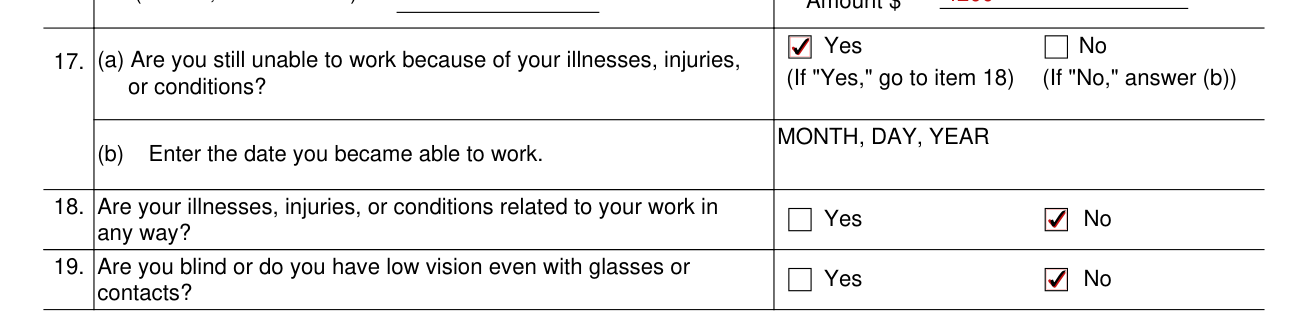
17(a). Are you still unable to work because of your illnesses, injuries, or conditions? If "Yes," go to item 18. If "No," answer (b). 17(b). Enter the date you became able to work (month, day, year).
18. Are your illnesses, injuries, or conditions related to your work in any way? Check Yes or No. 19. Are you blind or do you have low vision even with glasses or contacts? Check Yes or No.
Item 20, other public disability benefits
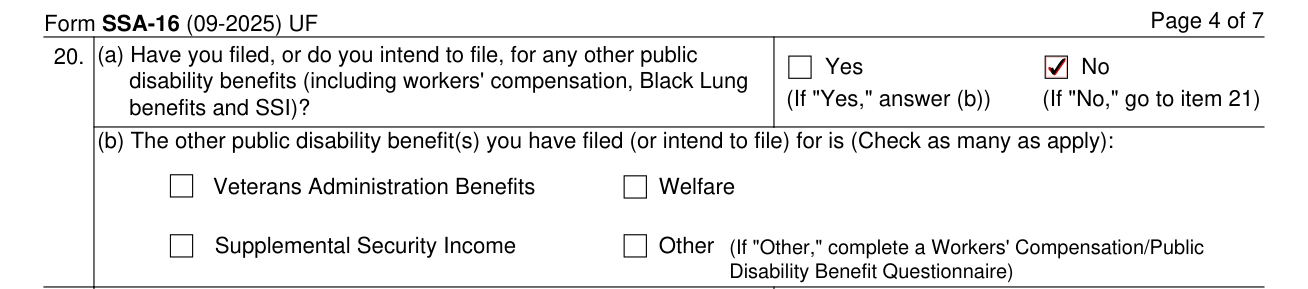
20(a). Have you filed, or do you intend to file, for any other public disability benefits (including workers' compensation, Black Lung benefits and SSI)? If "Yes," answer (b). If "No," go to item 21. 20(b). The other public disability benefit(s) you have filed (or intend to file) for is (check as many as apply): Veterans Administration Benefits, Welfare, Supplemental Security Income, or Other (if "Other," complete a Workers' Compensation/Public Disability Benefit Questionnaire).
Items 21 and 22, money from an employer and a child

21(a). Did you receive any money from an employer(s) on or after the date in item 8 when you became unable to work because of your illnesses, injuries, or conditions? If "Yes", give the amounts and explain in "Remarks". 21(b). Do you expect to receive any additional money from an employer, such as sick pay, vacation pay, other special pay? If "Yes," please give amounts and explain in "Remarks". Check Yes or No for each.
22. Do you, or did you, have a child under age 3 (your own or your spouse's) living with you in one or more calendar years when you had no earnings? Check Yes or No.
Remarks
Remarks: you may use this space for any explanation. If you need more space, attach a separate sheet.
Signature, date and telephone number

You declare under penalty of perjury that you have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of your knowledge.
Signature of applicant: write your signature in ink (first name, middle initial, last name). Enter the date (month, day, year).
Enter the telephone number(s) at which you may be contacted during the day (include the area code).
Direct deposit and mailing address
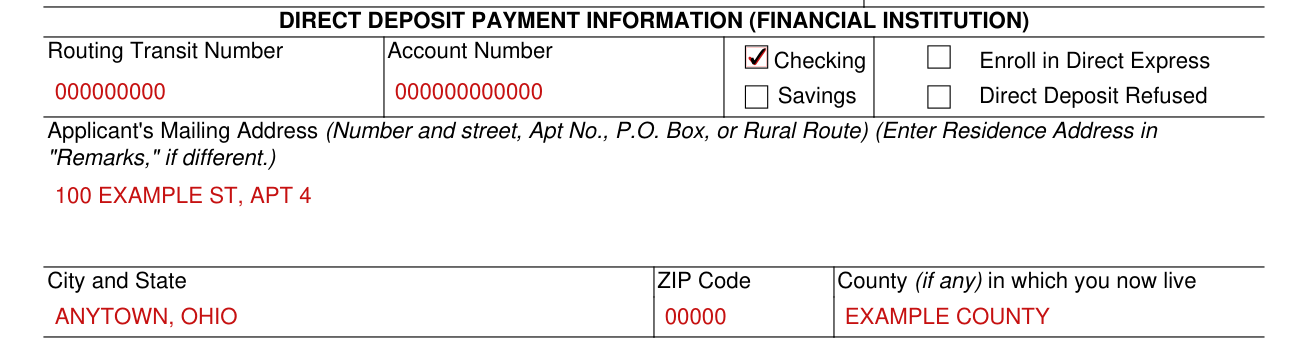
Direct deposit payment information (financial institution): enter the routing transit number and the account number. The boxes are Checking, Savings, Enroll in Direct Express and Direct Deposit Refused.
Enter the applicant's mailing address (number and street, Apt No., P.O. Box, or Rural Route). Enter residence address in "Remarks," if different. Enter the city and state, ZIP code and county (if any) in which you now live.
More rules for Form SSA-16
Failing to provide all or part of the information may prevent an accurate and timely decision on the claim for benefits.
Common questions about Form SSA-16
What is form SSA 16 used for?
Form SSA-16 is the Social Security Administration application for disability insurance benefits. With this form you apply for a period of disability and/or all insurance benefits for which you are eligible under Title II and Part A of Title XVIII of the Social Security Act, as presently amended.
Where do I file it?
Send or bring the completed form to your local Social Security office. You can find your local Social Security office through SSA's website at www.socialsecurity.gov. Offices are also listed under U.S. Government agencies in your telephone directory, or you may call Social Security at 1-800-772-1213 (TTY 1-800-325-0778).
Is there a penalty?
You understand that anyone who knowingly gives a false statement about a material fact in this information, or causes someone else to do so, commits a crime and may be subject to a fine or imprisonment.
Sources
[1] Form SSA-16 (09-2025), Application for Disability Insurance Benefits, Social Security Administration (the Official source link on this page).