

Form SSA-2490-BK at a glance
What it is: Form SSA-2490-BK (04-2025) from the Social Security Administration is the Application for Benefits Under a U.S. International Social Security Agreement.
Who signs: Under SIGNATURE OF APPLICANT, write the Signature (First name, middle initial, last name) in ink.
If the worker is living, this application should be completed by or on behalf of the worker. If the worker is deceased, this application should be completed by one of the worker's survivors who is claiming benefits under the provisions of the international social security agreement.
A filled-in Form SSA-2490-BK example: a worker claims Canadian and U.S. retirement benefits

How to fill out Form SSA-2490-BK, box by box
Part 1: name of worker and foreign social security coverage
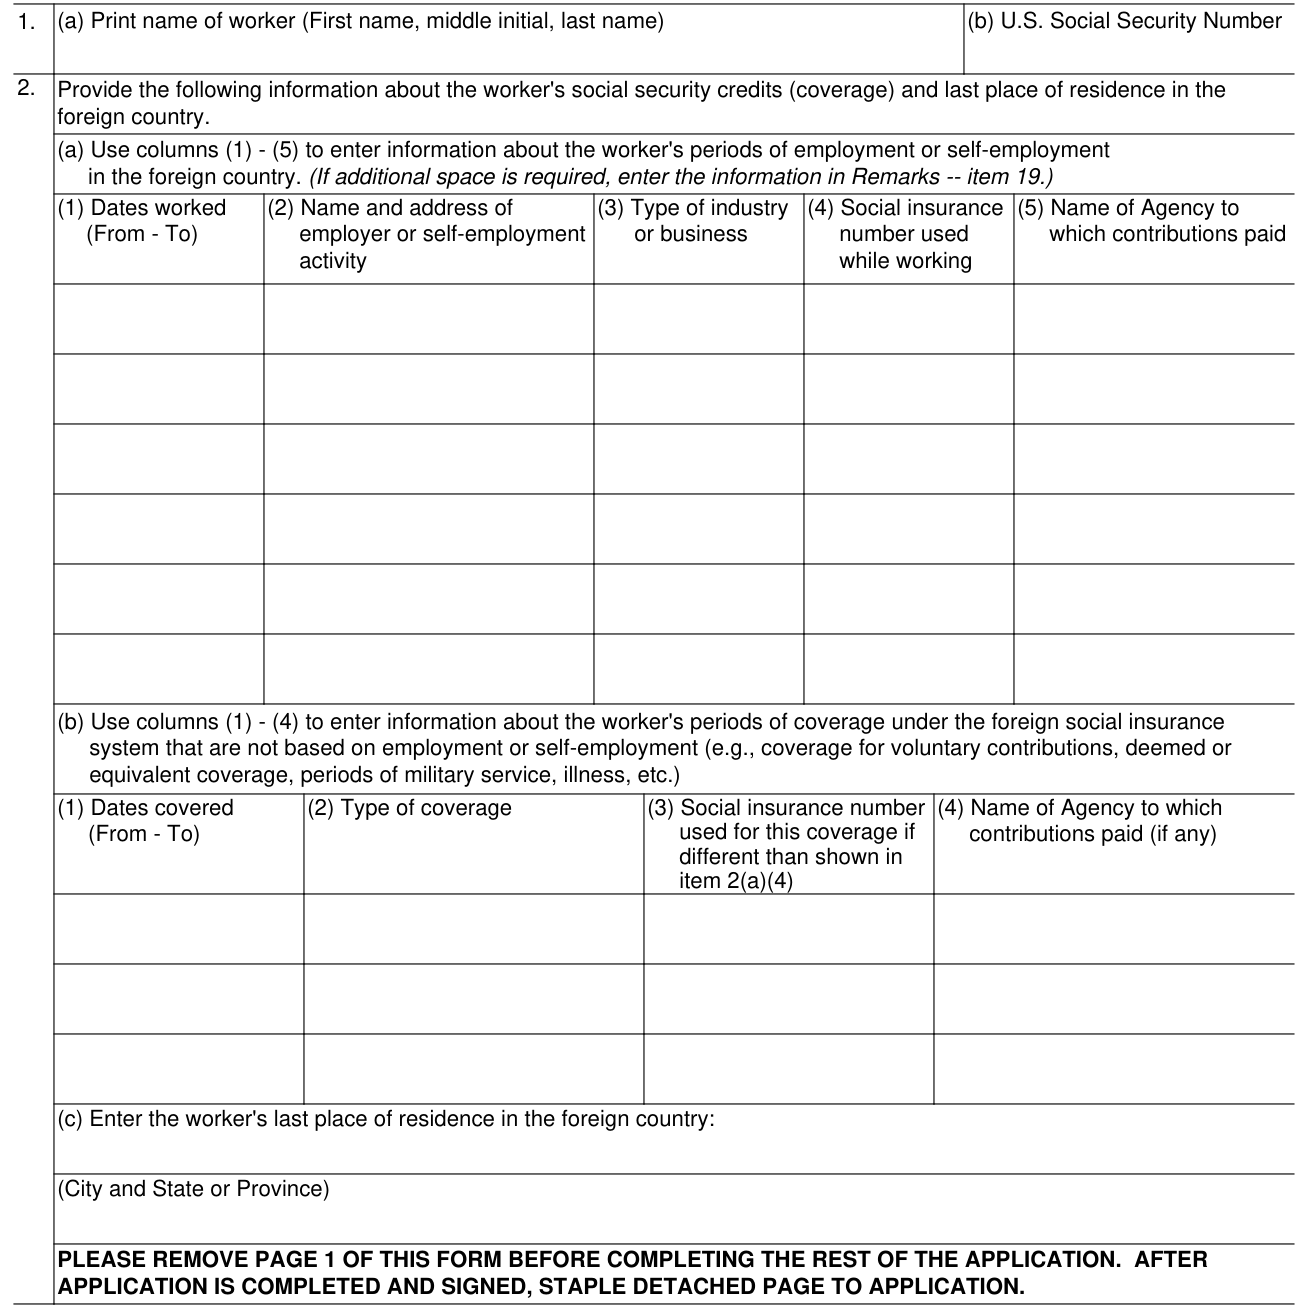
Complete Part 1 in all cases. Print name of worker (First name, middle initial, last name) and U.S. Social Security Number.
(a) Use columns (1) - (5) to enter information about the worker's periods of employment or self-employment in the foreign country: (1) Dates worked (From - To), (2) Name and address of employer or self-employment activity, (3) Type of industry or business, (4) Social insurance number used while working, (5) Name of Agency to which contributions paid. If additional space is required, enter the information in Remarks item 19.
(b) Use columns (1) - (4) to enter information about the worker's periods of coverage under the foreign social insurance system that are not based on employment or self-employment (e.g., coverage for voluntary contributions, deemed or equivalent coverage, periods of military service, illness, etc.): (1) Dates covered (From - To).
(2) Type of coverage, (3) Social insurance number used for this coverage if different than shown in item 2(a)(4), (4) Name of Agency to which contributions paid (if any).
(c) Enter the worker's last place of residence in the foreign country: (City and State or Province).
Remove page 1 of this form before completing the rest of the application. After the application is completed and signed, staple the detached page to the application.
Benefit claimed from the foreign country and from the United States
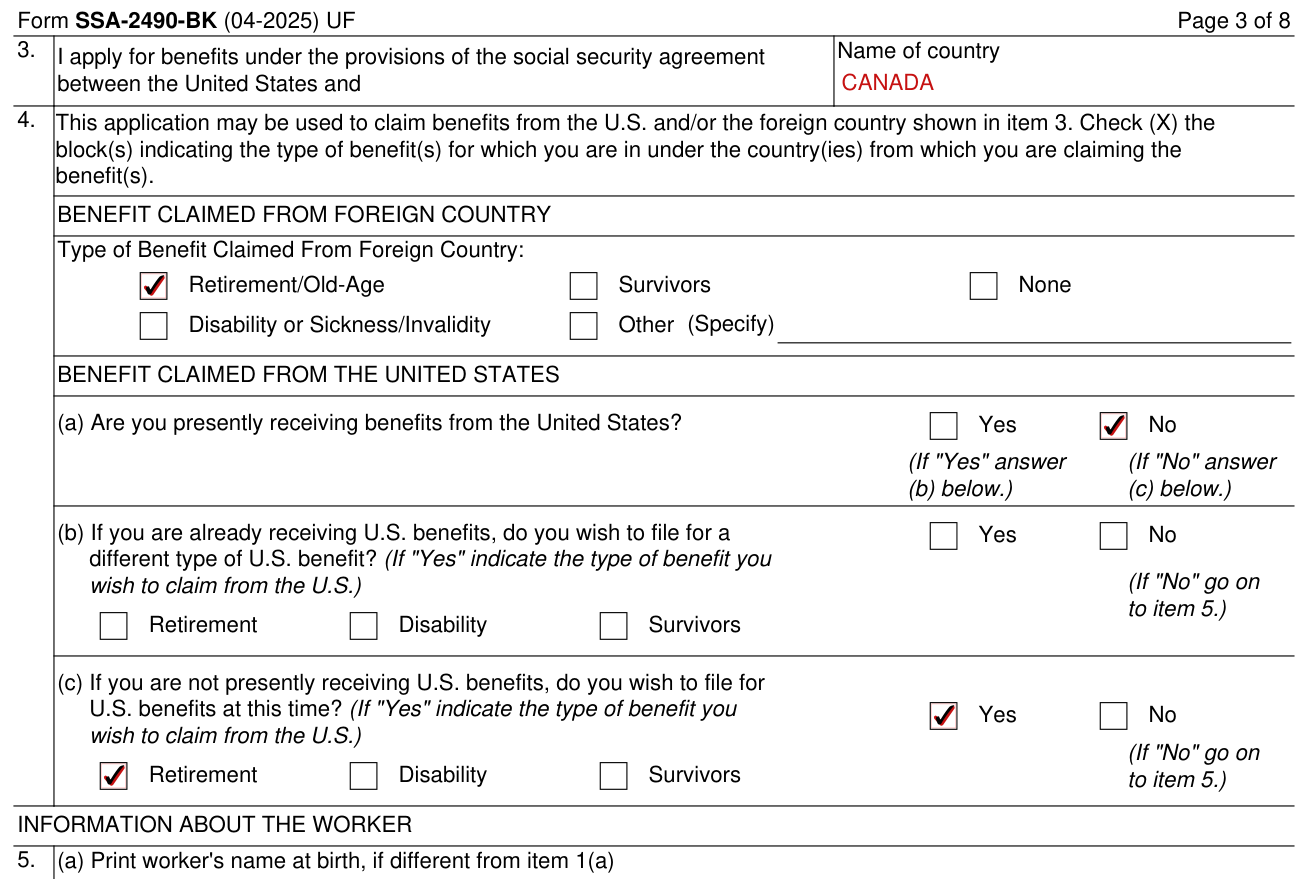
3. I apply for benefits under the provisions of the social security agreement between the United States and the country you write under Name of country.
This application may be used to claim benefits from the U.S. and/or the foreign country shown in item 3.
Under BENEFIT CLAIMED FROM FOREIGN COUNTRY, check (X) the block(s) indicating the type of benefit(s) you are claiming from the foreign country: Retirement/Old-Age, Survivors, None, Disability or Sickness/Invalidity, Other (Specify).
Under BENEFIT CLAIMED FROM THE UNITED STATES: (a) Are you presently receiving benefits from the United States? Yes or No. If "Yes" answer (b). If "No" answer (c).
(b) If you are already receiving U.S. benefits, do you wish to file for a different type of U.S. benefit? If "Yes" indicate the type of benefit you wish to claim from the U.S.: Retirement, Disability or Survivors. If "No" go on to item 5.
(c) If you are not presently receiving U.S. benefits, do you wish to file for U.S. benefits at this time? If "Yes" indicate the type of benefit. If "No" go on to item 5.
Information about the worker
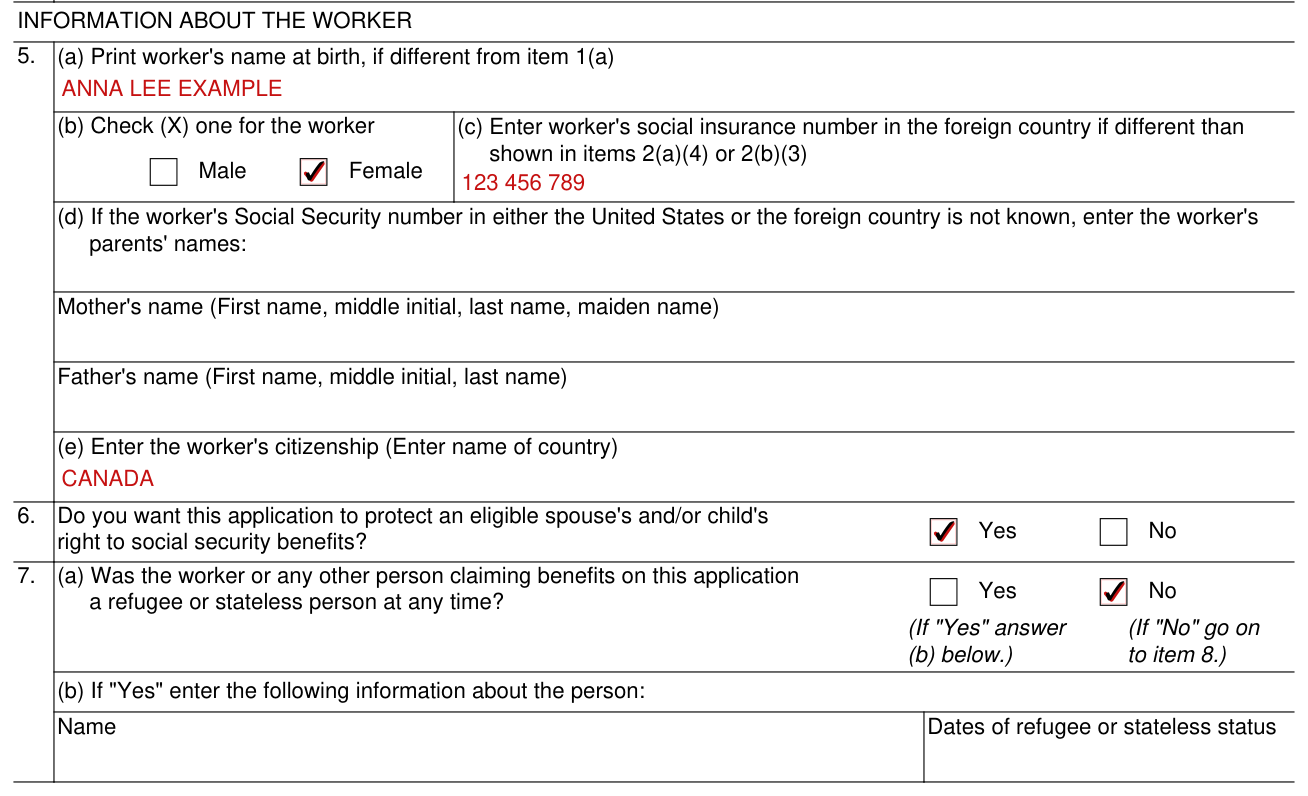
Under INFORMATION ABOUT THE WORKER: (a) Print worker's name at birth, if different from item 1(a). (b) Check (X) one for the worker: Male or Female.
Enter worker's social insurance number in the foreign country if different than shown in items 2(a)(4) or 2(b)(3).
(d) If the worker's Social Security number in either the United States or the foreign country is not known, enter the worker's parents' names: Mother's name (First name, middle initial, last name, maiden name) and Father's name (First name, middle initial, last name).
(e) Enter the worker's citizenship (Enter name of country).
Do you want this application to protect an eligible spouse's and/or child's right to social security benefits? Yes or No.
(a) Was the worker or any other person claiming benefits on this application a refugee or stateless person at any time? If "Yes" answer (b). If "No" go on to item 8.
(b) If "Yes" enter information about the person: Name, Dates of refugee or stateless status.
Part 2: benefits from a foreign country

Complete Part 2 ONLY if you are claiming benefits from a foreign country.
If you are applying for sickness or disability/invalidity benefits, enter the date you became disabled (MM/DD/YYYY). Otherwise enter 'N/A.'
(a) If you are applying for retirement/old-age benefits, have you stopped or do you plan to stop working? If "Yes" answer (b). If "No" go on to item 10. (b) If "Yes," enter the date you stopped or plan to stop working.
(a) Are you applying for foreign social security benefits under a special system that covers a specific occupation (e.g., miners, seamen, farmers)? If "Yes" answer (b) and (c). If "No" go on to item 11. (b) What was your occupation in the foreign country? (c) Did you perform the same type of work in the U.S?
Employment covered by the U.S. Social Security system in the past 24 months
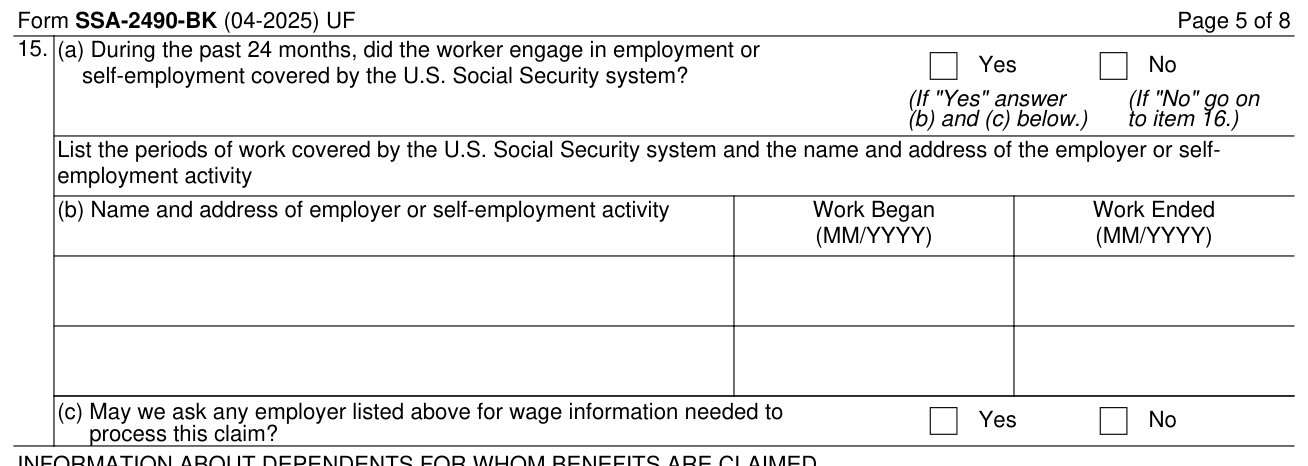
(a) During the past 24 months, did the worker engage in employment or self-employment covered by the U.S. Social Security system? If "Yes" answer (b) and (c). If "No" go on to item 16. (b) List the periods of work covered by the U.S. Social Security system and the name and address of the employer or self-employment activity.
Information about dependents for whom benefits are claimed
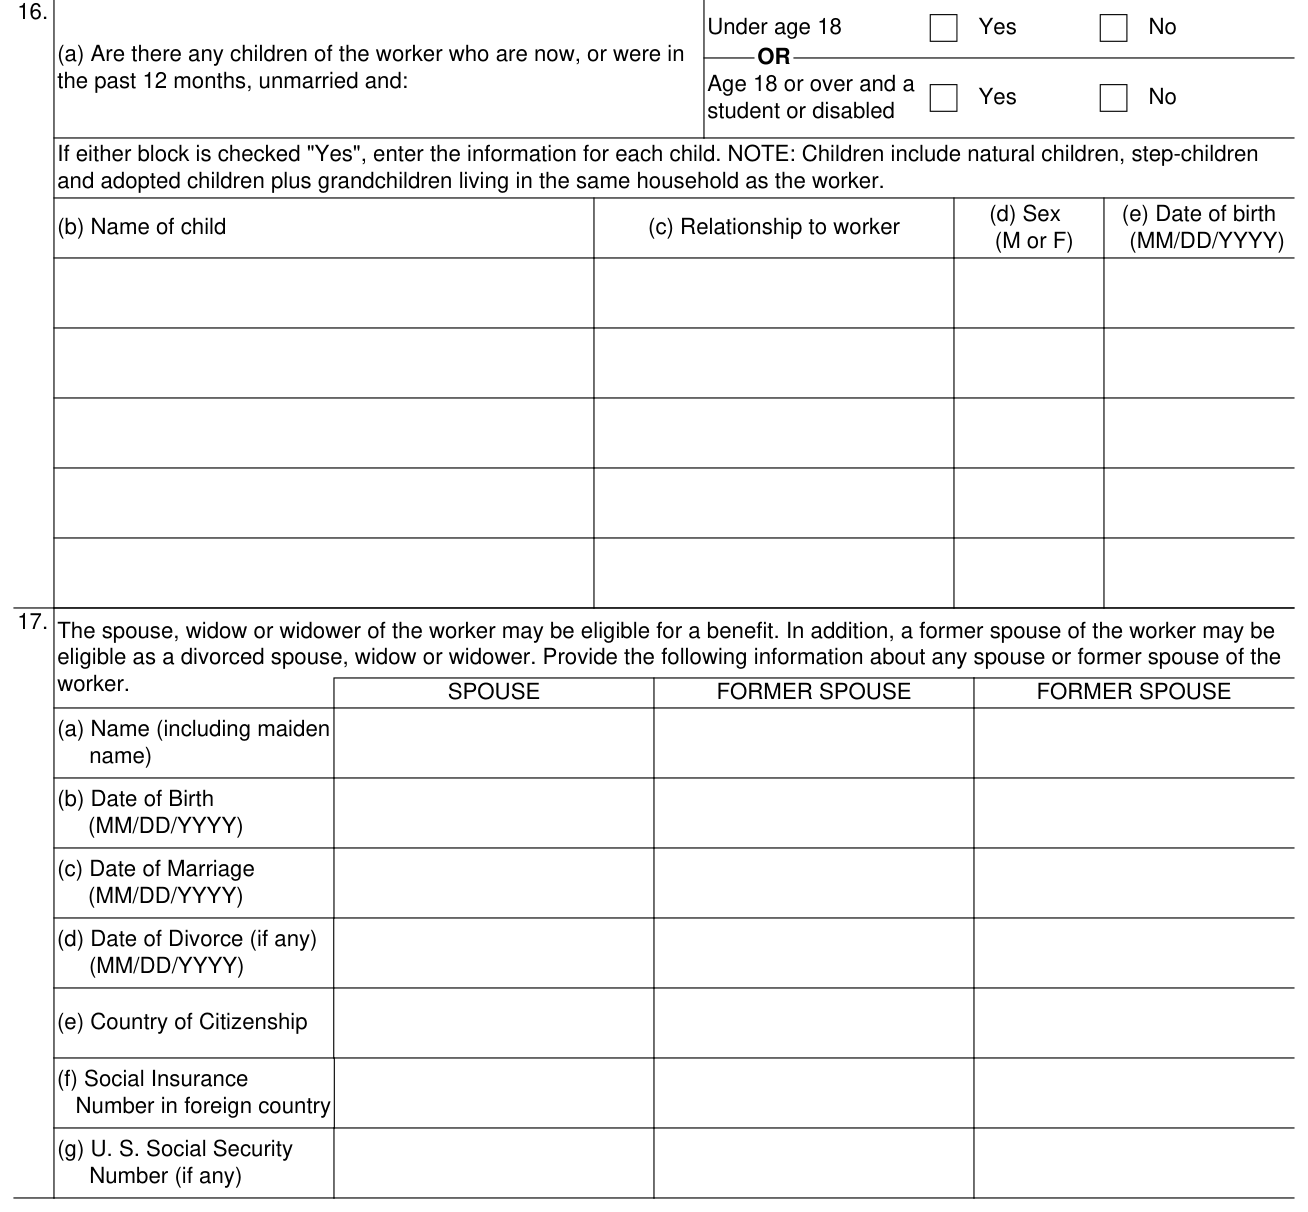
Information about dependents for whom benefits are claimed: (a) Are there any children of the worker who are now, or were in the past 12 months, unmarried and: Under age 18 Yes No OR Age 18 or over and a student or disabled Yes No? If either block is checked "Yes", enter the information for each child. NOTE: Children include natural children, step-children and adopted children plus grandchildren living in the same household as the worker.
The spouse, widow or widower of the worker may be eligible for a benefit. In addition, a former spouse of the worker may be eligible as a divorced spouse, widow or widower. Provide information about any spouse or former spouse of the worker.
More rules for Form SSA-2490-BK
Under ADDITIONAL INFORMATION ABOUT THE WORKER: (a) Enter worker's date of birth (MM/DD/YYYY). (b) Enter worker's place of birth (City, state, province, country).
(a) Has the worker, or any other person listed on this application, ever previously applied for U.S. Social Security benefits or social insurance benefits from the country shown in item 3 of this application? If "No" go on to item 19. If "Yes" enter the information requested for each person.
REMARKS (You may use this space for any explanations. If you need more space, attach a separate sheet.)
Enter the Date (MM/DD/YYYY) and the telephone number(s) at which you may be contacted during the day (include Area Code).
The estimate is about 30 minutes to read the instructions, gather the facts, and answer the questions.
Other situations
You are not the worker
Under INFORMATION ABOUT THE APPLICANT, complete item 11 ONLY if you are not the worker. If you are the worker, leave this question blank and go on to item 12.
The application is signed by mark (X)
Witnesses are required ONLY if this application has been signed by mark (X). If signed by mark (X), two witnesses to the signing who know the applicant must sign in Signature of Witness, giving their full addresses (Number and street, City, State, and ZIP Code). Also, print the applicant's name in the Signature block.
Common questions about Form SSA-2490-BK
Who signs it?
Under SIGNATURE OF APPLICANT, write the Signature (First name, middle initial, last name) in ink.
Is there a penalty?
I understand that anyone who knowingly gives a false or misleading statement about a material fact in this information, or causes someone else to do so, commits a crime and may be sent to prison, or may face other penalties, or both.
What am I certifying when I sign?
"I declare under penalty of perjury that I have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of my knowledge."
Sources
[1] Form SSA-2490-BK (04-2025), Application for Benefits Under a U.S. International Social Security Agreement, Social Security Administration (the Official source link on this page).
