

Form SSA-4641 at a glance
What it is: Form SSA-4641 (10-2019) is the authorization for the Social Security Administration to obtain account records from a financial institution and request for records.
Who signs: Sign in CUSTOMER'S SIGNATURE/AUTHORIZATION, then enter the MAILING ADDRESS and the DATE. Sign in LEGAL REPRESENTATIVE'S SIGNATURE / AUTHORIZATION, then enter the LEGAL REPRESENTATIVE'S MAILING ADDRESS and the DATE.
A filled-in Form SSA-4641 example: a customer authorizes her bank to release records

How to fill out Form SSA-4641, box by box
Customer's name, Social Security number, financial institution and account number(s)
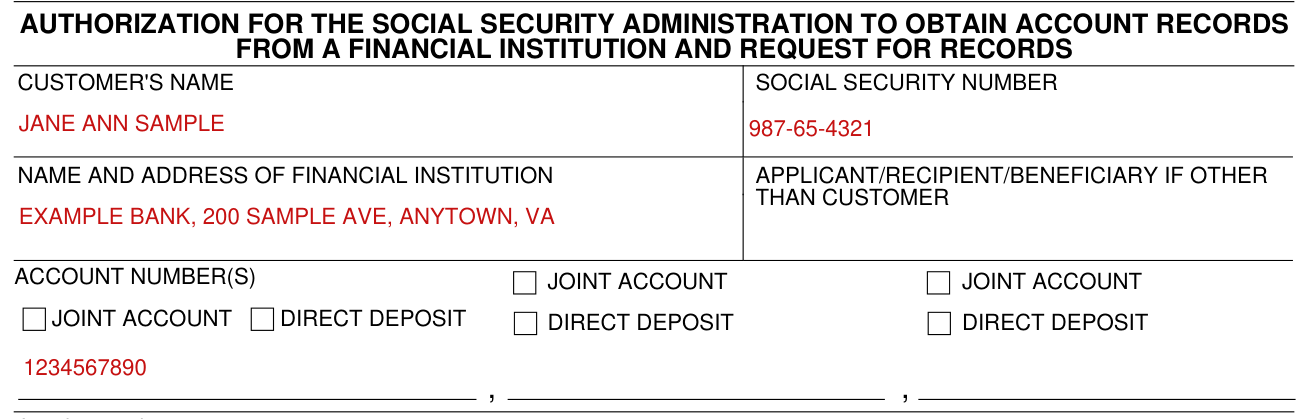
Enter the CUSTOMER'S NAME and the SOCIAL SECURITY NUMBER.
Enter the NAME AND ADDRESS OF FINANCIAL INSTITUTION and the APPLICANT/RECIPIENT/BENEFICIARY IF OTHER THAN CUSTOMER.
Enter the ACCOUNT NUMBER(S) and mark JOINT ACCOUNT or DIRECT DEPOSIT.
Reason for your authorization
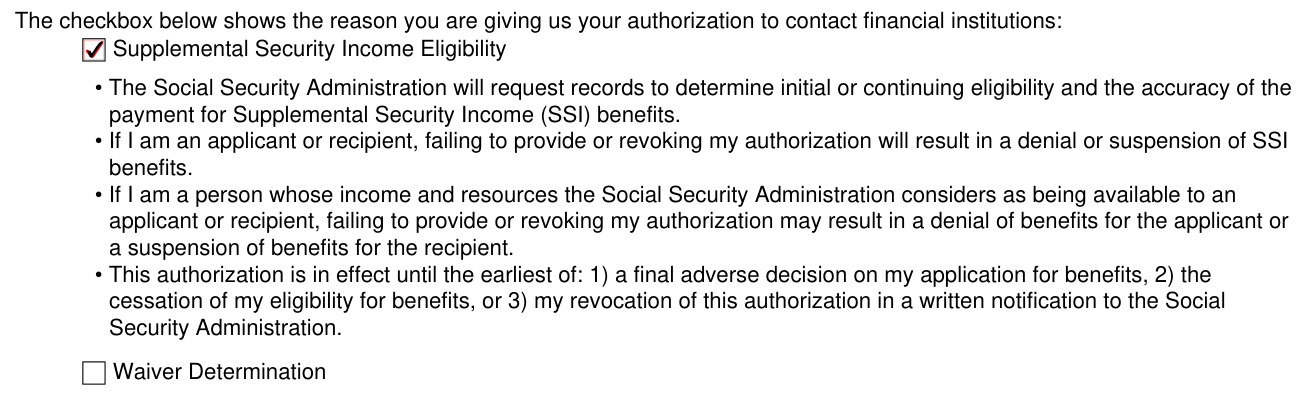
The checkbox shows the reason you are giving the Social Security Administration your authorization to contact financial institutions. Mark Supplemental Security Income Eligibility: the Social Security Administration will request records to determine initial or continuing eligibility and the accuracy of the payment for Supplemental Security Income (SSI) benefits. If you are an applicant or recipient, failing to provide or revoking your authorization will result in a denial or suspension of SSI benefits. If you are a person whose income and resources the Social Security Administration considers as being available to an applicant or recipient, failing to provide or revoking your authorization may result in a denial of benefits for the applicant or a suspension of benefits for the recipient. This authorization is in effect until the earliest of: 1) a final adverse decision on your application for benefits, 2) the cessation of your eligibility for benefits, or 3) your revocation of this authorization in a written notification to the Social Security Administration.
Mark Waiver Determination: the Social Security Administration will request records to determine the ability to repay an overpayment in conjunction with a waiver determination. Failing to provide or revoking your authorization may result in the Social Security Administration determining, on that basis, that adjustment or recovery of the overpayment will not deprive you of funds to pay your bills for food, clothing, housing, medical care, or other necessary expenses. This authorization is in effect until the earliest of: 1) a final decision on whether adjustment or recovery of your overpayment would deprive you of funds to pay your bills for food, clothing, housing, medical care, or other necessary expenses; or 2) your revocation of this authorization in a written notification to the Social Security Administration.
Authorization to disclose records

You authorize any custodian of records at this financial institution to disclose to the Social Security Administration any records about your financial business or that of the person whom you legally represent or whose benefits you manage.
Legal representative's signature, mailing address and date

Sign in LEGAL REPRESENTATIVE'S SIGNATURE / AUTHORIZATION, then enter the LEGAL REPRESENTATIVE'S MAILING ADDRESS and the DATE.
More rules for Form SSA-4641
You understand: you have the right to revoke this authorization at any time before any records are disclosed; the Social Security Administration may request all records about you from any financial institution; any information obtained will be kept confidential; you have the right to obtain a copy of the record which the financial institution keeps concerning the instances when it has disclosed records to a government authority unless the records were disclosed because of a court order; and this authorization is not required as a condition of doing business with any financial institution.
The Social Security Administration representative certifies that the applicable provisions of the Right to Financial Privacy Act of 1978 (12 U.S.C. 3401-3422) have been complied with in this request. Pursuant to the Right to Financial Privacy Act of 1978, good faith reliance upon this certification relieves the financial institution and its employees and agents of any possible liability to the customer in connection with the disclosure of these financial records.
Witnesses and the financial institution representative
You have signed by mark (X)
Your authorization does not ordinarily have to be witnessed. However, if you have signed by mark (X), two witnesses to the signing who know you must sign giving their full addresses.
Enter 1. SIGNATURE OF WITNESS and 2. SIGNATURE OF WITNESS, each with an ADDRESS (Number, Street, City, State, Zip Code).
For completion by the financial institution representative
Refer to page one for information concerning the accounts to be verified.
If the customer owns other accounts that are not listed, please provide information on those accounts for the time frame requested.
Spaces are available for up to three accounts. If there are more than three accounts, please provide information on a separate sheet of paper.
For ACCOUNT 1, ACCOUNT 2 and ACCOUNT 3, enter the TYPE OF ACCOUNT, the ACCOUNT NUMBER and the NAME(S) ON AND EXACT ACCOUNT DESIGNATION: 1 Checking, Savings, Time/Certificate of Deposit, Keogh, IRA, UGMA/UTMA, Escrow, Etc.
Copies of account records may be submitted in lieu of entering data. For all accounts, provide opening balances as of the first day of the month for each account, for each month listed in the period.
Unless this box is checked, do not provide interest paid or credited during each month.
If no accounts are located, check the box where indicated: No accounts were located for this customer.
Please include at the end of this form the name of the financial institution representative providing account information.
This request is authorized by sections 204(b), 1631(b)(1)(B) and 1631 (e)(1)(B) of the Social Security Act, as amended.
Please return this form and all supporting materials to the Social Security Administration in the postage free return envelope provided.
Sources
[1] Form SSA-4641 (10-2019), Authorization for the Social Security Administration to Obtain Account Records from a Financial Institution and Request for Records, Social Security Administration (the Official source link on this page).