


Form SSA-787 at a glance
What it is: Form SSA-787 (12-2018) of the Social Security Administration is the Medical Source Opinion of Patient's Capability to Manage Benefits.
Where and when to file: Send or bring the completed form to your local Social Security office.
The patient has filed for or is receiving Social Security or Supplemental Security Income benefits. Complete the back of this form and return it in the enclosed envelope to help decide if the Social Security Administration (SSA) should pay this person directly or if he or she needs a representative payee to manage the SSA benefits on his or her behalf. This determination affects how benefits are paid and has no bearing on disability determinations. SSA cannot compensate you for the time it takes to provide this information.
A representative payee is someone who manages the patient's SSA benefits to make sure the patient's basic needs are met.
A filled-in Form SSA-787 example: a physician says no to question 4

How to fill out Form SSA-787, box by box
Patient's name, Social Security number, date of birth and address
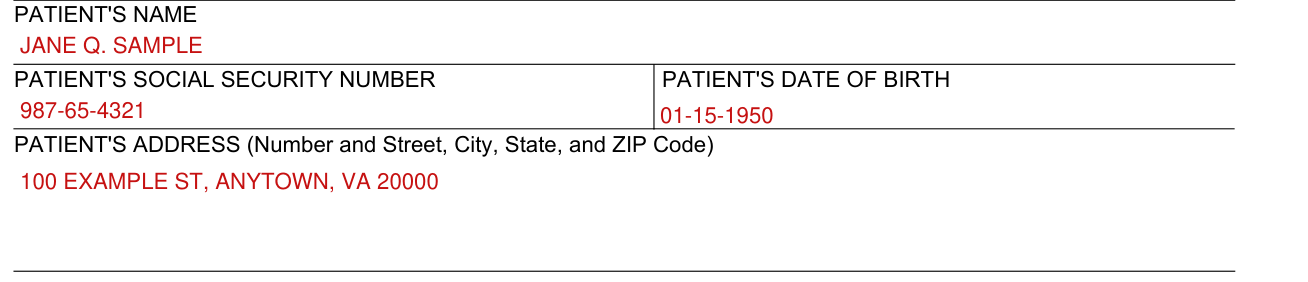
Enter the patient's name, the patient's social security number, the patient's date of birth and the patient's address (Number and Street, City, State, and ZIP Code).
Date you first saw the patient, date you last saw the patient and how many times

Enter the date you first saw the patient, the date you last saw the patient and how many times you have seen this patient.
Are you able to assess the patient's ability to manage or direct the management of funds
4. Are you able to assess the patient's ability to manage or direct the management of funds? Mark No or Yes.
If no, skip the remaining questions and sign and date the form.
The basis for your assessment
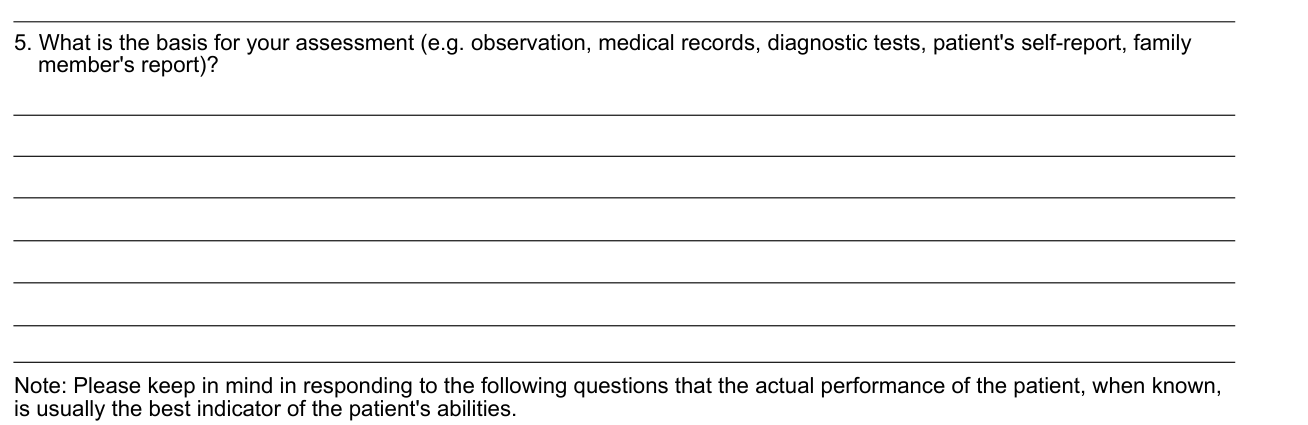
Write the basis for your assessment (e.g. observation, medical records, diagnostic tests, patient's self-report, family member's report).
Does the patient
Keep in mind in responding to the following questions that the actual performance of the patient, when known, is usually the best indicator of the patient's abilities.
6. Does the patient have a general understanding of his or her finances (i.e., income, assets, expenses), have sufficient ability to handle a checking/savings account, and have sufficient ability to pay bills in a timely manner? Mark Yes, No or Unknown for each.
Can the patient manage or direct the management of funds to meet basic needs

Can the patient successfully manage or direct the management of funds to meet basic needs (e.g. food, clothing, shelter)? Mark Unsure, No or Yes. If "Yes" or "No," provide a brief summary of the findings that led to this conclusion, and complete question 8. Also sign and date the form.
"Unsure," explain and sign and date the form.
Do you expect the patient to manage benefits in the future

Do you expect the patient to be able to manage or direct the management of his or her benefits in the future (e.g. the patient is temporarily unconscious)? Mark No or Yes. Please explain your answer.
Signing as the medical source

Print the TITLE, NAME OF MEDICAL SOURCE, TELEPHONE NUMBER (Include Area Code) and ADDRESS (Number and Street, City, State, and ZIP Code), then add the SIGNATURE OF MEDICAL SOURCE and the DATE.
You declare under penalty of perjury that you have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of your knowledge.
Anyone who knowingly gives a false statement about a material fact in this information, or causes someone else to do so, commits a crime and may be subject to a fine or imprisonment.
More rules for Form SSA-787
IDENTIFYING INFORMATION (SSA Only) is for SSA only, so leave the NAME OF WAGE EARNER OR SELF-EMPLOYED PERSON and the SOCIAL SECURITY NUMBER to SSA.
It will take about 20 minutes to read the instructions, gather the facts, and answer the questions.
Common questions about Form SSA-787
Where do I file it?
Send or bring the completed form to your local Social Security office. You can find your local Social Security office through SSA's website at www.socialsecurity.gov. You may call Social Security at 1-800-772-1213 (TTY 1-800-325-0778).
Sources
[1] Form SSA-787 (12-2018), Medical Source Opinion of Patient's Capability to Manage Benefits, Social Security Administration (the Official source link on this page).