

Tdap Vaccine Consent Form at a glance
What it is: Tdap Vaccine Consent Form: Tdap vaccine is recommended for adolescents and adults 11-64 years old. Tetanus leads to death in up to 2 cases out of 10. The vaccine is administered in the deltoid only.
Who signs: Sign on the line for the Signature of person receiving vaccine: I authorize SVNA to give me Tdap vaccination.
A filled-in Tdap Vaccine Consent Form example: an adult patient consents
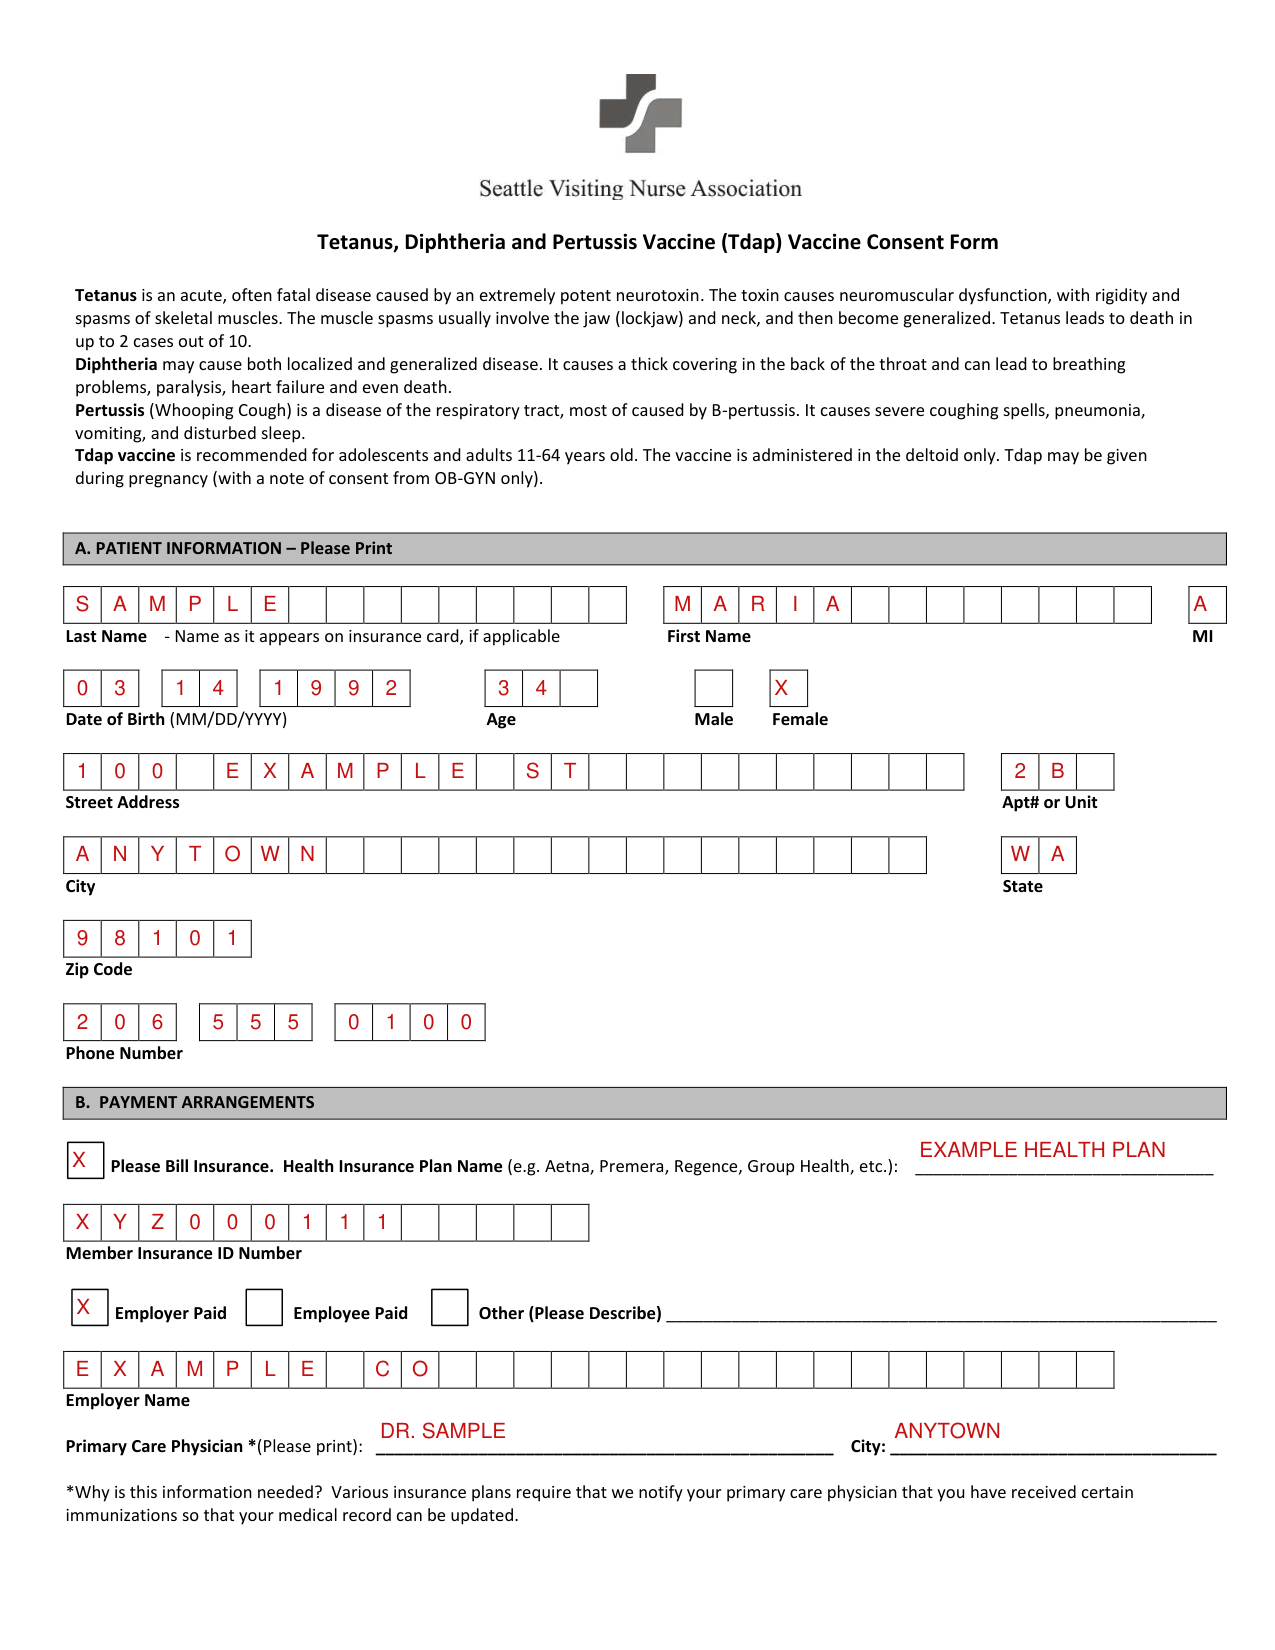
How to fill out Tdap Vaccine Consent Form, box by box
Last Name, Date of Birth and Street Address
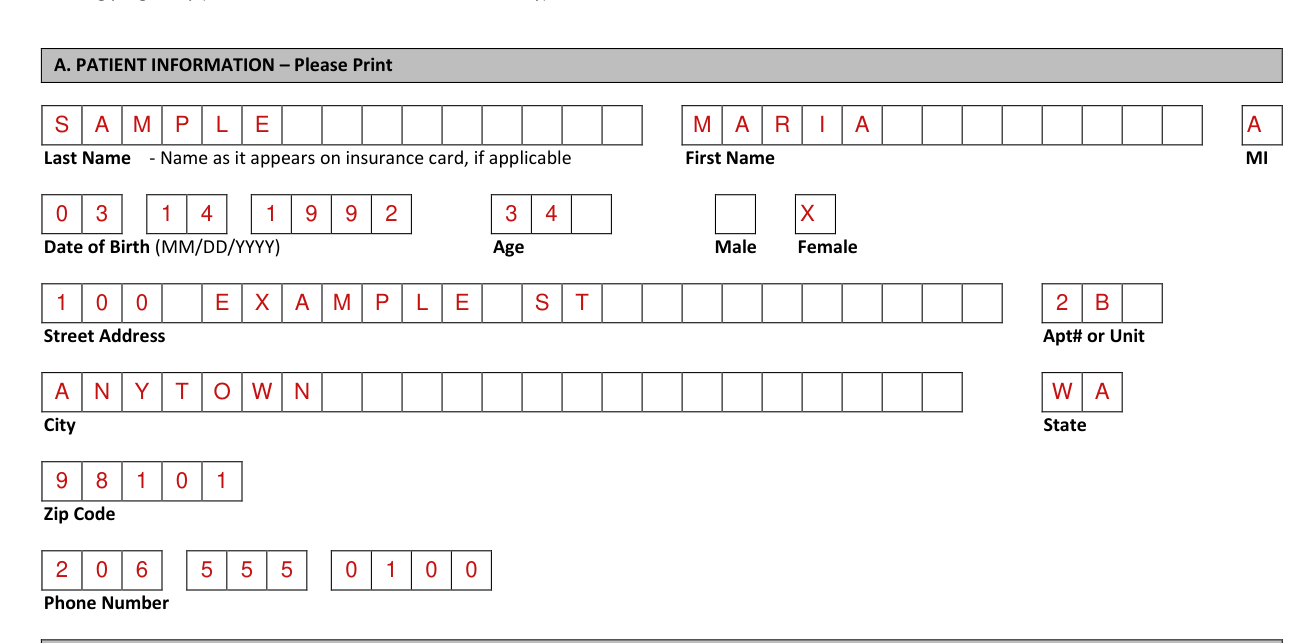
Enter the Last Name - Name as it appears on insurance card, if applicable, the First Name and the MI.
Enter the Date of Birth (MM/DD/YYYY) and the Age, then mark Male or Female.
Enter the Street Address and the Apt# or Unit.
Enter the City, the State, the Zip Code and the Phone Number.
B. PAYMENT ARRANGEMENTS

Under B. PAYMENT ARRANGEMENTS, mark Please Bill Insurance and enter the Health Insurance Plan Name (e.g. Aetna, Premera, Regence, Group Health, etc.).
Enter the Member Insurance ID Number.
Mark Employer Paid, Employee Paid or Other (Please Describe).
Enter the Employer Name, then print the Primary Care Physician and the City.
YES NO

Mark YES or NO for each of these: Are you allergic to preservatives, neomycin, thimerosal, streptomycin or latex? Do you have a history of Guillain-Barre syndrome or an active neurological disorder? Have you ever had a serious reaction after receiving any vaccination? Do you have a fever, diarrhea, or vomiting today? For Women: Are you pregnant or suspect you are pregnant?
If yes, you must consult your physician.
C. ACKNOWLEDGEMENT and AUTHORIZATION
It is recommended that, if this is a first vaccination, I will remain in the area for 15 minutes for assistance should any immediate reaction occur.
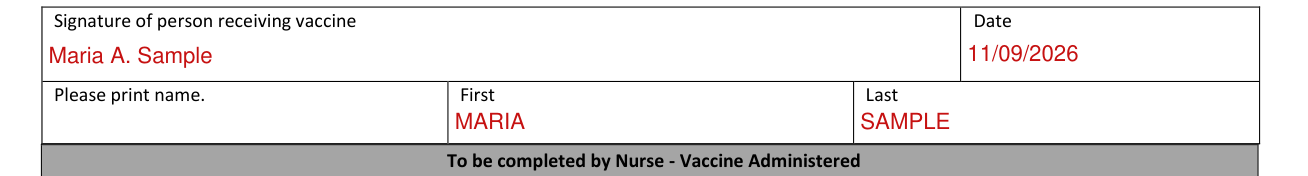
Sign on the line for the Signature of person receiving vaccine: I authorize SVNA to give me Tdap vaccination.
Enter the Date and Please print name, First and Last.
To be completed by Nurse

To be completed by Nurse - Vaccine Administered: Alpha Lot #, Dose, Right Deltoid or Left Deltoid, and Administered By with the Nurse Signature/Date.
More rules for Tdap Vaccine Consent Form
A person with a mild illness or low fever can usually be vaccinated.
Most people have no side effects from Tdap vaccines.
This may cause soreness for a day or two, mild fever, headache, tiredness, nausea, vomiting, diarrhea, stomach ache, chills, body aches, sore joints, rash, swollen glands.
Common questions about Tdap Vaccine Consent Form
When is this form not the right one?
Anyone who has had a life-threatening allergic reaction after a dose of DTP, DTap, DT or Td should not get Tdap.
Sources
[1] Tetanus, Diphtheria and Pertussis Vaccine (Tdap) Vaccine Consent Form (the Official source link on this page).
