

VA Form 21-0960C-8 at a glance
What it is: The Headaches (Including Migraine Headaches) Disability Benefits Questionnaire is for a physician whose patient is applying to the U.S. Department of Veterans Affairs (VA) for disability benefits.
Who signs: Sign in 9A. PHYSICIAN'S SIGNATURE.
A filled-in VA Form 21-0960C-8 example: a physician reports migraine and its treatment
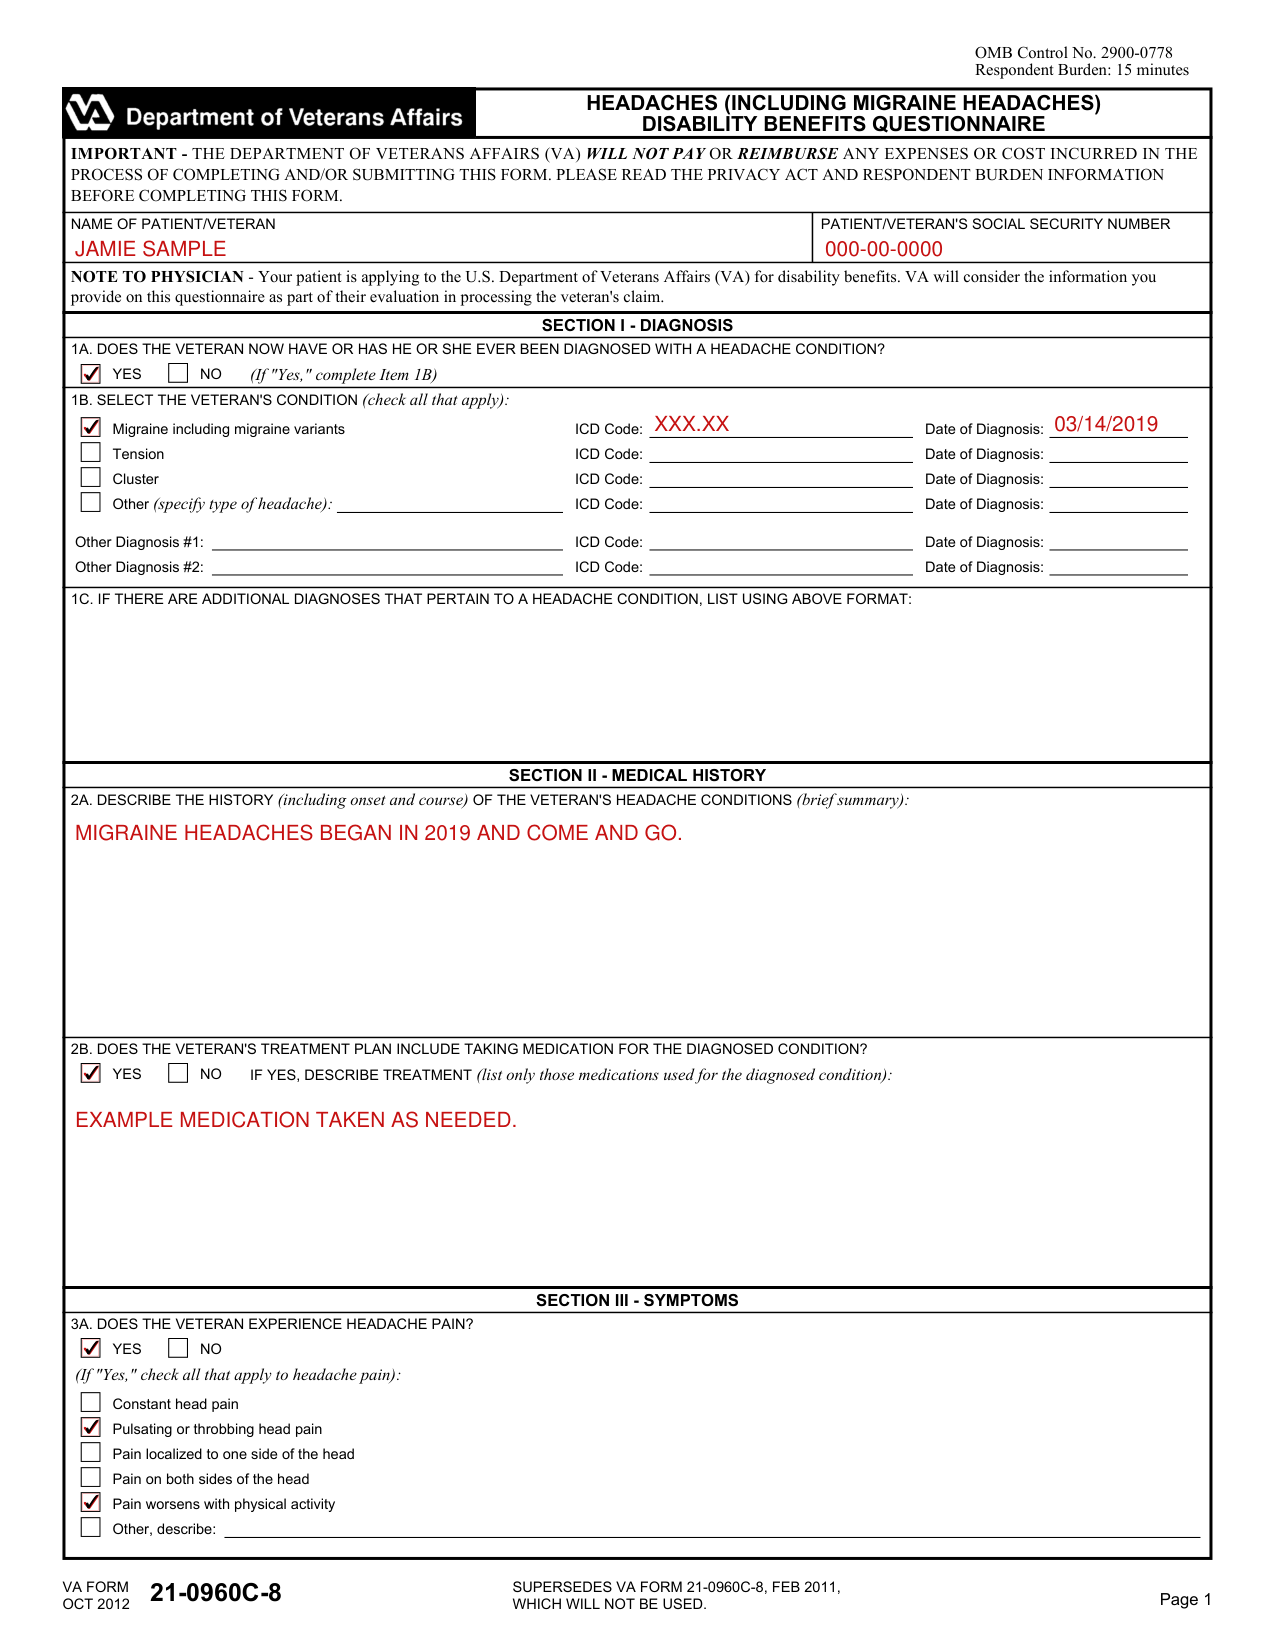
How to fill out VA Form 21-0960C-8, box by box
Name of patient/veteran and Social Security number

Enter the NAME OF PATIENT/VETERAN and the PATIENT/VETERAN'S SOCIAL SECURITY NUMBER.
1A. Does the veteran now have or has he or she ever been diagnosed with a headache condition?

Mark NO or YES for 1A: does the veteran now have or has he or she ever been diagnosed with a headache condition? If Yes, complete Item 1B.
1B. Select the veteran's condition
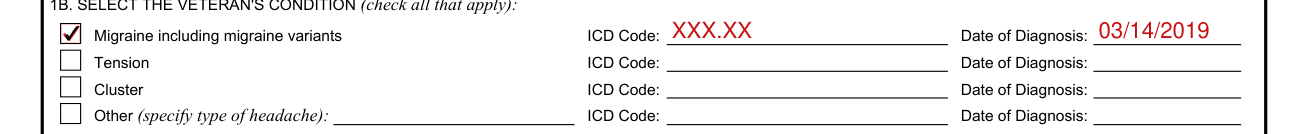
In 1B, check all that apply: Migraine including migraine variants, Tension, Cluster, or Other (specify type of headache).
For Migraine including migraine variants, enter the ICD Code and the Date of Diagnosis.
For Tension, enter the ICD Code and the Date of Diagnosis.
For Cluster, enter the ICD Code and the Date of Diagnosis.
For Other (specify type of headache), enter the ICD Code and the Date of Diagnosis.
1C. Additional diagnoses that pertain to a headache condition
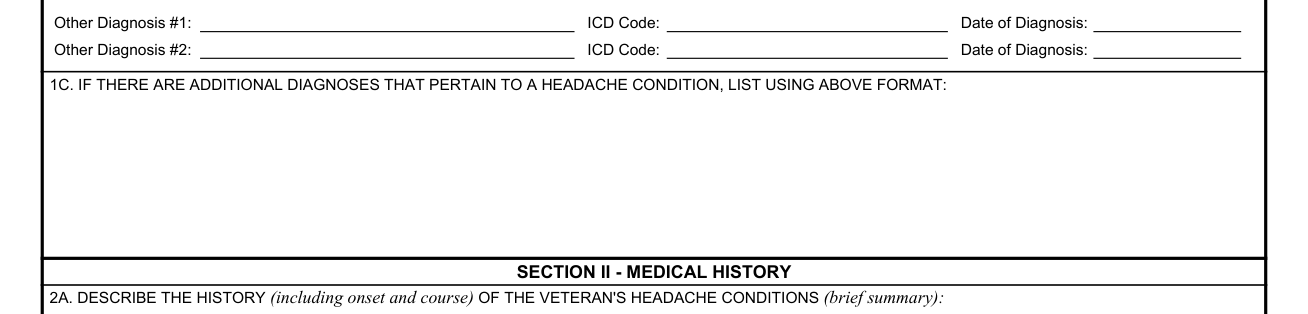
If there are additional diagnoses that pertain to a headache condition, list them in 1C as Other Diagnosis #1 and Other Diagnosis #2, each with its ICD Code and Date of Diagnosis.
2A. Describe the history of the veteran's headache conditions

In 2A, describe the history (including onset and course) of the veteran's headache conditions in a brief summary.
2B. Does the veteran's treatment plan include taking medication?
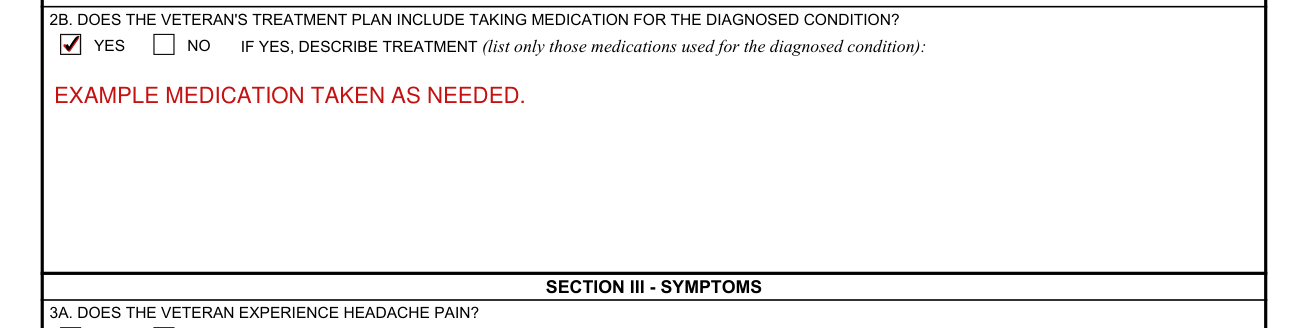
Mark YES or NO for 2B: does the veteran's treatment plan include taking medication for the diagnosed condition?
If Yes, describe treatment and list only those medications used for the diagnosed condition.
3A. Does the veteran experience headache pain?
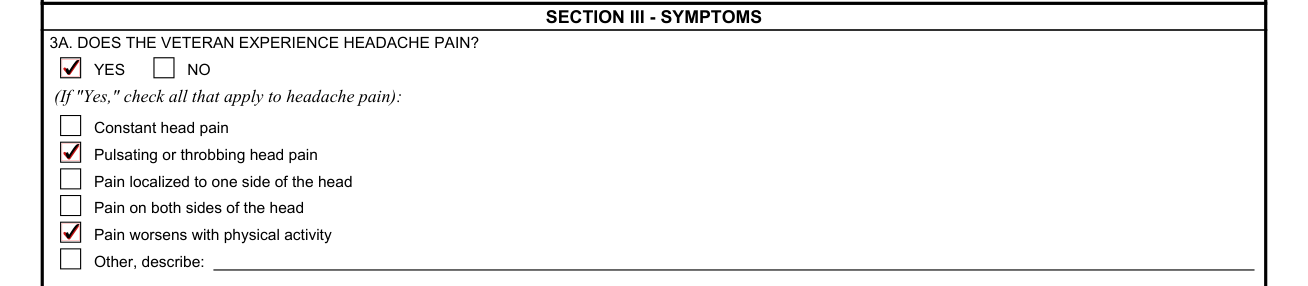
Mark YES or NO for 3A: does the veteran experience headache pain? If Yes, check all that apply to headache pain.
Check from Constant head pain, Pulsating or throbbing head pain, Pain localized to one side of the head, Pain on both sides of the head, Pain worsens with physical activity, and Other, describe.
3B. Non-headache symptoms associated with headaches
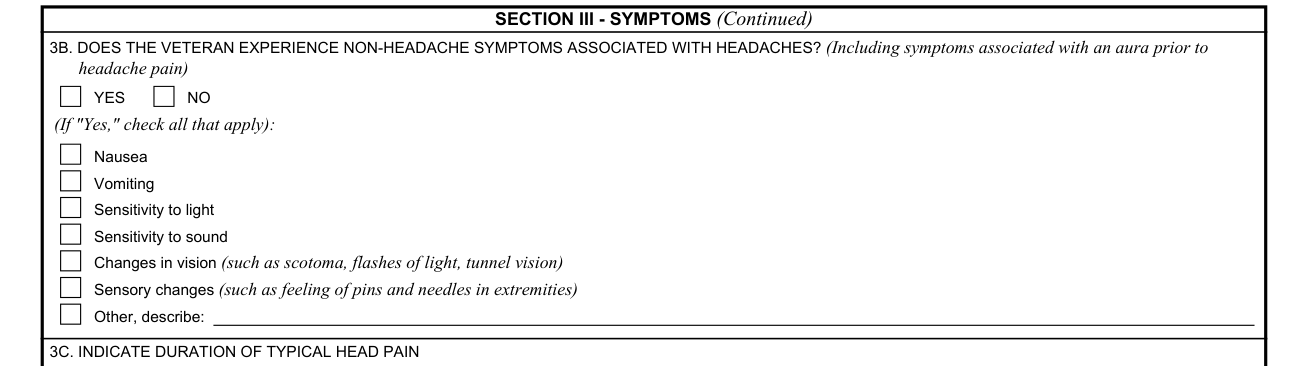
Mark NO or YES for 3B: does the veteran experience non-headache symptoms associated with headaches (including symptoms associated with an aura prior to headache pain)? If Yes, check all that apply.
Check from Nausea, Vomiting, Sensitivity to light, Sensitivity to sound, Changes in vision (such as scotoma, flashes of light, tunnel vision), Sensory changes (such as feeling of pins and needles in extremities), and Other, describe.
3C. Duration of typical head pain

In 3C, indicate duration of typical head pain: Less than 1 day, 1-2 days, More than 2 days, or Other, describe.
3D. Location of typical head pain

In 3D, indicate location of typical head pain: Right side of head, Left side of head, Both sides of head, or Other, describe.
4A and 4B. Migraine prostrating attacks
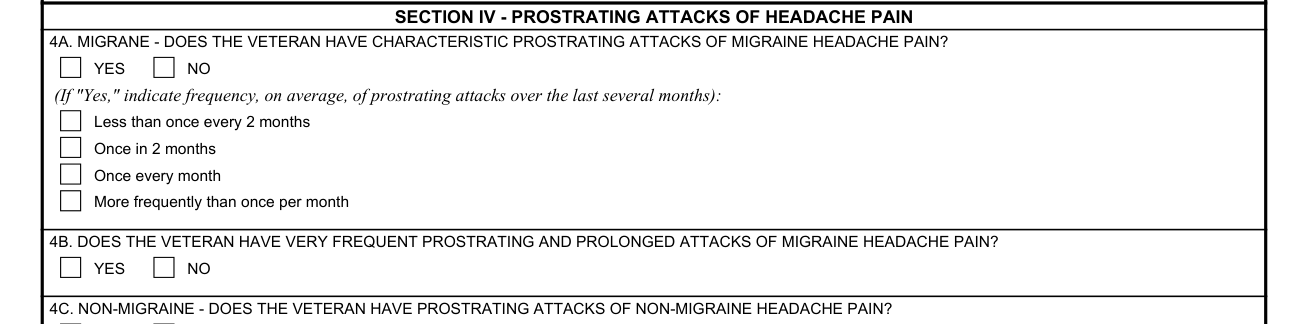
For 4A, mark YES or NO: does the veteran have characteristic prostrating attacks of migraine headache pain? If Yes, indicate frequency, on average, of prostrating attacks over the last several months: Less than once every 2 months, Once in 2 months, Once every month, or More frequently than once per month.
Mark YES or NO for 4B: does the veteran have very frequent prostrating and prolonged attacks of migraine headache pain?
4C and 4D. Non-migraine prostrating attacks
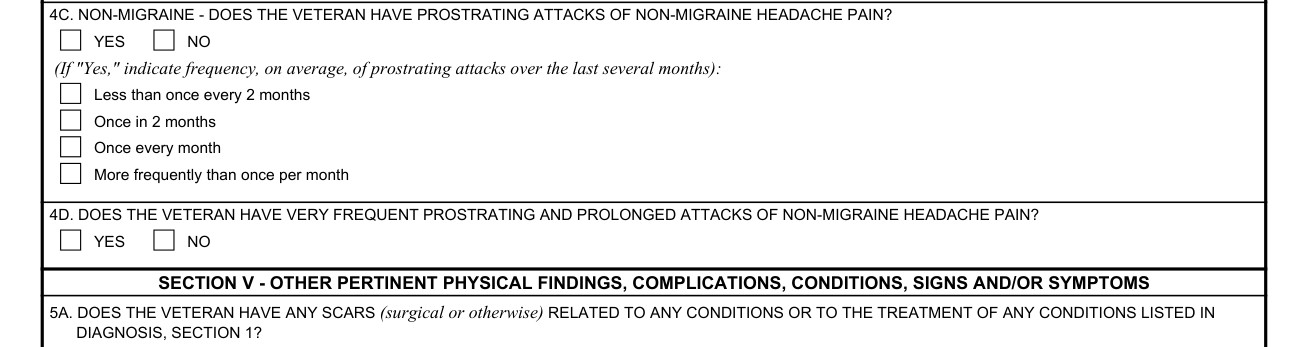
For 4C, mark NO or YES: does the veteran have prostrating attacks of non-migraine headache pain? If Yes, indicate frequency over the last several months, on average, of prostrating attacks: Less than once every 2 months, Once in 2 months, Once every month, or More frequently than once per month.
In 4D, does the veteran have very frequent prostrating and prolonged attacks of non-migraine headache pain? Mark YES or NO.
5A. Scars related to the conditions listed in Diagnosis

For 5A, mark NO or YES: does the veteran have any scars (surgical or otherwise) related to any conditions or to the treatment of any conditions listed in Diagnosis, Section 1? If Yes, mark NO or YES: are any of the scars painful and/or unstable, or is the total area of all related scars greater than or equal to 39 square cm (6 square inches)?
If Yes, also complete VA Form 21-0960F-1 Scars/Disfigurement Disability Benefits Questionnaire.
5B. Other pertinent physical findings

For 5B, mark NO or YES: does the veteran have any other pertinent physical findings, complications, conditions, signs and/or symptoms related to any conditions listed in Section 1, Diagnosis? If Yes, describe in a brief summary.
6. Other significant diagnostic test findings

For 6, mark YES or NO: are there any other significant diagnostic test findings and/or results? If Yes, provide type of test or procedure, date and results (brief summary).
Diagnostic testing is not requested for this examination report; if studies have already been completed, provide the most recent results.
7. Does the veteran's headache condition impact his or her ability to work?
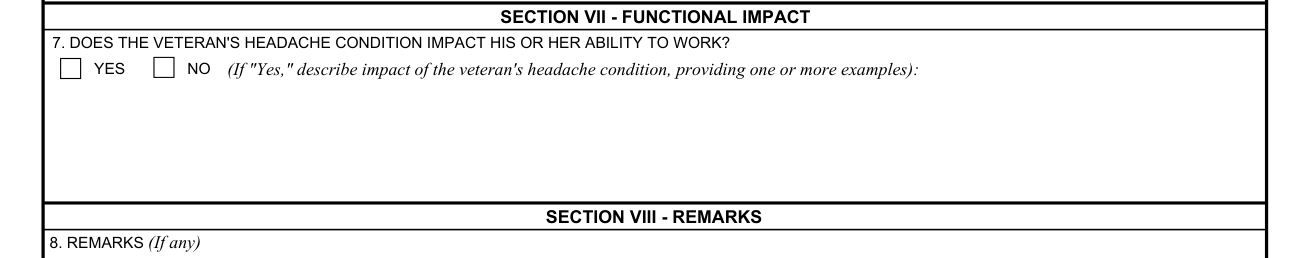
For 7, mark NO or YES: does the veteran's headache condition impact his or her ability to work? If Yes, describe impact of the veteran's headache condition, providing one or more examples.
8. Remarks
Enter any remarks in 8. REMARKS (If any).
Section IX. Physician's certification and signature

CERTIFICATION - To the best of my knowledge, the information contained herein is accurate, complete and current.
Enter 9B. PHYSICIAN'S PRINTED NAME and 9C. DATE SIGNED.
Enter 9D. PHYSICIAN'S PHONE AND FAX NUMBER, 9E. PHYSICIAN'S MEDICAL LICENSE NUMBER and 9F. PHYSICIAN'S ADDRESS.
VA may request additional medical information, including additional examinations, if necessary to complete VA's review of the veteran's application.
Physician please fax the completed form

Physician please fax the completed form to the VA Regional Office FAX No.
A list of VA Regional Office FAX Numbers can be found at www.benefits.va.gov/disabilityexams or obtained by calling 1-800-827-1000.
More rules for VA Form 21-0960C-8
VA will consider the information provided on this questionnaire as part of its evaluation in processing the veteran's claim.
Common questions about VA Form 21-0960C-8
Are there fees?
VA will not pay or reimburse any expenses or cost incurred in the process of completing and/or submitting this form.
Sources
[1] VA Form 21-0960C-8 (OCT 2012), Headaches (Including Migraine Headaches) Disability Benefits Questionnaire, Department of Veterans Affairs (the Official source link on this page).
