
Vision Benefits Claim Form PDF Details

Navigating the terrain of insurance claims can often feel like deciphering an ancient script. Among such forms, the Vision Benefits Claim Form emerges as a critical document for those aiming to secure reimbursements for vision care expenses. This form mandates a meticulous level of accuracy and thoroughness from the cardholder, highlighting the importance of providing correct and complete information to ensure the smooth processing of claims. Essential fields include patient and cardholder details, such as names, identification numbers, and relationships, alongside specifics about the insurance carrier and employer, delineating the pathway to ascertain coverage eligibility. Furthermore, the form opens a window into the detailed universe of vision care, demanding information about the services rendered—ranging from exams to eyewear. Also crucial is the authorization for information release, underpinning the claim's legitimacy, and a declaration ensuring that the information provided is truthful and claims are made solely for incurred charges. Augmenting the form are stark fraud warnings across various states, underscoring the legal implications of submitting fraudulent claims, thereby weaving a tapestry of accountability and precision. Thus, this form not only facilitates the reimbursement process but also diligently guards against insurance fraud, illuminating its multifaceted role in the landscape of vision care insurance.

QuestionAnswer
Form NameVision Benefits Claim Form
Form Length2 pages
Fillable?Yes
Fillable fields54
Avg. time to fill out30 sec
Other namesclaimant, avesis forms, avesis android app, Arizona

How to Fill Out Vision Benefits Claim Form

Vision Benefits Claim Form at a glance

What it is: The Vision Benefits Claim Form is submitted with itemized receipt(s) to Avēsis Third Party Administrators, Inc.

Who signs: The cardholder signs on the Signature of Cardholder line and enters the Date Signed.

The form is to be completed by the cardholder.

A filled-in Vision Benefits Claim Form example: John Sample claims for his wife
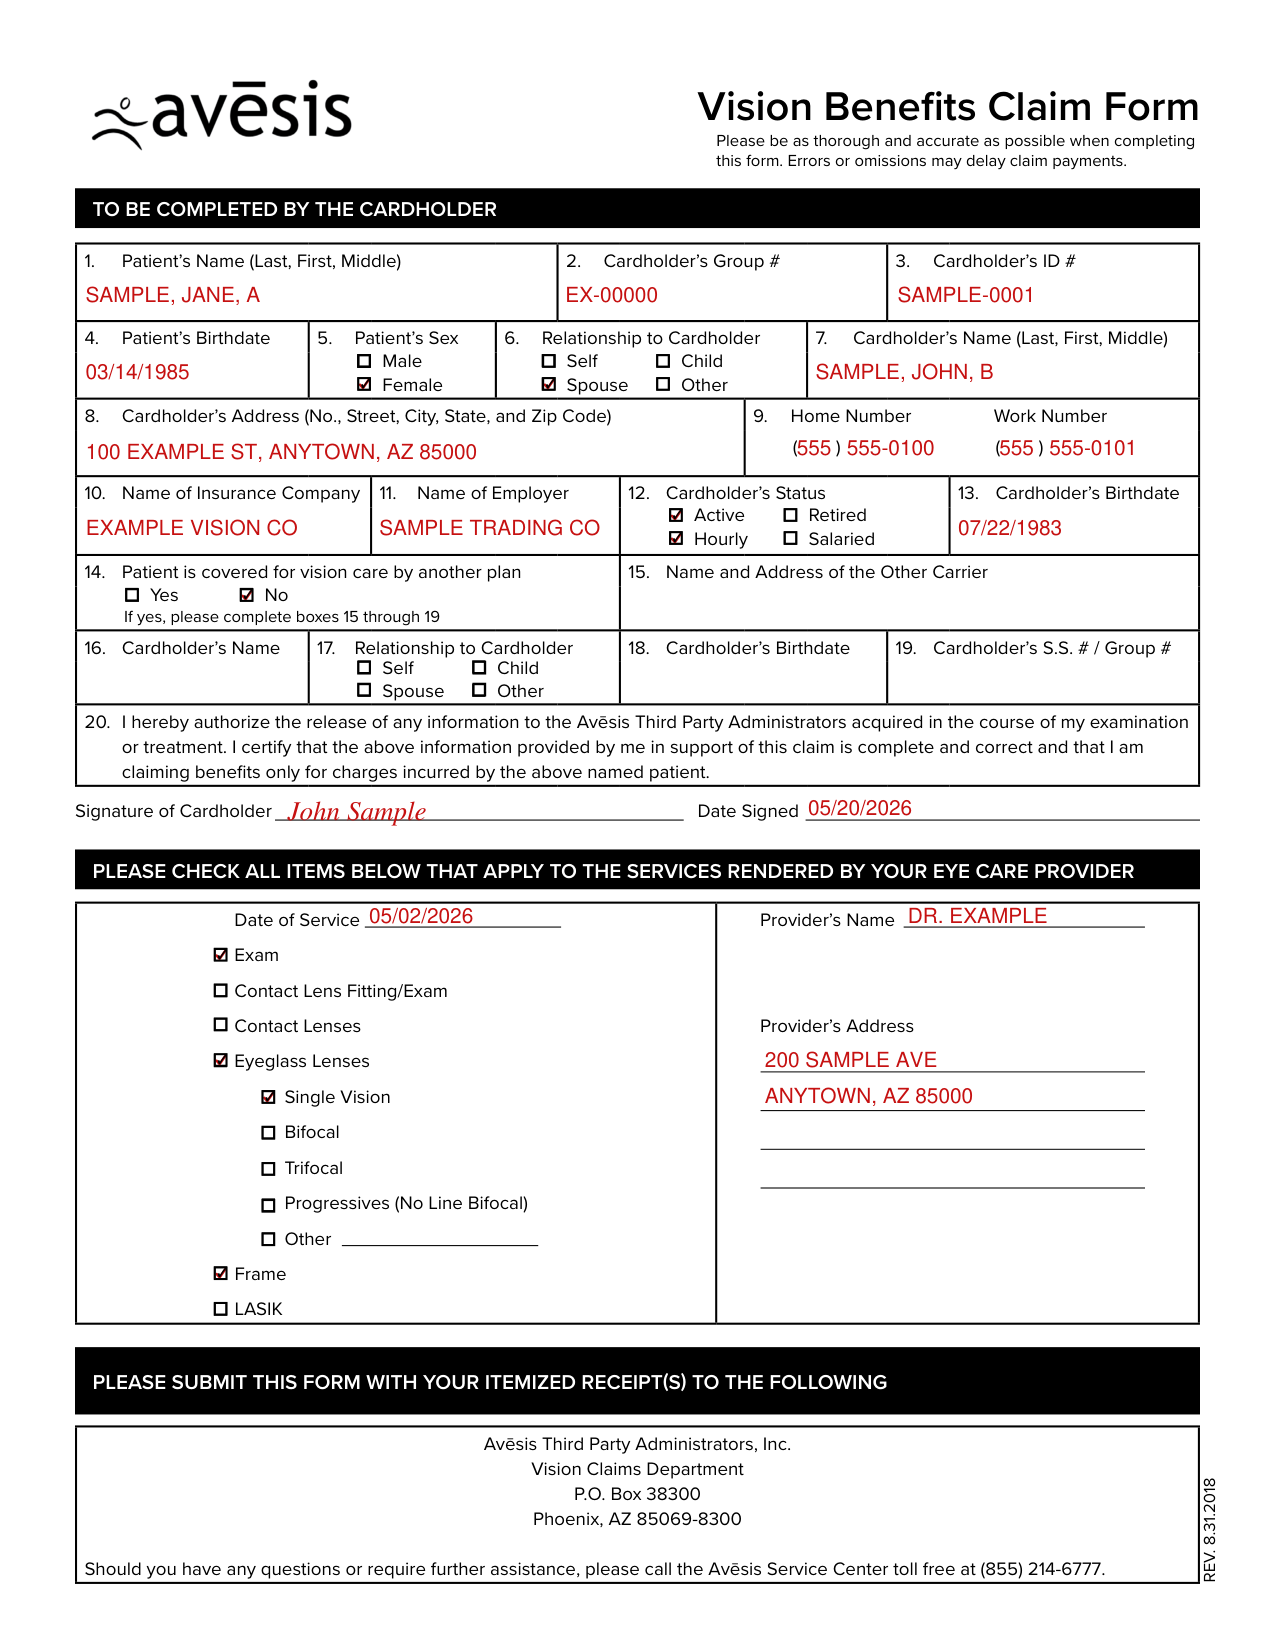
Vision Benefits Claim Form example filled out, example: John Sample claims for his wife
John Sample files the Vision Benefits Claim Form for his wife Jane. Jane had an eye exam and bought a frame with single vision lenses. The picture shows the filled form, and none of its entries is real. Jane is John's spouse and a woman, so Female and Spouse are checked. John is an active hourly employee, so Active and Hourly are checked. No other plan covers Jane, so No is checked and the other carrier boxes 15 through 19 stay empty.

How to fill out Vision Benefits Claim Form, box by box

Patient's Name, Birthdate and Relationship to Cardholder
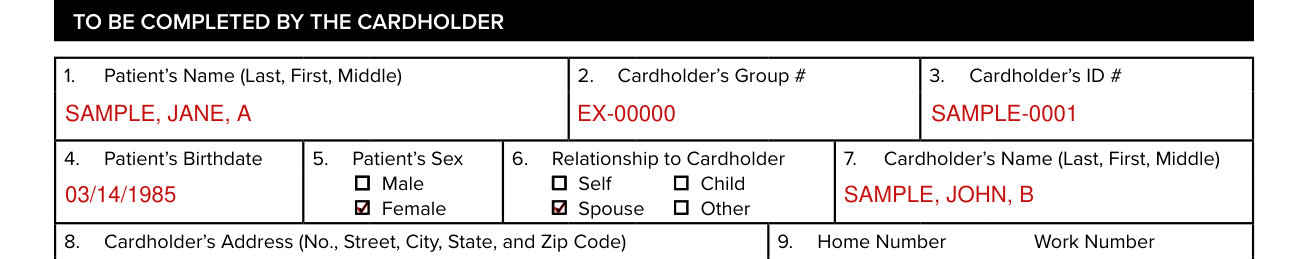
Vision Benefits Claim Form example filled out, patient's Name, Birthdate and Relationship to Cardholder

Enter the Patient's Name (Last, First, Middle), the Cardholder's Group # and the Cardholder's ID #.

Enter the Patient's Birthdate, check the Patient's Sex (Male or Female) and the Relationship to Cardholder (Self, Spouse, Child or Other), and enter the Cardholder's Name (Last, First, Middle).

Cardholder's Address, Home Number and Work Number
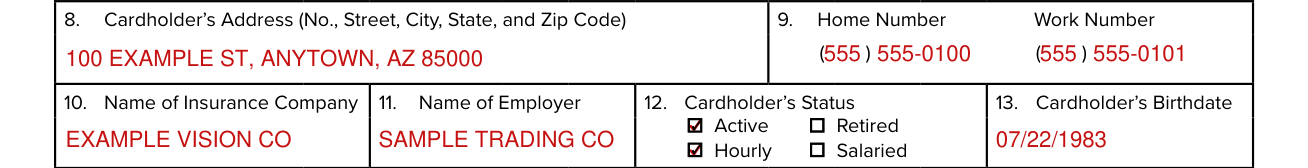
Vision Benefits Claim Form example filled out, cardholder's Address, Home Number and Work Number

Enter the Cardholder's Address (No., Street, City, State, and Zip Code), the Home Number and the Work Number.

Name of Insurance Company, Name of Employer and Cardholder's Status
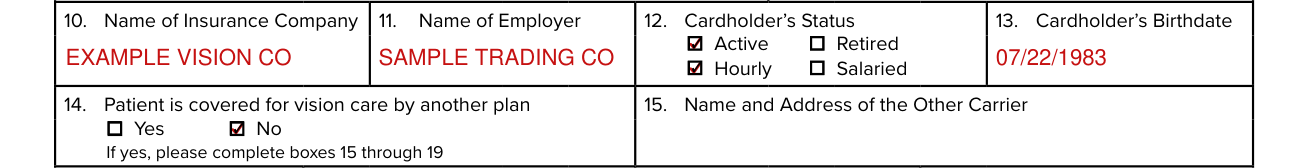
Vision Benefits Claim Form example filled out, name of Insurance Company, Name of Employer and Cardholder's Status

Enter the Name of Insurance Company, the Name of Employer and the Cardholder's Birthdate, and check the Cardholder's Status: Active, Hourly, Retired or Salaried.

Other carrier: boxes 14 through 19
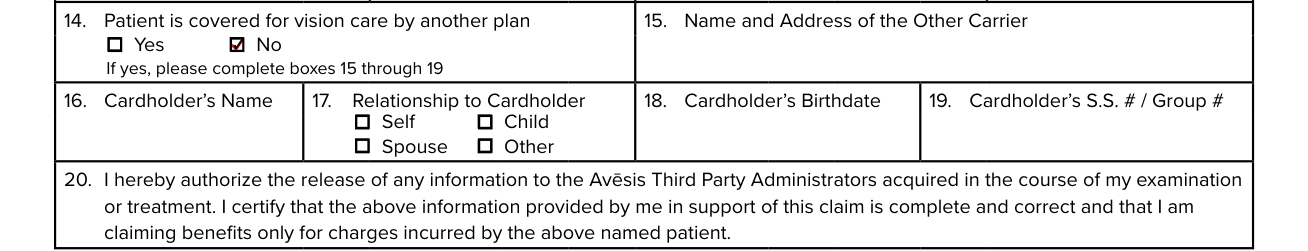
Vision Benefits Claim Form example filled out, other carrier: boxes 14 through 19

Check Yes or No for the patient covered for vision care by another plan.

If yes, complete boxes 15 through 19: the Name and Address of the Other Carrier, the Cardholder's Name, the Relationship to Cardholder (Self, Spouse, Child or Other), the Cardholder's Birthdate and the Cardholder's S.S. # / Group #.

Signature, box 20

Vision Benefits Claim Form example filled out, signature, box 20

By signing box 20, you authorize the release of any information to the Avēsis Third Party Administrators acquired in the course of your examination or treatment. You certify that the information provided by you in support of this claim is complete and correct and that you are claiming benefits only for charges incurred by the named patient.

Services rendered by your eye care provider

Vision Benefits Claim Form example filled out, services rendered by your eye care provider

Check all items that apply to the services rendered by your eye care provider: Exam, Contact Lens Fitting/Exam, Contact Lenses, Eyeglass Lenses, Single Vision, Bifocal, Trifocal, Progressives (No Line Bifocal), Other, Frame and LASIK.

For the services rendered by your eye care provider, enter the Date of Service, the Provider's Name and the Provider's Address.

More rules for Vision Benefits Claim Form

Be as thorough and accurate as possible when completing this form. Errors or omissions may delay claim payments.

Call the Avēsis Service Center toll free at (855) 214-6777 with any questions or to require further assistance.

Common questions about Vision Benefits Claim Form

Where do I file it?

Submit this form with your itemized receipt(s) to Avēsis Third Party Administrators, Inc., Vision Claims Department, P.O. Box 38300 Phoenix, AZ 85069-8300.

Sources

[1] Vision Benefits Claim Form (REV. 8.31.2018), Avēsis Third Party Administrators (the Official source link on this page).

Please rate Vision Benefits Claim Form Rev. 8.31.2018

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .