Vision Claim Transmittal Form PDF Details

When it comes to vision care claims, ensuring accuracy and completeness in documentation is crucial for a smooth processing experience. The Vision Claim Transmittal form, utilized for submissions to UnitedHealthcare, embodies this principle by guiding both providers and policyholders through a detailed outline of necessary information. Situated at the core of the form are sections dedicated to comprehensive member and patient details, including identification, contact, and insurance information, all designed to streamline the identification and processing of the claim. Noteworthy is the section aimed specifically at vision care providers, mandating the inclusion of a correct patient diagnosis, the date of service, and the precise circling of applicable procedure codes, emphasizing the necessity of precision in health claims submissions. Furthermore, the form addresses scenarios involving accidents, inquiring about their nature and details, an aspect critical for claims tied to specific incidents. It also navigates through the intricacies of dealing with other insurance carriers that may cover the patient, requesting detailed information to ascertain coordination of benefits. Insightfully, the form provides a designated area for providers to list services rendered alongside their associated charges, which plays a pivotal role in determining the claim amount. Significantly, it features an option for the assignment of benefits, which, when opted into, allows for direct payment to service providers, simplifying the reimbursement process. By meticulously filling out this form and ensuring no supplementary documents such as receipts or bills are attached upon submission, claimants enhance the efficiency of the adjudication process, thereby fostering a smoother path to claim resolution.

QuestionAnswer
Form NameVision Claim Transmittal Form
Form Length2 pages
Fillable?No
Fillable fields0
Avg. time to fill out30 sec
Other namesuhc vision claim form, united healthcare reimbursement form vision, united healthcare vision out of network claim form, united healthcare vision reimbursement form

How to Fill Out Vision Claim Transmittal

Vision Claim Transmittal at a glance

What it is: Vision Claim Transmittal, Claim Address: UnitedHealthcare PO Box 740800 Atlanta, GA 30374-0800, Employer Name: North Jersey Health Insurance Fund.

Where and when to file: Make sure form is completely filled out and mail only this form to the address on the form.

A filled-in Vision Claim Transmittal example: a member fills in sections A and B
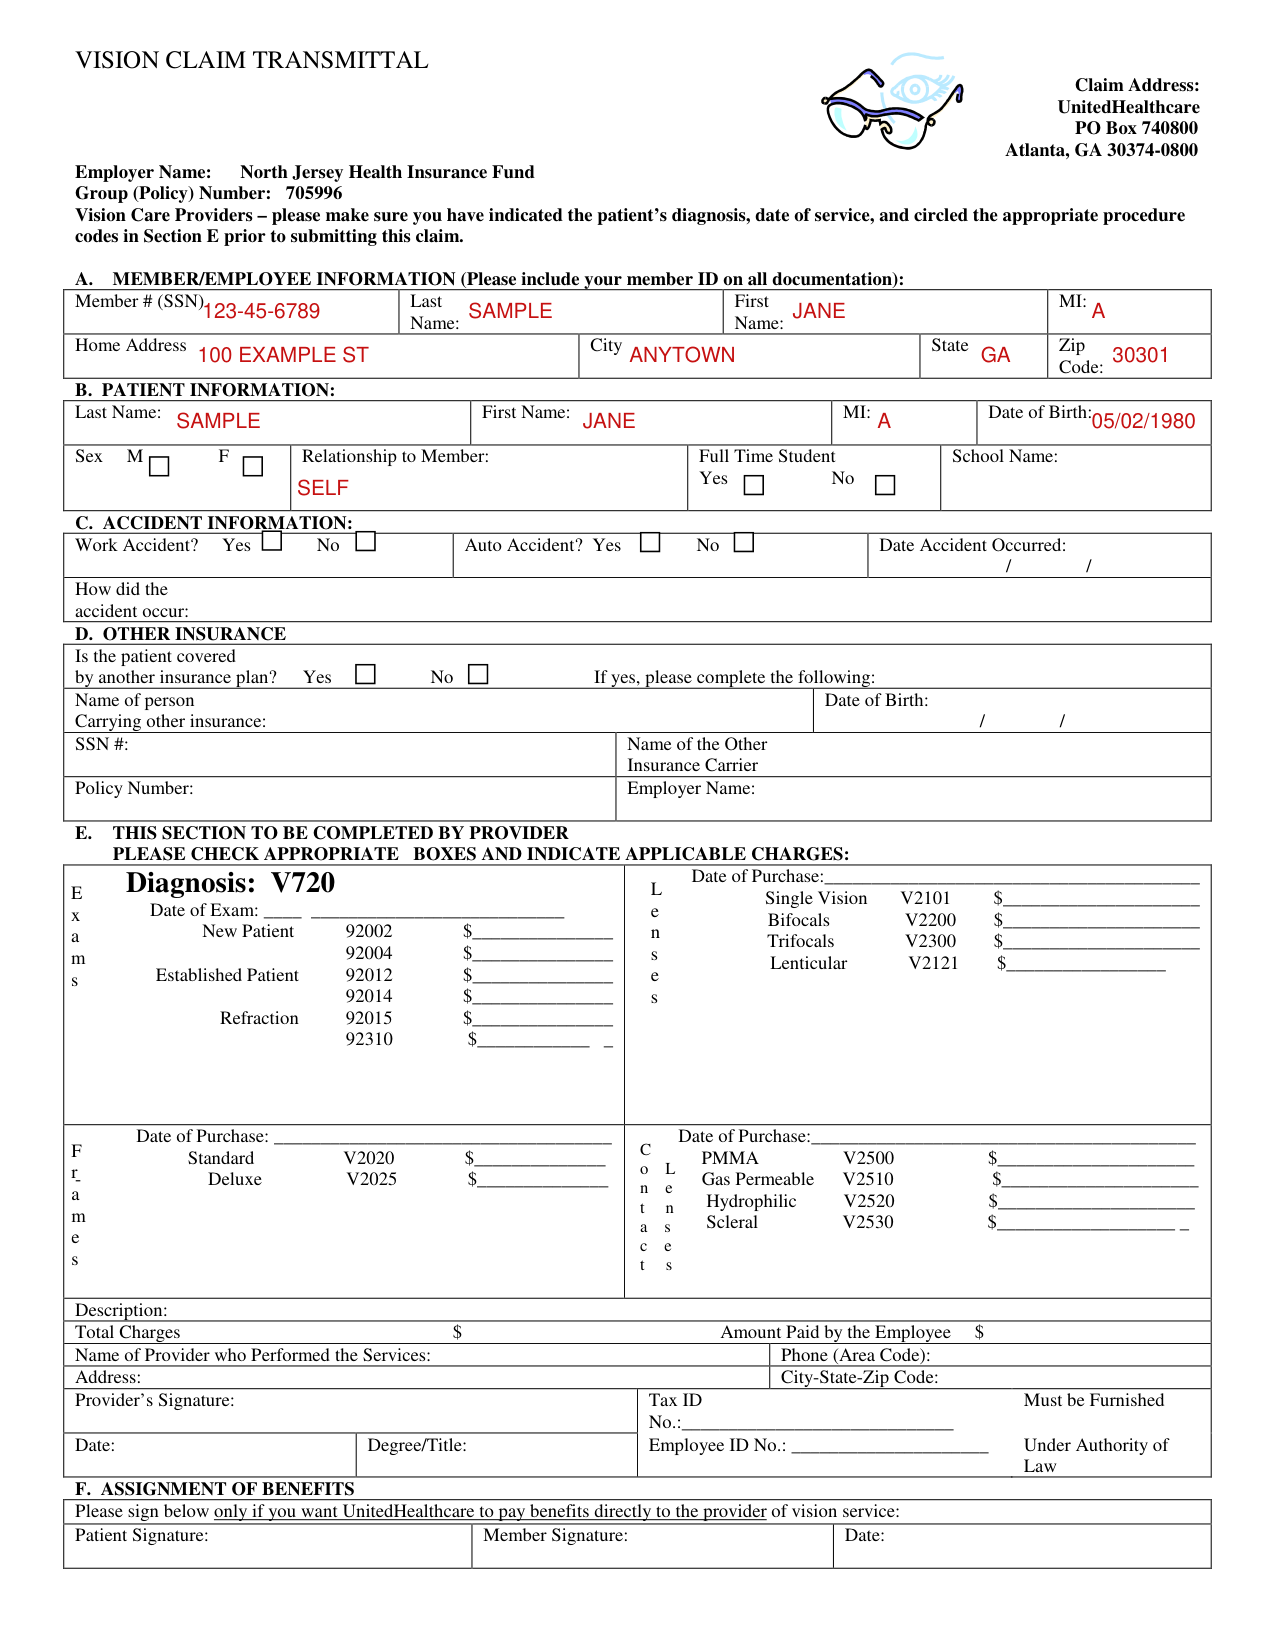
Vision Claim Transmittal example filled out, example: a member fills in sections A and B
Jane Sample, a member, fills out the Vision Claim Transmittal for herself. She is her own patient, so B repeats her name and Relationship to Member says Self. The picture shows sections A and B; every value in it is made up. She checks No for Work Accident? and Auto Accident? and No for Is the patient covered by another insurance plan?, and the provider completes E. Assignment of benefits is left blank because she wants no direct payment to the provider.

How to fill out Vision Claim Transmittal, box by box

A. Member/Employee information
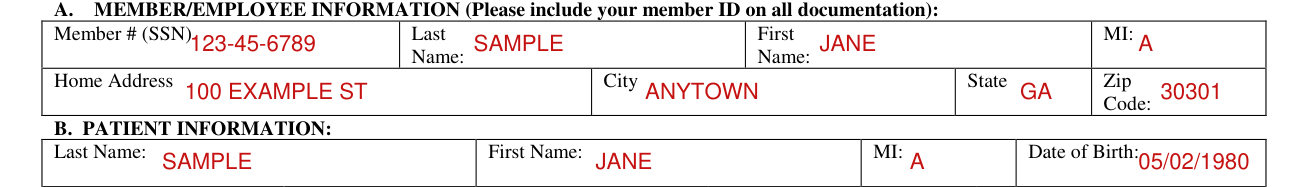
Vision Claim Transmittal example filled out, a. Member/Employee information

In A. MEMBER/EMPLOYEE INFORMATION, include your member ID on all documentation and enter Member # (SSN), Last Name, First Name and MI.

B. Patient information
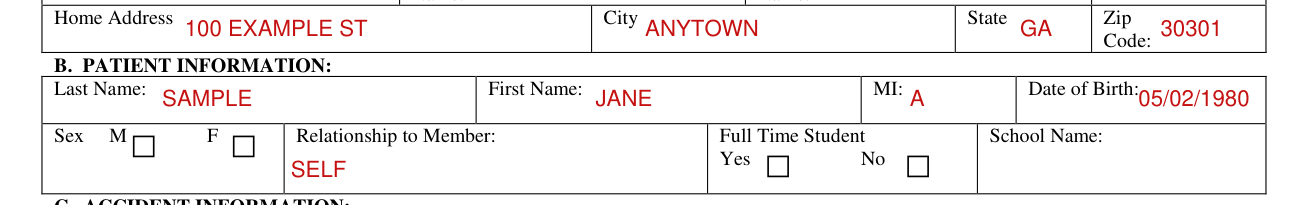
Vision Claim Transmittal example filled out, b. Patient information

Under Home Address, enter City, State and Zip Code. In B. PATIENT INFORMATION, enter Last Name, First Name, MI, Date of Birth, Sex M F, Relationship to Member and Full Time Student Yes No.

Enter the School Name.

C. Accident, D. Other insurance and E. Provider section

Vision Claim Transmittal example filled out, c. Accident, D. Other insurance and E. Provider section

C. Accident Information: Work Accident? Yes No Auto Accident? Yes No Date Accident Occurred, How did the accident occur. D. Other Insurance: Is the patient covered by another insurance plan? Yes No If yes, please complete the following: Name of person Carrying other insurance, Date of Birth, SSN #, Name of the Other Insurance Carrier, Policy Number, Employer Name. E. This section to be completed by provider, please check appropriate boxes and indicate applicable charges: Diagnosis: V720 Date of Exam, New Patient 92002 92004, Established Patient 92012 92014, Refraction 92015 92310.

Vision Care Providers, make sure you have indicated the patient's diagnosis, date of service, and circled the appropriate procedure codes in Section E prior to submitting this claim.

F. Assignment of benefits

Vision Claim Transmittal example filled out, f. Assignment of benefits

In F. Assignment of Benefits, sign only if you want UnitedHealthcare to pay benefits directly to the provider of vision service: Patient Signature, Member Signature and Date. Employee ID No. is not one of the lines of F.

Common questions about Vision Claim Transmittal

Where do I file it?

Make sure form is completely filled out and mail only this form to the address on the form. Please do not attach any receipts or bills to this form.

Sources

[1] Vision Claim Transmittal, UnitedHealthcare claim form (the Official source link on this page).

Please rate Vision Claim Transmittal Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .