

Workers' Compensation Case Intake Form at a glance
What it is: The Workers' Compensation Case Intake Form (Rev 11/13) of the Professional Liability Fund.
A filled-in Workers' Compensation Case Intake Form example: a paralegal opens a client file

How to fill out Workers' Compensation Case Intake Form, box by box
Client information
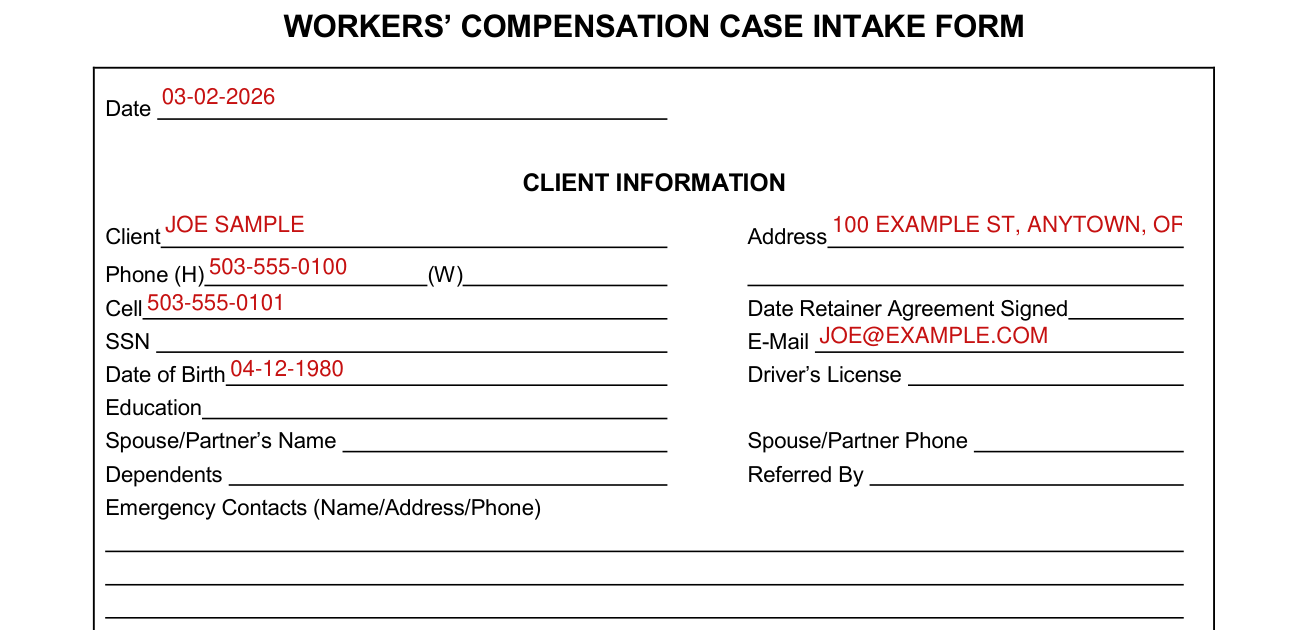
Enter the Date, then under CLIENT INFORMATION enter the Client and the Address.
Enter Phone (H) (W) and Cell, and the Date Retainer Agreement Signed.
Enter SSN, E-Mail, Date of Birth, Driver's License, Education, Spouse/Partner's Name and Spouse/Partner Phone.
Enter Dependents and Referred By, then Emergency Contacts (Name/Address/Phone).
Primary employer

Under EMPLOYMENT/INSURANCE/UNION MEMBERSHIP, enter the Primary Employer, its Address and the Wage.
Enter the Insurer, Adjuster, Address, Claim No. and Telephone.
Mark Managed Care Organization Yes or No, enter the Policy No., and enter the Date for: When was the comp insurer notified of the claim being filed?
Enter Date of Hire, Occupation, Currently Working, Scheduled Days Off and Wage Loss Paid.
Secondary employer

If there is a Secondary Employer, enter it and its Address, then the Wage, Insurer and Adjuster.
Mark Managed Care Organization Yes or No with the Policy No., and enter Address, Claim No. and Telephone.
Enter the Date for: When was the comp insurer notified of the claim being filed? Mark Yes or No for: Has documentation of the wage at the secondary job been obtained?
Enter Wage Loss Paid, Currently Working, Scheduled Days Off, Occupation and Date of Hire.
Carriers and union membership

Mark Non-Industrial Carrier Yes or No, then enter the Policy No., the Carrier and the Carrier Address.
Mark Private Health Carrier (if any) Yes or No, then enter the Policy No., the Carrier and the Address.
Mark Union Membership Yes or No, then enter the Local No. and the Union Name.
Injury and prior claims
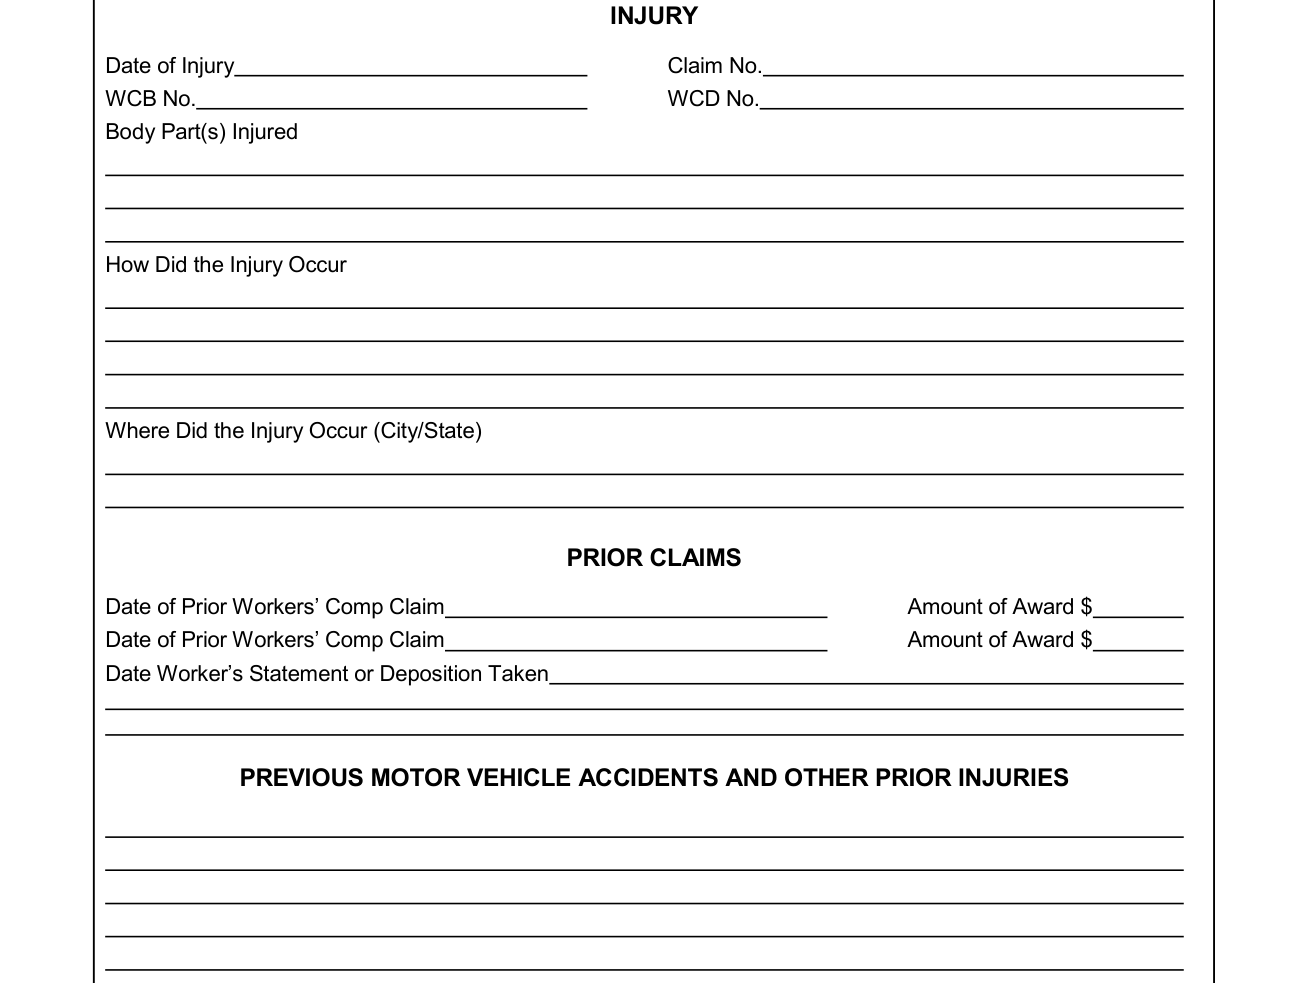
Under INJURY, enter the Date of Injury, Claim No., WCB No. and WCD No.
Enter the Body Part(s) Injured, How Did the Injury Occur and Where Did the Injury Occur (City/State).
Under PRIOR CLAIMS, enter the Date of Prior Workers' Comp Claim and the Amount of Award $.
Enter the Date Worker's Statement or Deposition Taken, then the previous motor vehicle accidents and other prior injuries.
Medical conditions, arrests and mental health
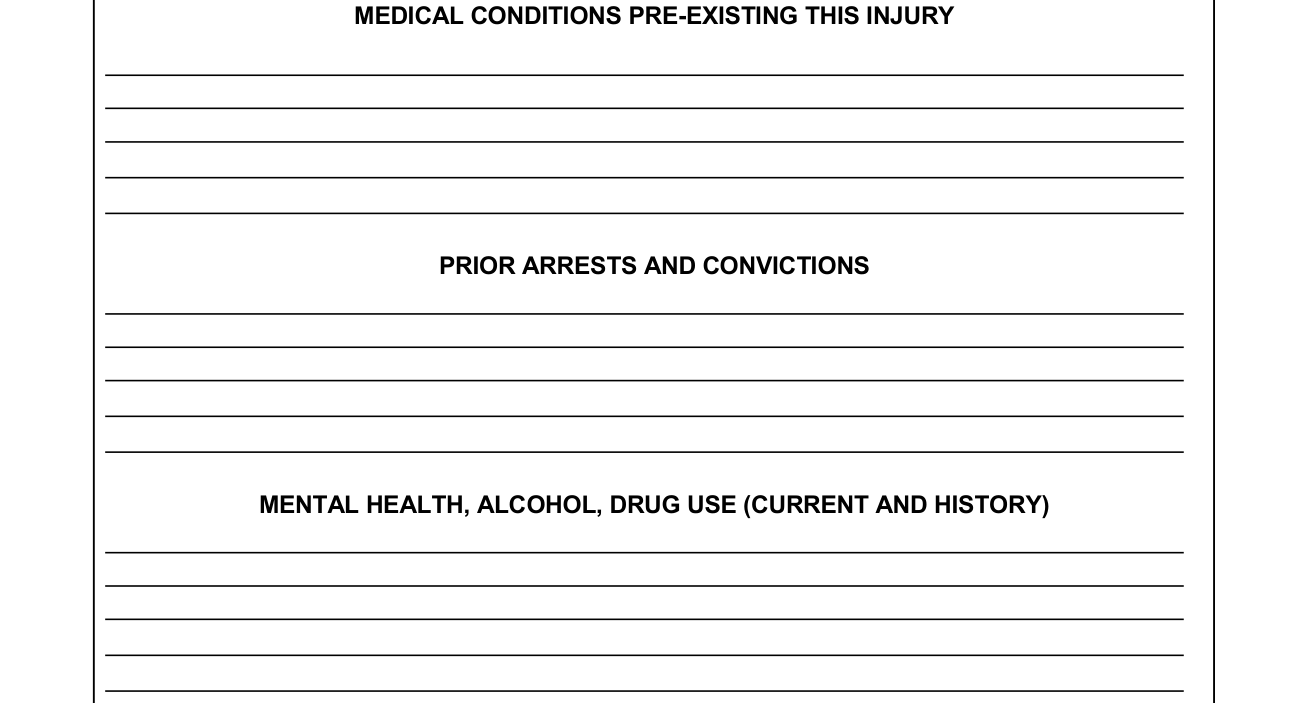
Enter medical conditions pre-existing this injury, prior arrests and convictions and mental health, alcohol, drug use (current and history).
Deadlines to calendar
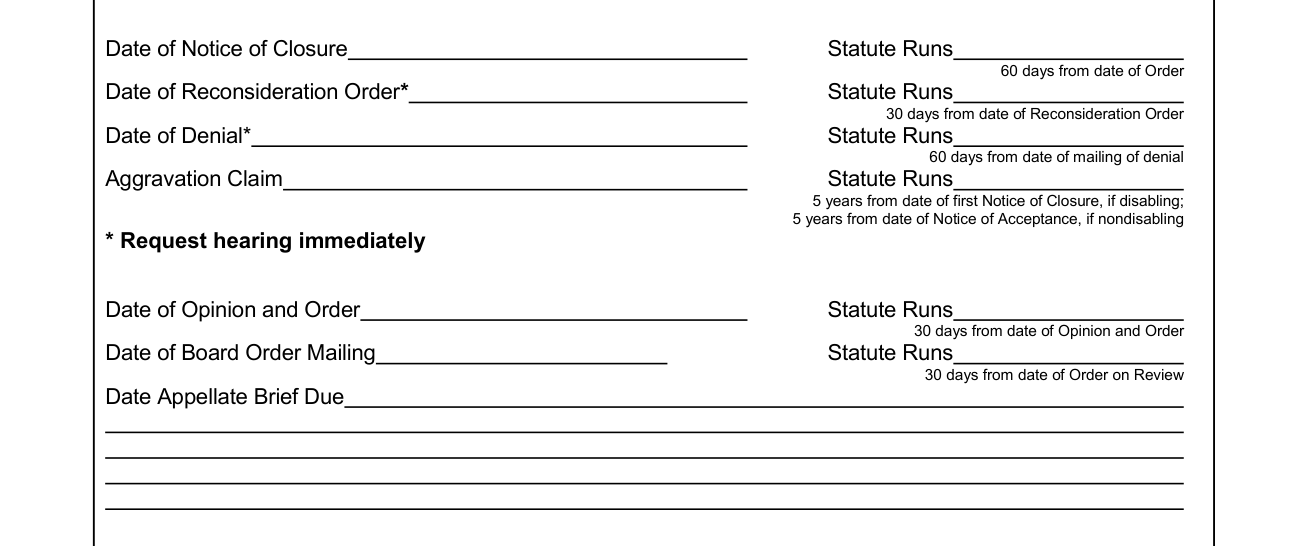
Under DEADLINES TO CALENDAR, for the Date of Notice of Closure the Statute Runs 60 days from date of Order. For the Date of Reconsideration Order* the Statute Runs 30 days from date of Reconsideration Order, and for the Date of Denial* 60 days from date of mailing of denial; * Request hearing immediately. For an Aggravation Claim the Statute Runs 5 years from date of first Notice of Closure, if disabling; 5 years from date of Notice of Acceptance, if nondisabling. For the Date of Opinion and Order the Statute Runs 30 days from date of Opinion and Order; for the Date of Board Order Mailing, 30 days from date of Order on Review; then enter the Date Appellate Brief Due.
Demand letter, hearing and review dates
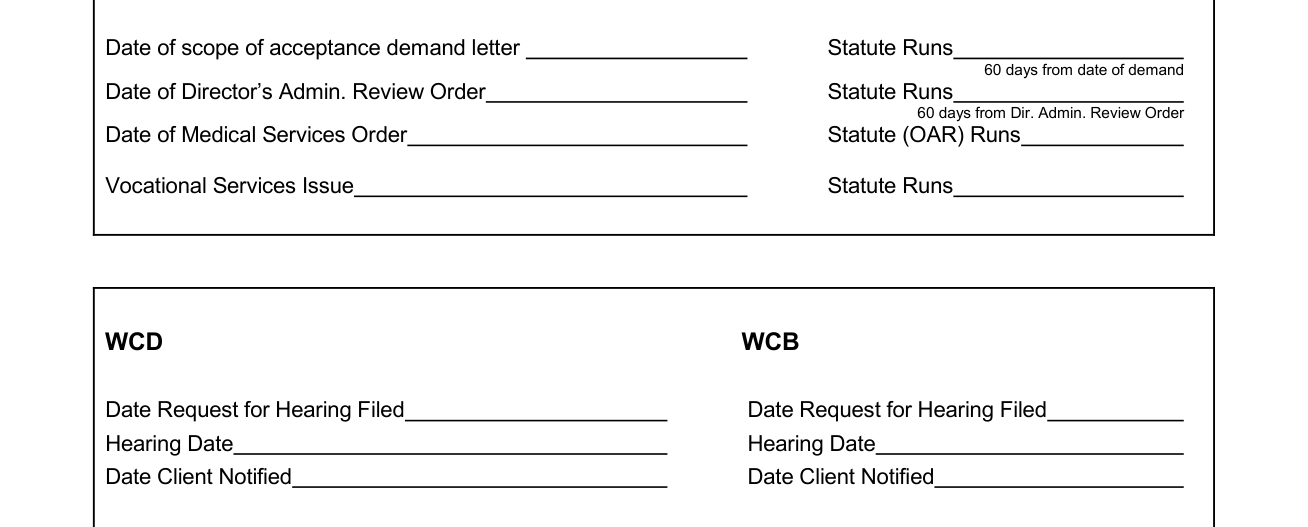
For the Date of scope of acceptance demand letter, the Statute Runs 60 days from date of demand. For the Date of Director's Admin. Review Order, the Statute Runs 60 days from Dir. Admin. Review Order; then enter the Date of Medical Services Order with its Statute (OAR) Runs, and the Vocational Services Issue with its Statute Runs.
Enter the Date Request for Hearing Filed, the Hearing Date and the Date Client Notified.
Lien items, physicians and records
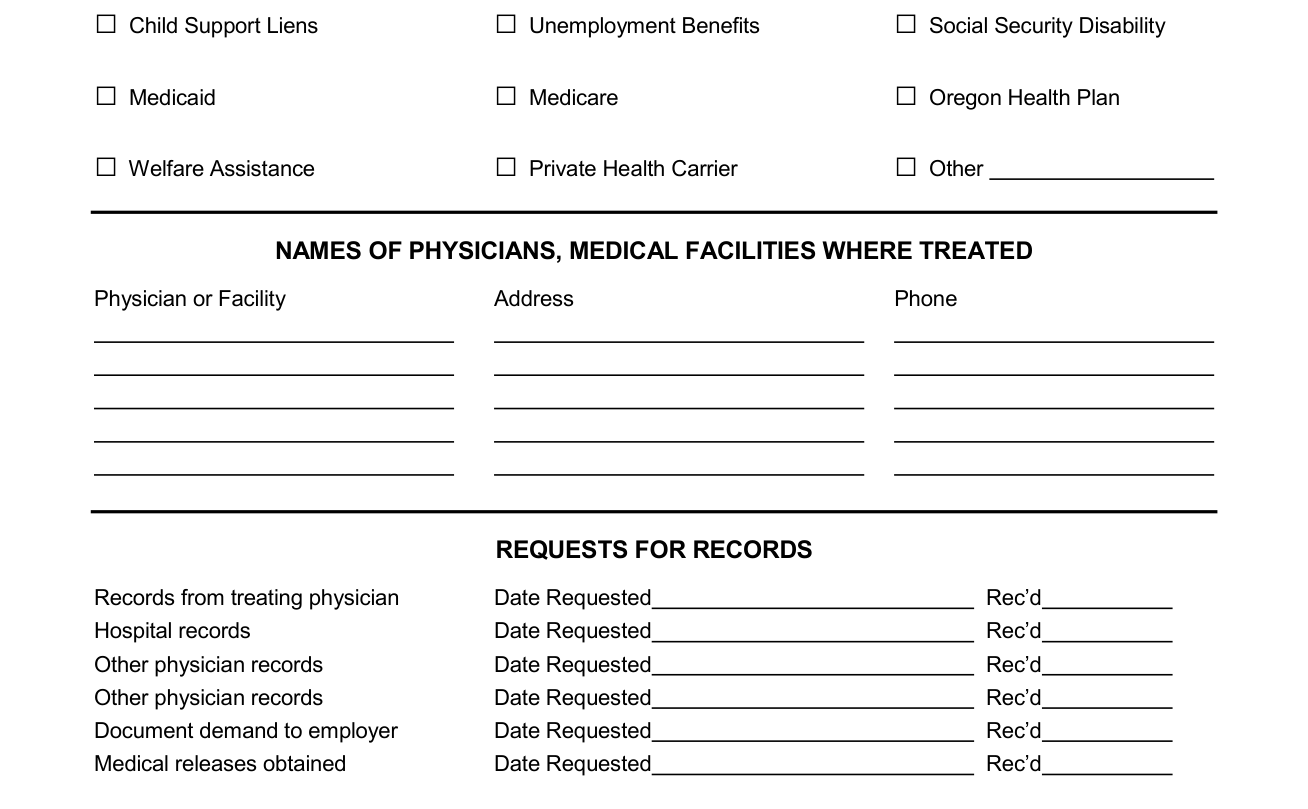
Under LIEN ITEMS, mark Child Support Liens, Unemployment Benefits, Social Security Disability, Medicaid, Medicare, Oregon Health Plan, Welfare Assistance, Private Health Carrier or Other.
Under NAMES OF PHYSICIANS, MEDICAL FACILITIES WHERE TREATED, enter the Physician or Facility, Address and Phone.
Under REQUESTS FOR RECORDS, enter the Date Requested and Rec'd for Records from treating physician, Hospital records, Other physician records, Document demand to employer and Medical releases obtained.
Third party responsibility and witnesses

Under THIRD PARTY RESPONSIBILITY, enter the Third Party Potential, Potentially Responsible Party, Theory of Liability, SOL and Notes.
Under WITNESSES, enter the Name, Address and Telephone, and mark Interviewed or Subpoenaed.
Sources
[1] Workers' Compensation Case Intake Form (Rev 11/13), Professional Liability Fund (the Official source link on this page).
