
Updated:
Get Form Now
SSA Form SSA-3373-BK, known as the “Function Report – Adult,” is a comprehensive questionnaire used by the Social Security Administration (SSA) to assess the everyday functioning of individuals applying for disability benefits. This form is filled out by the disability applicant themselves and provides the SSA with detailed insights into how an applicant’s condition affects their ability to perform daily activities, manage personal care, and maintain social interactions. It is an essential part of the disability determination process, helping the SSA gauge the severity of the disability and its impact on the applicant’s life, particularly in relation to their capacity for work.
The form covers a wide range of topics, including the applicant’s ability to perform tasks such as cooking, cleaning, shopping, and managing money. It also delves into the individual’s ability to walk, sit, lift, and use public transportation, among other physical functions. Additionally, SSA Form SSA-3373-BK explores mental and emotional health by asking about memory, concentration, handling stress, and changes in social behavior.
Other SSA Forms
Should you wish to check out more SSA documents that you can edit and fill out online, listed here are a number of the more popular forms among our users. Moreover, do not forget that you may upload, fill out, and edit any PDF at FormsPal.
What it is: Function Report - Adult, Form SSA-3373-BK: how your illnesses, injuries, or conditions limit your activities.
Who signs: Give the name and address of the person completing this form on Page 10: Name of person completing this form (Please print), Date (MM/DD/YYYY), Email address (optional), Address (Number and Street), City, State, ZIP Code.
The information that you give on this form will be used by the office that makes the disability decision on your disability claim. Complete as much of the form as you can.


In 1, enter the Name of disabled person (First, Middle Initial, Last); in 2, enter the Social Security number. In 3, give your daytime telephone number, Area Code and Phone Number. If there is no telephone number where you can be reached, give a daytime number where Social Security can leave a message for you. Check Your Number, Message Number, or None.
In 4a, where do you live? Check one: House, Apartment, Boarding House, Nursing Home, Shelter, Group Home, or Other (What?).
With whom do you live? Check one: Alone, With Family, With Friends, or Other (Describe relationship.).

In 5, say how your illnesses, injuries, or conditions limit your ability to work.
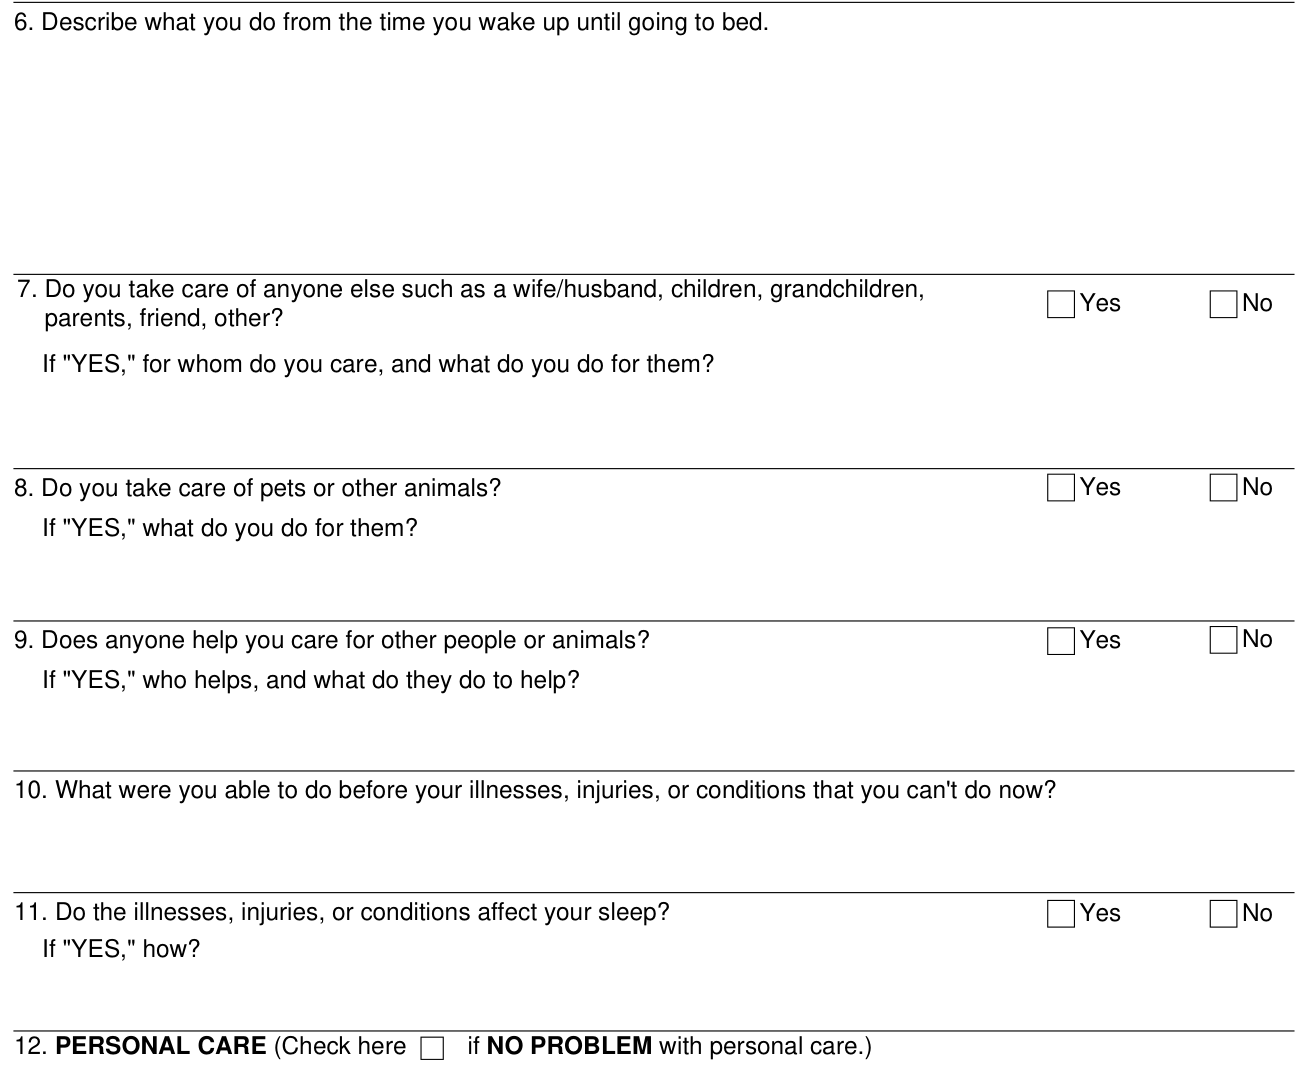
In 6, describe what you do from the time you wake up until going to bed.
Do you take care of anyone else such as a wife/husband, children, grandchildren, parents, friend, other? Mark Yes or No. If "YES," say for whom you care, and what you do for them.
Do you take care of pets or other animals? Mark Yes or No. If "YES," say what you do for them.
Does anyone help you care for other people or animals? Mark Yes or No. If "YES," say who helps, and what they do to help.
Do the illnesses, injuries, or conditions affect your sleep? Mark Yes or No. If "YES," say how.
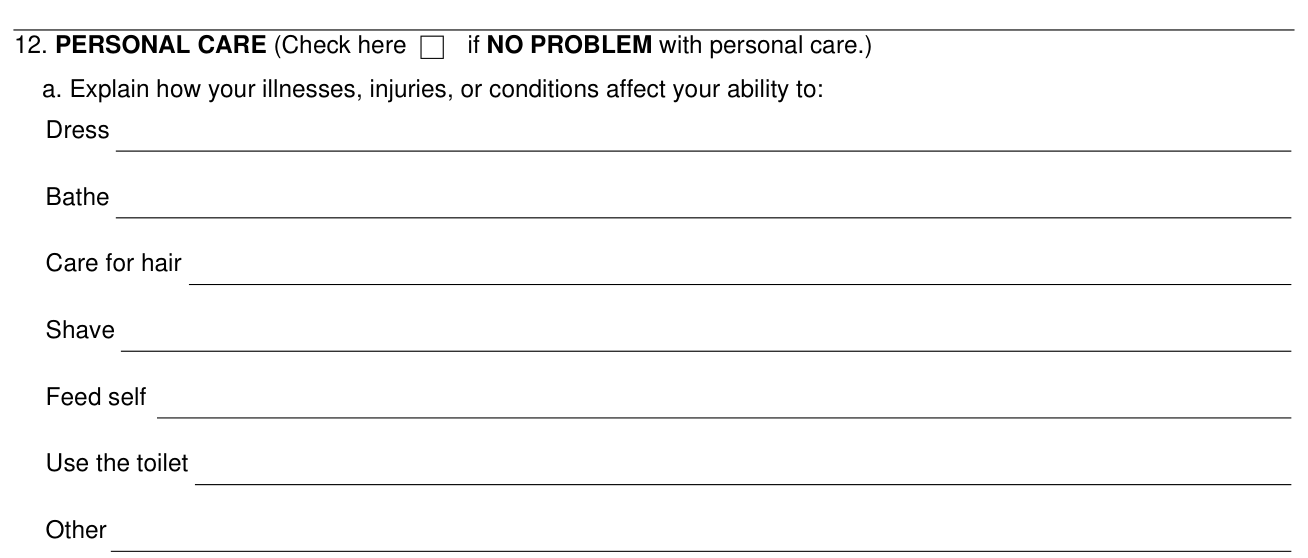
In 12, check the box if there is NO PROBLEM with personal care.
Explain how your illnesses, injuries, or conditions affect your ability to: Dress, Bathe, Care for hair, Shave, Feed self, Use the toilet, Other.
Do you need any special reminders to take care of personal needs and grooming? Mark Yes or No. If "YES," say what type of help or reminders are needed.
Do you need help or reminders taking medicine? Mark Yes or No. If "YES," say what kind of help you need.

In 13a, do you prepare your own meals? Mark Yes or No. If "Yes," say what kind of food you prepare.
If "No," explain why you cannot or do not prepare meals.
Do you need help or encouragement doing these things? Mark Yes or No. If "YES," say what help is needed.
If you don't do house or yard work, explain why not.

In 15a, say how often you go outside. If you don't go out at all, explain why not.
When going out, how do you travel? Check all that apply: Walk, Drive a car, Ride in a car, Ride a bicycle, Use public transportation, or Other (Explain).
When going out, can you go out alone? Mark Yes or No. If "NO," explain why you can't go out alone.
Do you drive? Mark Yes or No. If you don't drive, explain why not.
In 16a, if you do any shopping, do you shop: (Check all that apply.) In stores, By phone, By mail, By computer, or None.
In 17a, are you able to: Pay bills, Handle a savings account, Count change, Use a checkbook/money orders? Mark Yes or No. Explain all "NO" answers.
Has your ability to handle money changed since the illnesses, injuries, or conditions began? Mark Yes or No. If "YES," explain how the ability to handle money has changed.

In 18a, say what your hobbies and interests are (for example, reading, watching TV, sewing, playing sports, etc.).
How do you spend time with others? (Check all that apply.) In person, On the phone, Email, Texting, Mail, Video Chat (for example Skype or Facetime), or Other (Explain).
Do you need to be reminded to go places? Mark Yes or No. Do you need someone to accompany you? Mark Yes or No. If "YES", explain.
Describe any changes in social activities since the illnesses, injuries, or conditions began.
Do you have any problems getting along with family, friends, neighbors, or others? Mark Yes or No. If "YES," explain.

In 20a, check any of the following items that your illnesses, injuries, or conditions affect: Lifting, Walking, Stair Climbing, Understanding, Squatting, Sitting, Seeing, Following Instructions, Bending, Kneeling, Memory, Using Hands, Standing, Talking, Completing Tasks, Getting Along With Others, Reaching, Hearing, Concentration. Please explain how your illnesses, injuries, or conditions affect each of the items you checked (for example, you can only lift (how many pounds), or you can only walk (how far)).
Check Right Handed or Left Handed.
How far can you walk before needing to stop and rest? If you have to rest, how long before you can resume walking?
For how long can you pay attention? Do you finish what you start (for example, a conversation, chores, reading, watching a movie)? Mark Yes or No.
Have you ever been fired or laid off from a job because of problems getting along with other people? Mark Yes or No. If "YES," please explain, and if "YES," give the name of employer.
Have you noticed any unusual behavior or fears? Mark Yes or No. If "YES," please explain.

In 21, do you use any of the following? (Check all that apply.) Crutches, Cane, Hearing Aid, None, Walker, Brace/Splint, Glasses/Contact Lenses, Wheelchair, Artificial Limb, Artificial Voice Box, Other (Explain).
Also say which of these were prescribed by a doctor, when it was prescribed, and when you need to use these aids.
In 22, do you currently take any medicines for your illnesses, injuries, or conditions? Mark Yes or No. If "YES," do any of your medicines cause side effects? Mark Yes or No. If "YES," please explain: do not list all of the medicines that you take, list only the medicines that cause side effects, under NAME OF MEDICINE and SIDE EFFECTS YOU HAVE.
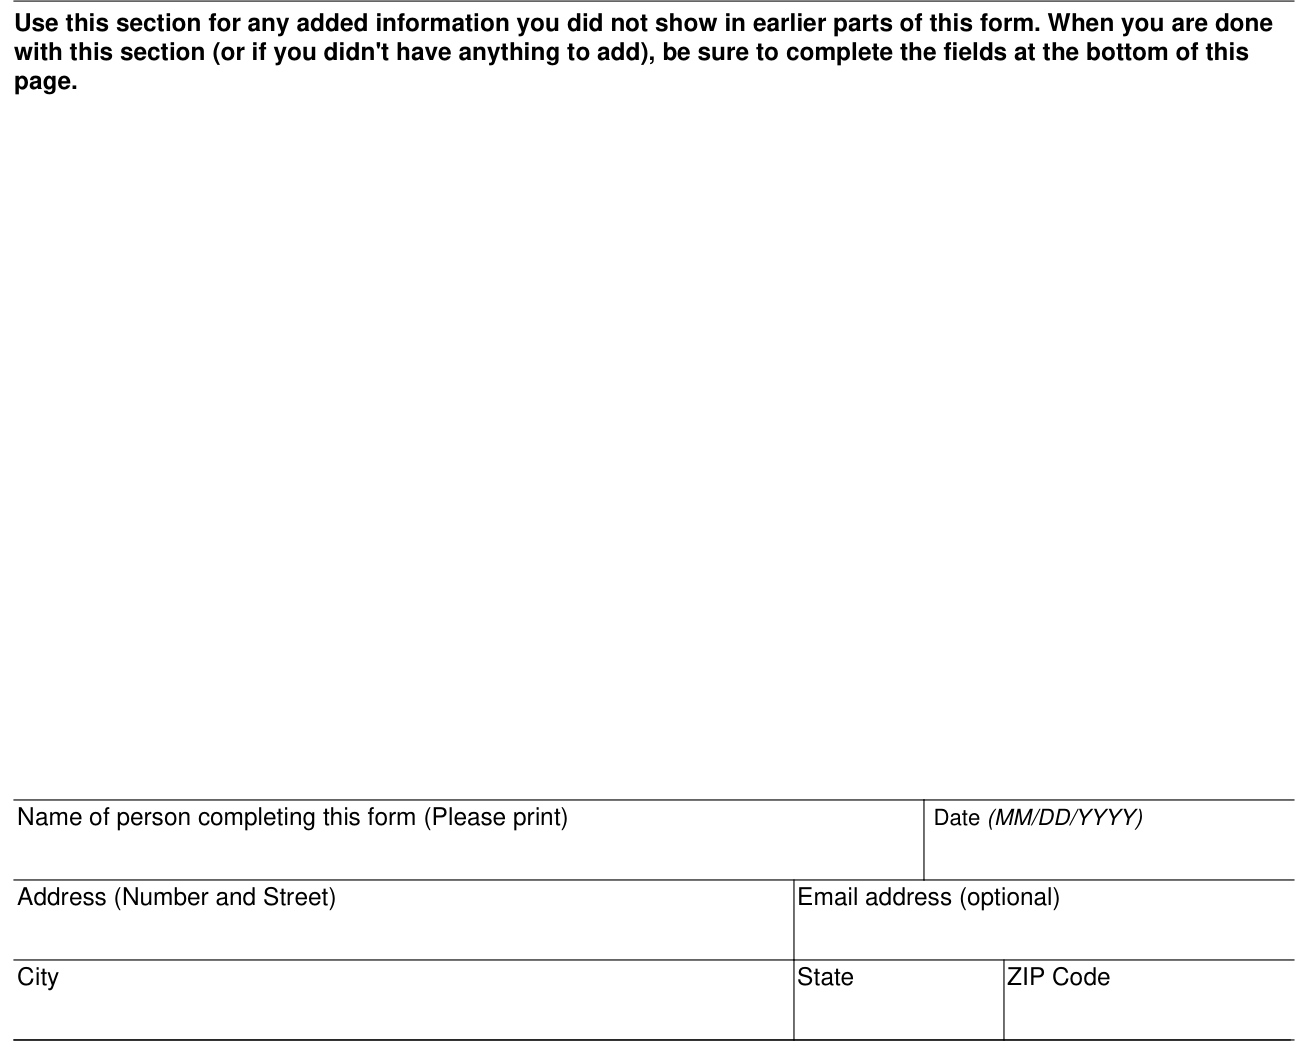
Section E - Remarks: use this section for any added information you did not show in earlier parts of this form. When you are done with this section (or if you didn't have anything to add), be sure to complete the fields at the bottom of the page, in the Who signs row.
Please remove this sheet before returning the completed form.
For SSA Use Only. Do not write in this box.
Read all of this information before you begin completing this form. Print or type. DO NOT LEAVE ANSWERS BLANK. If you do not know the answer or the answer is "none" or "does not apply," write "don't know" or "none" or "does not apply." Do not ask a doctor or hospital to complete this form. Be sure to explain an answer if the question asks for an explanation, or if you think you need to explain an answer. If more space is needed to answer any questions, use the "REMARKS" section on Page 10, and show the number of the question being answered. If a specific activity is performed with the help of others, indicate that.
Send or bring the completed form to your local Social Security office. You can find your local Social Security office through SSA's website at www.socialsecurity.gov. Offices are also listed under U.S. Government agencies in your telephone directory, or you may call Social Security at 1-800-772-1213 (TTY 1-800-325-0778).
Anyone who makes or causes to be made a false statement or representation of material fact for use in determining a payment under the Social Security Act, or knowingly conceals or fails to disclose an event with an intent to affect an initial or continued right to payment, commits a crime punishable under Federal law by fine, imprisonment, or both, and may be subject to administrative sanctions.
If you need help with this form, complete as much of it as you can and call the phone number provided on the letter sent with the form, or contact the person who asked you to complete the form.
[1] Form SSA-3373-BK (08-2026), Function Report - Adult, Social Security Administration (the Official source link on this page).