

Access NY Supplement A (DOH-4495A) at a glance
What it is: Access NY Supplement A is completed if anyone applying is age 65 or older, certified blind or disabled, not certified disabled but chronically ill, or institutionalized and applying for coverage of nursing home care.
Who signs: Signature of applicant/representative and Signature of applicant's spouse, each with a Date signed.
Complete this Supplement if anyone who is applying is age 65 or older, certified blind or certified disabled (of any age), not certified disabled but chronically ill, or institutionalized and applying for coverage of nursing home care, which includes care in a hospital that is equivalent to nursing home care.
What to bring and attach to Access NY Supplement A (DOH-4495A)
In 5, Trust Accounts: if you and/or your spouse created or are the beneficiary of a trust, submit a copy of the trust, including the schedule of trust assets.
If yes to H 3 (a deposit given to any health care or residential facility, such as a nursing home), send copy of agreement.
A filled-in Access NY Supplement A (DOH-4495A) example: a 70-year-old completes the Supplement for herself
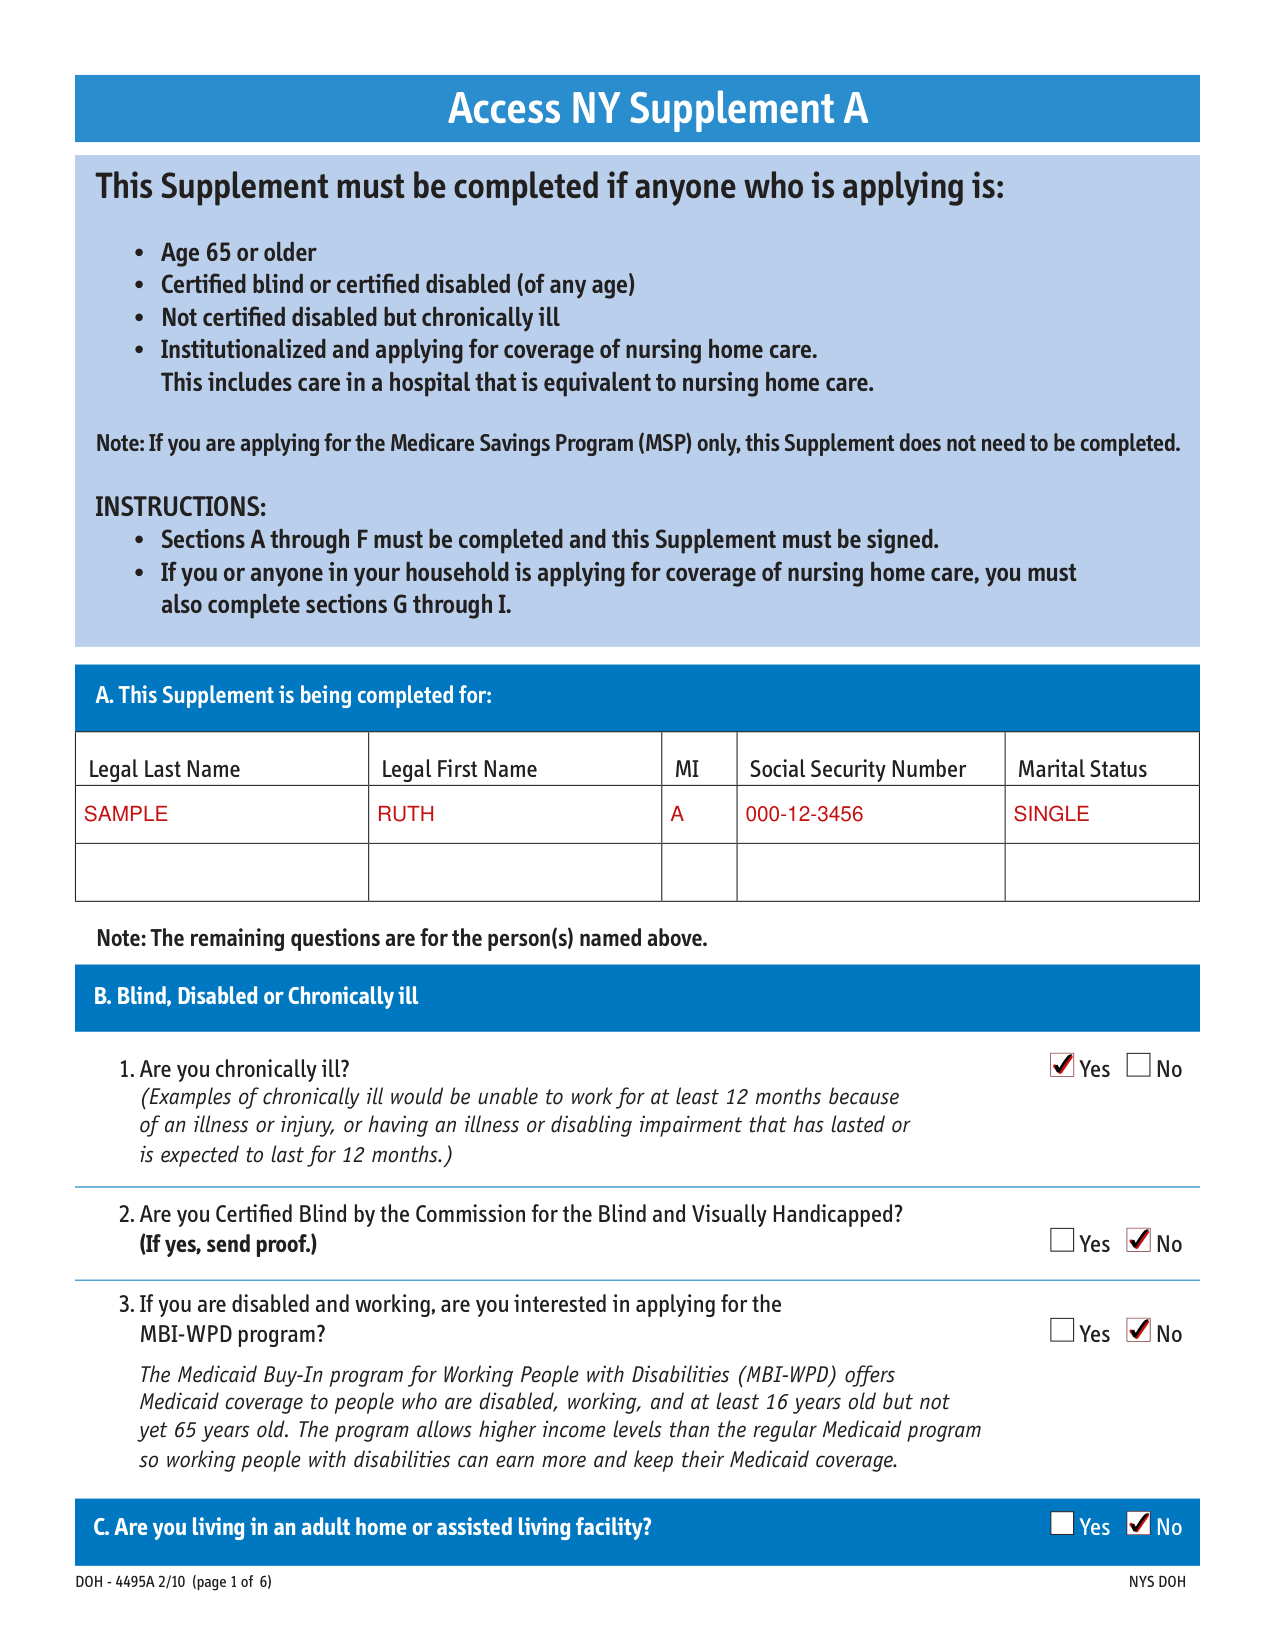
How to fill out Access NY Supplement A (DOH-4495A), box by box
A. This Supplement is being completed for
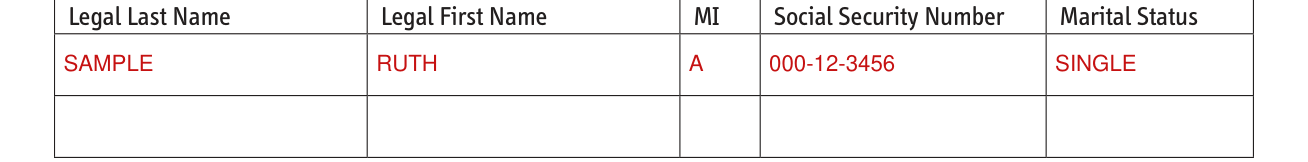
Under A, enter Legal Last Name, Legal First Name, MI, Social Security Number and Marital Status for the person for whom this Supplement is being completed. The remaining questions are for the person(s) named.
B. Blind, Disabled or Chronically ill

In B, mark Yes or No to 1. Are you chronically ill? Examples of chronically ill would be unable to work for at least 12 months because of an illness or injury, or having an illness or disabling impairment that has lasted or is expected to last for 12 months.
In B, mark Yes or No to 2. Are you Certified Blind by the Commission for the Blind and Visually Handicapped? If yes, send proof.
In B, mark Yes or No to 3. If you are disabled and working, are you interested in applying for the MBI-WPD program? The program offers Medicaid coverage to people who are disabled, working, and at least 16 years old but not yet 65 years old.
C. Are you living in an adult home or assisted living facility?

In C, mark Yes or No to Are you living in an adult home or assisted living facility?
More rules for Access NY Supplement A (DOH-4495A)
Sections A through F must be completed and this Supplement must be signed. If you or anyone in your household is applying for coverage of nursing home care, you must also complete sections G through I.
If your situation is different
You are listing resources in D
In D, check the box that applies. If you are applying for Medicaid coverage but not coverage of community-based long-term care services, you may attest to the amount of your resources and you are not required to submit documentation of your resources.
If you are applying for coverage of community-based long-term care services, you must submit documentation of the current amount of your resources.
If you are institutionalized and applying for coverage of nursing home care, you must submit documentation of your resources back to February 1, 2006, or the past 60 months, whichever is less.
List all resources owned by you and/or your spouse/parent(s), including custodial accounts. If applying for coverage of nursing home care, also list any accounts closed since February 1, 2006, or in the past 60 months, whichever period is shorter; include balance at closing and provide an explanation of where the balance was transferred to or how it was spent.
On a separate sheet of paper, provide an explanation of each transaction of $2,000 or more. (checked November 7, 2026)
In 1, Checking/Savings/Credit Union Accounts/Certificates of Deposits (CDs), enter Bank Name and Account Number, Name of Owner(s), Current Dollar Amount and Closed Account Balance/ Date Closed.
In 2, Retirement Accounts (Deferred Compensation, IRA and/or Keogh), enter Account Number, Name of Owner(s), Type/Institution and Current Dollar Amount, and mark Pay Out Yes or No.
In 3, Life Insurance Policies, enter Insurance Company, Policy Number, Name of Owner(s), Cash Value and Face Value.
In 4, Annuities, Stocks, Bonds, Mutual Funds, enter Name of Owner(s), Company, Date Purchased and Value.
For each trust, enter Name of Trust, Grantor, Trustee(s), Assets, Beneficiary and Income.
In 6, Burial Assets/Burial Contracts, include copies and mark Yes or No to each: Do you and/or your spouse have a pre-paid funeral agreement for you or anyone else in your family? Do you and/or your spouse have a burial space or plot for you or anyone else in your family? Do you and/or your spouse have money in a bank account set aside for a burial fund?
In 7, Vehicle(s), list all cars, trucks and vans. List all recreational vehicles, including campers, snowmobiles, boats and motorcycles. For each, enter Name of Owner(s), Year/Make/Model, Fair-Market Value and Amount Owed, and mark In Use Yes or No.
In 8, Equity Value in Home, if you own your home, enter the equity value in your home. Equity value is the fair market value less any outstanding liens, mortgages, etc.
In 9, List Any Other Resources, enter Resource Type, Name of Owner(s) and Value.
You own other real property
In E, Real Property (other than your home), mark Yes or No: Do you and/or your spouse own or have a legal interest in any other real property? If yes, check any that apply: Rental Property, Vacation Property, Time Share, Vacant Land or Other Property Rights (In or outside of New York State).
You own or have a legal interest in your home
In F, Homestead, mark Yes or No to 1. Do you and/or your spouse own or have a legal interest in your home, including a life estate? Mark Yes or No to 2. If you are in a medical facility and own your home, do you intend to return to your home?
Mark Yes or No to 3. If no, is anyone living in the home? Enter who is living in the home and how this person is related to you and/or your spouse. If you and/or your spouse's child (of any age) is living in the home, is the child disabled? Mark Yes or No.
You or anyone in your household is applying for coverage of nursing home care
Stop here unless you or anyone in your household is institutionalized and applying for coverage of nursing home care. However, the last page of this document must be signed.
In G, enter Name of Facility, Date Admitted and Telephone Number, then Street Address, City, State and Zip, and then the Applicant's Previous Address, City, State and Zip.
In H, mark Yes or No: Did you, your spouse, or someone on your behalf transfer, change ownership in, give away, or sell any assets, including your home or other real property?
Mark Yes or No: Are you in the process of selling property?
Mark Yes or No: Did you, your spouse or someone on your behalf, change the deed or the ownership of any real property, including creating a life estate? If yes, when?
Mark Yes or No: If you purchased a life estate in another person's home, did you live in the home for at least one year after you purchased the life estate?
Mark Yes or No: Did you, your spouse, or someone on your behalf purchase a mortgage, loan, or promissory note? If yes, when?
Mark Yes or No: Did you, your spouse, or someone on your behalf purchase or change an annuity? If yes, when?
Mark Yes or No to 2. In the last 60 months, have you or your spouse created or transferred any assets into or out of a trust?
If you answered yes to any of the questions in H, explain the transfer(s) with Description of Asset (including income), Date of Transfer, Transferred to Whom and Amount of Transfer. Attach additional sheets of paper, if needed.
In H, mark Yes or No to 3. Have you, your spouse, or someone acting on your behalf given a deposit to any health care or residential facility, such as a nursing home, assisted living facility, continuing care retirement community or life care community?
In I, Tax Returns, mark Yes or No: Did you and/or your spouse file U.S. income tax returns in the last four years? If yes, send copies of these returns.
Signature of applicant/representative and Signature of applicant's spouse
Signing certifies, under penalty of perjury, that the information on this form is correct and complete to the best of your knowledge, and that you understand you must report any changes in this information within 10 days of the change.
Sign on the Signature of applicant/representative line and enter the Date signed. Sign on the Signature of applicant's spouse line and enter the Date signed.
Common questions about Access NY Supplement A (DOH-4495A)
When is this form not the right one?
If you are applying for the Medicare Savings Program (MSP) only, this Supplement does not need to be completed.
Sources
[1] Access NY Supplement A (DOH-4495A 2/10), New York State Department of Health (the Official source link on this page).