
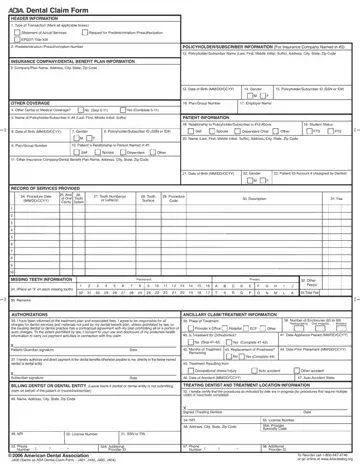
ADA Dental Claim Form J430 at a glance
What it is: Dental Claim Form J430 is the ADA form whose RECORD OF SERVICES PROVIDED lists the Procedure Date (MM/DD/CCYY).
Who signs: Under AUTHORIZATIONS, the patient or guardian signs and dates in 36 to agree to be responsible for all charges for dental services and materials not paid by the dental benefit plan, unless prohibited by law, or the treating dentist or dental practice has a contractual agreement with the plan prohibiting all or a portion of such charges. The subscriber signs and dates in 37, and in 53 the treating dentist signs and dates.
A filled-in ADA Dental Claim Form J430 example: a dental claim for one visit
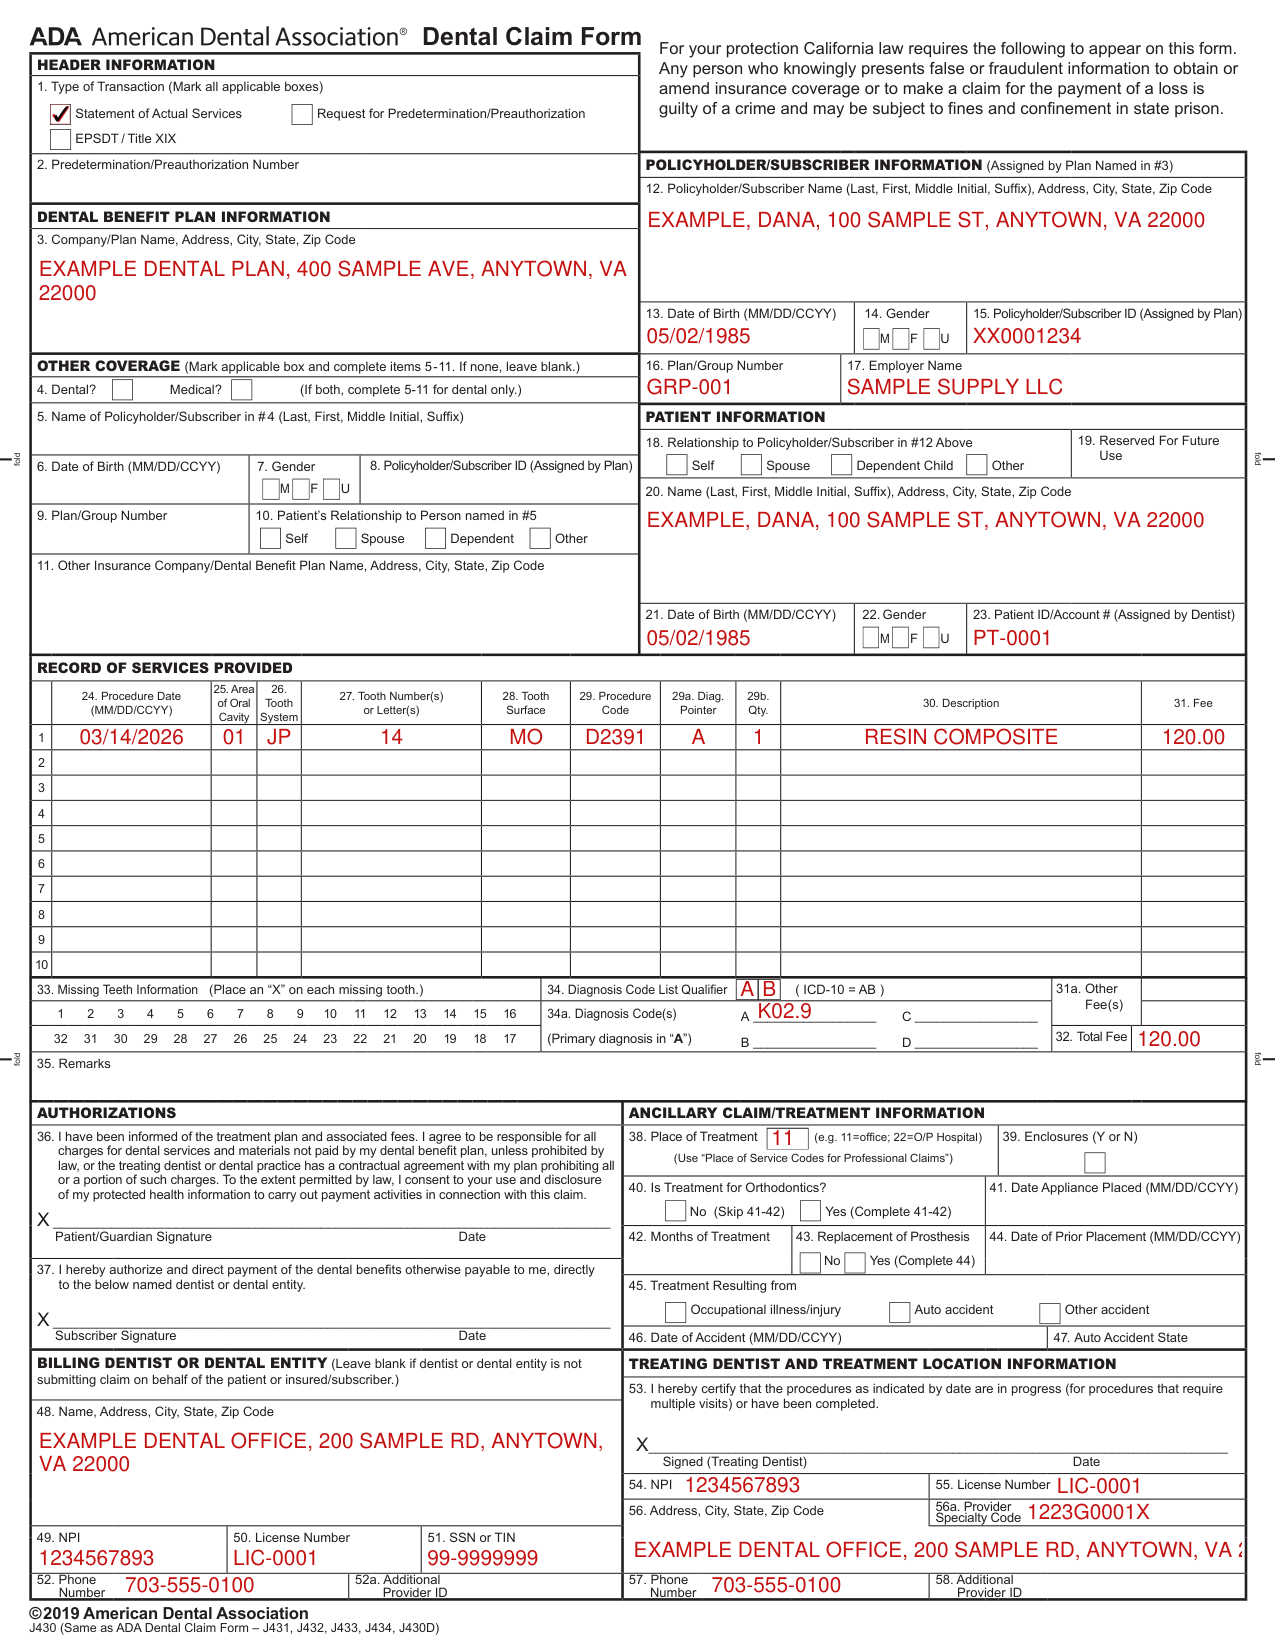
How to fill out ADA Dental Claim Form J430, box by box
Type of Transaction

In 1. Type of Transaction, mark all applicable boxes: Statement of Actual Services, Request for Predetermination/Preauthorization or EPSDT / Title XIX.
Predetermination/Preauthorization Number

Enter the Predetermination/Preauthorization Number in 2.
Dental Benefit Plan Information

Enter the Company/Plan Name, Address, City, State, Zip Code in 3. The form is designed so that the name and address (Item 3) of the third-party payer receiving the claim (insurance company/dental benefit plan) is visible in a standard #9 window envelope (window to the left).
Policyholder/Subscriber Information
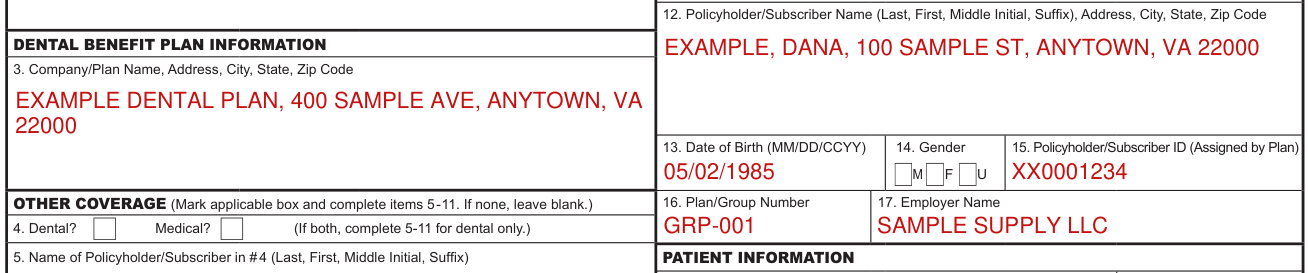
Under POLICYHOLDER/SUBSCRIBER INFORMATION (Assigned by Plan Named in #3), enter in 12 the Policyholder/Subscriber Name (Last, First, Middle Initial, Suffix), Address, City, State, Zip Code.
Enter the Date of Birth (MM/DD/CCYY) in 13 and the Policyholder/Subscriber ID (Assigned by Plan) in 15.
Mark 14. Gender: M, F or U.
Enter the Plan/Group Number in 16 and the Employer Name in 17.
Other Coverage
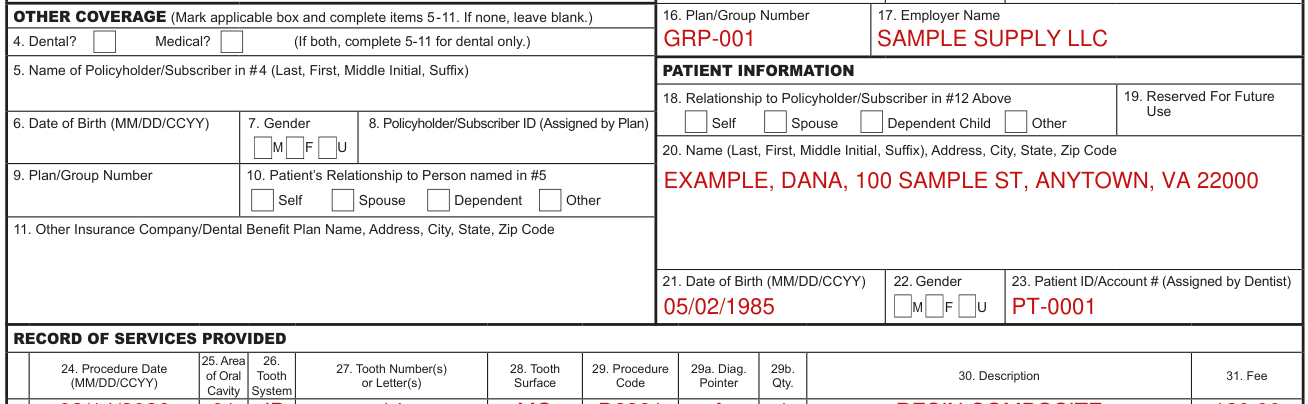
Under OTHER COVERAGE, mark applicable box and complete items 5-11. If none, leave blank. In 4, mark Dental or Medical; if both, complete 5-11 for dental only.
Enter in 5 the Name of Policyholder/Subscriber in # 4 (Last, First, Middle Initial, Suffix).
Enter the Date of Birth (MM/DD/CCYY) in 6 and the Policyholder/Subscriber ID (Assigned by Plan) in 8.
Mark 7. Gender: F, M or U.
Enter the Plan/Group Number in 9. In 10, mark the Patient's Relationship to Person named in #5: Self, Spouse, Dependent or Other.
Enter the Other Insurance Company/Dental Benefit Plan Name, Address, City, State, Zip Code in 11.
GENDER Codes (Items 7, 14 and 22) - M = Male; F = Female; U = Unknown. When a claim is being submitted to the secondary payer, complete the entire form and attach the primary payer's Explanation of Benefits (EOB) showing the amount paid by the primary payer. You may also note the primary carrier paid amount in the Remarks field (Item 35).
Patient Information
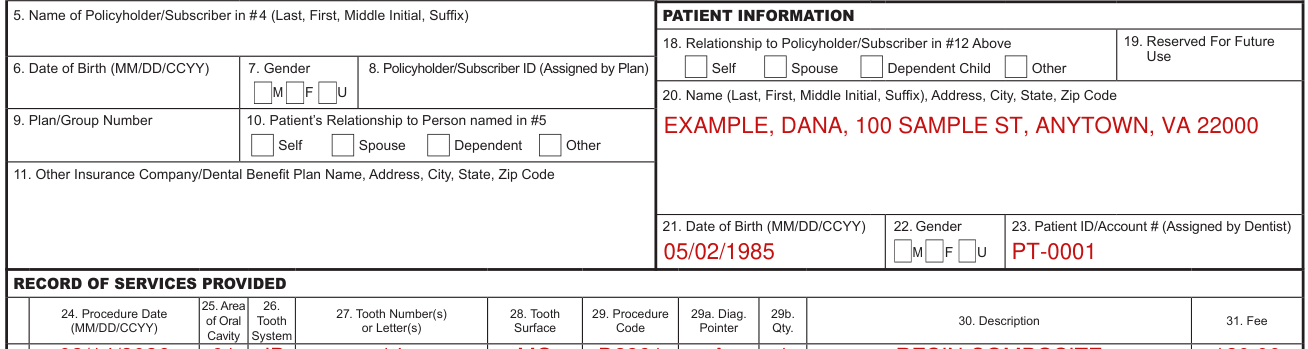
Under PATIENT INFORMATION, mark in 18 the Relationship to Policyholder/Subscriber in #12: Self, Spouse, Dependent Child or Other.
19 is Reserved For Future Use.
Enter the Name (Last, First, Middle Initial, Suffix), Address, City, State, Zip Code in 20.
Enter the Date of Birth (MM/DD/CCYY) in 21 and the Patient ID/Account # (Assigned by Dentist) in 23.
Mark 22. Gender: U, M or F.
Record of Services Provided
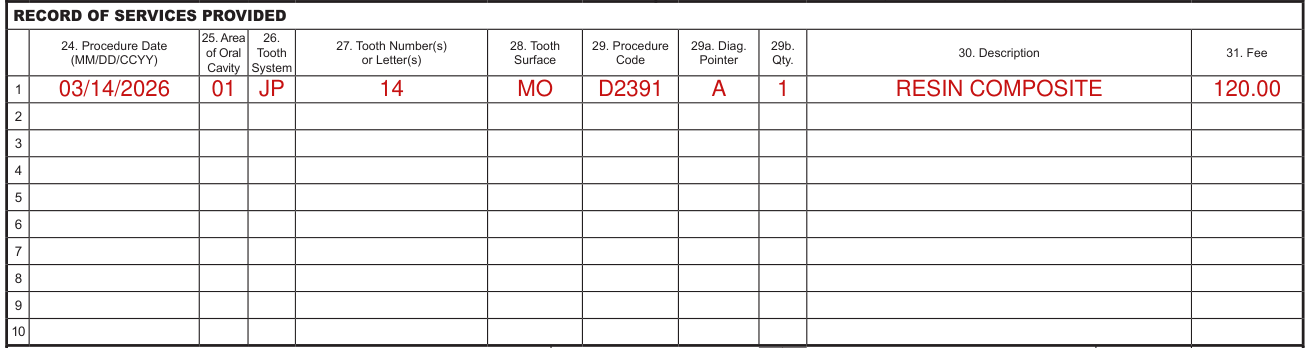
Under RECORD OF SERVICES PROVIDED, enter on each line the Procedure Date (MM/DD/CCYY) in 24, the Area of Oral Cavity in 25, the Tooth System in 26, the Tooth Number(s) or Letter(s) in 27, the Tooth Surface in 28, the Procedure Code in 29, the Diag. Pointer in 29a, the Qty. in 29b, the Description in 30 and the Fee in 31.
If the number of procedures reported exceeds the number of lines available on one claim form, list the remaining procedures on a separate, fully completed claim form.
All dates must include the four-digit year.
Diagnosis, Missing Teeth, Fees and Remarks

The form supports reporting up to four diagnosis codes per dental procedure. Diagnosis codes are linked to procedures using Item 29a - Diagnosis Code Pointer (A through D as applicable from Item 34a), Item 34 - Diagnosis Code List Qualifier (AB for ICD-10-CM) and Item 34a - Diagnosis Code(s) / A, B, C, D (up to four, with the primary adjacent to the letter A).
Under 33. Missing Teeth Information, place an X on each missing tooth. Enter the Diagnosis Code List Qualifier in 34 and the Diagnosis Code(s) in 34a, with the primary diagnosis in A.
Enter the 31a. Other Fee(s) and the 32. Total Fee.
Enter the Remarks in 35.
Authorizations and Claim/Treatment Information
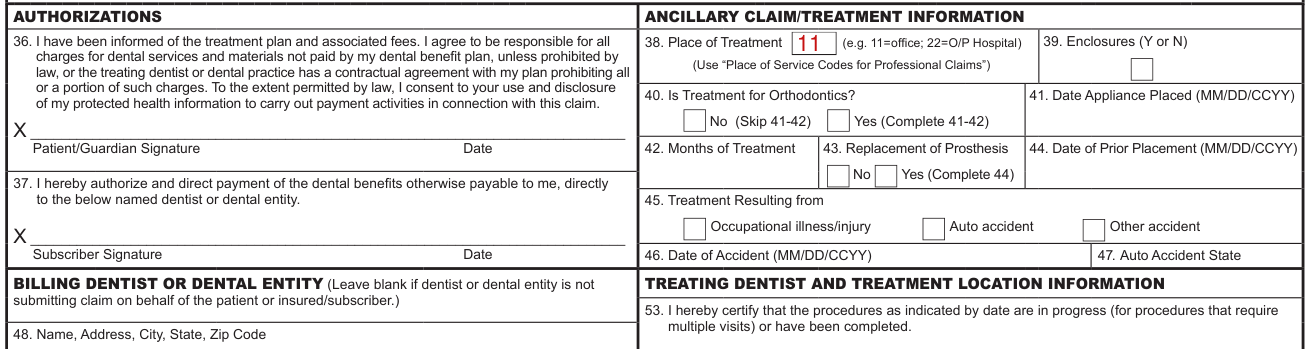
In 37, the subscriber signs and dates to authorize and direct payment of the dental benefits otherwise payable to the subscriber, directly to the named dentist or dental entity.
In 38. Place of Treatment, enter the code (e.g. 11=office; 22=O/P Hospital); use Place of Service Codes for Professional Claims.
Enter Y or N in 39. Enclosures.
In 40. Is Treatment for Orthodontics?, mark No (Skip 41-42) or Yes (Complete 41-42). Enter the Date Appliance Placed (MM/DD/CCYY) in 41 and the Months of Treatment in 42.
In 43. Replacement of Prosthesis, mark No or Yes (Complete 44). Enter the Date of Prior Placement (MM/DD/CCYY) in 44.
In 45. Treatment Resulting from, mark Occupational illness/injury, Auto accident or Other accident. Enter the Date of Accident (MM/DD/CCYY) in 46 and the Auto Accident State in 47.
Billing Dentist or Dental Entity
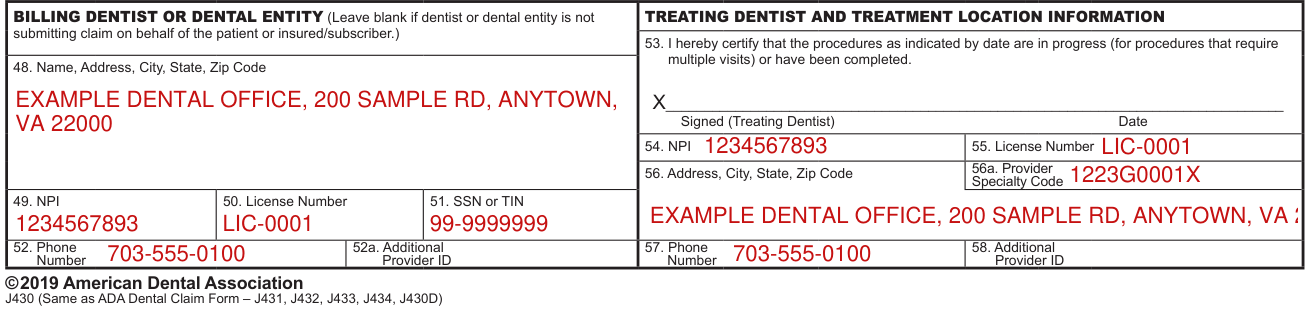
Leave BILLING DENTIST OR DENTAL ENTITY blank if dentist or dental entity is not submitting claim on behalf of the patient or insured/subscriber. Enter the Name, Address, City, State, Zip Code in 48.
Enter the NPI in 49, the License Number in 50, the SSN or TIN in 51, the Phone Number in 52 and the Additional Provider ID in 52a.
Treating Dentist and Treatment Location Information
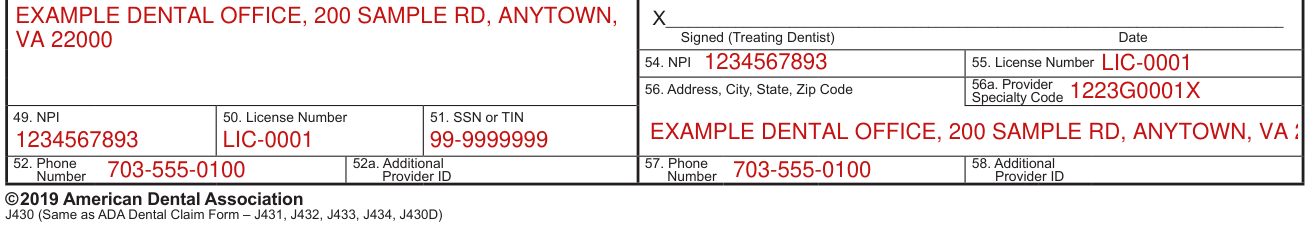
In 53, the treating dentist signs and dates the line: "I hereby certify that the procedures as indicated by date are in progress (for procedures that require multiple visits) or have been completed."
Enter the NPI in 54, the License Number in 55, the Address, City, State, Zip Code in 56, the Provider Specialty Code in 56a, the Phone Number in 57 and the Additional Provider ID in 58.
For 56a. Provider Specialty Code, the general code listed as Dentist may be used instead of any of the other codes.
More rules for ADA Dental Claim Form J430
Complete all items unless noted otherwise on the form or in the instructions posted on the ADA's web site (ADA.org).
Comprehensive ADA Dental Claim Form completion instructions are posted on the ADA's web site (https://www.ADA.org/en/publications/cdt/ada-dental-claim-form).
Common questions about ADA Dental Claim Form J430
Is there a penalty?
California law requires this form to say that any person who knowingly presents false or fraudulent information to obtain or amend insurance coverage or to make a claim for the payment of a loss is guilty of a crime and may be subject to fines and confinement in state prison.
Sources
[1] Dental Claim Form J430, American Dental Association (the served file; no issuer file found) (the Official source link on this page).
