


AHCA Form 1823 at a glance
What it is: AHCA Form 1823 is the Resident Health Assessment for Assisted Living Facilities.
Who signs: Enter Telephone Number and Address of Examiner. The examiner signs under Signature of Examiner and enters the Date of Examination.
Section 1. Health Assessment must be completed by a licensed health care provider and must include a face-to-face examination.
What to bring and attach to AHCA Form 1823
Attach a listing of all currently prescribed medications, including dosage, directions for use, and route.
A filled-in AHCA Form 1823 example: a facility and a provider fill out all three pages
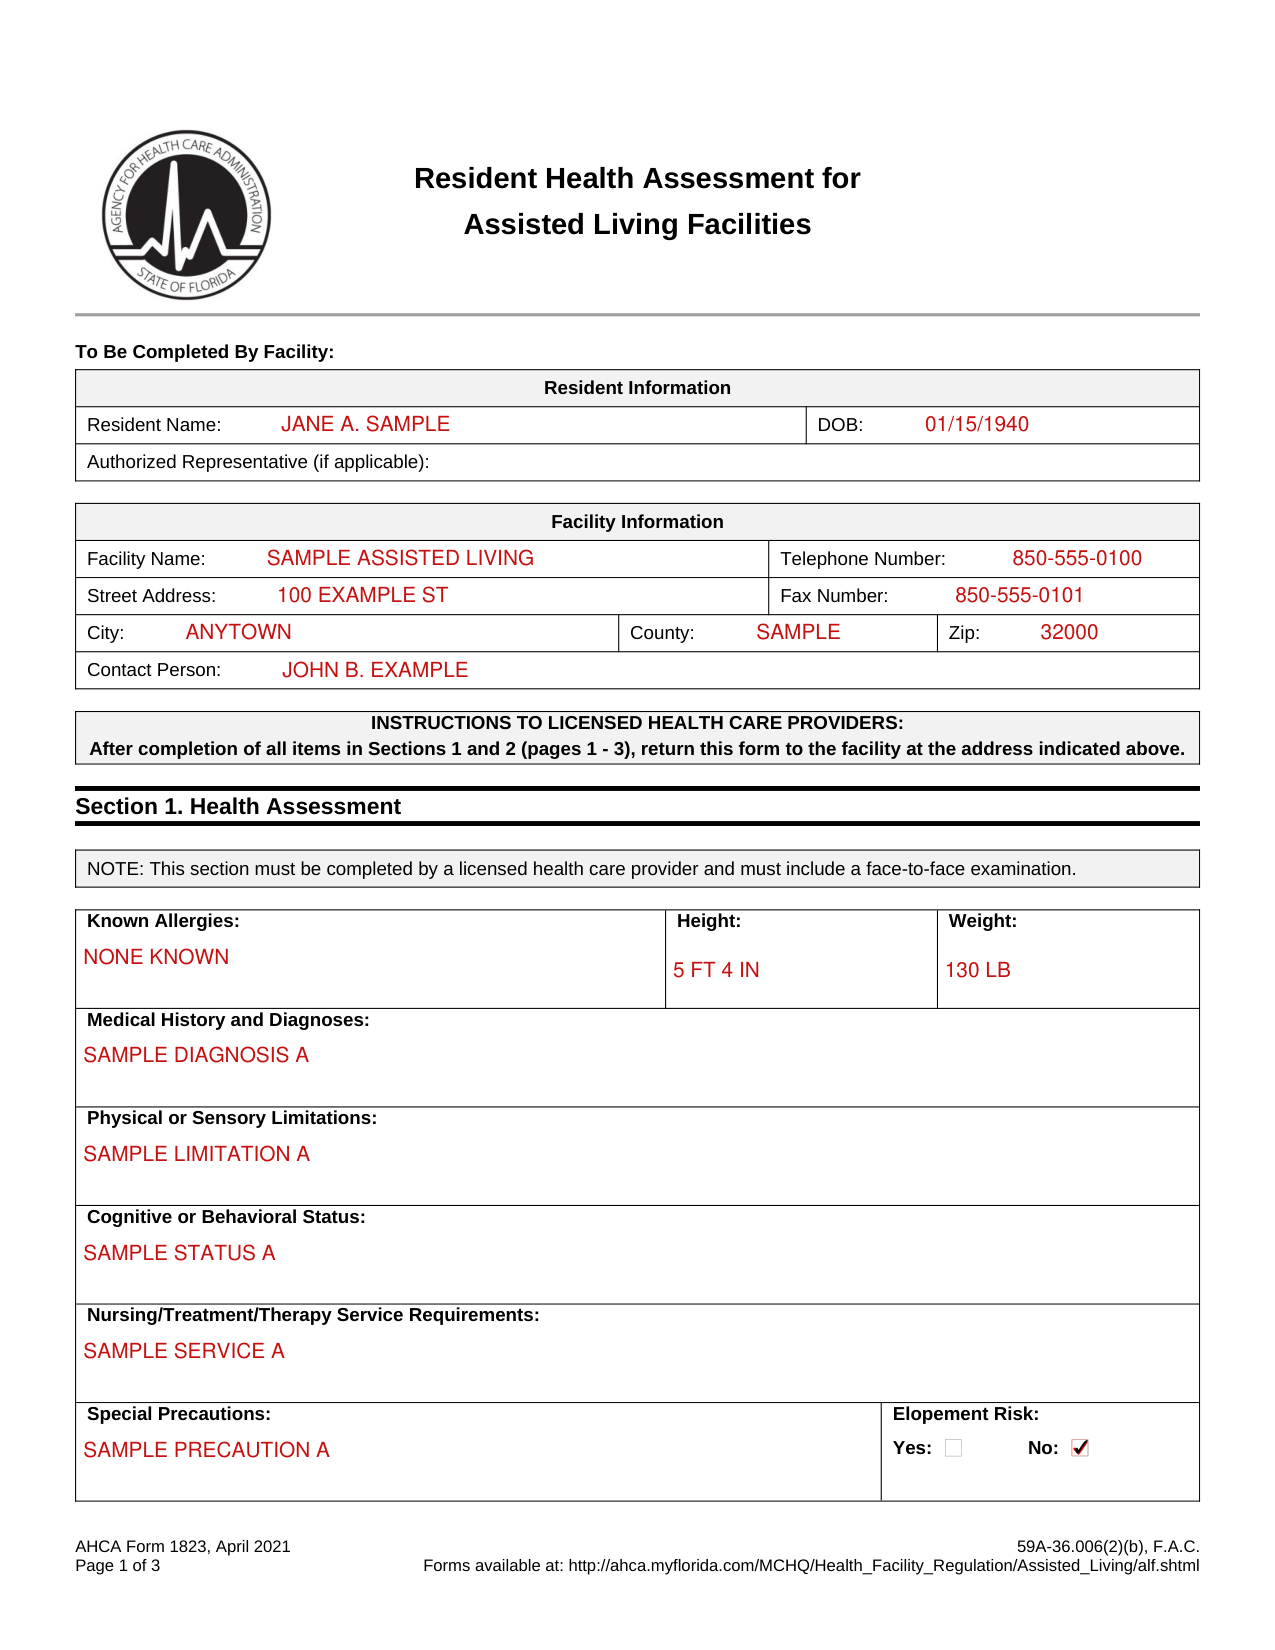
How to fill out AHCA Form 1823, box by box
Resident Information

The facility completes Resident Information: Resident Name, DOB and Authorized Representative (if applicable).
Facility Information
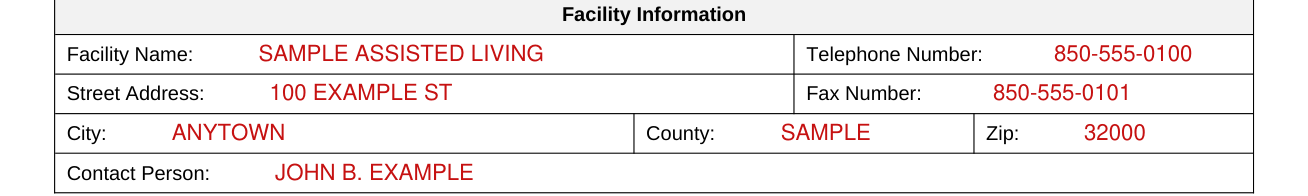
The facility completes Facility Information: Facility Name, Telephone Number, Street Address, Fax Number, City, County, Zip and Contact Person.
Known Allergies, Medical History and Special Precautions
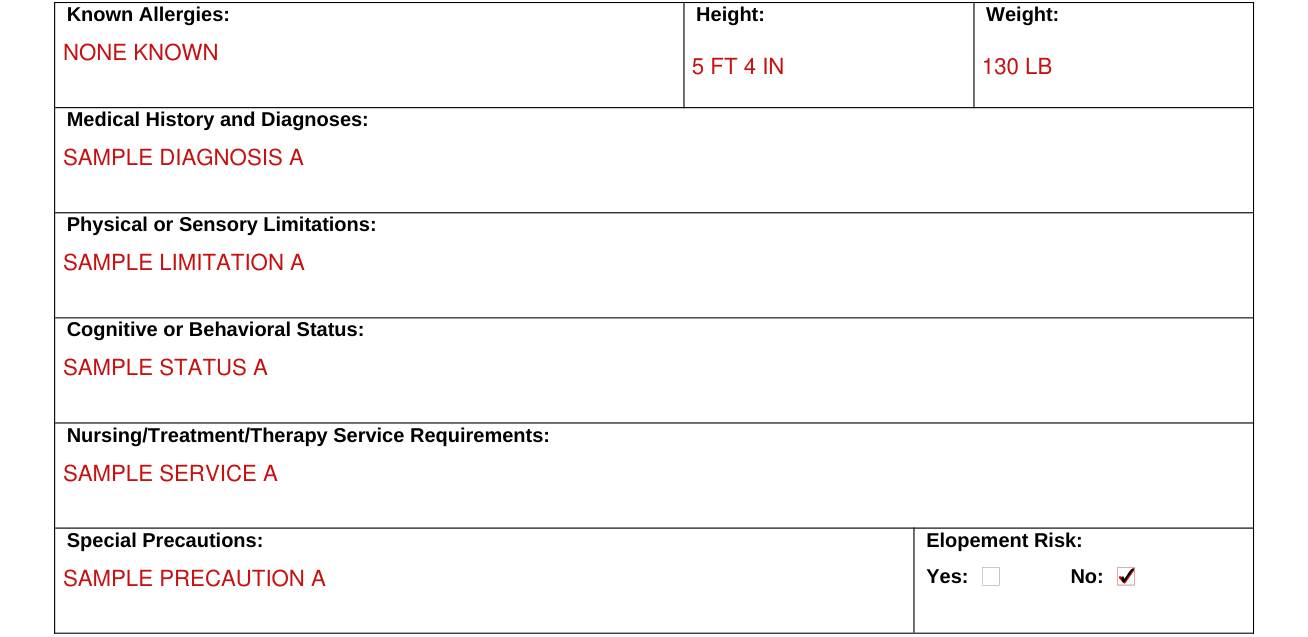
Enter Known Allergies, Height, Weight, Medical History and Diagnoses, Physical or Sensory Limitations, Cognitive or Behavioral Status and Nursing/Treatment/Therapy Service Requirements.
Enter Special Precautions, and mark Yes or No for Elopement Risk.
A. Activities of Daily Living
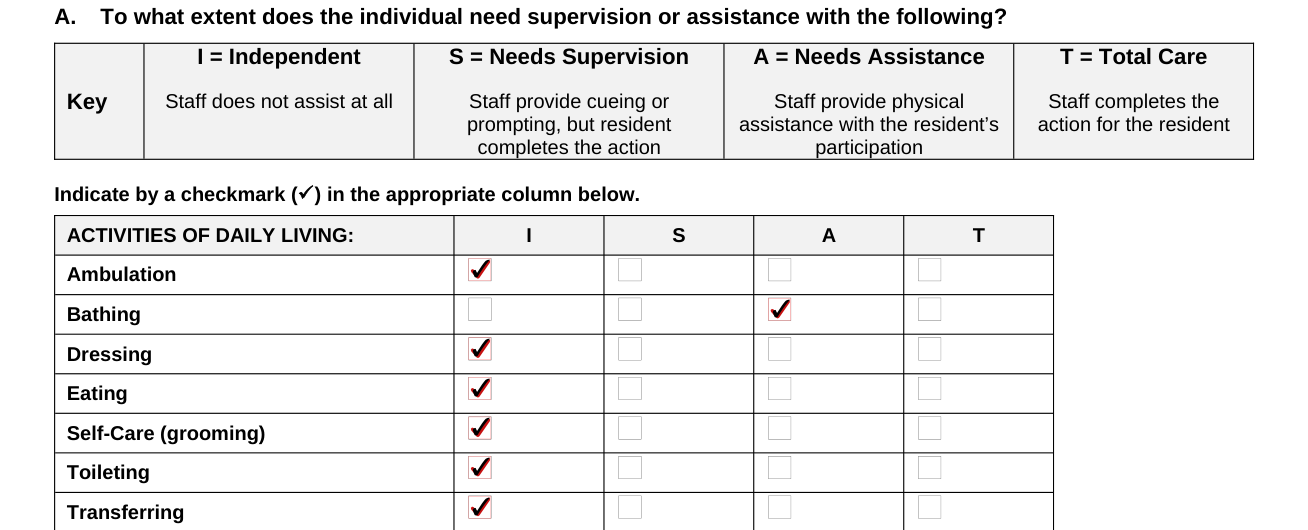
To what extent does the individual need supervision or assistance with Ambulation, Bathing, Dressing, Eating, Self-Care (grooming), Toileting and Transferring? Indicate by a checkmark in the appropriate column.
I = Independent: Staff does not assist at all. S = Needs Supervision: Staff provide cueing or prompting, but resident completes the action. A = Needs Assistance: Staff provide physical assistance with the resident's participation. T = Total Care: Staff completes the action for the resident.
B. Special Diet Instructions

Special Diet Instructions: mark Regular, Calorie Controlled, No Added Salt, Low Fat/Low Cholesterol, or Other (specify, including consistency changes such as puree).
C. Does the individual have any of the following conditions/requirements?
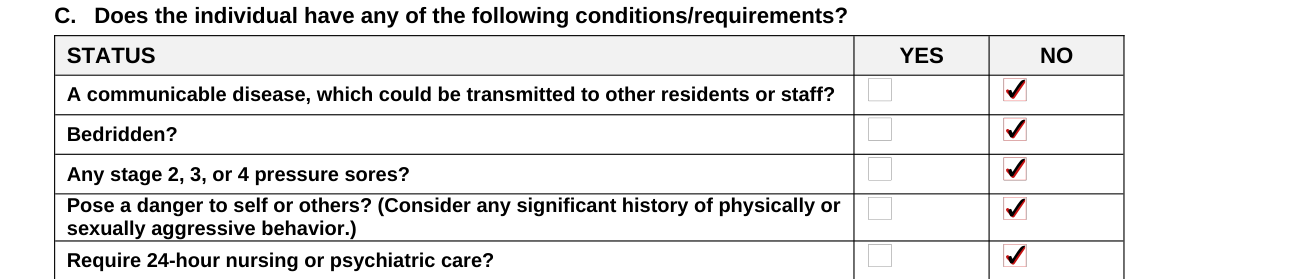
Does the individual have any of the following conditions/requirements? Mark YES or NO under STATUS.
A communicable disease, which could be transmitted to other residents or staff? Bedridden? Any stage 2, 3, or 4 pressure sores? Pose a danger to self or others? (Consider any significant history of physically or sexually aggressive behavior.) Require 24-hour nursing or psychiatric care?
D. Can this individual's needs be met in an assisted living facility?

In your professional opinion, can this individual's needs be met in an assisted living facility, which is not a medical, nursing, or psychiatric facility? Mark Yes or No.
B. Does the individual need help with taking his or her medications (meds)?

Does the individual need help with taking his or her medications (meds)? Mark Yes or No. If YES, place a checkmark in front of the appropriate box.
Needs Assistance With Self-Administration: This allows unlicensed staff to assist with nasal, ophthalmic, oral, otic, and topical medications.
Needs Medication Administration: Not all assisted living facilities have licensed staff to perform this service.
Able To Self-Administer Medications: Resident does not need staff assistance.
C. Additional Comments/Observations

Enter Additional Comments/Observations; use additional pages, if necessary.
Name of Examiner, Medical License Number, Title of Examiner and Signature of Examiner
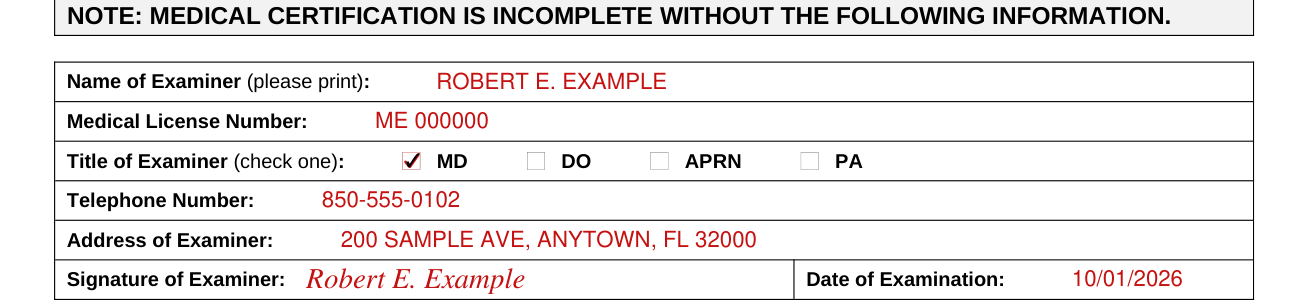
Medical certification is incomplete without the following information.
Enter Name of Examiner (please print) and Medical License Number. Title of Examiner (check one): MD, DO, APRN or PA.
Enter Telephone Number and Address of Examiner. The examiner signs under Signature of Examiner and enters the Date of Examination.
Common questions about AHCA Form 1823
What is an 1823 form in Florida?
AHCA Form 1823 is the Resident Health Assessment for Assisted Living Facilities. Licensed health care providers: after completion of all items in Sections 1 and 2 (pages 1 - 3), return this form to the facility at the address indicated in Facility Information.
Sources
[1] AHCA Form 1823 (April 2021), Resident Health Assessment for Assisted Living Facilities, Florida Agency for Health Care Administration (the Official source link on this page).