

Form 04-002 at a glance
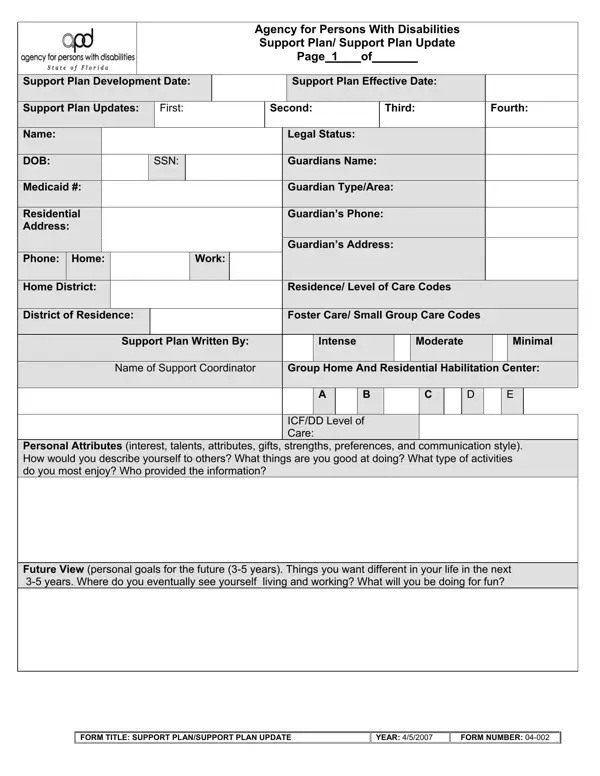
What it is: Agency for Persons With Disabilities Support Plan/ Support Plan Update, form number 04-002; the purpose of this plan is to identify strengths, needs, preferences, and resources to help promote a positive quality of life.
Who signs: Sign on the Individual's Signature line, and enter Date and Date Copy Sent. If there is a legal representative, sign on the Legal Representative's Signature line, and enter Date and Date Copy Sent. Enter Printed Name and Telephone Number and Relationship (parent, guardian advocate, POA). Support plan participants sign on the Signature of Support Plan Participants lines, and enter Relationship, Name /Address/Program (if applicable), Date of Signature and Date Copy Sent. Signature of Support Plan Participants: Enter the relationship, and the name(s)/address/program (if applicable) of the individual(s) who are invited by the person and participated in the development of the support plan, and the date the support plan was signed.
Note: Pages A, B, and C should be completed by the Support Coordinator Prior to the Support Plan Meeting.
A filled-in Form 04-002 example: a new support plan for Alex Sample
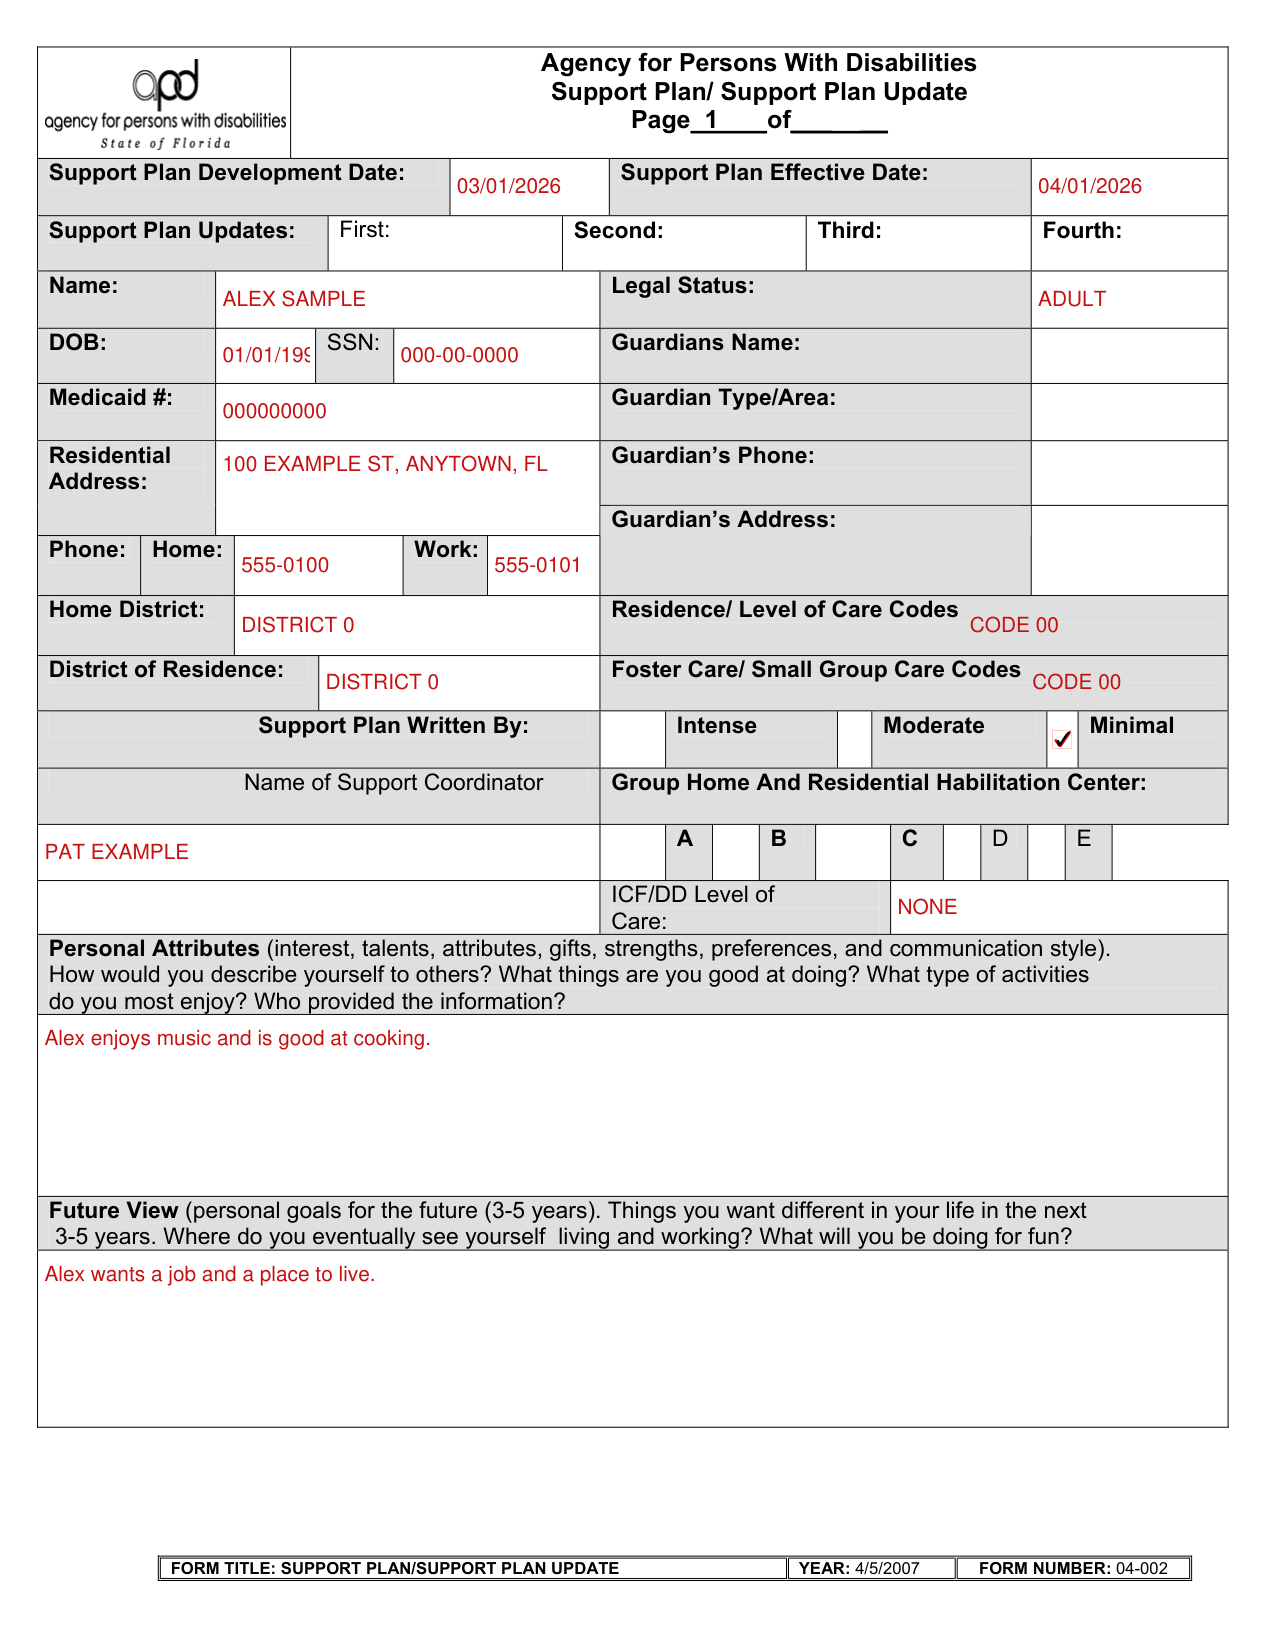
How to fill out Form 04-002, box by box
Support Plan Development Date, Effective Date and Updates
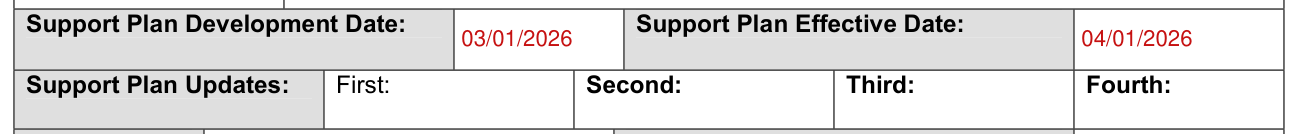
Enter the Support Plan Development Date and the Support Plan Effective Date.
Under Support Plan Updates, enter First, Second, Third and Fourth.
Name, Legal Status and Guardian
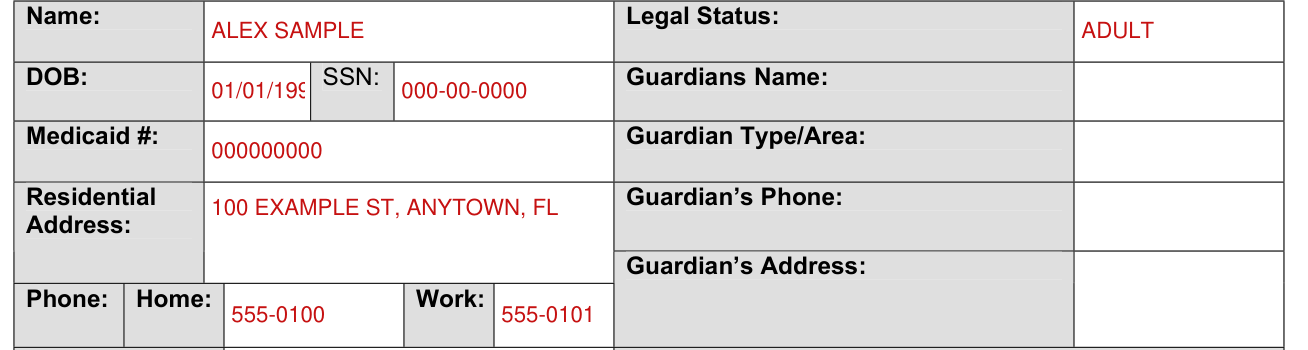
Enter Name and Legal Status.
Enter DOB, SSN and Guardians Name.
Enter Medicaid # and Guardian Type/Area.
Enter Guardian's Phone and Residential Address.
Enter Guardian's Address.
Enter Phone: Home and Work.
Home District, District of Residence and Care Codes

Enter Home District and Residence/ Level of Care Codes.
Enter District of Residence and Foster Care/ Small Group Care Codes.
Support Plan Written By
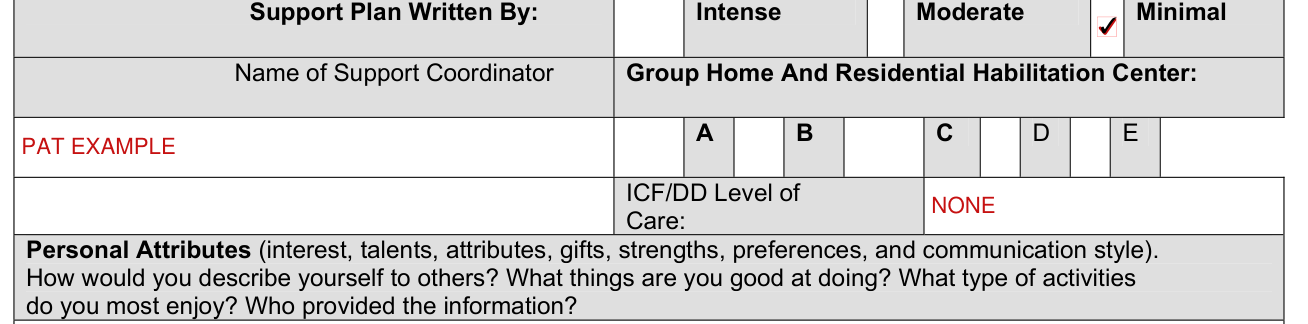
Under Support Plan Written By, mark Intense, Moderate or Minimal.
Enter the Name of Support Coordinator.
Group Home And Residential Habilitation Center and ICF/DD Level of Care

Under Group Home And Residential Habilitation Center, mark A, B, C, D or E.
Enter ICF/DD Level of Care.
Personal Attributes and Future View
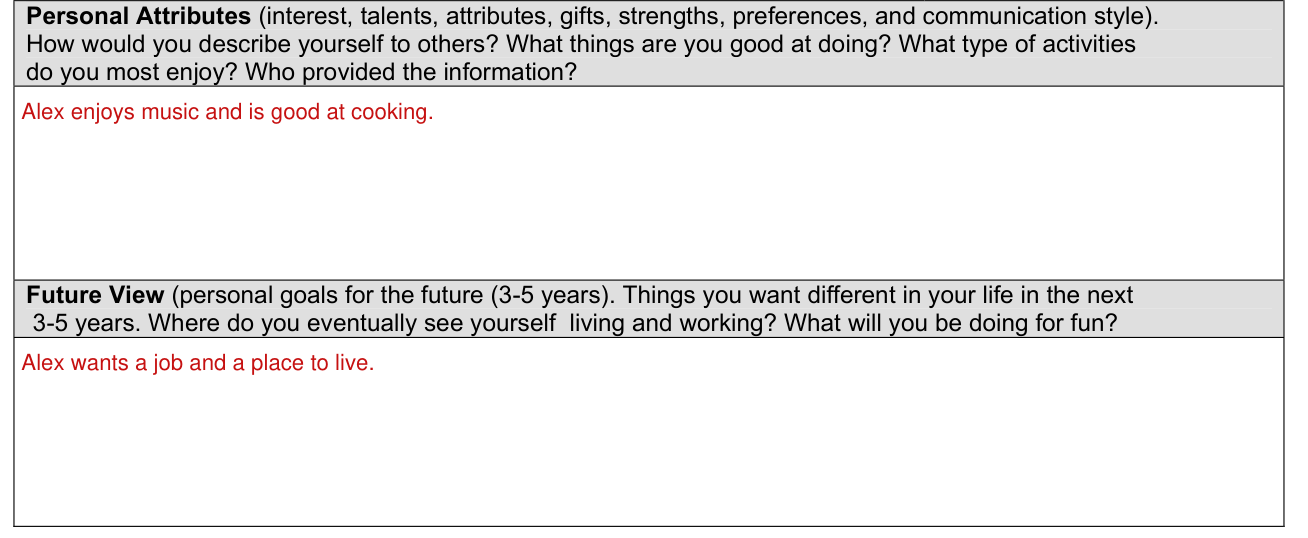
Personal Attributes (interest, talents, attributes, gifts, strengths, preferences, and communication style). How would you describe yourself to others? What things are you good at doing? What type of activities do you most enjoy? Who provided the information?
Future View (personal goals for the future (3-5 years). Things you want different in your life in the next 3-5 years. Where do you eventually see yourself living and working? What will you be doing for fun?
Life Area and Present situation
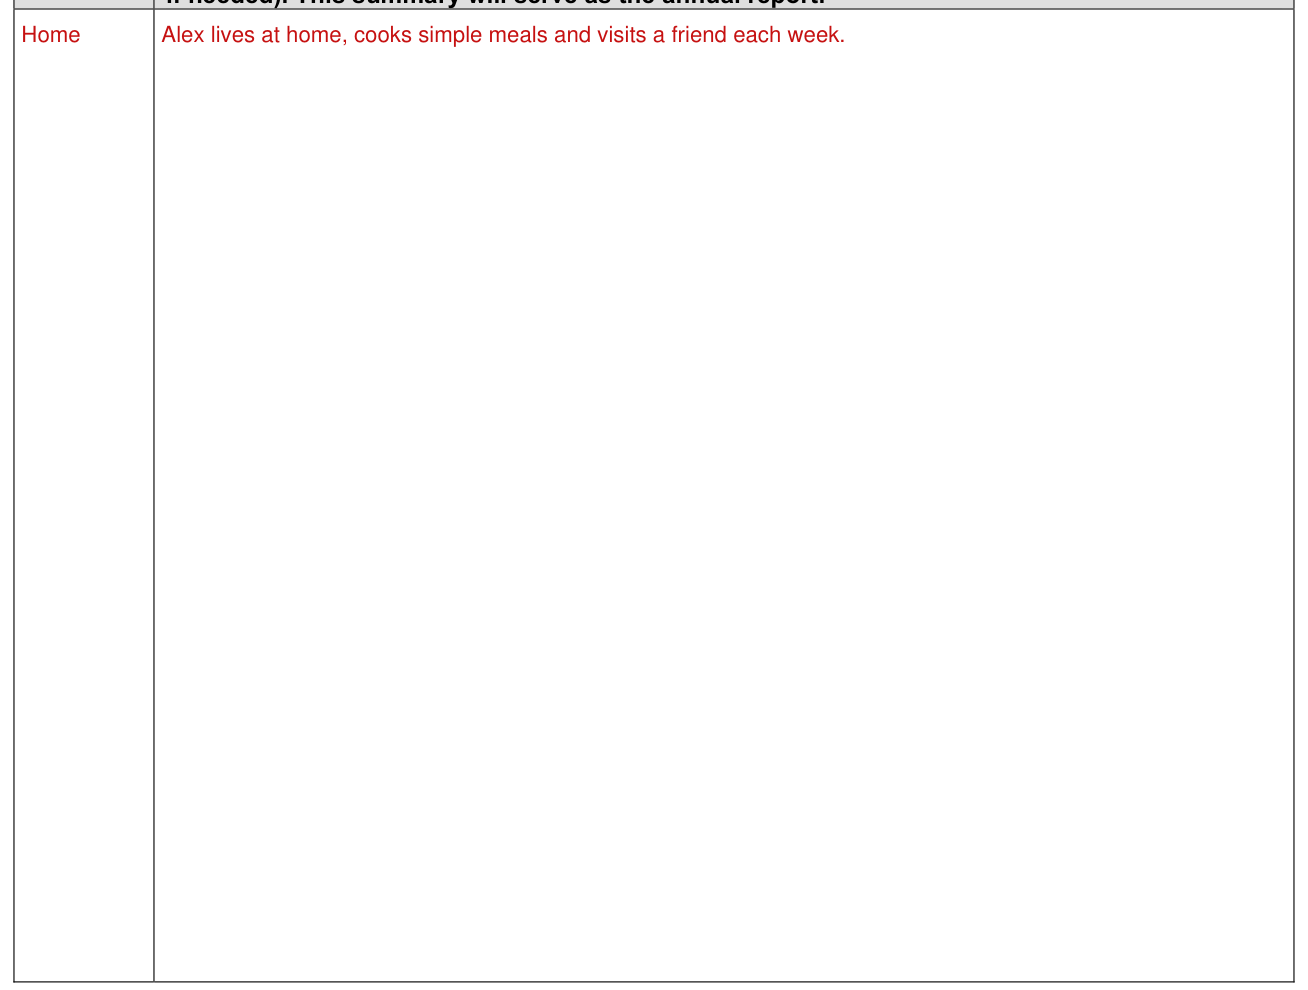
Under Life Area, enter the Present situation (in the life areas of home, daily activities/work/school and personal/social).
Include a brief functional description of : (1) capabilities, (2) daily activities, (3) interactions with others, (4) valued roles, (5) community opportunities, (6) supports and services currently being received (both paid and unpaid), (7) issues or concerns (health, challenging behaviors or situations) the person is experiencing, (8) any changes the person wants in their present situation, and (9) important relationships in the person's life.
Also include a brief summary of personal goals achieved in the past year and/or the status toward completion.
(Add additional pages if needed).
This summary will serve as the annual report.
Health Summary
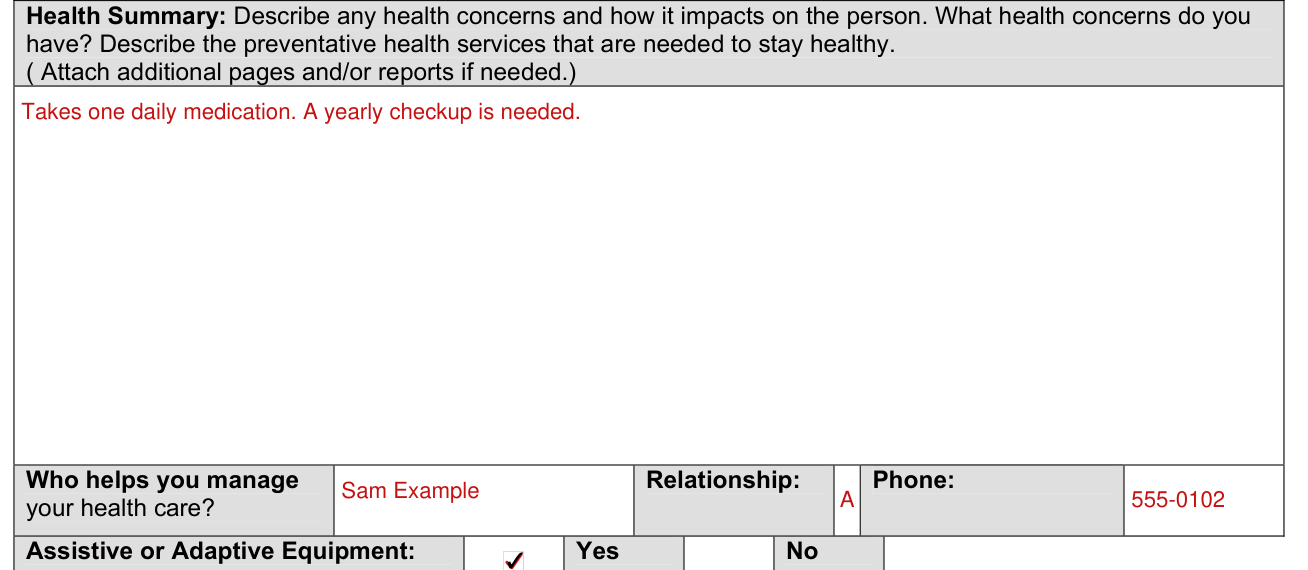
Health Summary: Describe any health concerns and how it impacts on the person. What health concerns do you have?
Describe the preventative health services that are needed to stay healthy. (Attach additional pages and/or reports if needed.)
Who helps you manage your health care? Enter Relationship and Phone.
Assistive or Adaptive Equipment

Under Assistive or Adaptive Equipment, mark Yes or No.
Identify glasses, dentures, equipment, etc. What adaptive equipment do you use and what is it used for?
Medications
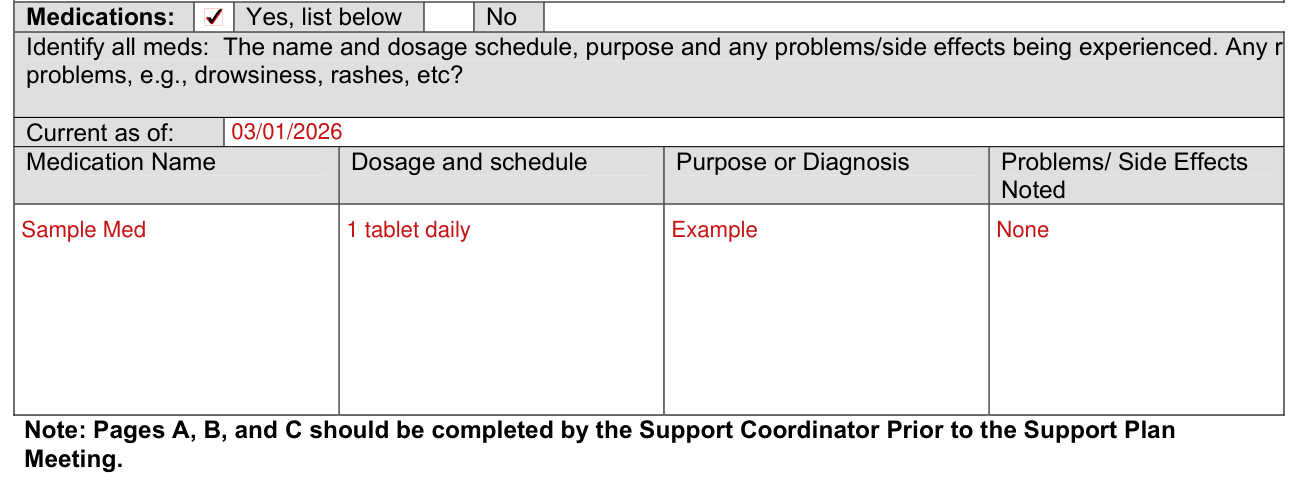
Under Medications, mark Yes or No. Identify all meds: The name and dosage schedule, purpose and any problems/side effects being experienced.
Any problems, e.g., drowsiness, rashes, etc?
Enter Current as of, and for each medication enter Medication Name, Dosage and schedule, Purpose or Diagnosis and Problems/ Side Effects Noted.
Personal Goals, Support/Services Needed and Who will take the Lead
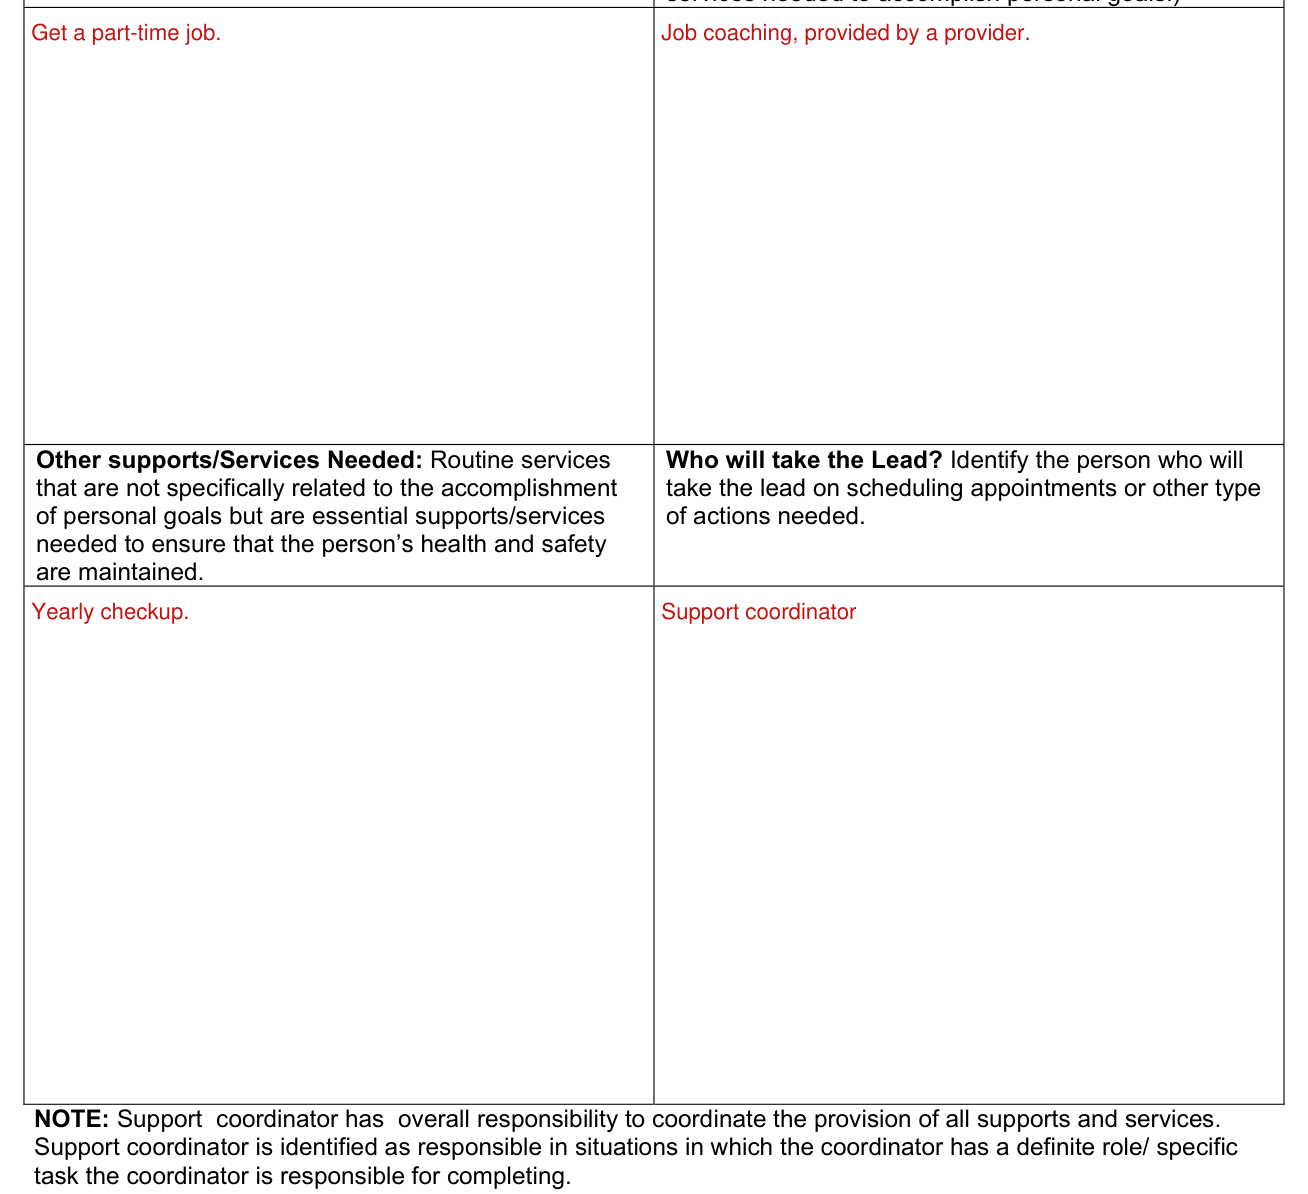
Personal Goals for Upcoming Year: What do you want to accomplish this year? What are the most important things you want to see happen in your life?
Support/Services Needed: Include all natural, generic, community and paid supports. Identify the type of service and who is responsible. (include only those services needed to accomplish personal goals.)
Other supports/Services Needed: Routine services that are not specifically related to the accomplishment of personal goals but are essential supports/services needed to ensure that the person's health and safety are maintained.
Who will take the Lead? Identify the person who will take the lead on scheduling appointments or other type of actions needed.
NOTE: Support coordinator has overall responsibility to coordinate the provision of all supports and services. Support coordinator is identified as responsible in situations in which the coordinator has a definite role/ specific task the coordinator is responsible for completing.
Individual/Guardian Consent
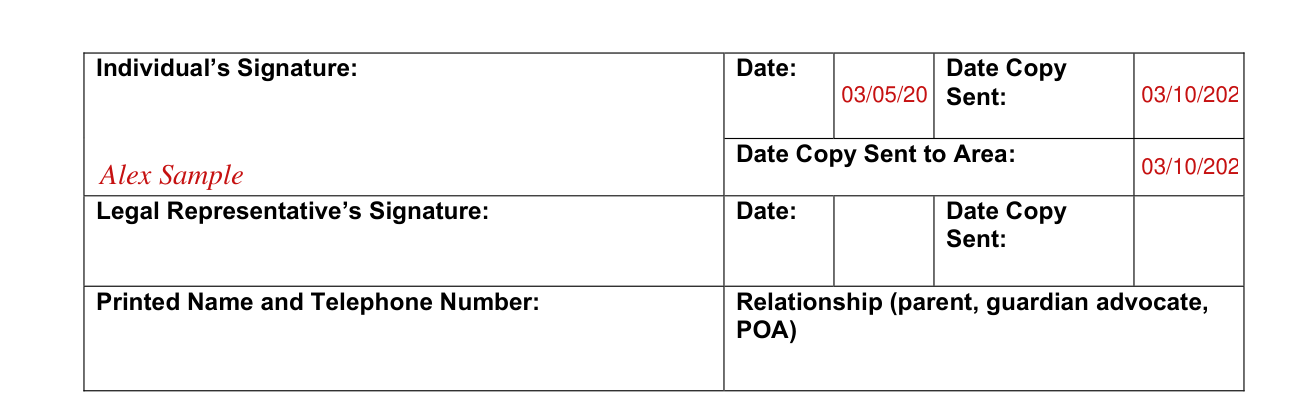
Individual/Guardian Consent: I have participated in the development of the plan and I agree to the contents.
I have been informed of my due process rights under Florida Statutes 120 and that I may appeal any portion of this plan.
I understand that if my needs change, an update to this support plan may be needed.
Supports should be identified according to my or my family's needs regardless of the availability of funds.
Supports and services needed to meet my needs will be sought from my personal resources, community resources and government resources.
When government resources are necessary, they shall be provided based on the availability of general revenue funds.
Sign on the Individual's Signature line, and enter Date and Date Copy Sent.
Enter Date Copy Sent to Area.
If there is a legal representative, sign on the Legal Representative's Signature line, and enter Date and Date Copy Sent.
Enter Printed Name and Telephone Number and Relationship (parent, guardian advocate, POA).
Signature of Support Plan Participants
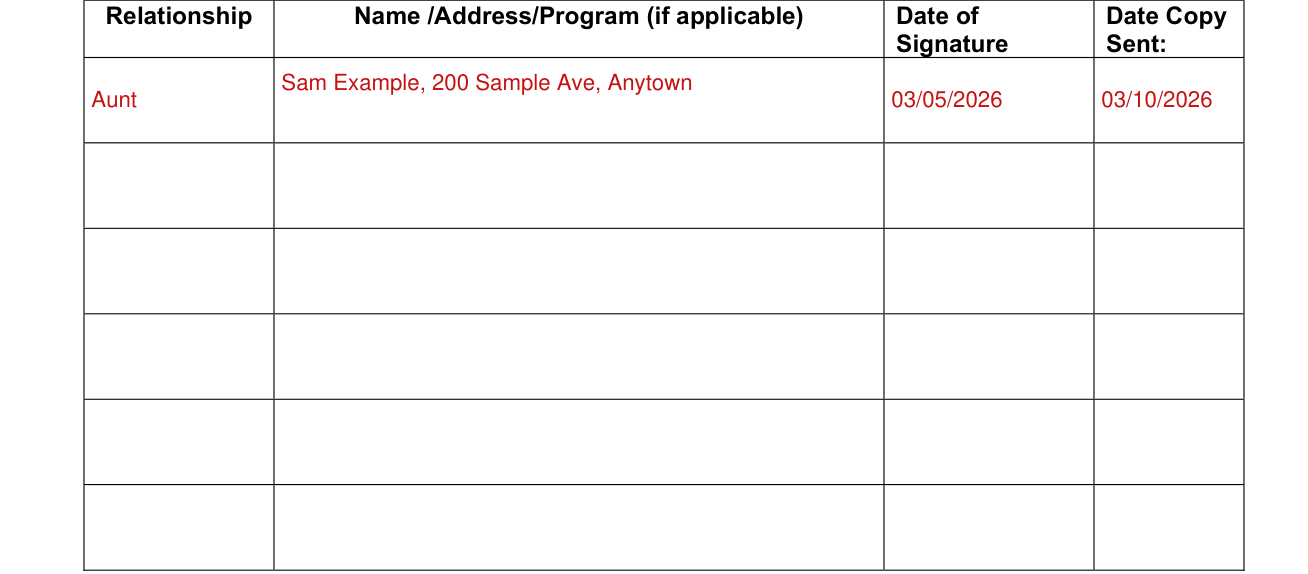
Provide the date the support plan was provided/mailed to the participant.
Sources
[1] Form 04-002 (4/5/2007), Support Plan/Support Plan Update, Agency for Persons With Disabilities (the Official source link on this page).