

SCAT Paratransit Application at a glance
What it is: The SCAT Paratransit Application, Revised 4/2024, is an application for the Suffolk County Accessible Transit (SCAT) Paratransit system.
Who signs: The information I have given on this application is true to the best of my knowledge. False statements are punishable under Section 210.45 of the Penal Law. Sign as the Signature of Applicant, then enter the Printed Name of Applicant and Date. Sign as the Signature of preparer, then enter the Printed Name of Preparer and Date, and if other than applicant, Doctor or Staff that have assisted, the Relationship, Agency name and Phone No.
SCAT is for people whose disability is so severe that it prevents them from using public buses.
In compliance with the Americans with Disabilities Act of 1990 (ADA) Suffolk County provides curb-to-curb paratransit services for the SCAT Program to anyone who, because of physical or mental disability, is unable to use the regular, fixed route bus service.
A filled-in SCAT Paratransit Application example: a first-time applicant fills out the first page

How to fill out SCAT Paratransit Application, box by box
First time applying or recertifying

Mark First time applying, or mark Recertifying and write your SCAT ID#.
Date of Birth, name and address
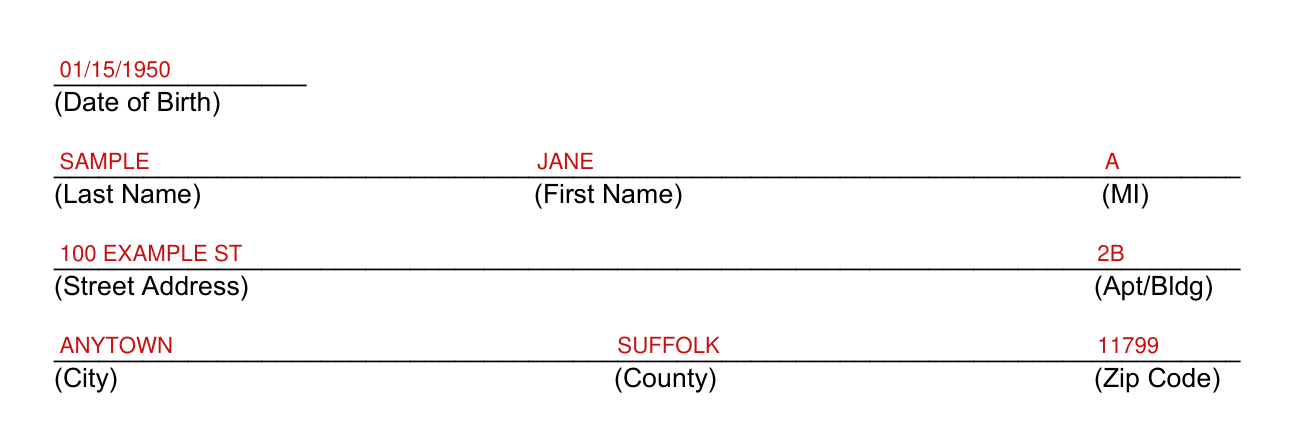
Enter the Date of Birth, Last Name, First Name, MI, Street Address, Apt/Bldg, City, County and Zip Code.
Home phone, Cell number and Email

Enter the Home phone, Cell number and Email.
Mailing address if different

Under Mailing address (If different), enter the Street address, Apt/Bldg, City, County and Zip Code.
Braille, large print, audio format, language, other and the Emergency

Do you require information and material given to you in any of the following ways? Braille; large print; audio format; language; other. Mark each one you require. Give the Last Name, First Name, Cell number and Alternate number of someone to call in an Emergency. Do not write in Certifier initials, CERTIFICATION DATA or Date Received.
Signature of Applicant and mail it
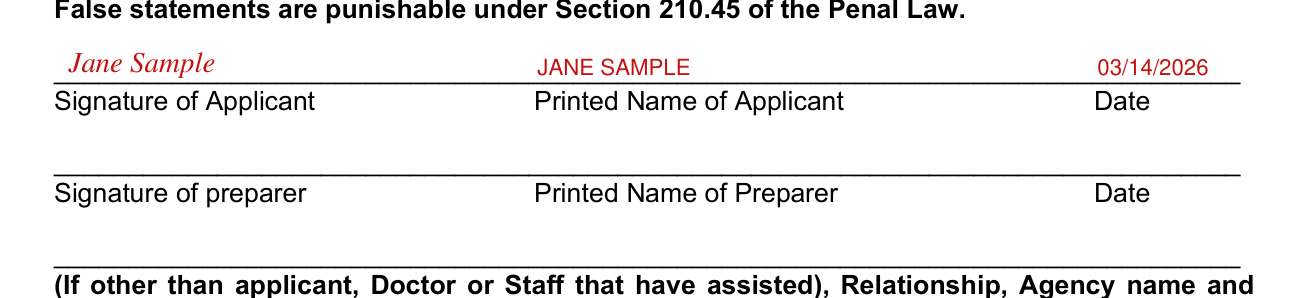
When you have completed and signed the application, mail it (original only, Suffolk County will not accept photocopies or faxes of this application) to: Suffolk County Office for People with Disabilities William J. Lindsay County Complex, Building 158 725 Veterans Memorial Hwy. P.O. Box 6100 Hauppauge, NY 11788-0099. You will be notified as to your eligibility by mail within 21 business days.
I understand that a false statement made herein may result in the rejection of my application for paratransit service.
More rules for SCAT Paratransit Application
Only original forms of this document will be accepted.
The Office for People with Disabilities will no longer be issuing SCAT ID cards. Riders can use a Government or a University Identification card.
As part of the eligibility process, you may be required to undergo an in-depth interview. Failure to attend will result in denial of your application.
Each application will be evaluated on a case-by-case basis, taking into consideration all of the information provided.
I understand that my application will be returned if it is not complete.
I understand the application process can take up to 21 days from the time SCAT receives a completed application. If my application is returned for clarification or additional information, this can delay the process.
The applicant, or someone assisting them, must complete all the questions.
Mobility, fixed route use, disability and the medical form
Mobility aides or equipment
1) Indicate if you use any of the following mobility aides or equipment? Cane; Manual wheelchair; Crutches; Powered wheelchair; Long white cane (for the visually impaired); Powered scooter/cart; Service/guide animal (describe); Respirator/oxygen tank; Walker; Other; Leg braces; or I don't require any assistive devices. The applicant may not be accommodated if the wheelchair or scooter is longer than 48 " or wider than 32 3/4", or if the combined weight of the applicant and wheelchair is more than 600 pounds.
Fixed route buses and what might help
2) Have you ever used the fixed route buses? Mark Yes, I typically use fixed-route buses ___ times a week; Yes, but only for trips I am familiar with; Yes, I used to but stopped because ___; or No. 3) If you currently do not use the fixed route is there something that might help you to ride the buses? (Mark all that apply.) Yes, route and schedule information; Yes, buses with wheelchair lifts; Yes, learning to use the buses; Yes, a communication aid; Yes, if bus stops were closer to where I live and where I need to go; Yes, (describe); No, none of these would help.
Nearest bus stop and how far you can travel
4) How far from your home is the nearest bus stop? Less than 1 block, 1-2 blocks, 3-4 blocks, 5 or more blocks, or I don't know. 5) On your own or using an assistive device, how far can you travel? I can get to the curb in front of my house/apartment, I can travel up to 3 blocks (1/4 mile), up to 6 blocks (1/2 mile), up to 9 blocks (3/4 mile), or I don't know.
Disabilities that prevent you from using the fixed route
6) Mark ALL of the disabilities that prevent you the applicant from using the fixed route.
7) Explain in DETAIL how your identified disability prevents you, the applicant from riding the fixed route buses.
Permanent, temporary and Personal Care Attendant (PCA)
8) Is this condition permanent? Mark YES or NO. Is this condition temporary? Mark YES or NO. If temporary, what is the expected duration? (Number of months) 9) Does the applicant need to travel with his or her own Personal Care Attendant (PCA)? Mark YES or NO.
6) For riders requiring a personal care attendant (PCA), the attendant will travel free. In addition to the PCA, one companion can also accompany the rider by paying the full fare.
Able to travel to and from a bus stop
10) Is the applicant able to travel to and from a bus stop? Mark YES or NO. If no, please indicate all that apply: Cannot negotiate where there are no sidewalks. Cannot travel if there are no curb cuts. Cannot cross busy streets and intersections. Cannot tolerate extreme temperatures. Cannot travel on surfaces covered with ice/snow. Cannot locate or identify bus stop due to a visual impairment. Easily becomes confused and may get lost. Other (please specify).
Functions without assistance from another person
11) Is the applicant able to perform the following functions? Find their way between familiar locations; Grasp coins, passes, railings and handles; Climb up and down three 12 inch steps; Travel 3/4 miles to a bus stop; Identify the stop at your destination; Deal with unexpected situations or unexpected changes in routine. Mark Yes or No for each, without assistance from another person.
Other type of transportation service
12) Do you use any other type of transportation service? (Please check the appropriate box) Medicaid Transportation, Senior Transportation, or Other (Please explain).
The medical certification
A New York State licensed medical professional is required to complete the medical certification, this consists only of an M.D., D.O., P.A., N.P, or D.C.
ONLY If you do not have access to a licensed medical professional, call (631) 853-8333 for assistance.
This form must be completed in its entirety; any question left blank will deem this form void and incomplete. IF THE APPLICANT COMPLETES THIS FORM, IT WILL BE DEEMED VOID.
Please mark all the disabilities, which prevent the applicant from using the fixed route bus service. Conditions, which make it difficult or uncomfortable, should not be checked.
Applications with illegible or incomplete information will be returned and deemed void.
The physician fills in Signed this day of and 20, the Name of Physician, Signature of Physician, License number, Phone number, Street address, City, State and Zip, and places the medical office stamp.
Common questions about SCAT Paratransit Application
Are there fees?
5) The fare is $4.00 one way ($8.00 round trip) (checked November 1, 2026). Exact fare is required.
When is this form not the right one?
Age, distance from a bus stop, or inability to drive, are conditions which are not taken into consideration in making an eligibility determination.
Sources
[1] SCAT Paratransit Application (Revised 4/2024), Suffolk County Office for People with Disabilities (the Official source link on this page).