


Notice and Proof of Claim for Disability Benefits (1199SEIU National Benefit Fund, 3NBF343 06/20) at a glance
What it is: This is the Notice and Proof of Claim for Disability Benefits of the 1199SEIU National Benefit Fund.
Who signs: Be sure to date and sign your claim (see item 12). If you cannot sign this claim form, your representative may sign on your behalf. In that event, the representative's full name, address and relationship to you should be noted under the signature. Do not mail this claim unless your healthcare provider completes and signs Part B. You must complete the member's section at the top of Part C, and then mail it to your employer.
Member: use this form only if you become sick or disabled while employed or if you become sick or disabled within four (4) weeks after termination of employment. Healthcare provider: use this form only if the member becomes sick while employed or becomes sick or disabled within four (4) weeks after termination of employment.
Use green Claim Form DB-300 if you become sick or disabled after having been unemployed more than four (4) weeks.
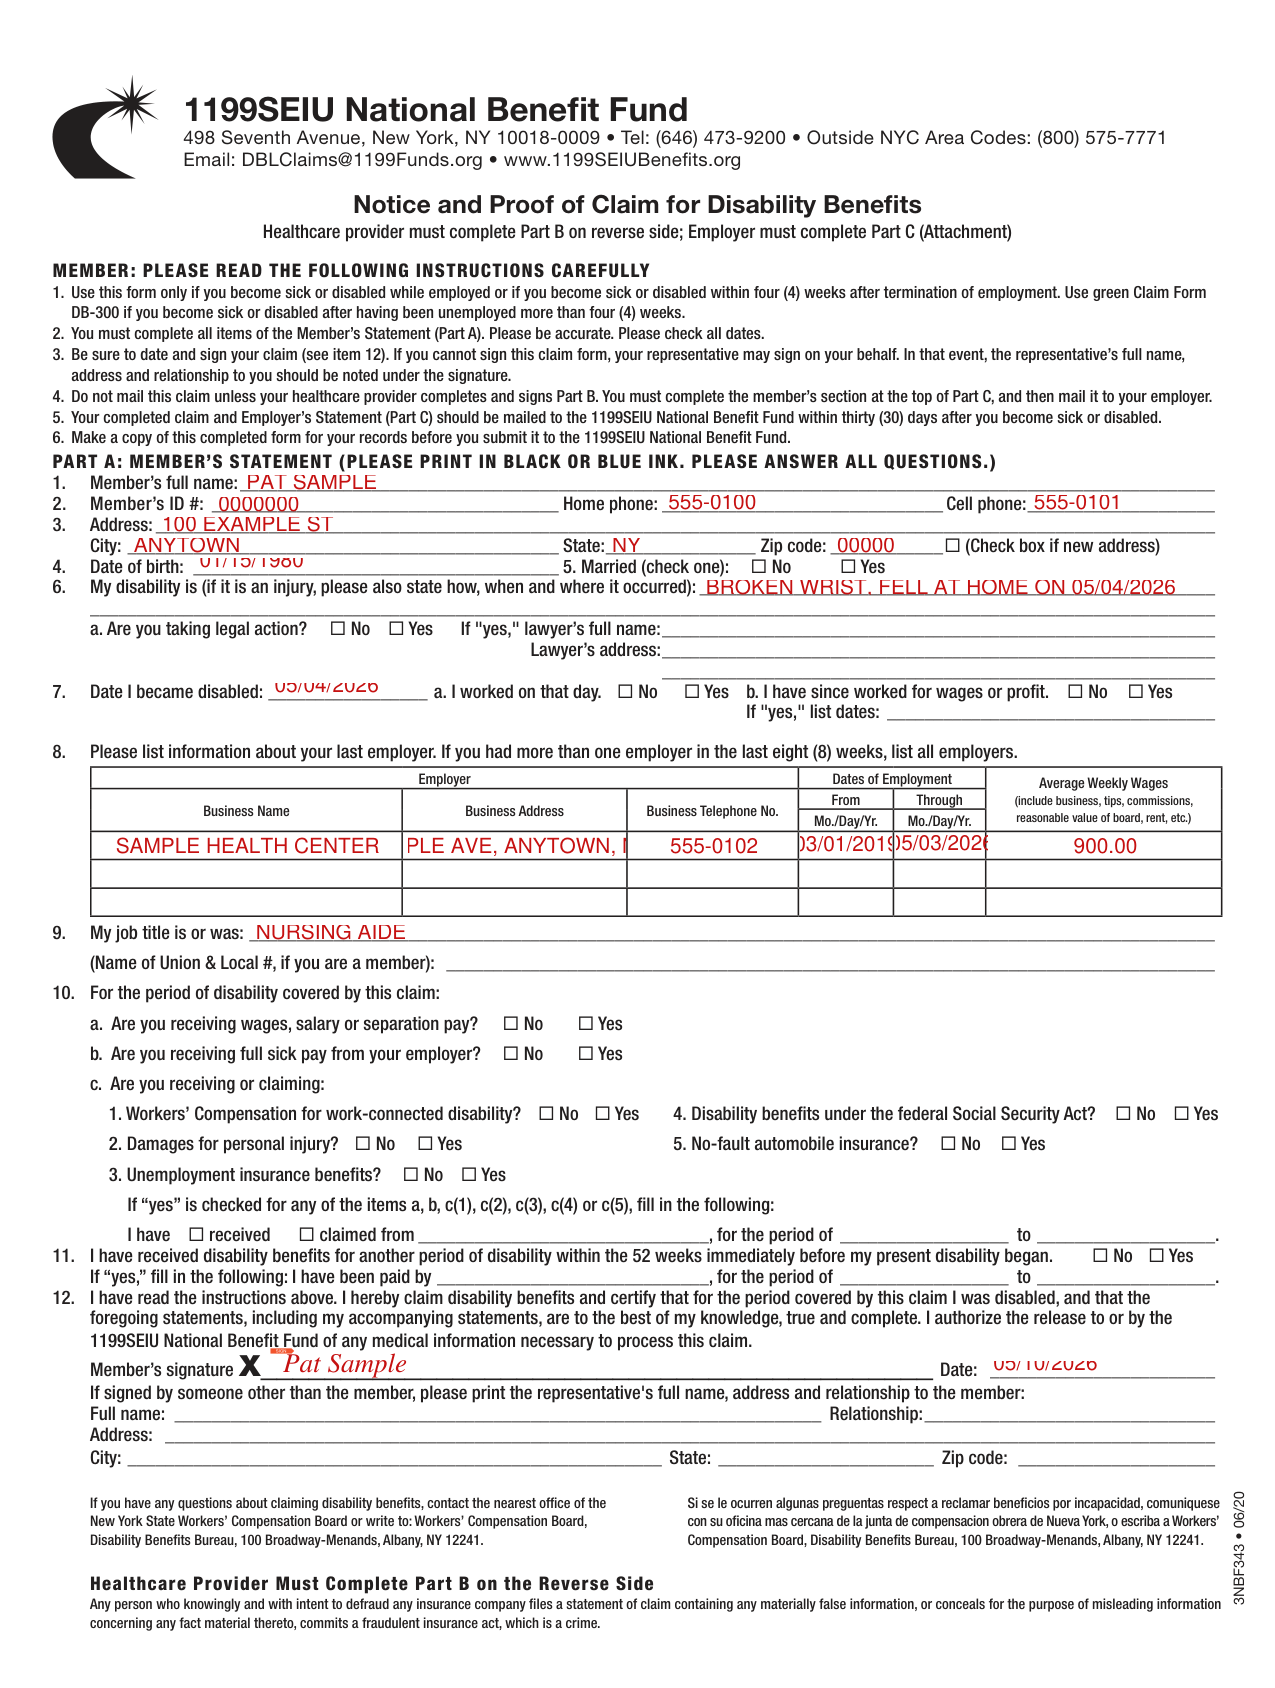
A filled-in Notice and Proof of Claim for Disability Benefits (1199SEIU National Benefit Fund, 3NBF343 06/20) example: a member fills out Part A
How to fill out Notice and Proof of Claim for Disability Benefits (1199SEIU National Benefit Fund, 3NBF343 06/20), box by box
Member's full name, ID, address and date of birth

You must complete all items of the Member's Statement (Part A). Please be accurate. Please check all dates. Please print in black or blue ink and answer all questions: write the Member's full name, Member's ID #, Home phone, Cell phone, Address, City, State, Zip code (check box if new address) and Date of birth, and check one for Married: No or Yes.
Your disability and the date you became disabled

In item 6, state your disability and, if it is an injury, please also state how, when and where it occurred. Check No or Yes for taking legal action; if "yes," write the lawyer's full name and address.
Enter the date you became disabled in Box 7. Check No or Yes for: I worked on that day; I have since worked for wages or profit. If "yes," list dates.
Your last employer, job title and union
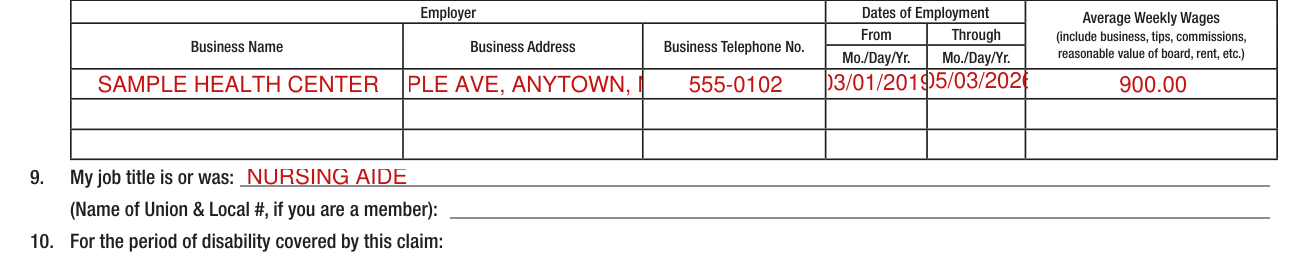
List information about your last employer. If you had more than one employer in the last eight (8) weeks, list all employers.
For each employer write the Business Name, Business Address, Business Telephone No., Dates of Employment From and Through (Mo./Day/Yr.) and Average Weekly Wages (include business, tips, commissions, reasonable value of board, rent, etc.).
Enter your job title and, if you are a member, the Name of Union & Local #.
Wages, sick pay and other benefits

For the period of disability covered by this claim, in Box 10: a. Are you receiving wages, salary or separation pay? b. Are you receiving full sick pay from your employer? Check No or Yes for each.
c. Are you receiving or claiming: 1. Workers' Compensation for work-connected disability, 2. Damages for personal injury, 3. Unemployment insurance benefits, 4. Disability benefits under the federal Social Security Act, 5. No-fault automobile insurance? Check No or Yes for each.
If "yes" is checked for any of the items a, b, c(1), c(2), c(3), c(4) or c(5), write who I have received or claimed from and the period of to.
Box 11: I have received disability benefits for another period of disability within the 52 weeks immediately before my present disability began. Check No or Yes. If "yes," fill in the following.
I have been paid by (who), for the period of (from) to (until).
Signing your claim

Member's signature and Date. If signed by someone other than the member, print the representative's full name, address, City, State, Zip code and relationship to the member.
By signing Box 12 you certify that for the period covered by this claim you were disabled, and that the foregoing statements, including your accompanying statements, are to the best of your knowledge, true and complete. You authorize the release to or by the 1199SEIU National Benefit Fund of any medical information necessary to process this claim.
Your completed claim and Employer's Statement (Part C) should be mailed to the 1199SEIU National Benefit Fund within thirty (30) days after you become sick or disabled. The Fund is at 498 Seventh Avenue, New York, NY 10018-0009.
Part B: healthcare provider's statement
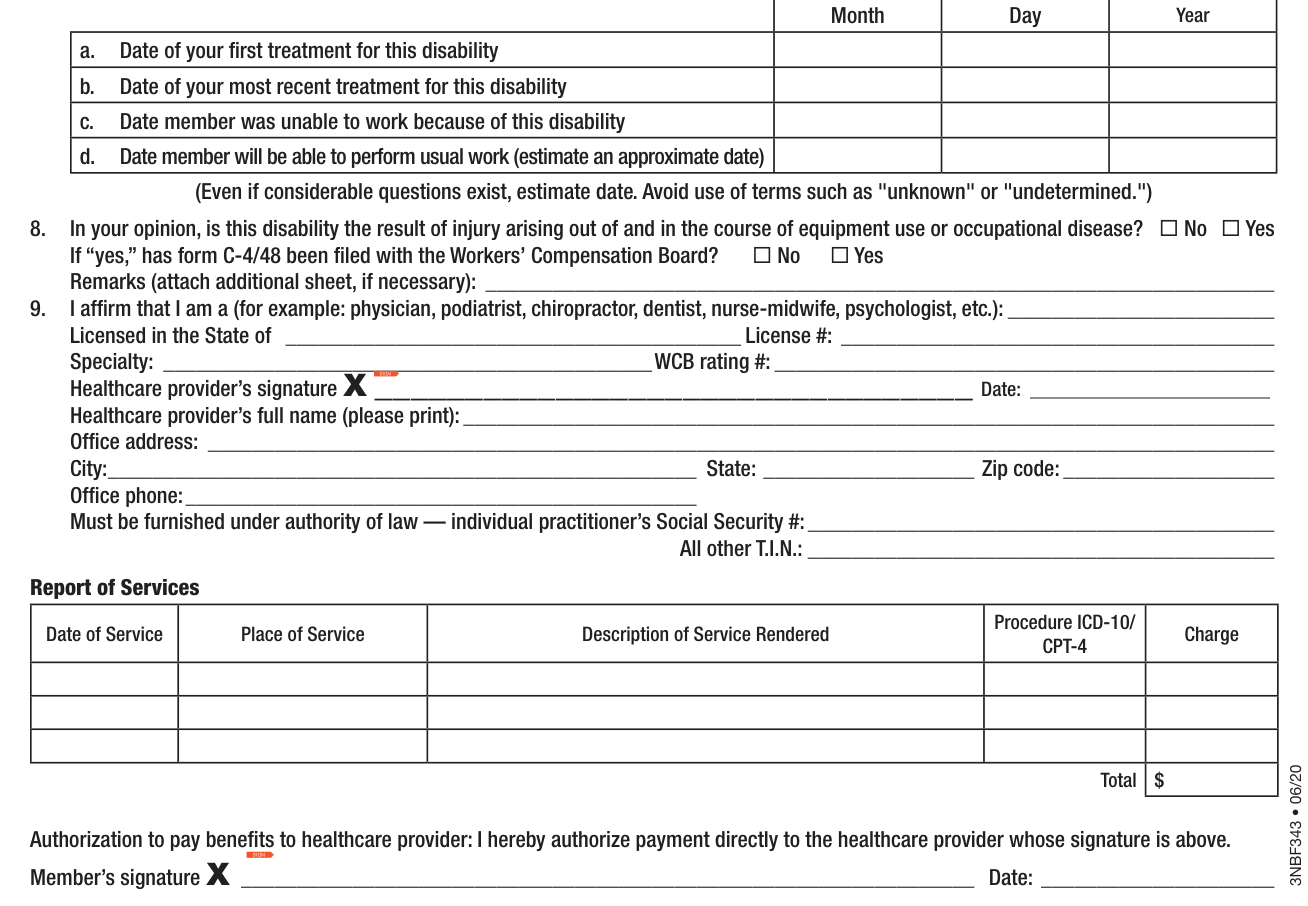
PART B: HEALTHCARE PROVIDER'S STATEMENT is to be completed by provider and signed by member.
The healthcare provider's statement must be filled in completely and mailed to the 1199SEIU National Benefit Fund or returned to the member within seven (7) days of receipt of the form.
Part B is to be completed by the provider. In Box 7 the provider enters the Month, Day and Year for the date of first treatment for this disability and the date of most recent treatment for this disability. The provider also enters the date the member was unable to work because of this disability and the date the member will be able to perform usual work (estimate an approximate date).
For item 7(d), estimate an approximate date. Even if considerable questions exist, estimate date. Avoid use of terms such as "unknown" or "undetermined."
Delay in the payment of disability benefits may be prevented if disability is caused by or arises in connection with pregnancy. Enter an estimated delivery date under "Remarks" in item 8.
Authorization to pay benefits to healthcare provider: the member's signature authorizes payment directly to the healthcare provider whose signature is in Part B.
Part C: Employer's Statement

Member: complete the following four (4) lines in Part C: Date, Member's full name, Member's ID # and Date disability began.
Since you are the member's present employer, you are required by the Union contract and the Trustees of the 1199SEIU National Benefit Fund to promptly complete the "Employer's Statement" and return the completed form to the employee.
The Employer's Statement is to be completed by the employer: in Box 1 the employer enters the Date employee was employed and the Employee's regular weekly wage, and in Box 2 the Date employee last worked (before disability).
Direct Electronic Deposit Authorization for Disability Benefits
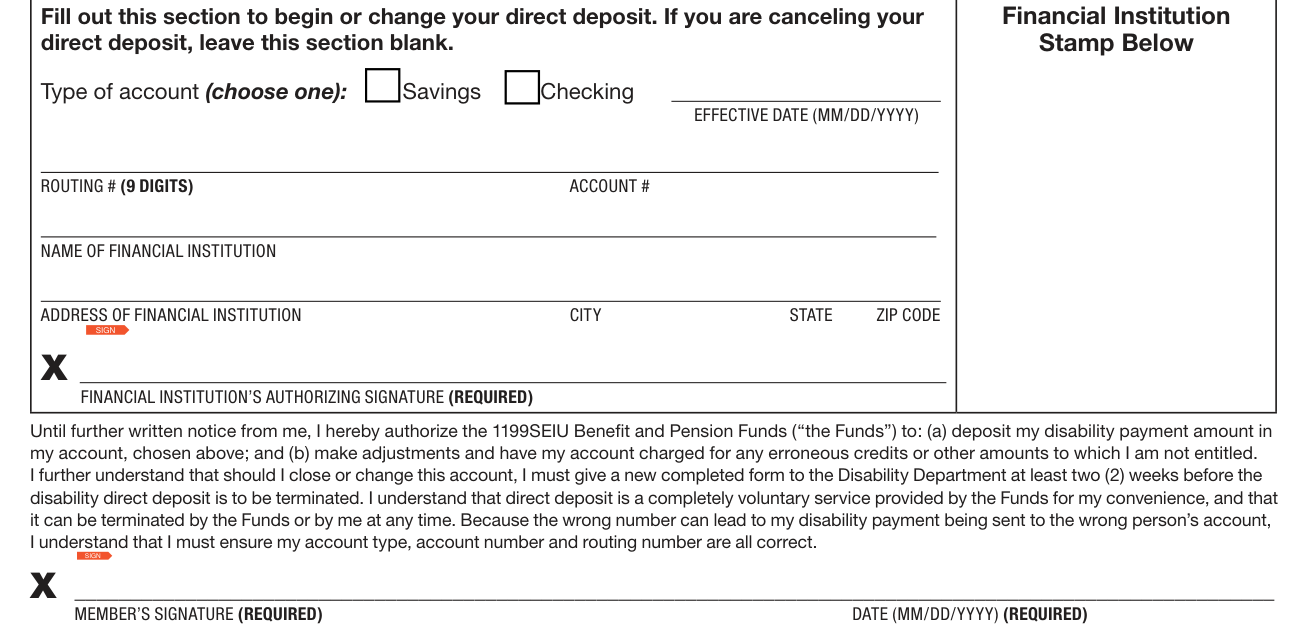
Direct Electronic Deposit Authorization for Disability Benefits: please allow a minimum of two (2) weeks for this authorization to be processed. A new authorization is required for each new (unique) disability claim.
Please print clearly in black or blue ink, or complete online. Remember to sign and date this form or it will not be valid. The member's signature and date (MM/DD/YYYY) are required.
Election of Direct Deposit: you must sign and date this form to make any change (choose one): New disability benefits direct deposit; Change from my current financial institution to the financial institution listed; I am staying with my financial institution, but my account information has changed; Cancel my direct deposit and send my checks to my home address listed.
Fill out this section to begin or change your direct deposit. If you are canceling your direct deposit, leave this section blank.
Choose one type of account, Savings or Checking, and write the effective date (MM/DD/YYYY), routing # (9 digits) and account #. The financial institution's authorizing signature is required.
For banks in foreign countries or banks that do not accept direct deposit: Your check will be mailed directly to your home address.
More rules for Notice and Proof of Claim for Disability Benefits (1199SEIU National Benefit Fund, 3NBF343 06/20)
Make a copy of this completed form for your records before you submit it to the 1199SEIU National Benefit Fund.
Any person who knowingly and with intent to defraud any insurance company files a statement of claim containing any materially false information, or conceals for the purpose of misleading information concerning any fact material thereto, commits a fraudulent insurance act, which is a crime.
The Worker's Compensation Board (WCB) will not disclose any information about your case to any unauthorized party without your consent. If you choose to have such information disclosed to any unauthorized party, you must file with the board an original signed Form OC-110A, Claimant's Authorization to Disclose Workers' Compensation Records, or an original signed, notarized authorization letter.
Where to get help with Notice and Proof of Claim for Disability Benefits (1199SEIU National Benefit Fund, 3NBF343 06/20)
If you have any questions about claiming disability benefits, contact the nearest office of the New York State Workers' Compensation Board or write to: Workers' Compensation Board, Disability Benefits Bureau, 100 Broadway-Menands, Albany, NY 12241.
Sources
[1] Notice and Proof of Claim for Disability Benefits, 1199SEIU National Benefit Fund (the Official source link on this page).