


Request for SUM Arbitration or UM Arbitration at a glance
What it is: American Arbitration Association New York State SUM/UM Arbitration Tribunals: request for SUM arbitration or UM arbitration, choose one only.
Who signs: Sign under Signed (May be Signed by a Representative).
The filing party, a party to an insurance policy providing for protection against loss due to personal injuries sustained in accidents involving uninsured, underinsured or hit-and-run motorist that provides for arbitration of disputes in accordance with the rules of the American Arbitration Association, hereby demands arbitration.
A filled-in Request for SUM Arbitration or UM Arbitration example: a request for UM arbitration after a hit-and-run

How to fill out Request for SUM Arbitration or UM Arbitration, box by box
To the Respondent
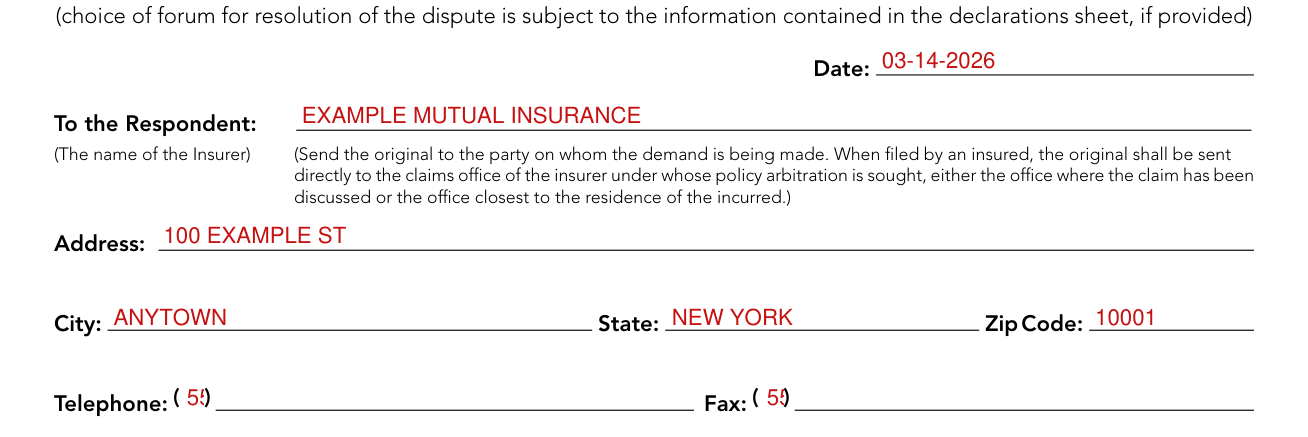
Enter the Date and, after To the Respondent, the name of the Insurer. Send the original to the party on whom the demand is being made. When filed by an insured, the original shall be sent directly to the claims office of the insurer under whose policy arbitration is sought, either the office where the claim has been discussed or the office closest to the residence of the incurred.
Enter the Address, City, State, Zip Code, Telephone and Fax.
Notice to the Respondent: pursuant to § 7503 (c) of the Civil Practice Law and Rules, unless, within twenty (20) days after service of this Demand for Arbitration or Notice of Intention to Arbitrate, the Respondent apply to stay arbitration, the Respondent will thereafter be precluded from objecting that a valid agreement was not made or has not been complied with and from asserting in court the bar of a limitation of time.
The Issuing Company, the policyholder and the claim
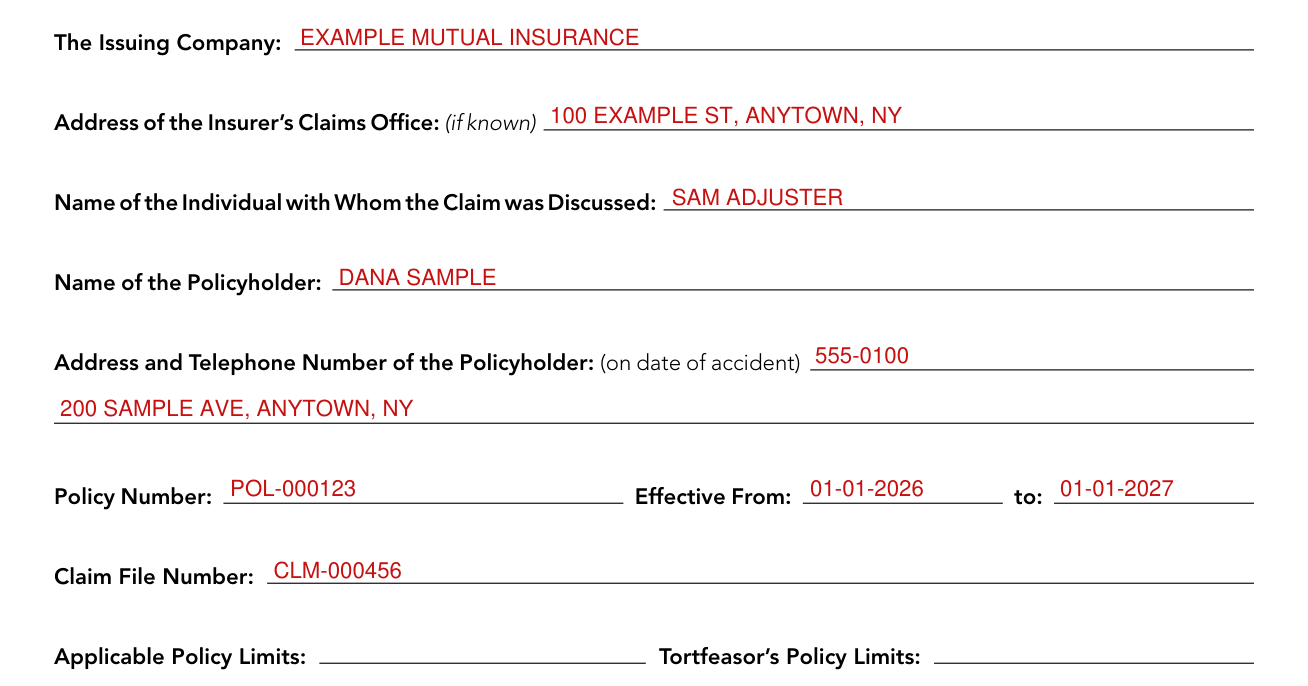
Enter the Issuing Company, the Address of the Insurer's Claims Office (if known) and the Name of the Individual with Whom the Claim was Discussed.
Enter the Name of the Policyholder and the Address and Telephone Number of the Policyholder (on date of accident).
Enter the Policy Number, Effective From and to, the Claim File Number, the Applicable Policy Limits and the Tortfeasor's Policy Limits.
Name(s) of Applicant(s) and Amount Claimed

Under Name(s) of Applicant(s), enter each name, Check if a minor and enter the Amount Claimed.
Enter the Name of Legal Representative if Applicant is a minor or incompetent.
Date of the Accident and Location

Enter the Date of the Accident and Location. Mark Uninsured, Underinsured or Hit-and-Run.
Under THE NATURE OF DISPUTE AND THE INJURES ALLEGED, attach additional sheets if necessary, although offers of settlement should not be included.
Signed and the Representative

Enter the Name, Address, Telephone and Facsimile Number of the Representative and the Name, Address, Telephone and Facsimile Number for the Applicant.
More rules for Request for SUM Arbitration or UM Arbitration
Choose One Only: SUM arbitration or UM arbitration. Choice of forum for resolution of the dispute is subject to the information contained in the declarations sheet, if provided.
Common questions about Request for SUM Arbitration or UM Arbitration
Are there fees?
The original of this demand must be served on the other party by U.S. certified mail-return receipt requested. Three (3) copies of this demand, together with corresponding copies of the endorsement and declarations page, must be filed at 120 Broadway, 11th Floor, New York, NY 10271. A non-refundable administrative fee in the amount of $250 is due and payable at the time of filing this demand (checked November 9, 2026).
Sources
[1] Request for SUM Arbitration or UM Arbitration, American Arbitration Association New York State SUM/UM Arbitration Tribunals (served file; no issuer file found) (the Official source link on this page).